ECG interpretation: simple conceptual guide
An ECG/EKG records the heart’s electrical activity, not its contraction directly.
Think of it like this:
Electricity happens first, then the muscle contracts.
The ECG shows the electrical signal that tells the heart muscle when to contract.
A normal electrical route is:
SA node → atria → AV node → His bundle → bundle branches → Purkinje fibers → ventricles
- SA node starts the impulse.
- The impulse spreads through atria: atria contract.
- It pauses briefly in the AV node so ventricles can fill.
- It then travels very rapidly through the ventricular conducting system: ventricles contract.
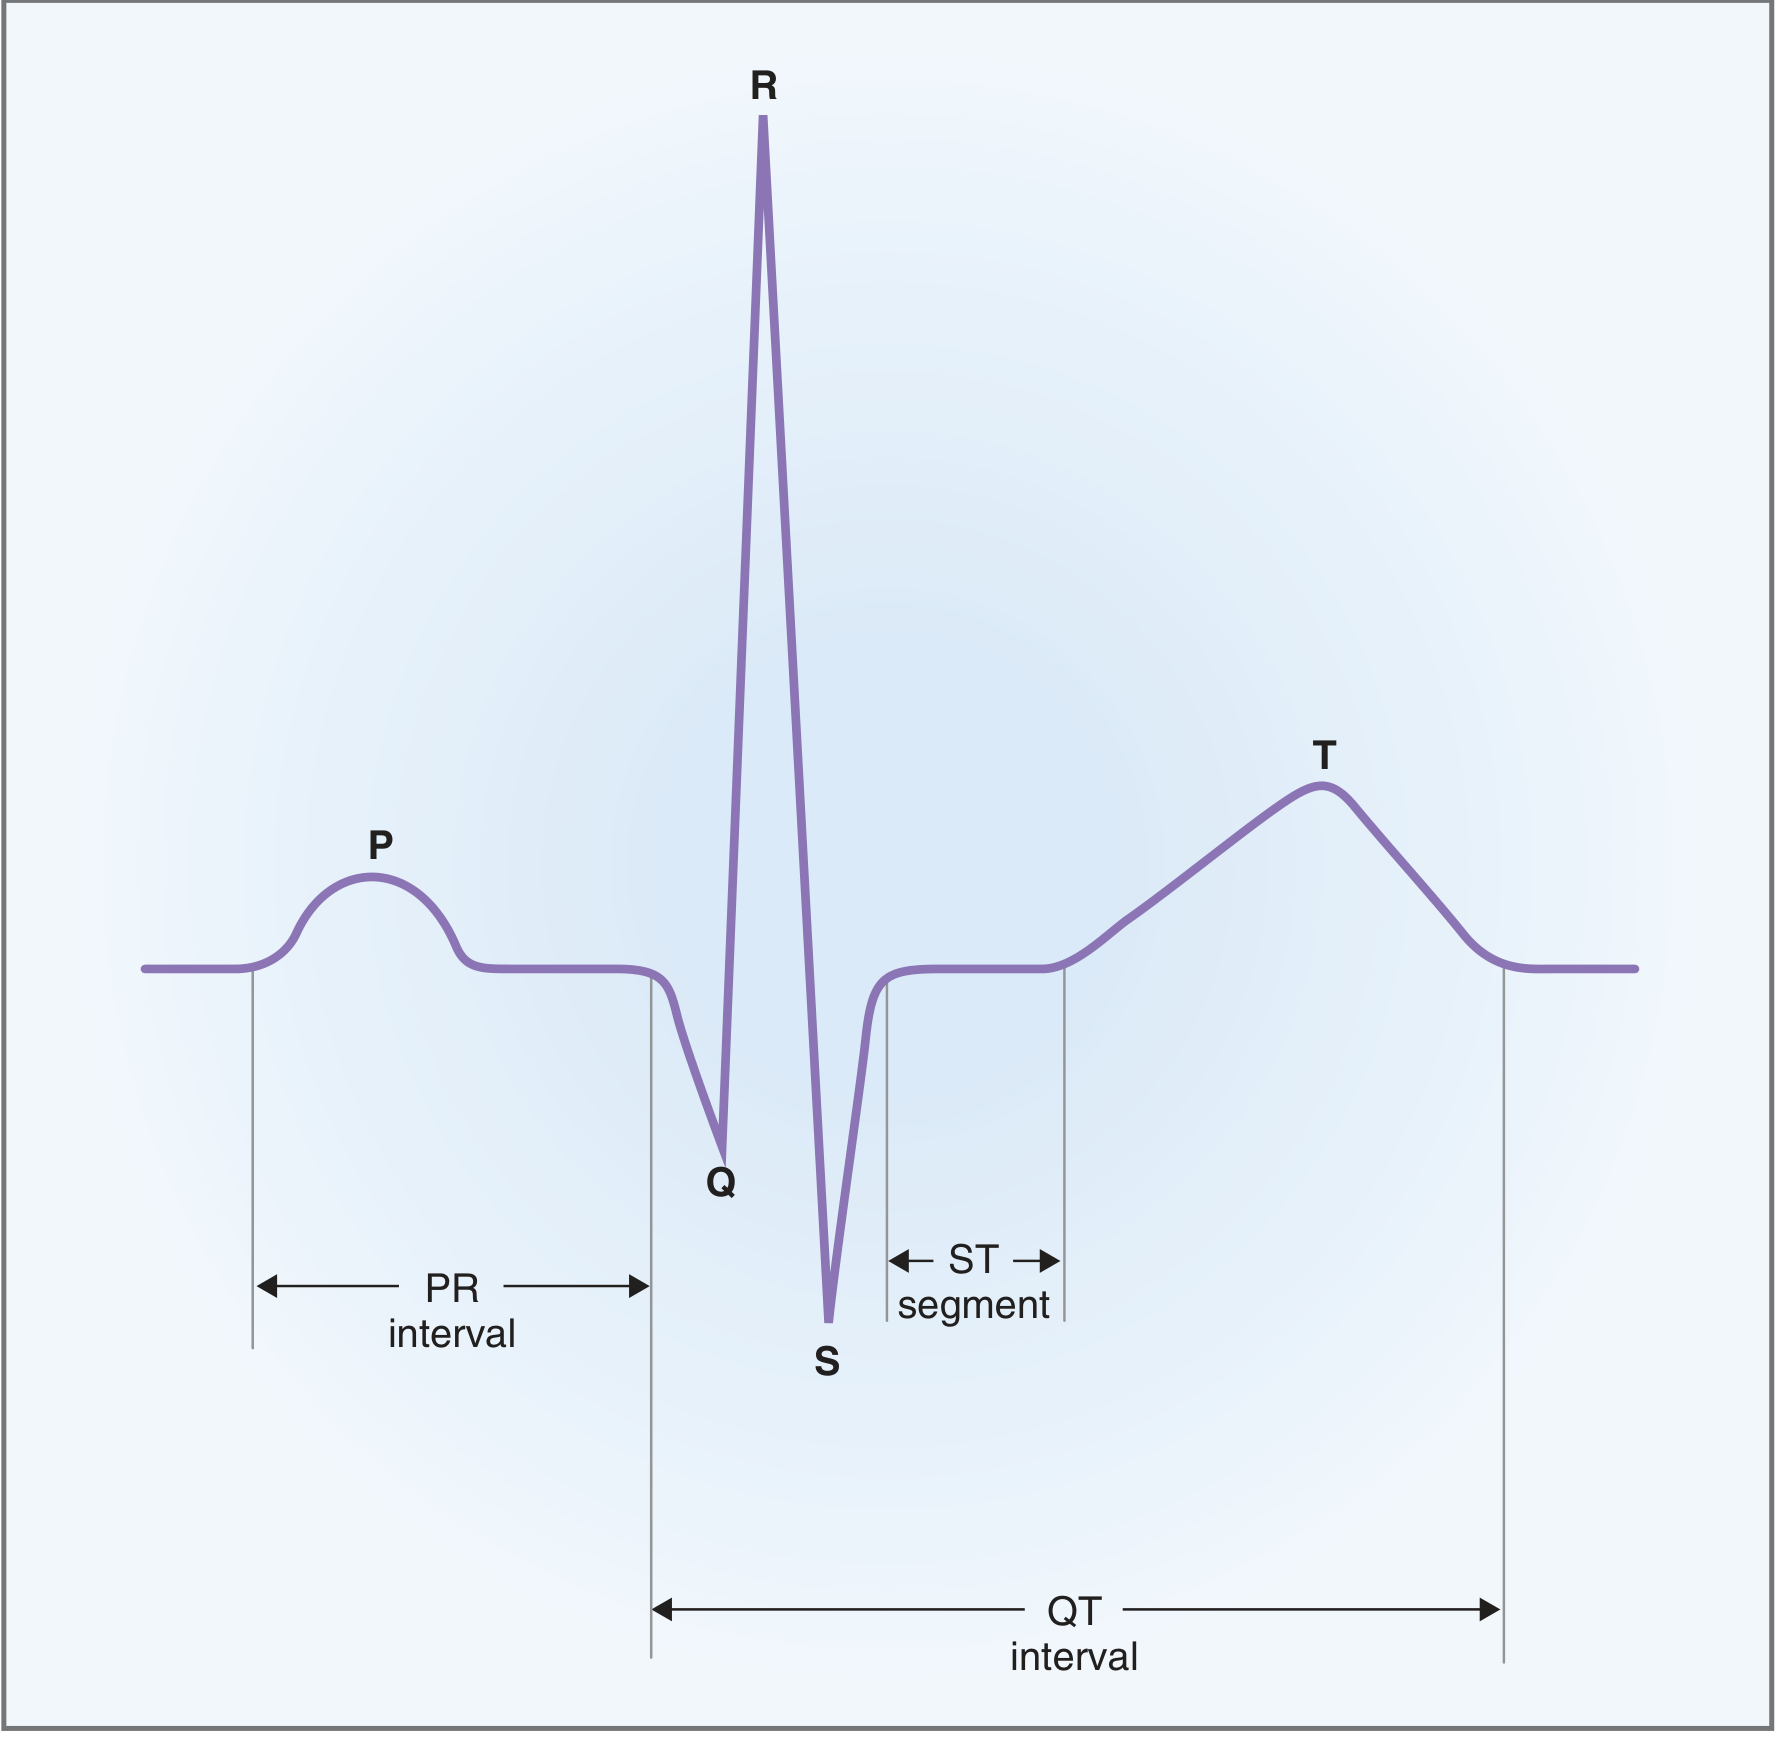
Normal ECG graph
                    QRS complex
                       /\
                      /  \
         P           /    \                         T
        /\          /      \                       /\
_______/  \________/        \_____________________/  \_______
       |<--- PR --->|         |<-- ST -->|
       |                            |
       |<--------- QT interval ---->|

       P        Q R S        T
       atrial   ventricular  ventricular
       depol.   depolarization repolarization
A more detailed labelled reference image from Costanzo Physiology is shown below.
1. Why do ECG waves go upward or downward?
An ECG lead is like a camera looking at the heart from one direction.
- Electrical activity moving toward the positive electrode produces an upward deflection.
- Electrical activity moving away from the positive electrode produces a downward deflection.
- Activity moving perpendicular to the lead may appear small or biphasic.
For example, in lead II, the main electrical direction usually travels toward the left leg electrode. Therefore, the P wave, QRS complex, and T wave are usually upright in lead II.
2. The waves and their meaning
A. P wave: atrial depolarization
       P wave
        /\
_______/  \_______
What it represents
Electrical activation, or depolarization, of both atria.
- First, right atrium depolarizes.
- Then left atrium depolarizes.
- Mechanical atrial contraction follows shortly after the P wave.
Normal value
- Duration: < 0.12 s or <3 small squares
- Height in lead II: usually < 2.5 mm
Importance
It tells you about:
- Origin of rhythm
- Atrial size
- Atrial conduction
- Relationship between atria and ventricles
Normal sinus rhythm requires
- A P wave before every QRS.
- Every P wave followed by a QRS.
- P waves look similar.
- P wave is usually upright in leads I, II, and aVF.
- Rhythm is regular or mildly variable with breathing.
Abnormal clues
- Tall, peaked P wave: possible right atrial enlargement
- Wide, notched P wave: possible left atrial enlargement
- No visible P waves: consider atrial fibrillation
- Inverted P wave in lead II: possible junctional rhythm or ectopic atrial rhythm
B. PR segment: AV nodal delay
P wave      PR segment
 /\              ______
/  \____________/
The PR segment is the flat part after the P wave and before QRS.
Why is it flat?
The impulse is passing slowly through the AV node and then His bundle. There is little net electrical movement visible on the body surface, so the line is nearly flat.
Why is AV nodal delay useful?
It gives the atria time to finish emptying blood into the ventricles before the ventricles contract.
The AV node is the heart’s “traffic signal.”
C. PR interval: atria-to-ventricle conduction time
|<--------- PR interval --------->|
        P wave + PR segment
_______/\____________________QRS____
Measurement
From the beginning of P wave to the beginning of QRS complex.
Normal value
- 0.12 to 0.20 s
- 120 to 200 ms
- 3 to 5 small squares at standard paper speed
What it represents
Total conduction time from atrial depolarization to the start of ventricular depolarization. It includes conduction through:
- Atria
- AV node
- His bundle
- Bundle branches
The AV nodal delay makes up the largest portion.
Importance of PR interval
| PR finding | Meaning | Common examples |
|---|
| Short PR <120 ms | Impulse reaches ventricle unusually quickly | Pre-excitation such as Wolff-Parkinson-White syndrome, junctional rhythm |
| Long PR >200 ms | Delayed AV conduction | First-degree AV block, high vagal tone, AV nodal drugs |
| Progressively longer PR, then dropped QRS | AV conduction progressively fails | Mobitz I / Wenckebach |
| Fixed PR with occasional dropped QRS | Intermittent serious conduction failure | Mobitz II |
| No relationship between P and QRS | Atria and ventricles beat independently | Complete heart block |
A normal PR interval is generally
120-200 ms, and a persistent PR >200 ms defines first-degree AV block or AV conduction delay, as described in
Goldman-Cecil Medicine.
D. QRS complex: ventricular depolarization
               R
              /\
             /  \
_______Q____/    \____S_______
        \              /
What it represents
Electrical activation of the ventricles.
The ventricles are much larger than the atria, so the QRS complex is much bigger than the P wave.
Although the ventricles are large, the QRS is normally short because the impulse travels extremely fast through the His-Purkinje system.
Important point
Atrial repolarization also occurs around this time, but it is hidden inside the large QRS complex.
What do Q, R, and S mean?
These letters describe the shape, not a specific anatomical location.
- Q wave: first negative deflection before an R wave
- R wave: first positive deflection
- S wave: negative deflection after an R wave
A complex can be:
Positive only:        R
                      /\

Negative only:        QS
                      \/

Positive-negative:    R-S
                      /\__
                         \/
Normal QRS duration
- Usually about 0.07-0.11 s
- A QRS <120 ms is generally considered narrow
- ≥120 ms is wide
Importance of QRS duration
| QRS finding | Meaning |
|---|
| Narrow QRS | Ventricular activation is using the normal conduction system |
| Wide QRS ≥120 ms | Delayed ventricular activation |
| Wide QRS with RBBB/LBBB pattern | Bundle branch block |
| Very wide bizarre QRS | Ventricular rhythm, hyperkalemia, drug toxicity, or pre-excitation may be considered |
Narrow QRS = normal fast ventricular highways are working.
Wide QRS = electricity is taking a slower route through ventricular muscle.
E. ST segment: ventricular plateau phase
QRS ends              T starts
____/\____ _____________/\
          ST segment
What it represents
The time when most ventricular muscle cells are depolarized.
It corresponds approximately to the plateau phase, phase 2, of the ventricular action potential.
Normal appearance
The ST segment should usually be near the baseline, called the isoelectric line.
Importance
| ST finding | Possible meaning |
|---|
| ST elevation in contiguous leads | Acute myocardial injury, including STEMI; also pericarditis, early repolarization, aneurysm, etc. |
| ST depression | Subendocardial ischemia, reciprocal changes, digoxin effect, strain pattern, other causes |
| Concave diffuse ST elevation with PR depression | Supports acute pericarditis in the right clinical setting |
ST changes must be interpreted with symptoms, serial ECGs, troponin testing, and the specific leads involved. An ECG cannot diagnose every cause by itself.
F. T wave: ventricular repolarization
                 T wave
                  /\
_________________/  \____________
What it represents
Ventricular repolarization, meaning the ventricles electrically recover and prepare for the next beat.
Why is the T wave often upright even though it is repolarization?
Repolarization travels in the opposite physical direction to depolarization, but repolarization has opposite electrical polarity. The two “opposites” make an upright T wave in leads where QRS is upright.
This is a common confusing point:
Depolarization toward a lead gives an upward wave.
Repolarization moving away from that lead can also give an upward wave because its polarity is reversed.
Normal T wave
- Usually upright in leads I, II, and V3-V6
- Often variable in lead III, aVL, and V1
- Usually asymmetric: slower upstroke and faster downstroke
Importance
| T-wave pattern | Possible significance |
|---|
| Tall, narrow, peaked T waves | Hyperkalemia, early ischemic changes |
| Deep symmetrical T-wave inversion | Ischemia, ventricular strain, CNS events, other causes |
| Flattened T waves | Hypokalemia, nonspecific change |
| Biphasic T waves | Ischemia or electrolyte abnormality may be considered |
G. U wave: sometimes seen after T wave
      T          U
     /\         /\
____/  \_______/  \______
What it may represent
Its exact source is not fully settled, but it may relate to late repolarization of the Purkinje system or ventricular structures.
Clinical importance
- Small U waves can be normal.
- Prominent U waves may occur in hypokalemia, bradycardia, or with some antiarrhythmic drugs.
- A negative U wave can be abnormal and may suggest ischemia or hypertension.
3. ECG intervals and segments: values and importance
Intervals versus segments
- An interval includes at least one wave.
- A segment is the flat part between waves.
PR interval = P wave + PR segment
QT interval = QRS complex + ST segment + T wave
| Feature | Measure from | Measure to | Normal adult value | Importance |
|---|
| P-wave duration | Start of P | End of P | <120 ms | Atrial conduction and atrial enlargement |
| PR interval | Start of P | Start of QRS | 120-200 ms | Atria-to-ventricle conduction, especially AV nodal conduction |
| PR segment | End of P | Start of QRS | Normally isoelectric | AV nodal delay; PR depression may support pericarditis |
| QRS duration | Start of Q/R | End of S | Usually 70-110 ms; <120 ms | Ventricular depolarization and intraventricular conduction |
| ST segment | J point, end of QRS | Beginning of T | Usually isoelectric | Myocardial ischemia/injury, pericarditis, electrolyte/drug effects |
| QT interval | Start of QRS | End of T | Depends on heart rate | Total ventricular depolarization plus repolarization |
| QTc | Corrected QT | Corrected for heart rate | Usually <450 ms in men and <460 ms in women | Risk assessment for torsades de pointes when prolonged |
| RR interval | One R wave | Next R wave | Depends on rate | Determines rate and rhythm regularity |
| PP interval | One P wave | Next P wave | Depends on atrial rate | Determines atrial rate and regularity |
4. QT interval and QTc: why they matter
QT interval
|<----------------- QT interval ---------------->|
      QRS complex + ST segment + T wave
______/\______________________________/ \________
Meaning
From the beginning of ventricular depolarization to the end of ventricular repolarization.
In simple terms:
QT = the total electrical working time of the ventricles.
QT gets naturally shorter at faster heart rates and longer at slower heart rates. Therefore, use QTc, the QT corrected for heart rate.
Common QT correction formula
QTc = QT / √RR
- QT and RR are measured in seconds.
- This is the Bazett formula.
- Bazett correction can overestimate QTc at fast rates and underestimate it at slow rates.
Prolonged QTc
A practical adult threshold is:
- >450 ms in men
- >460 ms in women
- ≥500 ms: substantially higher concern for torsades de pointes
Causes of long QT
- Congenital long-QT syndrome
- Low potassium, magnesium, or calcium
- Antiarrhythmic drugs
- Some antipsychotics, antidepressants, antibiotics, and antiemetics
- Bradycardia
- Myocardial ischemia
Why it matters
A prolonged QTc can predispose to
torsades de pointes, a potentially dangerous polymorphic ventricular tachycardia. QT measurement and correction are discussed in
Goldman-Cecil’s ECG guidance.
5. RR interval and heart-rate calculation
Standard ECG paper
At the usual paper speed of 25 mm/s:
1 small square = 0.04 seconds = 40 ms
1 large square = 0.20 seconds = 200 ms
5 large squares = 1 second
Vertical calibration is usually:
10 mm = 1 mV
Regular rhythm: 300 method
Heart rate = 300 / number of large squares between R waves
| Large squares between R waves | Heart rate |
|---|
| 1 | 300/min |
| 2 | 150/min |
| 3 | 100/min |
| 4 | 75/min |
| 5 | 60/min |
| 6 | 50/min |
Regular rhythm: 1500 method
Heart rate = 1500 / number of small squares between R waves
Irregular rhythm
Count QRS complexes in a 10-second strip and multiply by 6.
Rate = QRS complexes in 10 seconds × 6
6. A systematic method to interpret a 12-lead ECG
Use the same sequence every time.
Step 1: Check calibration and quality
- Correct patient and date?
- Standard speed: 25 mm/s?
- Standard gain: 10 mm/mV?
- Is there artifact or lead misplacement?
Step 2: Calculate heart rate
- Normal resting adult sinus rate: 60-100/min
- <60/min: bradycardia
-
100/min: tachycardia
Step 3: Assess rhythm
Ask:
- Are R-R intervals regular?
- Is there a P wave before every QRS?
- Is every P wave followed by a QRS?
- Is PR interval constant?
If yes, it is likely sinus rhythm.
Step 4: Look at P waves
- Are they upright in lead II?
- Are they too tall or wide?
- Are they absent, irregular, or abnormal in shape?
Step 5: Measure PR interval
- 120-200 ms is normal.
- Short or long PR suggests a conduction issue.
Step 6: Measure QRS duration
- Narrow or wide?
- Look for bundle branch block pattern.
- Look for pathological Q waves.
Step 7: Determine electrical axis
A quick screening method:
| Lead I | Lead aVF | Approximate axis |
|---|
| Positive | Positive | Normal axis |
| Positive | Negative | Left axis deviation possible |
| Negative | Positive | Right axis deviation possible |
| Negative | Negative | Extreme axis deviation |
Step 8: Assess ST segment, T waves, and U waves
- ST elevation or depression?
- T-wave inversion, flattening, or peaking?
- U wave present?
Step 9: Measure QTc
Check especially if there is syncope, electrolyte disturbance, or QT-prolonging medication.
Step 10: Compare with old ECG and clinical picture
An ECG is interpreted alongside:
- Chest pain or syncope
- Blood pressure and pulse
- Electrolytes
- Cardiac biomarkers
- Echocardiography or imaging when appropriate
7. Normal sinus ECG: quick summary
Normal sinus rhythm:

Rate:          60-100/min
P wave:        one P before every QRS; upright in lead II
PR interval:   120-200 ms
QRS duration:  <120 ms
ST segment:    near baseline
QTc:           usually <450 ms in men, <460 ms in women
8. Best memory map
P wave      = atrial depolarization
PR interval = atria to ventricles, mainly AV nodal delay
QRS complex = ventricular depolarization
ST segment  = ventricles are fully depolarized
T wave      = ventricular repolarization
QT interval = whole ventricular electrical activity
RR interval = ventricular rate and rhythm
Or remember:
P prepares the atria.
PR pauses at the AV node.
QRS activates the ventricles.
ST is the ventricular plateau.
T resets the ventricles.
QT is the ventricles’ total electrical working time.
The ECG reflects the ordered sequence of atrial then ventricular depolarization and repolarization, as outlined in Costanzo Physiology, 7th Edition, Electrocardiogram section.