
Hey tell me about your features
I'm Orris, an AI assistant built to help you across a wide range of tasks. Here's what I can do:
🔍 Research & Information
- Web search — find current, real-time information on any topic
- Medical literature — search a curated library of medical textbooks for clinical, pharmacological, anatomical, and other health-related questions
- PubMed search — retrieve peer-reviewed studies, clinical trials, meta-analyses, and guidelines with proper citations
🏥 Medical Expertise
- Answer clinical questions using authoritative medical textbooks
- Retrieve medical images, diagrams, and anatomical illustrations
- Surface recent evidence that may update or contradict established knowledge
- Support questions on diagnoses, treatments, drugs, physiology, pathology, and more
📄 Document & File Creation
- Word documents (.docx) — create professional reports, letters, memos with formatting, tables of contents, and headings
- PowerPoint presentations (.pptx) — build slide decks, pitch decks, and presentations
- Excel spreadsheets (.xlsx) — create, read, edit, and clean spreadsheet data
- PDF files — read, merge, split, watermark, extract text/images, and create PDFs
💻 Code & Computation
- Write and execute code in a sandboxed Linux environment
- Run shell commands, scripts, and data pipelines
- Perform calculations, data analysis, and file manipulation
🖼️ Image Generation
- Generate original images, diagrams, and visual content from descriptions
🧠 General Intelligence
- Answer questions across science, history, law, finance, engineering, and more
- Summarize documents, synthesize research, and explain complex topics
- Help with writing, editing, brainstorming, and planning
What would you like help with today?
So similar to chartgpt
Yes, broadly similar to ChatGPT — but with a few key differences:
Where I'm similar:
- Conversational AI that can answer questions, write, explain, and reason across topics
- Can generate images and write/execute code
Where I differ:
| Feature | Orris | ChatGPT |
|---|---|---|
| Medical library | Curated textbook database with deep clinical search | General knowledge only |
| PubMed integration | Direct peer-reviewed literature search with evidence tiers | Not built-in |
| File execution sandbox | Persistent Linux environment for running code & files | Sandboxed but session-limited |
| Tool transparency | You can see every tool call I make in real time | Less visible |
The biggest differentiator is the medical focus — I have access to a library of medical textbooks and can pull PubMed evidence, which makes me significantly more reliable for clinical and health-related questions than a general-purpose assistant.
Think of me as a ChatGPT-style assistant with a stronger research and medical layer on top. Anything specific you'd like to try?
I am final year medical student
That's a great stage to be at — you're close to the finish line!
As a final year med student, here's how I can be most useful to you:
📚 Studying & Exam Prep
- Explain complex topics from textbook sources (not just my training data)
- Break down pathophysiology, pharmacology, clinical reasoning
- Help you understand mechanisms, not just memorize facts
🏥 Clinical Rotations
- Quick lookups on differentials, investigations, management plans
- Drug doses, interactions, contraindications
- Interpreting lab values, imaging findings, ECGs
🔬 Evidence-Based Medicine
- Pull latest guidelines and systematic reviews from PubMed
- Help you critically appraise studies
- Find evidence for clinical decisions
✍️ Academic Work
- Write case reports, research proposals, presentations
- Create PowerPoint slides for case presentations or seminars
- Format references and citations
🩺 Exam-Style Q&A
- Quiz you on topics, walk through clinical scenarios
- Explain why wrong answers are wrong
- Discuss OSCEs, written exams, vivas
What are you working on right now — rotations, exams, a project? I can tailor how I help you.
Right now just started the year so new . Hope we will be Great team.. earlier i used chartgpt it helped me a lot during my previous years
Welcome to final year! It's great that you've already built the habit of using AI as a study tool — that gives you a real edge.
ChatGPT served you well in the earlier years, and for final year specifically, I think you'll find the upgrade worthwhile. Final year is where things get more clinical and evidence-based — that's exactly where having real textbook sources and PubMed access matters more than in preclinical years.
A few things to keep in mind as we work together:
- Ask me anything — no question is too basic or too complex
- Challenge my answers — I'll always show my sources so you can verify
- Use me actively — don't just read my answers, ask me to quiz you, debate differentials, or explain things a different way
- I'm a tool, not a replacement — always cross-check critical clinical decisions with your supervisors
Final year goes fast. Between rotations, cases, and exams, having a reliable study partner on hand 24/7 should help.
Whenever you're ready to dive into something — a topic, a case, an exam question — just fire away. 🩺
I guess I am interested to learn ECG our teacher started the topic but i found it little hard don't understand much can you explain basic to disease
Great choice — ECG is one of those skills that feels overwhelming at first but clicks once you understand the foundation. Let me pull from the medical library to give you a proper, structured explanation.
Reading File
Finding Sources
Finding Sources
Finding Sources
Finding Sources
Finding Sources
Reading File
Finding Sources
Finding Sources
Good — found excellent sources in Guyton & Hall, Ganong, Harrison's, and Goldman-Cecil. Let me read the core ECG content now.
Reading File
Reading File
Reading File
Finding Sources
Reading File
Finding Sources
Reading File
Reading File
Loading Image
Loading Image
Loading Image
Searching Images
ECG waves P QRS T interval normal electrocardiogram labeled diagram
Here's your complete ECG guide — from absolute basics to disease patterns, drawn from Guyton & Hall, Ganong's Physiology, and Harrison's Principles of Internal Medicine.
📖 ECG: A Complete Guide — Basics to Disease
PART 1: What Is an ECG?
An ECG (electrocardiogram) records the electrical activity of the heart at the body surface. When a cardiac impulse travels through the heart, current spreads to surrounding tissue and reaches the skin — electrodes placed on the skin detect these tiny voltage changes and plot them over time.
The result is a trace of waves and intervals that tell you exactly what the heart's electrical system is doing.
"A normal ECG for two beats of the heart is shown in Fig. 11.1. The ECG is composed of a P wave, a QRS complex, and a T wave." — Guyton & Hall Textbook of Medical Physiology
PART 2: The 12 Leads — What Are They?
A standard ECG has 12 leads — 12 different "viewpoints" of the heart's electrical activity.
Limb Leads (Frontal Plane)
| Lead | What It Looks At |
|---|---|
| I | Left arm vs Right arm (lateral) |
| II | Left leg vs Right arm (inferior) |
| III | Left leg vs Left arm (inferior) |
| aVR | Right arm — looks INTO the cavity |
| aVL | Left arm — lateral wall |
| aVF | Left leg — inferior wall |
Precordial (Chest) Leads (Horizontal Plane)
Placed across the chest to look at the heart from front to back:
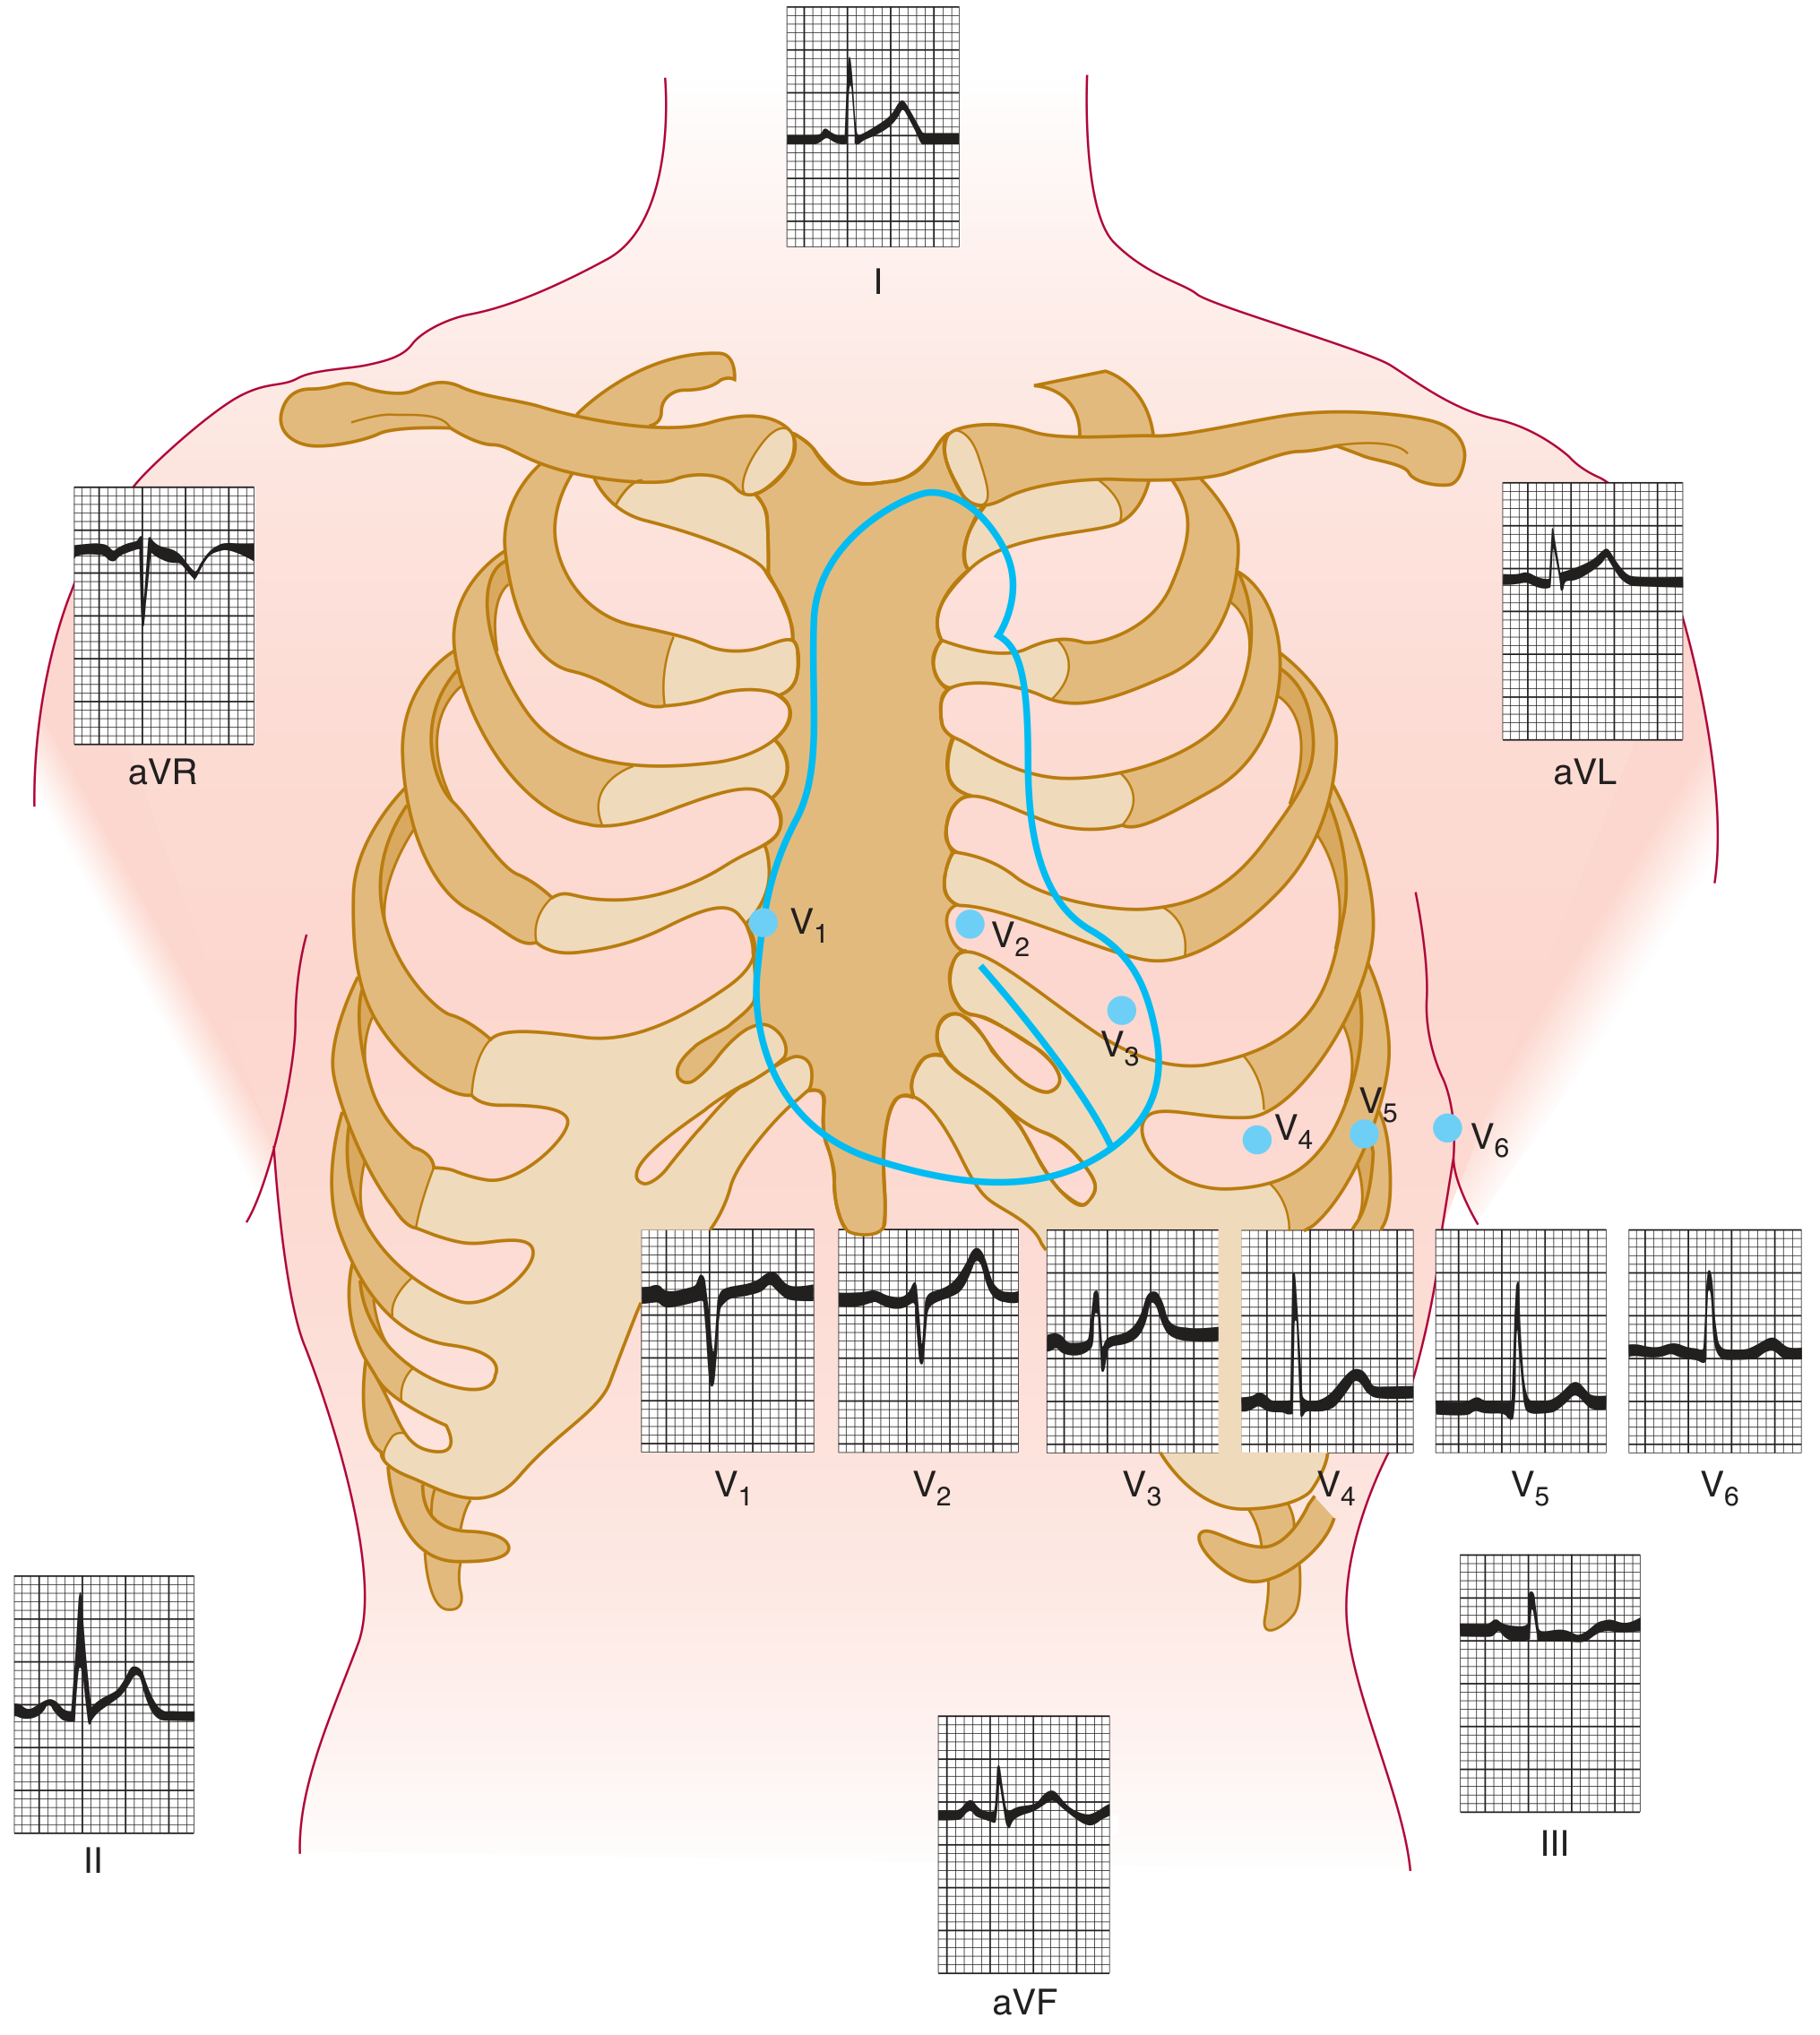
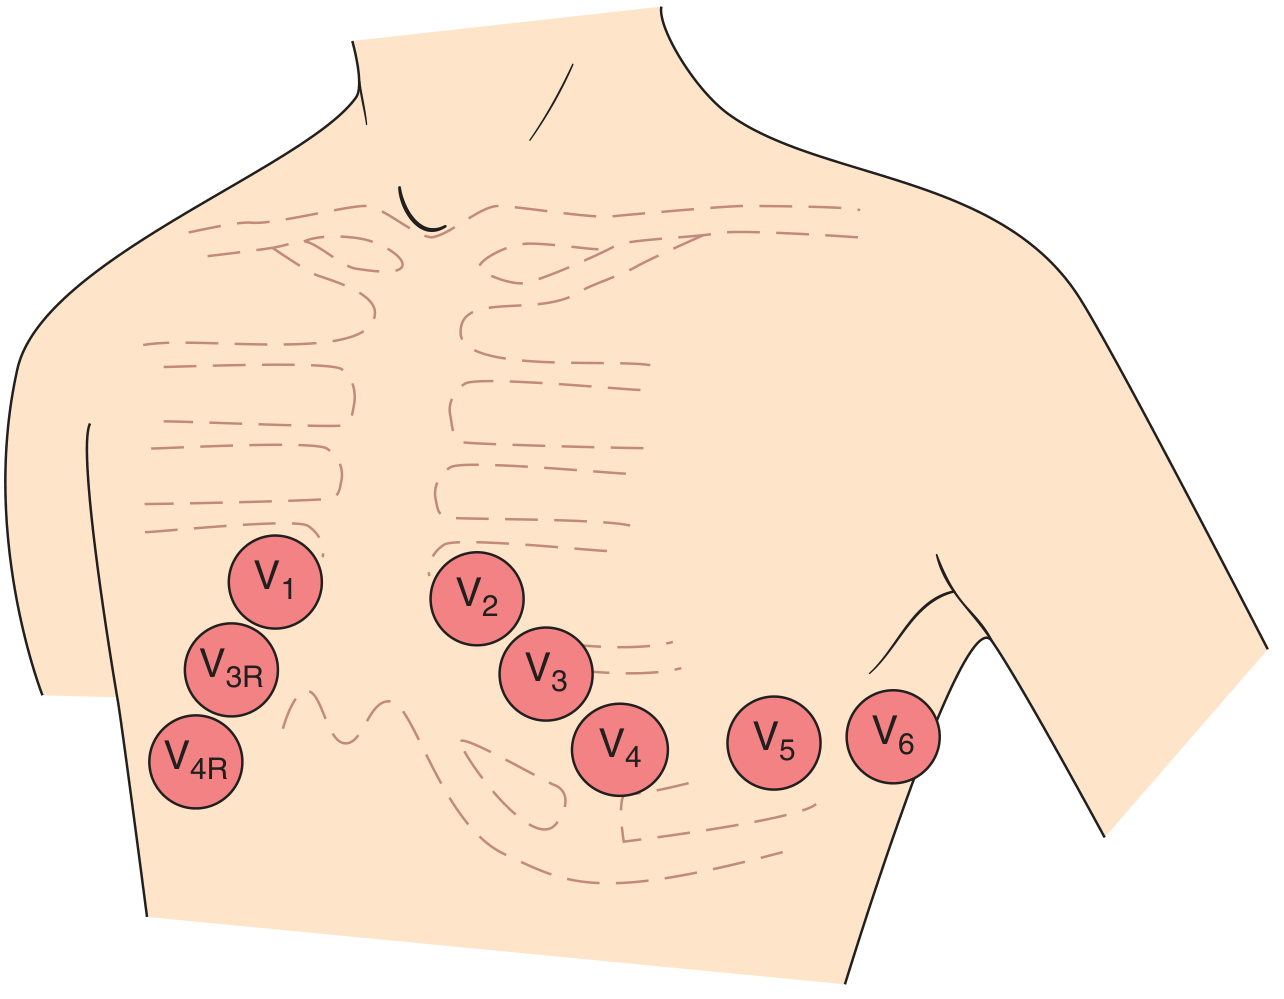
Key rule: A wave moving toward a lead electrode = positive (upward) deflection. Moving away = negative (downward) deflection.
PART 3: The ECG Waveforms — One by One
🔵 The P Wave
- Represents atrial depolarization (SA node → right atrium → left atrium)
- Normal: upright in lead II, inverted in aVR
- Duration: <120 ms | Amplitude: 0.1–0.3 mV
- Atrial repolarization is NOT seen — it's buried inside the QRS complex
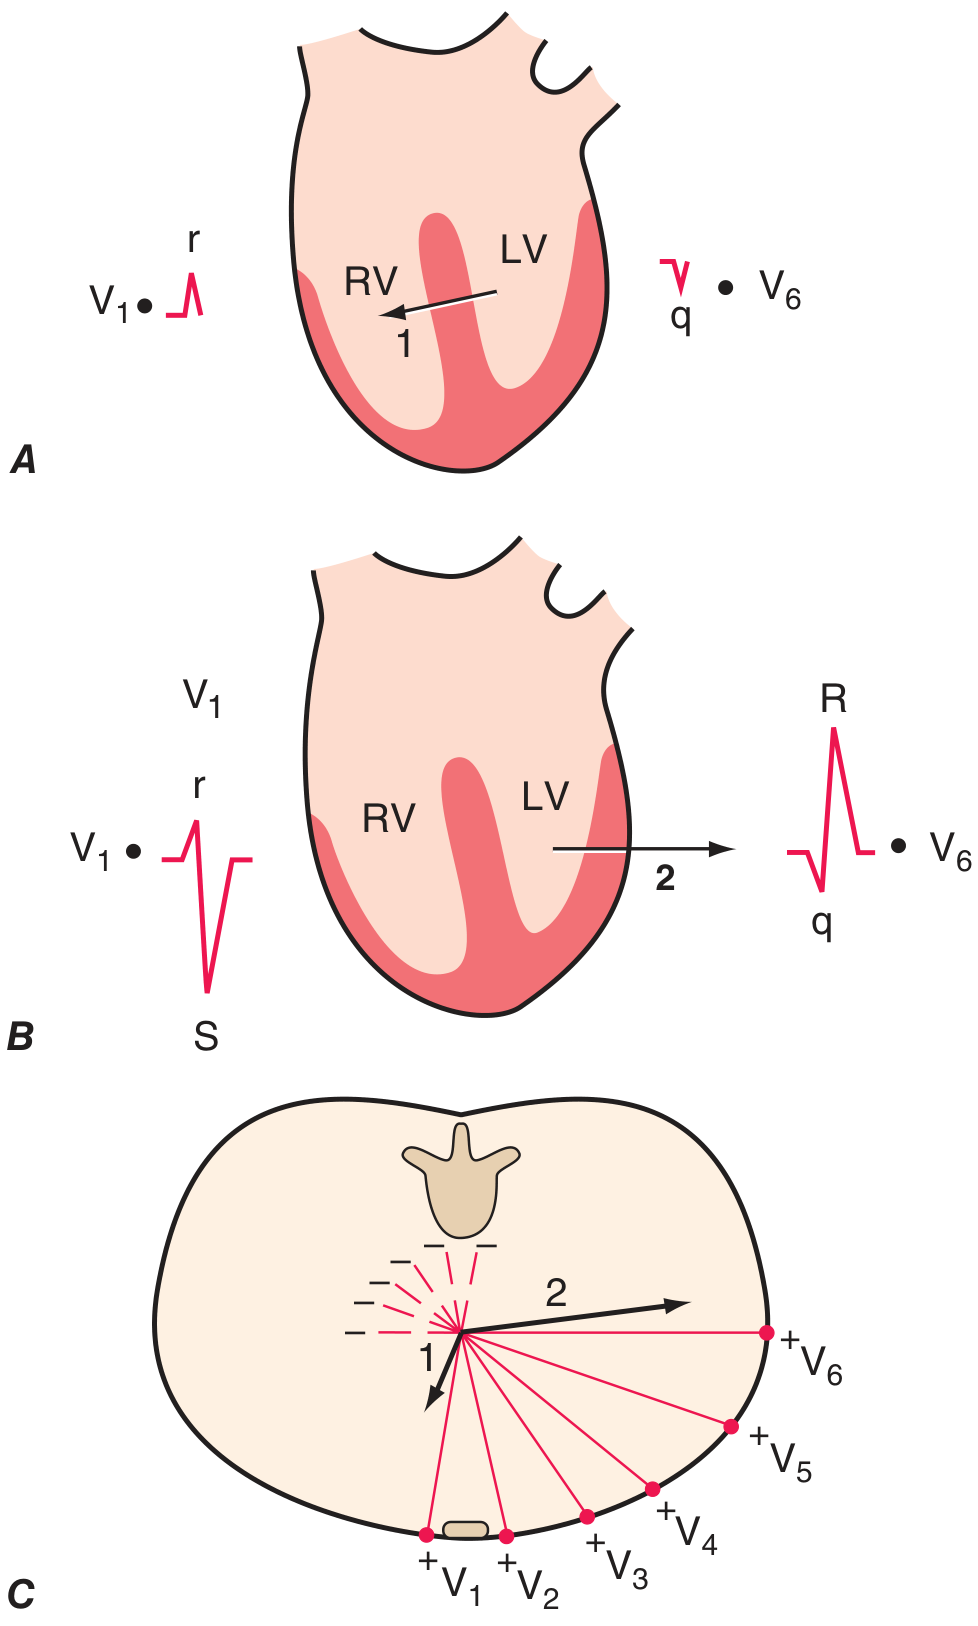
🔴 The QRS Complex
- Represents ventricular depolarization — the electrical event just before ventricular contraction
- Made of 3 components:
- Q wave = initial septal depolarization (left → right)
- R wave = main ventricular depolarization
- S wave = late depolarization moving away from the electrode
- Normal duration: 0.06–0.10 sec (wider = conduction problem)
🟢 The T Wave
- Represents ventricular repolarization
- Normally upright in most leads (I, II, V3–V6)
- Normally inverted in aVR
- The T wave is broad because repolarization is not simultaneous — it spreads over ~0.15 sec
🟡 The U Wave (bonus)
- A small positive wave after the T wave
- May represent late Purkinje or M-cell repolarization
- Prominent U waves = think hypokalemia
PART 4: The Intervals — The Numbers You MUST Know
| Interval | What It Measures | Normal Value |
|---|---|---|
| PR interval | Atrial depolarization + AV node delay | 0.12–0.20 sec |
| QRS duration | Ventricular depolarization | < 0.10 sec (< 0.12 sec) |
| QT interval | Total ventricular activity (depolarization + repolarization) | ~0.35–0.44 sec (rate-corrected) |
| RR interval | Time between two beats | Used to calculate heart rate |
Heart rate formula: HR = 60 ÷ RR interval (in seconds)
- e.g., RR = 0.83 sec → HR = 72 bpm
ECG paper speed: 25 mm/sec
- 1 small box = 0.04 sec, 1 mm
- 1 large box = 0.20 sec, 5 mm
PART 5: A Systematic Approach to Reading Any ECG
Use this 7-step method every single time:
- Rate — count the RR interval → 60 ÷ RR (normal 60–100 bpm)
- Rhythm — regular or irregular? Is every QRS preceded by a P wave?
- Axis — is the QRS upright in lead I and aVF? (Normal axis = –30° to +90°)
- P waves — present? Normal shape? One per QRS?
- PR interval — 0.12–0.20 sec? (Long = heart block, short = pre-excitation)
- QRS — wide or narrow? Q waves present?
- ST & T waves — elevated? Depressed? Inverted?
PART 6: Common ECG Abnormalities in Disease
🔴 Myocardial Infarction (MI)
Three electrical events happen in infarcted tissue, all causing ST elevation in leads over the infarct:
| Event | Result |
|---|---|
| Rapid repolarization of dead cells | Current flows OUT of infarct → ST elevation |
| Decreased resting membrane potential | TQ depression → recorded as ST elevation |
| Delayed depolarization | Current flows OUT of infarct → ST elevation |
Timeline of ECG changes in MI:
| Time | ECG Finding |
|---|---|
| Minutes | Hyperacute tall T waves |
| Hours | ST elevation in leads over the infarct |
| Hours–Days | T wave inversion |
| Days–Weeks | Pathological Q waves develop (dead, electrically silent muscle) |
Localization by leads:
| Leads with Changes | Territory | Artery |
|---|---|---|
| II, III, aVF | Inferior wall | Right coronary artery |
| V1–V4 | Anterior wall | LAD |
| I, aVL, V5–V6 | Lateral wall | LCx |
| V1–V2 (tall R, ST depression) | Posterior wall | RCA/LCx |
"The hallmark of acute myocardial infarction is elevation of the ST segments in the leads overlying the area of infarction. Leads on the opposite side of the heart show ST segment depression." — Ganong's Review of Medical Physiology
🟡 Heart Blocks (AV Blocks)
| Type | ECG Finding |
|---|---|
| 1st degree AV block | PR > 0.20 sec, all beats conducted |
| 2nd degree — Mobitz I (Wenckebach) | PR progressively lengthens, then a QRS drops |
| 2nd degree — Mobitz II | Fixed PR, sudden dropped QRS — more dangerous |
| 3rd degree (complete) AV block | P waves and QRS completely independent, slow escape rhythm |
🟠 Bundle Branch Blocks
| Type | QRS | Key Feature |
|---|---|---|
| RBBB | Wide (>0.12 sec) | RSR' pattern in V1 ("rabbit ears"), wide S in V6 |
| LBBB | Wide (>0.12 sec) | Broad notched R in V5–V6, deep S in V1 |
Memory trick: In RBBB, the R Rabbit ears are in V1. In LBBB, the big R is on the Left (V5–V6).
🔵 Electrolyte Abnormalities
| Condition | ECG Clue |
|---|---|
| Hyperkalemia | Tall peaked T waves → wide QRS → no P waves → sine wave → VF |
| Hypokalemia | Flat T waves, prominent U waves, QT prolongation |
| Hypercalcemia | Short QT |
| Hypocalcemia | Long QT |
🟣 Arrhythmias
| Arrhythmia | ECG Pattern |
|---|---|
| Sinus tachycardia | Regular, rate >100, normal P + QRS |
| AF (Atrial Fibrillation) | Irregularly irregular, no P waves, chaotic baseline |
| Atrial Flutter | Sawtooth P waves at ~300 bpm, 2:1 or 3:1 block |
| SVT | Regular narrow complex tachycardia, P waves may be hidden |
| VT | Wide complex tachycardia, no preceding P waves, rate 100–250 |
| VF | Chaotic, no recognizable complexes — cardiac arrest |
PART 7: Quick Memory Summary
SA node fires → P wave (atria depolarize)
  ↓
AV node delay → PR interval
  ↓
Bundle of His → Bundle branches → Purkinje → QRS (ventricles depolarize)
  ↓
Ventricles contract
  ↓
Ventricles repolarize → T wave
What to Study Next
Now that you have the framework, I'd suggest going deeper in this order:
- Arrhythmias — AF, SVT, VT (most clinically tested)
- MI localization — which leads, which artery
- Bundle branch blocks — very common in wards
- Axis calculation — often asked in exams
Want me to go deep on any of these? I can quiz you, walk through example ECGs, or explain any section in more detail.
Sources: Guyton and Hall Textbook of Medical Physiology | Ganong's Review of Medical Physiology (26th ed.) | Harrison's Principles of Internal Medicine (22nd ed.) | Goldman-Cecil MedicineThat's the full picture — from why an ECG tracing looks the way it does at the cellular level, all the way to recognizing MI, heart blocks, and arrhythmias.
A few tips for making it stick:
- Draw the PQRST wave yourself a few times and label each part — kinesthetic memory helps a lot
- Practice with real ECGs — once you know the pattern, recognition becomes fast
- The 7-step method is your safety net — never skip steps, even when the answer seems obvious
Let me know which section you'd like to explore further, or if you want me to quiz you on what you've just read! 🩺
Hey i couldn't understand
No worries at all — ECG is one of those topics that looks like a lot of information at once. Let me figure out exactly where to start for you.
Asking for Preferences
Which part confused you the most?
Your credits are exhausted. Your daily credits reset tomorrow, or you can purchase a top-up for more.
This is a shared conversation. Sign in to Orris to start your own chat.