
Ectopic atrial rhyghms seen in
Ectopic atrial rhythms arise from foci outside the sinoatrial node firing spontaneously. They are seen in:
- Digitalis toxicity
- Chronic obstructive pulmonary disease (COPD) / cor pulmonale
- Electrolyte disturbances (hypokalemia, hypomagnesemia)
- Structural heart disease (mitral valve disease, cardiomyopathy)
- Hypoxia / hypercapnia
- Alcohol use ("holiday heart")
- Caffeine or stimulant excess
- Post-cardiac surgery
- Rheumatic heart disease
Searching sources...
Reading File
Finding Sources
Finding Sources
Reading File
Reading File
Reading File
Now let me also check for the etiology/causes section in the Family Medicine textbook, which had a very relevant mention of digitalis and lung/heart disease:
Reading File
Loading Image
Here is a complete, textbook-sourced answer on ectopic atrial rhythms:
Ectopic Atrial Rhythms
Definition
An ectopic atrial rhythm is a nonsinus atrial rhythm arising from a single focus outside the sinoatrial (SA) node, producing a single, consistent P wave morphology that differs from normal sinus P waves (i.e., P waves are not upright in leads I, II, and III). Rate is typically <100 bpm but faster than sinus rhythm. When the rate exceeds 100 bpm, it is called ectopic atrial tachycardia.
A wandering atrial pacemaker is a related condition with at least three distinct P wave morphologies at rates between 50-100 bpm, indicating multiple shifting ectopic foci.
- Goldman-Cecil Medicine, p. 566; Textbook of Family Medicine 9e, p. 720
Seen In (Clinical Associations)
| Category | Specific Causes |
|---|---|
| Drug toxicity | Digitalis (digoxin) toxicity - a classic cause |
| Pulmonary/Lung disease | COPD, cor pulmonale, hypoxia, hypercapnia |
| Heart disease | Rheumatic heart disease, cardiomyopathy, mitral valve disease, hypertrophic cardiomyopathy |
| Electrolyte disturbance | Hypokalemia, hypomagnesemia |
| Exogenous stimulants | Caffeine, tobacco, alcohol excess, sympathomimetic drugs |
| Structural/extrinsic | Extrinsic compression of the atrium by adjacent abnormal structures |
| Normal variant | Can be seen in otherwise healthy individuals - often asymptomatic |
| Sick sinus syndrome | SA node abnormally susceptible to suppression by ectopic atrial activity; ectopic rhythms emerge as escape |
- Textbook of Family Medicine 9e, p. 719-720; Bradley and Daroff's Neurology in Clinical Practice
ECG Findings
The P wave morphology is abnormal (not upright in limb leads I, II, III); P-P intervals are approximately equal; QRS is typically narrow unless aberrant conduction is present.
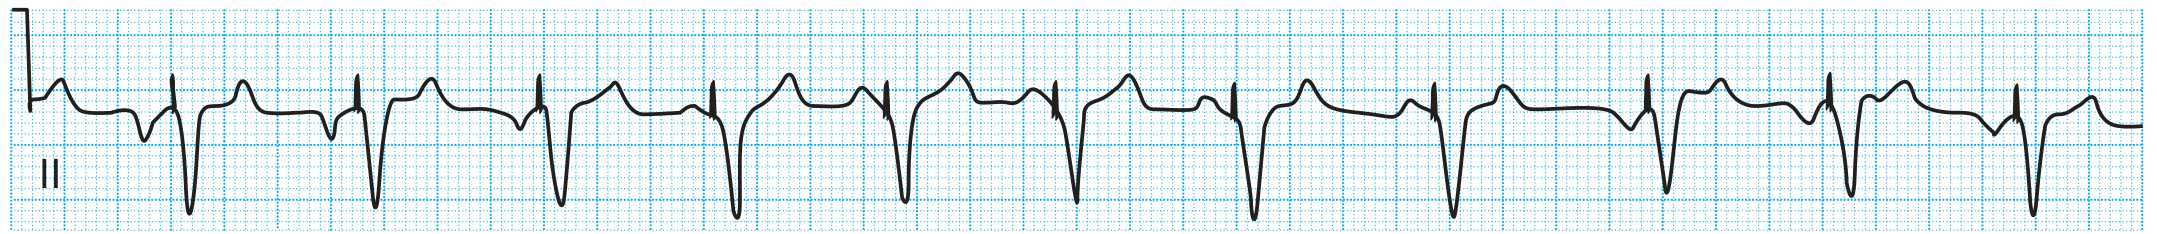
ECG: Ectopic atrial rhythm at 85 beats/min with negative P waves in lead II, replaced by slower sinus rhythm (upright P waves) mid-strip, then returning at the end. - Textbook of Family Medicine 9e, Fig. 27-39
Clinical Features
- Usually asymptomatic - often incidentally found on routine ECG or Holter monitoring
- Rarely, a very slow ectopic rhythm causes fatigue
- Incessant rapid ectopic atrial tachycardia can lead to tachycardia-induced (rate-related) cardiomyopathy
- In Wolff-Parkinson-White (WPW) syndrome or severe structural heart disease (e.g., HCM), a supraventricular arrhythmia can rarely precipitate cardiac arrest
Key Distinction from PACs
Multiple sequential PACs can mimic ectopic atrial rhythm. A consistent P wave morphology and regular P-P intervals distinguish a sustained ectopic atrial rhythm from sequential PACs. - Goldman-Cecil Medicine, p. 566
Treatment
- Asymptomatic: No specific treatment required
- Symptomatic/rapid: Beta-blockers or calcium channel blockers to reduce ectopy and slow ventricular response
- Incessant tachycardia with cardiomyopathy: Class Ia, Ic, or III antiarrhythmics; catheter ablation may be needed
- Very slow ectopic rhythm causing fatigue: Atrial pacing at a rate faster than the ectopic rhythm
Rsr pattern in v1 v2
An RSR' pattern in V1-V2 (a small r, deep S, then a second r' "rabbit ear" pattern) is classically associated with right bundle branch block (RBBB), but has several important causes.
Searching sources...
Finding Sources
Finding Sources
Reading File
Reading File
Finding Sources
Loading Image
Reading File
Finding Sources
Here is a complete, textbook-sourced breakdown of the RSR' pattern in V1-V2:
RSR' Pattern in V1-V2
The RSR' (also written rSR', rsR', or "M-shaped" / "rabbit ears") pattern in leads V1-V2 reflects delayed right ventricular activation - the terminal QRS vector is oriented to the right and anteriorly, producing the characteristic double-peak in V1.
Causes (Most to Least Common)
1. Normal Variant / Incomplete RBBB
- An RSR' with QRS < 120 ms and R' amplitude NOT greater than the initial R wave = incomplete RBBB, which is a normal finding in young individuals and athletes
- Right ventricular conduction delay (RVCD) is more frequent in people under 21 years and in athletes
- Does not necessarily progress to complete RBBB
- Pfenninger and Fowler's Procedures for Primary Care, p. 4340
2. Complete Right Bundle Branch Block (RBBB)
- QRS ≥ 120 ms, rSR' in V1, wide terminal S wave in V5-V6
- The terminal QRS vector shifts right and anteriorly due to delayed right ventricular depolarization
- Occurs in:
- No structural disease (most common for RBBB vs LBBB)
- Congenital heart disease - especially atrial septal defect (ASD)
- Acquired heart disease - valvular, ischemic, cor pulmonale, myocarditis
- Trauma to the right bundle
- Harrison's Principles of Internal Medicine 22E, p. 1915; Pfenninger and Fowler, p. 4340
3. Atrial Septal Defect (ASD)
- A classic association - both incomplete and complete RBBB patterns with RSR' in V1 are seen
- Due to right ventricular volume overload from left-to-right shunting
- Fixed splitting of S2 is the clinical clue
- Harrison's 22E; Pfenninger and Fowler
4. Brugada Pattern / Brugada Syndrome
- Type 1 (diagnostic): Coved ST elevation ≥ 2 mm in V1-V2, downsloping, followed by T-wave inversion - the rSR'/Rsr' is part of this pattern
- Type 2: Saddle-back ST elevation with RSR' - not diagnostic alone
- Associated with risk of polymorphic VT/VF and sudden cardiac death in structurally normal heart
- Harrison's 22E - "a Brugada pattern of Rsr' with ST elevation in leads V1 or V2"
5. Right Ventricular Hypertrophy (RVH)
- RSR' in V1 with R' > 15 mm in infants or > 10 mm in children (after 1st year of life)
- Seen in: pulmonary hypertension, COPD, pulmonary valve stenosis, Eisenmenger syndrome
- Tintinalli's Emergency Medicine
6. Pulmonary Embolism (Acute)
- Acute right heart strain can produce transient RSR' or incomplete RBBB in V1
- Part of the S1Q3T3 pattern constellation (though RSR' may appear alone)
- Pfenninger and Fowler: "Any pulmonary disease process can be associated with RVCD, and RVCD can occur acutely with exacerbation of lung disease or pulmonary embolus"
7. Posterior Wall MI
- Posterior MI produces increased R wave in V1-V2 (reciprocal change), which can mimic RSR' morphology
- The R/S ratio in V1 becomes ≥ 1 with ST depression
8. Wolff-Parkinson-White (WPW) - Left-sided Accessory Pathway
- Left-sided pathways produce a dominant R in V1 that can superficially resemble RSR'
- Delta wave and short PR distinguish this
9. Hyperkalemia / Drug Toxicity
- Class Ia antiarrhythmics, tricyclic antidepressants, phenothiazines can slow right ventricular conduction and produce intraventricular conduction delay resembling RBBB pattern
- Harrison's 22E, p. 1916
Quick Memory Summary
| QRS Duration | Pattern | Think of |
|---|---|---|
| < 120 ms, small R' | Incomplete RBBB / RVCD | Normal variant, athlete, ASD, pulmonary disease |
| ≥ 120 ms | Complete RBBB | Organic heart disease, congenital, ischemia |
| RSR' + ST elevation (coved) V1-V2 | Brugada Type 1 | Sudden death risk - refer urgently |
| RSR' + right axis + fixed S2 split | ASD | Echo + bubble study |
| RSR' + acute dyspnea/hypoxia | Acute cor pulmonale / PE | CT-PA / V-Q scan |
Key point from Harrison's 22E: "A distinctive abnormality simulating right bundle branch block with ST-segment elevations in the right chest leads is seen with the Brugada pattern" - this must always be distinguished from benign RBBB.
This is a shared conversation. Sign in to Orris to start your own chat.