
Fluticasone cream
Reading File
Fluticasone cream is a medium-to-high potency topical corticosteroid used for inflammatory skin conditions. Let me pull authoritative details from the medical library.
Searching sources...
Finding Sources
Searching the Web
fluticasone propionate cream indications dosing mechanism side effects
The library results focus on inhaled fluticasone. Let me pull topical/dermatology-specific content and the StatPearls article in parallel.
Finding Sources
Finding Sources
Reading Web Page
https://www.ncbi.nlm.nih.gov/books/NBK542161
Now let me pull the specific Harriet Lane and Lippincott sections for full topical fluticasone details.
Reading File
Reading File
I now also need the Harriet Lane topical side effects section and the potency classification detail. Let me read a bit more.
Reading File
I now have comprehensive information to write a thorough answer on fluticasone cream.
Fluticasone Propionate Cream
Overview
Fluticasone propionate cream (brand name Cutivate) is a synthetic fluorinated corticosteroid available as a 0.05% cream (and 0.005% ointment). It is classified as an intermediate potency topical corticosteroid and is one of the most widely used agents for inflammatory skin conditions. - Lippincott Illustrated Reviews: Pharmacology, p. 1511
Mechanism of Action
Fluticasone binds to intracellular glucocorticoid receptors, triggering effects including:
- Anti-inflammatory - suppresses phospholipase A2, reducing arachidonic acid release and blocking synthesis of prostaglandins and leukotrienes
- Antiproliferative - slows keratinocyte turnover (useful in psoriasis)
- Immunosuppressive - reduces cytokine production (IL-1, IL-2, TNF-α)
- Vasoconstrictive - reduces erythema and edema
Its high lipophilicity allows good skin penetration. Only about 5% of a topical dose is systemically absorbed, with the majority excreted in feces. - StatPearls - Fluticasone
FDA-Approved Indications (Topical)
| Condition | Notes |
|---|---|
| Atopic dermatitis | Primary indication; approved from age 3 months |
| Psoriasis | Intermediate-potency agent suitable for non-facial sites |
| Other corticosteroid-responsive dermatoses | Eczema, seborrhoeic dermatitis, contact dermatitis, lichen planus |
Dosing
Cream 0.05% (primary topical form):
- Children ≥3 months and adults: Apply a thin film to affected areas once daily to twice daily; once symptoms are controlled, step down to a less potent agent
- Safety and efficacy have not been evaluated beyond 4 weeks of continuous use
Lotion:
- Children ≥3 months and adults: Apply thin film once daily; not evaluated beyond 4 weeks
Ointment 0.005%:
- Adults only: Apply thin film twice daily
Important: Fluticasone propionate and fluticasone furoate are NOT interchangeable - they have different potencies and dosing regimens. - The Harriet Lane Handbook, 23rd ed., p. 1495
Potency Classification
Fluticasone propionate 0.05% cream falls in the intermediate potency range (Class III-IV), alongside agents such as betamethasone dipropionate 0.05% cream and mometasone furoate 0.1%.
| Potency Class | Example Agents |
|---|---|
| Low | Hydrocortisone 0.25-2.5%, alclometasone 0.05% |
| Intermediate | Fluticasone propionate 0.005-0.05%, mometasone 0.1%, betamethasone valerate 0.1% |
| High | Fluocinonide 0.05%, betamethasone dipropionate augmented |
| Very High | Clobetasol propionate 0.05%, halobetasol propionate 0.05% |
- Lippincott Illustrated Reviews: Pharmacology, p. 1511
Adverse Effects
Local (most common)
- Skin atrophy and striae (especially with prolonged use or occlusion)
- Irritation, burning, pruritus
- Folliculitis and acneiform eruptions
- Hypopigmentation
- Perioral dermatitis
- Hypertrichosis
- Allergic contact dermatitis
- Secondary infections (bacterial, fungal)
- Miliaria
Ocular
- Cataracts and glaucoma have been reported - avoid contact with eyes
Systemic (rare, with extensive/prolonged use)
-
Hypothalamic-pituitary-adrenal (HPA) axis suppression - especially in young children with large surface area application
-
Growth retardation in children with excessive use
-
Cushing-like features
-
The Harriet Lane Handbook, 23rd ed., p. 1537
Contraindications & Precautions
- Avoid on the face, axillae, or groin (higher absorption, skin thinning risk)
- Do not use under occlusive dressings unless directed - increases systemic absorption
- Reassess diagnosis if no improvement within 2 weeks
- Pregnancy: Use with caution; systemic absorption is low but topical corticosteroids can cause fetal harm in animal studies
- CYP3A4 inhibitors (e.g., ritonavir, ketoconazole): Can increase systemic fluticasone levels, increasing risk of HPA suppression and Cushing syndrome
- Do not use for perioral dermatitis or rosacea (can worsen both)
Practical Tips
- Apply only to affected areas - not as a general moisturiser
- Use the smallest effective amount for the shortest duration
- Avoid wrapping or covering treated areas with bandages
- Once inflammation is controlled, taper to a lower-potency agent or switch to a non-steroidal maintenance therapy (e.g., tacrolimus or pimecrolimus for atopic dermatitis)
- Intermittent ("weekend") dosing of fluticasone propionate cream has evidence for reducing relapse risk in atopic dermatitis - Dermatology 2-Volume Set 5e
Available Formulations Summary
| Formulation | Concentration | Approved Age |
|---|---|---|
| Cream (Cutivate) | 0.05% | ≥3 months |
| Lotion | 0.05% | ≥3 months |
| Ointment | 0.005% | Adults only |
Piles
Piles (hemorrhoids) are swollen vascular cushions in the anal canal. Let me pull comprehensive details from the medical library.
Searching sources...
Reading File
Finding Sources
Searching the Web
hemorrhoids piles classification pathophysiology management treatment 2024
Excellent hits. Let me now read the Bailey & Love and Sleisenger & Fordtran sections in parallel - both are definitive surgical/GI textbooks for this topic.
Reading File
Reading File
Excellent content. Let me now read the Bailey & Love section on external hemorrhoids and management, and the Sleisenger treatment section in parallel.
Reading File
Reading File
I have rich, comprehensive material. Let me read a bit more on surgical options and external hemorrhoids from Bailey & Love, then compile the full answer.
Reading File
Reading File
I now have comprehensive content from two major surgical/GI textbooks. Let me also fetch the thrombosed external hemorrhoid image to include in the answer.
Reading File
I now have all the material needed for a comprehensive answer. Let me compile it.
Piles (Haemorrhoids)
Definition
Piles (haemorrhoids) are symptomatic enlargements and distal displacement of the normal anal vascular cushions. The word "haemorrhoid" derives from Greek (haima = blood, rhos = flowing); "piles" comes from Latin (pila = a ball). Haemorrhoids are a normal part of anal anatomy - their presence does not imply disease; only when they become symptomatic do they constitute a clinical problem. - Bailey and Love's Short Practice of Surgery, 28th ed.
Anatomy
There are three primary anal cushions at the 3, 7, and 11 o'clock positions (in the lithotomy position). Secondary haemorrhoids may develop between these. The anal cushions form the submucosal component of the anal canal and help seal it, contributing to continence.
-
Internal haemorrhoids - originate above the dentate line, covered by columnar or transitional mucosa (insensate - so usually painless)
-
External haemorrhoids - located below the dentate line, covered by squamous epithelium (pain-sensitive)
-
Sleisenger and Fordtran's GI and Liver Disease
Pathophysiology
Several factors contribute to haemorrhoidal development:
-
Man's upright posture - increases hydrostatic pressure in the venous plexus
-
Absence of valves in the portal venous system
-
Raised intra-abdominal pressure - from straining during defecation, pregnancy, chronic cough, or ascites
-
Shearing forces during defecation lead to mucosal trauma (bleeding) and caudal displacement of the anal cushions (prolapse)
-
This causes impaired venous drainage, progressive engorgement, local stasis, and transudation of fluid (causing pruritus)
-
With time, fragmentation of supporting connective tissue (normal with ageing, but accelerated in haemorrhoidal disease) leads to loss of elasticity - cushions no longer retract after defecation
-
Increased levels of circulating matrix metalloproteinases are associated with symptoms, suggesting connective tissue degradation plays a key role
-
Bailey and Love's Short Practice of Surgery, 28th ed.
Classification
Internal Haemorrhoids (Grades I-IV)
| Grade | Description |
|---|---|
| Grade I | Bleed but do not prolapse; may be enlarged |
| Grade II | Prolapse on straining/defecation, reduce spontaneously |
| Grade III | Prolapse and require manual reduction |
| Grade IV | Remain permanently prolapsed, cannot be reduced |
"Mixed" haemorrhoids have a significant cutaneous (external) component - essentially external extensions of internal haemorrhoids arising through repeated congestion and oedema.
External Haemorrhoids
Relate to the inferior haemorrhoidal plexus deep in the perianal skin. Frequently confused with anal skin tags (which are not true haemorrhoids). The most clinically significant presentation is thrombosed external haemorrhoid (perianal haematoma).
- Sleisenger and Fordtran's GI and Liver Disease; Bailey and Love's Short Practice of Surgery, 28th ed.
Clinical Features
| Symptom | Details |
|---|---|
| Bleeding | Earliest symptom; bright red, painless; separate from stool - seen on paper or as a fresh splash in the pan; rarely causes anaemia |
| Prolapse | Feeling of a lump at the anus during/after defecation |
| Pruritus | Due to mucus discharge from prolapsed mucosa |
| Mucus discharge | Causes perianal moisture and soiling |
| Pain | Generally absent with uncomplicated internal haemorrhoids (above dentate line); pain should prompt search for another diagnosis (anal fissure, abscess, thrombosis) |
Key point: Pain = think of another diagnosis. Uncomplicated internal haemorrhoids bleed but do not hurt. - Bailey and Love's Short Practice of Surgery, 28th ed.
Thrombosed External Haemorrhoid
- Sudden onset, olive-shaped, painful, blue subcutaneous swelling at the anal margin
- Follows straining, coughing, or heavy lifting
- Usually in a lateral position at the anal margin
- Natural history: may resolve, suppurate, fibrose into a skin tag, or spontaneously rupture with clot extrusion
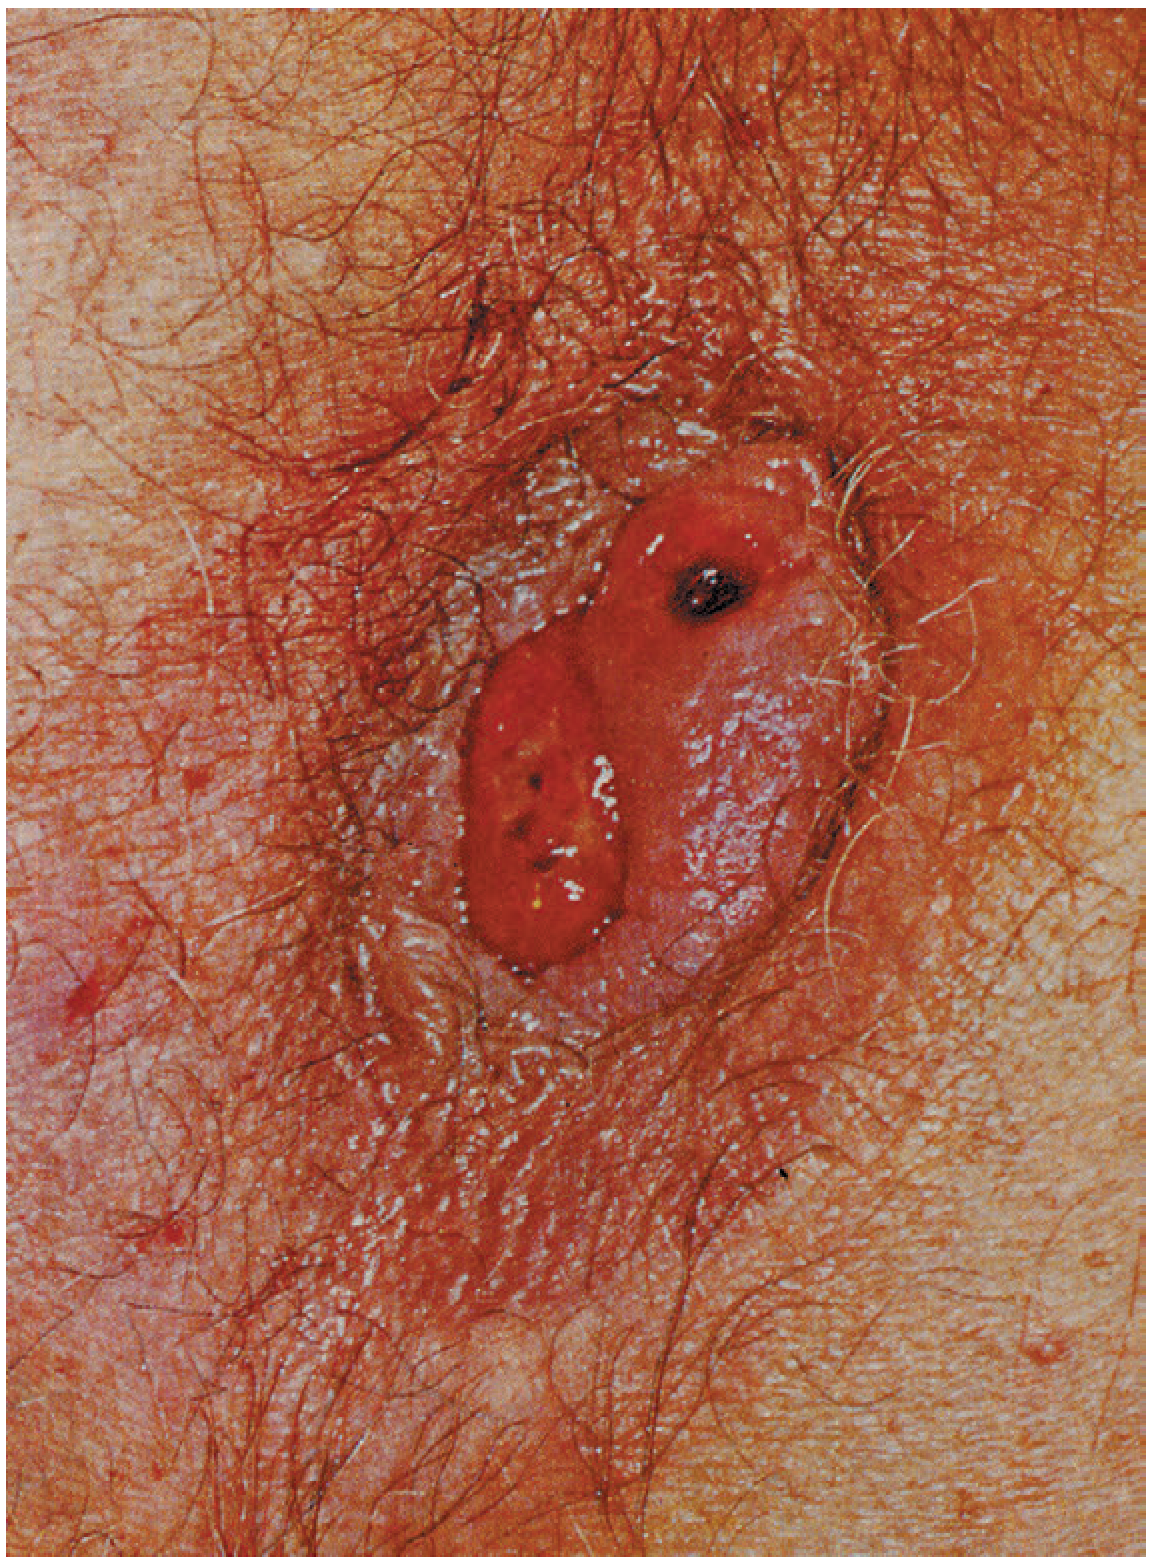
Thrombosed external haemorrhoid that has spontaneously ruptured - Bailey and Love's, Fig. 80.26
Risk Factors
- Chronic constipation / straining
- Low-fibre diet
- Prolonged time sitting on the toilet
- Pregnancy
- Portal hypertension / liver cirrhosis
- Increasing age (connective tissue fragmentation)
- Chronic diarrhoea (loose stools also increase risk)
Diagnosis
- History - nature of bleeding, prolapse, pain
- Inspection - perianal skin, anal verge; ask patient to strain
- Digital rectal examination - internal haemorrhoids are generally not palpable
- Proctoscopy / Anoscopy (key investigation) - visualises internal haemorrhoids and grades protrusion
- Sigmoidoscopy/Colonoscopy - essential to exclude colorectal malignancy as a cause of rectal bleeding, especially in patients >40 years or with alarm features
"Haemorrhoids located elsewhere than the classic 3, 7, 11 o'clock positions should raise concern for other diseases - carcinoma, lymphoma, condyloma." - Sleisenger and Fordtran's GI and Liver Disease
Management
Step 1 - Conservative (All Grades)
- High-fibre diet (20-30 g/day) and adequate fluid intake (6-8 glasses/day)
- Stool softeners (e.g., docusate sodium) if stools remain hard
- Polyethylene glycol 3350 for constipation
- Avoid prolonged sitting on the toilet; avoid straining
- Warm sitz baths for comfort
- Topical agents: Phenylephrine/mineral oil/petrolatum or mild glucocorticoid creams temporarily relieve pain/itching (note: steroid creams predispose to local infections)
- Phlebotonics (flavonoids such as diosmin/hesperidin, plant extracts, calcium dobesilate): improve venous tone, stabilise capillary permeability, reduce bleeding; superior to placebo; excellent safety profile - particularly useful for Grade II-III
Step 2 - Office-Based Procedures (Grade I-III)
| Procedure | Details |
|---|---|
| Rubber Band Ligation (RBL) | Most common office procedure; band placed above the dentate line to cause ischaemic necrosis; bands slough within 10 days; treats Grade II-III; complications: bleeding (warn patient), pain (if band too distal), rare pelvic sepsis |
| Injection Sclerotherapy | 5% phenol in arachis/almond oil injected at the apex of the pedicle (3-5 mL per haemorrhoid); causes fibrosis obliterating vascular channels; for Grade I-II; largely superseded by RBL |
| Infrared Photocoagulation | Heat causes coagulation necrosis; less commonly used |
| Cryotherapy | Not commonly used due to variable results |
Step 3 - Surgical (Grade III-IV, Failed Office Procedures)
Indications for haemorrhoidectomy:
- Grade III and IV haemorrhoids
- Grade II not cured by non-operative treatment
- Mixed haemorrhoids with well-defined external component
- Bleeding causing anaemia
- Thrombosed external haemorrhoid presenting within 48 hours (clot evacuation under local anaesthesia)
Surgical techniques:
| Technique | Description |
|---|---|
| Milligan-Morgan (Open) | Classic UK technique; ligation and excision; wounds left open to heal by secondary intention; mucocutaneous skin bridges preserved |
| Ferguson (Closed) | Popular in USA; same as above but wounds sutured closed |
| Stapled Haemorrhoidopexy (PPH) | Circumferential strip of mucosa/submucosa excised above dentate line using circular stapler; less painful, faster recovery; but higher recurrence rates; risk of staple line dehiscence, rectovaginal fistula, tenesmus |
| Transanal Haemorrhoidal Ligation (HAL/HALO) | Doppler-guided ligation of feeding vessels ± mucopexy; lower recurrence than RBL but more expensive and invasive |
- Bailey and Love's Short Practice of Surgery, 28th ed.; Sleisenger and Fordtran's GI and Liver Disease
Management by Grade - Summary
| Grade | Treatment |
|---|---|
| I | Conservative; sclerotherapy if persistent bleeding |
| II | Conservative + RBL; sclerotherapy |
| III | RBL (first-line); HAL; haemorrhoidectomy if failed |
| IV | Haemorrhoidectomy |
| Thrombosed external | Clot evacuation <48 h; conservative if >48 h |
Complications of Haemorrhoids
- Chronic blood loss anaemia (uncommon)
- Strangulation (irreducible Grade IV with sphincter spasm)
- Thrombosis
- Ulceration and infection
- Pruritus ani (from mucus discharge)
Complications of Surgery
- Post-operative bleeding (primary, reactionary, secondary)
- Urinary retention
- Anal stenosis (if skin bridges not preserved)
- Faecal incontinence (rare, from sphincter damage)
- Anal fissure
- Pelvic sepsis (rare but potentially life-threatening, especially after RBL)
Special Situations
- Pregnancy: Conservative management preferred; RBL and haemorrhoidectomy generally deferred until post-partum
- Portal hypertension/Cirrhosis: Treat conservatively; haemorrhoidectomy carries high risk of bleeding; caution with all interventions
- Immunocompromised/Diabetics: Bowel preparation recommended before RBL; higher infection risk
- Anticoagulated patients: Increased bleeding risk; manage conservatively where possible
Treatment
The previous topic was piles (haemorrhoids), so "Treatment" refers to the treatment of haemorrhoids in more depth. Let me pull detailed treatment content from the textbooks.
Diving deeper...
Finding Sources
Finding Sources
Searching the Web
hemorrhoid treatment guidelines 2024 ASCRS rubber band ligation hemorrhoidectomy
Good. Let me now pull the Current Surgical Therapy and Pfenninger sections for detailed procedural content, plus Sleisenger's treatment section in full.
Reading File
Reading File
Reading File
Let me now read the rest of Sleisenger's hemorrhoid treatment section (surgical options, external hemorrhoids, special situations) and the Current Surgical Therapy section on RBL and IRC.
Reading File
Reading File
I now have comprehensive, multi-textbook content covering every treatment modality. Let me compile the full, detailed answer.
Treatment of Piles (Haemorrhoids)
Treatment is tailored to grade, type (internal vs. external), symptom severity, and patient factors. It follows a stepwise approach: conservative first, then office-based procedures, then surgery.
Step 1 - Conservative (Medical) Management
Appropriate for: All grades as first-line; definitive treatment for Grade I-II in many patients.
Dietary & Lifestyle Measures
- High-fibre diet: 20-30 g/day - softens stools, reduces straining
- Fluid intake: 6-8 glasses of non-alcoholic, non-caffeinated beverages daily
- Avoid prolonged sitting on the toilet - reduces sustained venous engorgement
- Avoid straining - most important modifiable factor
- Sitz baths: Warm water soaks for 10-15 min after bowel movements - reduce discomfort and spasm
Laxatives & Stool Softeners
| Agent | Role |
|---|---|
| Bulk-forming agents (ispaghula, psyllium, methylcellulose) | First choice - increase stool bulk, soften consistency |
| Docusate sodium | Stool softener; added when bulk agents alone insufficient |
| Polyethylene glycol 3350 | Osmotic laxative for hard stools/constipation unresponsive to fibre |
| Lactulose/enemas | Rarely needed |
Topical Agents
- Local anaesthetic/astringent creams (e.g. phenylephrine + mineral oil + petrolatum, lidocaine-based preparations) - temporarily relieve pain and pruritus
- Witch hazel preparations - mild astringent, topical soothing
- Glucocorticoid-based creams (e.g. hydrocortisone) - reduce inflammation and itch; caution: predispose to local infection (e.g. candidiasis) and should not be used long-term
- Glycerin suppositories have little role in treating haemorrhoids
Phlebotonics (Venotonics)
A heterogeneous group of plant extracts (flavonoids) and synthetic compounds:
- Diosmin/Hesperidin (Daflon), Rutoside, Calcium dobesilate
- Mechanism: improve venous tone, stabilise capillary permeability, reduce oedema, increase lymphatic drainage
- Superior to placebo for acute symptoms; reduce bleeding; excellent safety profile
- Particularly useful for Grade II-III, and in pregnancy
- Available as oral tablets or suppositories
"Phlebotonics are superior to placebo in treating acute hemorrhoid symptoms and have an excellent safety profile." - Sleisenger and Fordtran's GI and Liver Disease
Step 2 - Office-Based (Non-Excisional) Procedures
Appropriate for: Grade I-III, persistent symptoms despite conservative treatment, or Grade IV in frail/high-risk patients.
1. Rubber Band Ligation (RBL)
Most common and most effective office procedure for haemorrhoids (ASCRS 2024 Guidelines).
- Grades: Primarily Grade II and III; can be used for Grade I if large enough
- Technique: A tight elastic band is placed just proximal to the dentate line (above it - critical to avoid pain) using a slotted anoscope (Barron's bander) or suction device (CRH-O'Regan, ConMed SpaceBander)
- Mechanism: Band causes ischaemic necrosis → tissue sloughs within 7-10 days → fibrosis anchors the remaining cushion
- One to three haemorrhoids can be banded; typically 1 per session to minimise pain; reassess in 4-6 weeks; most patients need ≤3 procedures
- Contraindication: Do NOT place band at or distal to the dentate line - causes severe pain from somatic innervation; band must be removed immediately if too distal
- Not used for external haemorrhoids
Complications:
| Complication | Notes |
|---|---|
| Pain/discomfort | Most common; from reactive oedema or band too distal |
| Bleeding | ~1-2% significant bleed at sloughing (~day 7-10); warn patients |
| Urinary retention | Uncommon |
| Pelvic sepsis | Rare but life-threatening; any fever + perineal pain post-RBL = emergency |
| Vasovagal reaction | During procedure |
Advantages over sclerotherapy: Simpler, more effective, lower recurrence rate. - Sleisenger and Fordtran's GI and Liver Disease; Bailey and Love's, 28th ed.
2. Injection Sclerotherapy
- Grades: I and II (small, bleeding haemorrhoids)
- Agent: 5% phenol in arachis oil (or almond oil); 3-5 mL per haemorrhoid injected submucosally at the apex of the pedicle (not into the haemorrhoid itself)
- Mechanism: Causes fibrosis that obliterates vascular channels and provides a scar to support prolapsing mucosa
- Technique: Injected above the dentate line through anoscope; pain during injection = needle in wrong position (withdraw immediately); rapid mucosal bulging turning white = too superficial (risk of ulceration)
- Repeated every 8 weeks if needed
- Advantage: Can be used in anticoagulated patients (unlike RBL)
- Complications: Superficial ulceration, rare pelvic sepsis/prostatitis (if too deep), anaphylaxis (rare), impotence (reported)
- Largely superseded by RBL due to higher complication risk and technically more demanding - Bailey and Love's, 28th ed.; Pfenninger & Fowler's Procedures for Primary Care
3. Infrared Photocoagulation (IRC)
- Grades: Grade I (best), Grade II
- Mechanism: Infrared radiation applied for 1.5 seconds to 2-3 sites proximal to the haemorrhoidal plexus; coagulates tissue → fibrosis
- Multiple sites treated per visit
- Results comparable to RBL for Grade I; less effective for larger haemorrhoids
- Best suited for Grade I, especially in patients who have experienced pain with RBL
- Complications rare (pain, bleeding uncommon) - Current Surgical Therapy, 14th ed.; Sleisenger and Fordtran's GI and Liver Disease
4. Cryotherapy
- Uses liquid nitrogen to freeze and destroy haemorrhoidal tissue
- Largely fallen out of favour - difficult to control depth of destruction, prolonged procedure, foul-smelling discharge from necrosis - Sleisenger and Fordtran's GI and Liver Disease
5. Doppler-Guided Haemorrhoidal Artery Ligation (HAL / HALO)
- Grades: II and III
- A Doppler probe identifies and ligates the feeding arteries to the haemorrhoidal columns transanally; can be combined with mucopexy (suture plication of prolapsed mucosa)
- Less painful than conventional haemorrhoidectomy; no excision
- HubBLe trial: HAL has significantly lower recurrence rates than RBL, but is more expensive and time-consuming
- Growing evidence supports it as an effective, minimally invasive alternative - Bailey and Love's, 28th ed.; Current Surgical Therapy, 14th ed.
Step 3 - Surgical Treatment
Indications for surgery:
- Grade III haemorrhoids unresponsive to office-based procedures
- Grade IV haemorrhoids (most)
- Symptomatic external haemorrhoids unresponsive to conservative treatment
- Mixed internal + external haemorrhoids with well-defined external component
- Bleeding causing anaemia
- Thrombosed external haemorrhoid presenting within 48 hours (clot evacuation)
- Patient preference after failed office procedures
1. Ferguson Hemorrhoidectomy (Closed) - USA Standard
- Most common haemorrhoid operation in the United States
- V-shaped incision in perianal skin → haemorrhoid elevated off sphincters → vascular pedicle suture-ligated (2-0 Vicryl) → mucosal defect closed with running suture (last few mm left open to drain)
- Can use scalpel, cautery, or energy devices (LigaSure/Harmonic - faster, but higher cost; must carefully identify internal sphincter)
- Position: Prone jack-knife under spinal anaesthesia (preferred)
- Long-term recurrence: ~26% at median 17 years; 11% require additional procedure - Current Surgical Therapy, 14th ed.
2. Milligan-Morgan Hemorrhoidectomy (Open) - UK/European Standard
- Most common operation in the UK and Europe
- Identical to Ferguson except wounds are left open to heal by secondary intention
- Anoderm between haemorrhoids injected with dilute adrenaline (1:300,000) to reduce bleeding
- Artery forceps applied → V-shaped cut → dissection reveals internal sphincter → transfixion ligature at pedicle apex → haemorrhoid excised → skin bridges preserved (critical to prevent anal stenosis)
- Wound healing is slower than closed technique; outcomes are otherwise similar
Complications of Excisional Haemorrhoidectomy:
| Complication | Notes |
|---|---|
| Post-operative pain | Most significant drawback; greatest barrier to patient acceptance |
| Primary/reactionary bleeding | Intraoperative or within 24 h |
| Secondary bleeding | Day 7-10 at pedicle sloughing |
| Urinary retention | Common; especially in males |
| Anal stenosis | If skin bridges not adequately preserved |
| Faecal incontinence | Rare; from sphincter damage |
| Anal fissure | From scarring |
| Pelvic sepsis | Rare but serious |
Pain reduction adjuncts after haemorrhoidectomy: Topical glyceryl trinitrate, anaesthetic cream, sucralfate, topical 2% atorvastatin, topical cholestyramine, liposomal bupivacaine (long-acting local anaesthetic) - Sleisenger and Fordtran's GI and Liver Disease
3. Stapled Haemorrhoidopexy (PPH - Procedure for Prolapse and Haemorrhoids)
- Grades: I-III circumferential internal haemorrhoids without a bulky external component
- Technique: Circular EEA stapler removes a circumferential band of mucosa and submucosa 3-4 cm proximal to the dentate line → no external wounds → staple line above dentate line (less pain) → repositions prolapsed cushions, disrupts vascular pedicle
- Does NOT excise haemorrhoids - flattens and repositions them; may flatten minor external disease but does not adequately treat large external haemorrhoids
- Purse-string suture placement (circumferential submucosal, ~2 cm proximal to haemorrhoidal pedicle) is the key technical step; must check vagina digitally in women before firing to avoid rectovaginal fistula
- Advantages: Less post-operative pain, faster recovery, better short-term quality of life
- Disadvantages: Higher long-term recurrence than conventional haemorrhoidectomy; external haemorrhoids may persist
- Serious complications (rare): Staple line dehiscence, pelvic sepsis, rectovaginal fistula, tenesmus from staples near dentate line, rectal perforation, staple line stricture - Current Surgical Therapy, 14th ed.; Pfenninger & Fowler's Procedures for Primary Care; Bailey and Love's, 28th ed.
Treatment of External Haemorrhoids
Thrombosed External Haemorrhoid (Perianal Haematoma)
| Timing | Management |
|---|---|
| < 48 hours from onset | Surgical clot evacuation under local anaesthesia - elliptical excision of overlying skin and clot; provides immediate relief |
| > 48 hours | Conservative management preferred (pain typically peaks by 48-72 h and improves) - warm sitz baths, analgesia, stool softeners |
Natural history if untreated: resolution, fibrosis (giving rise to a skin tag), suppuration, or spontaneous rupture with clot extrusion. - Bailey and Love's, 28th ed.; Current Surgical Therapy, 14th ed.
Treatment by Grade - Summary
| Grade | First Line | Second Line | Surgery |
|---|---|---|---|
| I | Conservative + dietary | Sclerotherapy / IRC | Rarely needed |
| II | Conservative + dietary | RBL (most effective) | If RBL fails |
| III | RBL or HAL | Repeat procedures | Haemorrhoidectomy |
| IV | Surgery usually required | Stapled haemorrhoidopexy in selected cases | Excisional haemorrhoidectomy |
| Thrombosed external | <48 h: clot evacuation; >48 h: conservative | - | Excision in selected cases |
Special Situations
| Situation | Approach |
|---|---|
| Pregnancy | Conservative + phlebotonics; RBL/surgery deferred to post-partum |
| Portal hypertension / Cirrhosis | Conservative only; haemorrhoidectomy carries high bleeding risk |
| Anticoagulated patients | Sclerotherapy preferred over RBL; conservative where possible |
| Immunocompromised / Diabetic | Bowel prep before office procedures; higher infection vigilance |
| Acute haemorrhoidal crisis (prolapsed, oedematous, strangulated) | Hyaluronidase injection + massage to reduce oedema; urgent or semi-urgent haemorrhoidectomy |
2024 ASCRS Guidelines - Key Recommendations
- Strong recommendation: Disease-specific history and physical examination for all patients
- Conditional recommendation: Complete colonoscopic evaluation in patients with symptomatic haemorrhoids AND rectal bleeding (to exclude colorectal malignancy)
- Strong recommendation: Office-based procedures for most Grade I-II and selected Grade III haemorrhoids refractory to conservative treatment; haemorrhoid banding is the most effective office procedure
- Selected patients with thrombosed external haemorrhoids: early surgical excision may be beneficial
- Grade III-IV or external haemorrhoids: typically offered excisional haemorrhoidectomy
- The AGA (2026) additionally endorses both banding and infrared coagulation as safe, effective options before surgery for Grade I-III
This is a shared conversation. Sign in to Orris to start your own chat.