
Types of IOL
"intraocular lenses"[MeSH Terms]
AAO intraocular lens types monofocal multifocal toric EDOF accommodating
Types of intraocular lenses (IOLs)
1. By optical function
| Type | Main purpose | Key point |
|---|---|---|
| Monofocal IOL | Focus at one distance, usually distance | Most commonly used. Reading glasses are often needed for near work. |
| Multifocal IOL | Distance and near vision | May reduce spectacle dependence, but can cause glare, halos, and reduced contrast sensitivity. Includes bifocal and trifocal IOLs. |
| Extended depth-of-focus (EDOF) IOL | Distance plus intermediate vision | Often provides good computer-distance vision; reading glasses may still be required for fine print. |
| Accommodative IOL | Attempts to change focus using ciliary-muscle movement | Designed to provide a range of focus, though near vision results can vary. |
| Toric IOL | Corrects corneal astigmatism | Can be monofocal, EDOF, or multifocal. Accurate alignment is required. |
| Light-adjustable IOL | Postoperative adjustment of refractive power | Power can be altered after surgery using ultraviolet light treatment. |
| Aspheric IOL | Reduces spherical aberration | Often incorporated into monofocal and premium IOLs to improve image quality and contrast. |
2. By material
- Rigid PMMA IOL: Requires a larger incision. Used less often in routine phacoemulsification.
- Foldable silicone IOL: Can be inserted through a small incision.
- Foldable hydrophobic acrylic IOL: Widely used; good capsular-bag stability.
- Hydrophilic acrylic IOL: Foldable and injectable; has different risks of deposits or opacification depending on the model.
3. By position or fixation in the eye
- Posterior chamber IOL (PCIOL): Placed in the capsular bag or ciliary sulcus. This is the usual location after uncomplicated cataract surgery.
- Anterior chamber IOL (ACIOL): Placed in the anterior chamber when posterior capsular support is inadequate.
- Iris-fixated or iris-claw IOL: Attached to the iris.
- Scleral-fixated IOL: Secured to the sclera when capsular support is absent. It may be sutured or sutureless.
4. By design
- One-piece IOL
- Three-piece IOL
- Spherical IOL
- Aspheric IOL
- Blue-light filtering IOL
- UV-filtering IOL
- Phakic IOL: Implanted without removing the natural crystalline lens, usually for refractive correction in high myopia or other refractive errors.
- Pseudophakic IOL: Implanted after the natural lens has been removed, usually after cataract extraction.
Exam-oriented summary
- Monofocal
- Multifocal or trifocal
- EDOF
- Toric
- Accommodative
- Light-adjustable
- Aspheric
Cataract types
"cataract"[MeSH Terms] AND classification
AAO types of cataracts nuclear cortical posterior subcapsular congenital traumatic
Types of cataract
A. By anatomical location and morphology
| Type | Appearance and key feature |
|---|---|
| Nuclear sclerotic cataract | Central lens nucleus becomes yellow, then brown. Causes gradual distance-vision reduction and may produce a temporary myopic shift, called second sight. |
| Cortical cataract | Opacity in the lens cortex, classically wedge-shaped or radial spokes extending toward the centre. Glare and night-driving difficulty are common. |
| Posterior subcapsular cataract (PSC) | Central opacity just beneath the posterior capsule. Causes marked glare and poor near vision, often worse in bright light. It can progress relatively quickly. |
| Anterior subcapsular cataract | Opacity beneath the anterior lens capsule, often associated with inflammation, trauma, atopy, or other causes. |
| Anterior polar cataract | Small central anterior capsular opacity, commonly congenital. |
| Posterior polar cataract | Central posterior capsular opacity, often congenital. Important surgically because of a higher risk of posterior-capsule weakness. |
| Lamellar or zonular cataract | Layered opacity surrounding the nucleus, with clear and opaque lamellae. A common congenital cataract. |
| Coronary cataract | Peripheral cortical opacities around the equator, often with little visual effect initially. |
| Christmas-tree cataract | Multicoloured, needle-like crystalline opacities, classically associated with myotonic dystrophy. |
| Sunflower cataract | Central disc with radiating petals, associated with Wilson disease. |
| Snowflake cataract | White cortical opacities that may occur in poorly controlled diabetes, especially in younger people. |
B. By cause
-
Age-related or senile cataract
- Most common
- Usually nuclear, cortical, or PSC
-
Congenital/developmental cataract
- Present at birth or develops in childhood
- Examples: lamellar, polar, sutural, cerulean cataract
-
Traumatic cataract
- Blunt trauma: classically rosette-shaped cataract
- Penetrating trauma may directly damage the lens
-
Complicated cataract
- Secondary to chronic intraocular disease, especially uveitis, retinal detachment, or high myopia
- Often begins as a posterior subcapsular opacity
-
Metabolic cataract
- Diabetes mellitus: snowflake cataract
- Galactosaemia: oil-droplet cataract
- Wilson disease: sunflower cataract
- Hypocalcaemia: cortical cataract
-
Drug-induced cataract
- Most notably long-term corticosteroids, commonly causing PSC
- Also associated with some other drugs, depending on exposure and patient factors
-
Radiation or electric cataract
C. By maturity
- Immature cataract: Lens is partially opaque, with some clear cortex remaining.
- Mature cataract: Entire lens becomes opaque.
- Hypermature cataract: Advanced mature cataract with liquefied cortex and a shrunken or sinking nucleus.
- May be Morgagnian cataract if the nucleus sinks in liquefied cortex.
The three common age-related cataracts are nuclear sclerotic, cortical, and posterior subcapsular cataract.
Stages of hepatic encephalopathy according to davidson
Davidson's Principles and Practice of Medicine hepatic encephalopathy grades West Haven stage 1 2 3 4 table
"hepatic encephalopathy"[MeSH Terms] AND "severity of illness index"[MeSH Terms]
Grades of hepatic encephalopathy (West Haven)
| Grade | Mental state | Neuromuscular signs |
|---|---|---|
| 1 | Mild confusion, euphoria or anxiety, short attention span, irritability, sleep reversal (day-night pattern) | Fine tremor, possible mild incoordination. Asterixis may be present. |
| 2 | Lethargy or apathy, disorientation (especially to time), inappropriate or altered personality and behaviour | Asterixis is present. Speech may be slurred. |
| 3 | Somnolent but rousable, marked confusion, incoherent speech, aggressive behaviour | Asterixis is usually still present. Hyperreflexia and a positive Babinski sign may occur. |
| 4 | Coma, unresponsive to voice or pain | Asterixis cannot be tested. Decerebrate posturing may occur in deep coma. |
- Grade I: sleep reversal, mild confusion, irritability, tremor, asterixis.
- Grade II: lethargy, disorientation, inappropriate behaviour, asterixis.
- Grade III: somnolence, severe confusion, aggressive behaviour, asterixis.
- Grade IV: coma.
Points often asked in exams
- Minimal (covert) hepatic encephalopathy comes before grade 1. Patients look normal clinically, but psychometric or neurophysiological tests are abnormal.
- Asterixis (flapping tremor) is present in grades 1 to 3, though it is not specific to hepatic encephalopathy.
- EEG shows slow, high-amplitude and triphasic waves.
- Blood ammonia is neither sensitive nor specific, and it correlates poorly with grade. Diagnosis is clinical.
- Common precipitants:
- GI bleeding
- infection
- constipation
- electrolyte disturbance
- sedatives
- non-adherence to lactulose
- azotaemia
- Treatment: correct the precipitant, then give lactulose, with rifaximin added to prevent recurrence.
Spider naevi other causes
spider naevus spider angioma
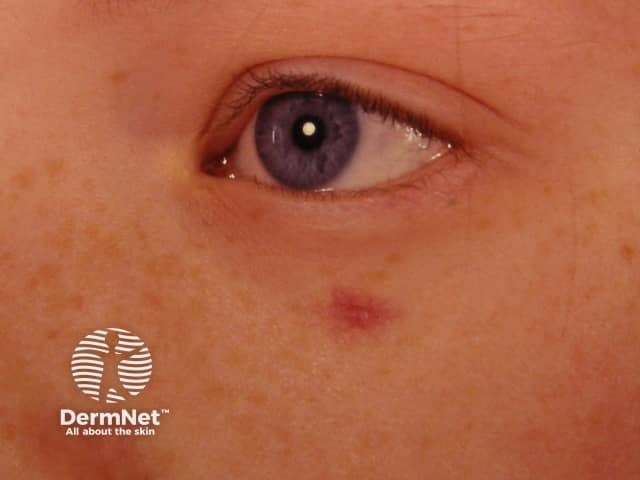
Imaging modality: Dermatologic clinical photography; technique: color-calibrated, high-resolution close-up; lesion located on left cheek; pattern: central red nidus with radiating telangiectatic vessels; compatible with spider angioma (spider naevus). The vascular telangiectasia is clearly visible around the central dot; surrounding skin shows mild solar lentigines. Pathophysiology involves arborizing capillaries supplied by a feeding arteriole in the dermis. Clinically, lesions are usually solitary and benign; differential diagnoses include cherry angioma and capillary malformations. Spider naevi can be associated with elevated estrogen states, pregnancy, or hepatic disease when multiple. The finding is of diagnostic significance to distinguish vascular lesions and to educate about cutaneous vascular patterns. Suitable for teaching dermatology students, patient education, and research on cutaneous telangiectasia; management is typically observation unless cosmetic concerns or systemic associations warrant evaluation.
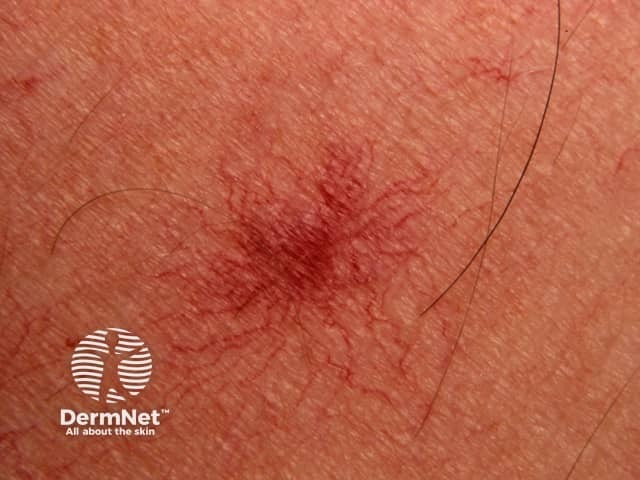
Imaging modality: Clinical Photography; Macro-level bright-field digital image of a single spider naevus on the cutaneous surface. Anatomical context: integumentary system; dermal superficial vascular network. The lesion shows a central reddish dot with radiating slender vessels forming a spider-like capillary pattern. Vascularity is conspicuous; lesion is small, approximately few millimeters in diameter, well circumscribed, blanching with pressure. The surrounding skin is normal in tone with fine hairs; no surrounding edema. The appearance is classic for spider angioma: telangiectatic capillaries in the dermis emanating from a central vessel; superficial vascular plexus; mild erythema. The lesion is non-inflamed, non-pigmented; flat to slightly raised; edges discrete. Pathophysiology involves dilation of preexisting venules and capillaries with a central feeding arteriole; histology would show dilated capillaries in the superficial dermis radiating outward. Clinically, spider naevus is typically benign; blanching on compression; may be solitary or multiple; associations include hormonal states (pregnancy, estrogen therapy) and liver disease in adults; evaluate context accordingly. Diagnostic significance includes distinguishing from cherry angioma, telangiectasia, capillary malformation, or basal cell carcinoma with superficial telangiectasia. Potential clinical uses include educational dermatology references, differential diagnosis, liver disease screening cue, and teaching vessel anatomy. This imaging supports patient education, documentation, and consistent cross visit comparison over time.

Imaging modality and technique: This image is a high‑resolution, color clinical photograph of a solitary cutaneous spider angioma (spider naevus) captured in vivo on the skin surface using standard dermato- photographic technique. The lesion is a small, bright red papule with multiple radiating telangiectatic vessels extending from a central nidus, producing a spider‑like morphology. The surrounding skin is sun‑tanned with faint lentigines. The lesion blanches on gentle pressure, consistent with superficial vascular dilation. Anatomical location is cutaneous; axial skin surface of an extremity is implied but not specified; the body region is the integumentary system. Histology is not provided; therefore, microscopy findings are not shown. Clinically, spider angiomas are benign cutaneous vascular lesions seen commonly in young patients, pregnant individuals, and those with liver disease or hepatic cirrhosis in adults. Differential diagnosis includes cherry angioma, capillary malformation, rosacea‑associated telangiectasia, and less likely basal cell carcinoma. Diagnostic significance: typically benign, cosmetic concern; may indicate hormonal or hepatic conditions in certain contexts. The image is suitable for clinical education, dermatology training, and vascular lesion cataloging. The site demonstrates a prototypical central arteriole with radiating venules, which is typical of spider angioma and can guide recognition and differentiation in practice.
spider angioma OR "spider naevus"
Spider naevi: causes other than chronic liver disease
Physiological and benign causes
- Normal healthy people, especially children. Spider naevi are common in healthy children and may involute over several years without treatment (Andrews' Diseases of the Skin, Dilation of Preexisting Vessels).
- Pregnancy. Bailey & Love notes they appear in about two-thirds of pregnant women and usually disappear in the puerperium (Bailey & Love's Short Practice of Surgery, 28th ed., Spider naevi). Palmar erythema is usually present alongside them in pregnancy (Andrews).
- Puberty. They may appear, and sometimes disappear, spontaneously (Bailey & Love).
- Sun exposure. They occur most often on the face, neck and dorsal hands, which suggests sun-induced vascular change (Andrews). Creasy & Resnik also describes them as most prevalent in sun-exposed areas.
Drug and hormonal causes
- Oestrogen therapy, such as the combined oral contraceptive pill or hormone replacement. I did not find this stated in the textbook sections I read. It follows from the oestrogen mechanism and from the DermNet image caption, which lists pregnancy and oestrogen therapy.
Other disease associations
- Liver disease other than cirrhosis. Andrews lists hepatitis C, malignant liver disease, and other hepatic dysfunction. A raised blood oestrogen level is the common link. Creasy & Resnik attributes it to decreased hepatic oestrogen catabolism. Raised VEGF and basic fibroblast growth factor are predictors in cirrhotic patients (Andrews).
- Other states with high oestrogen. From general knowledge rather than the sources I read, these include oestrogen-producing tumours and thyrotoxicosis. Rheumatoid arthritis and malnutrition are also sometimes quoted.
Points for exams
- Number matters. One to three spider naevi are common in normal people. More than about five, or a sudden crop, should prompt a search for liver disease.
- Site. They occur in the SVC territory (face, neck, upper chest, arms), not below the nipple line. The textbook sources did not state this, so it is from general knowledge.
- Associated signs suggesting cirrhosis: palmar erythema, pale nails with distal hyperaemic bands, gynaecomastia, and testicular atrophy.
- Treatment, if wanted: pulsed-dye laser, intense pulsed light, or electrodesiccation (Andrews; Bailey & Love).