
I need detailed info from Bailey and love surgery about breast ca
Reading File
Now let me search for breast cancer content in Bailey & Love simultaneously with a PubMed search for recent evidence.
Finding Sources
Searching PubMed
"breast cancer" AND "surgical management"
I have all the section locations. Now let me read the key sections in parallel - pathology, staging, treatment, risk factors, and molecular classification.
Reading File
Reading File
Good. Now let me read pathology, molecular classification, and treatment details in parallel.
Reading File
Reading File
Excellent - I have rich content. Let me now read the surgical treatment, axilla management, screening, hereditary breast cancer, and follow-up sections.
Reading File
Reading File
Excellent content. Let me read the chemotherapy/hormonal/targeted therapy, follow-up, hereditary, screening sections now.
Reading File
Reading File
I now have comprehensive content from all the key sections. Let me also quickly read the screening section and the axilla management section.
Reading File
Reading File
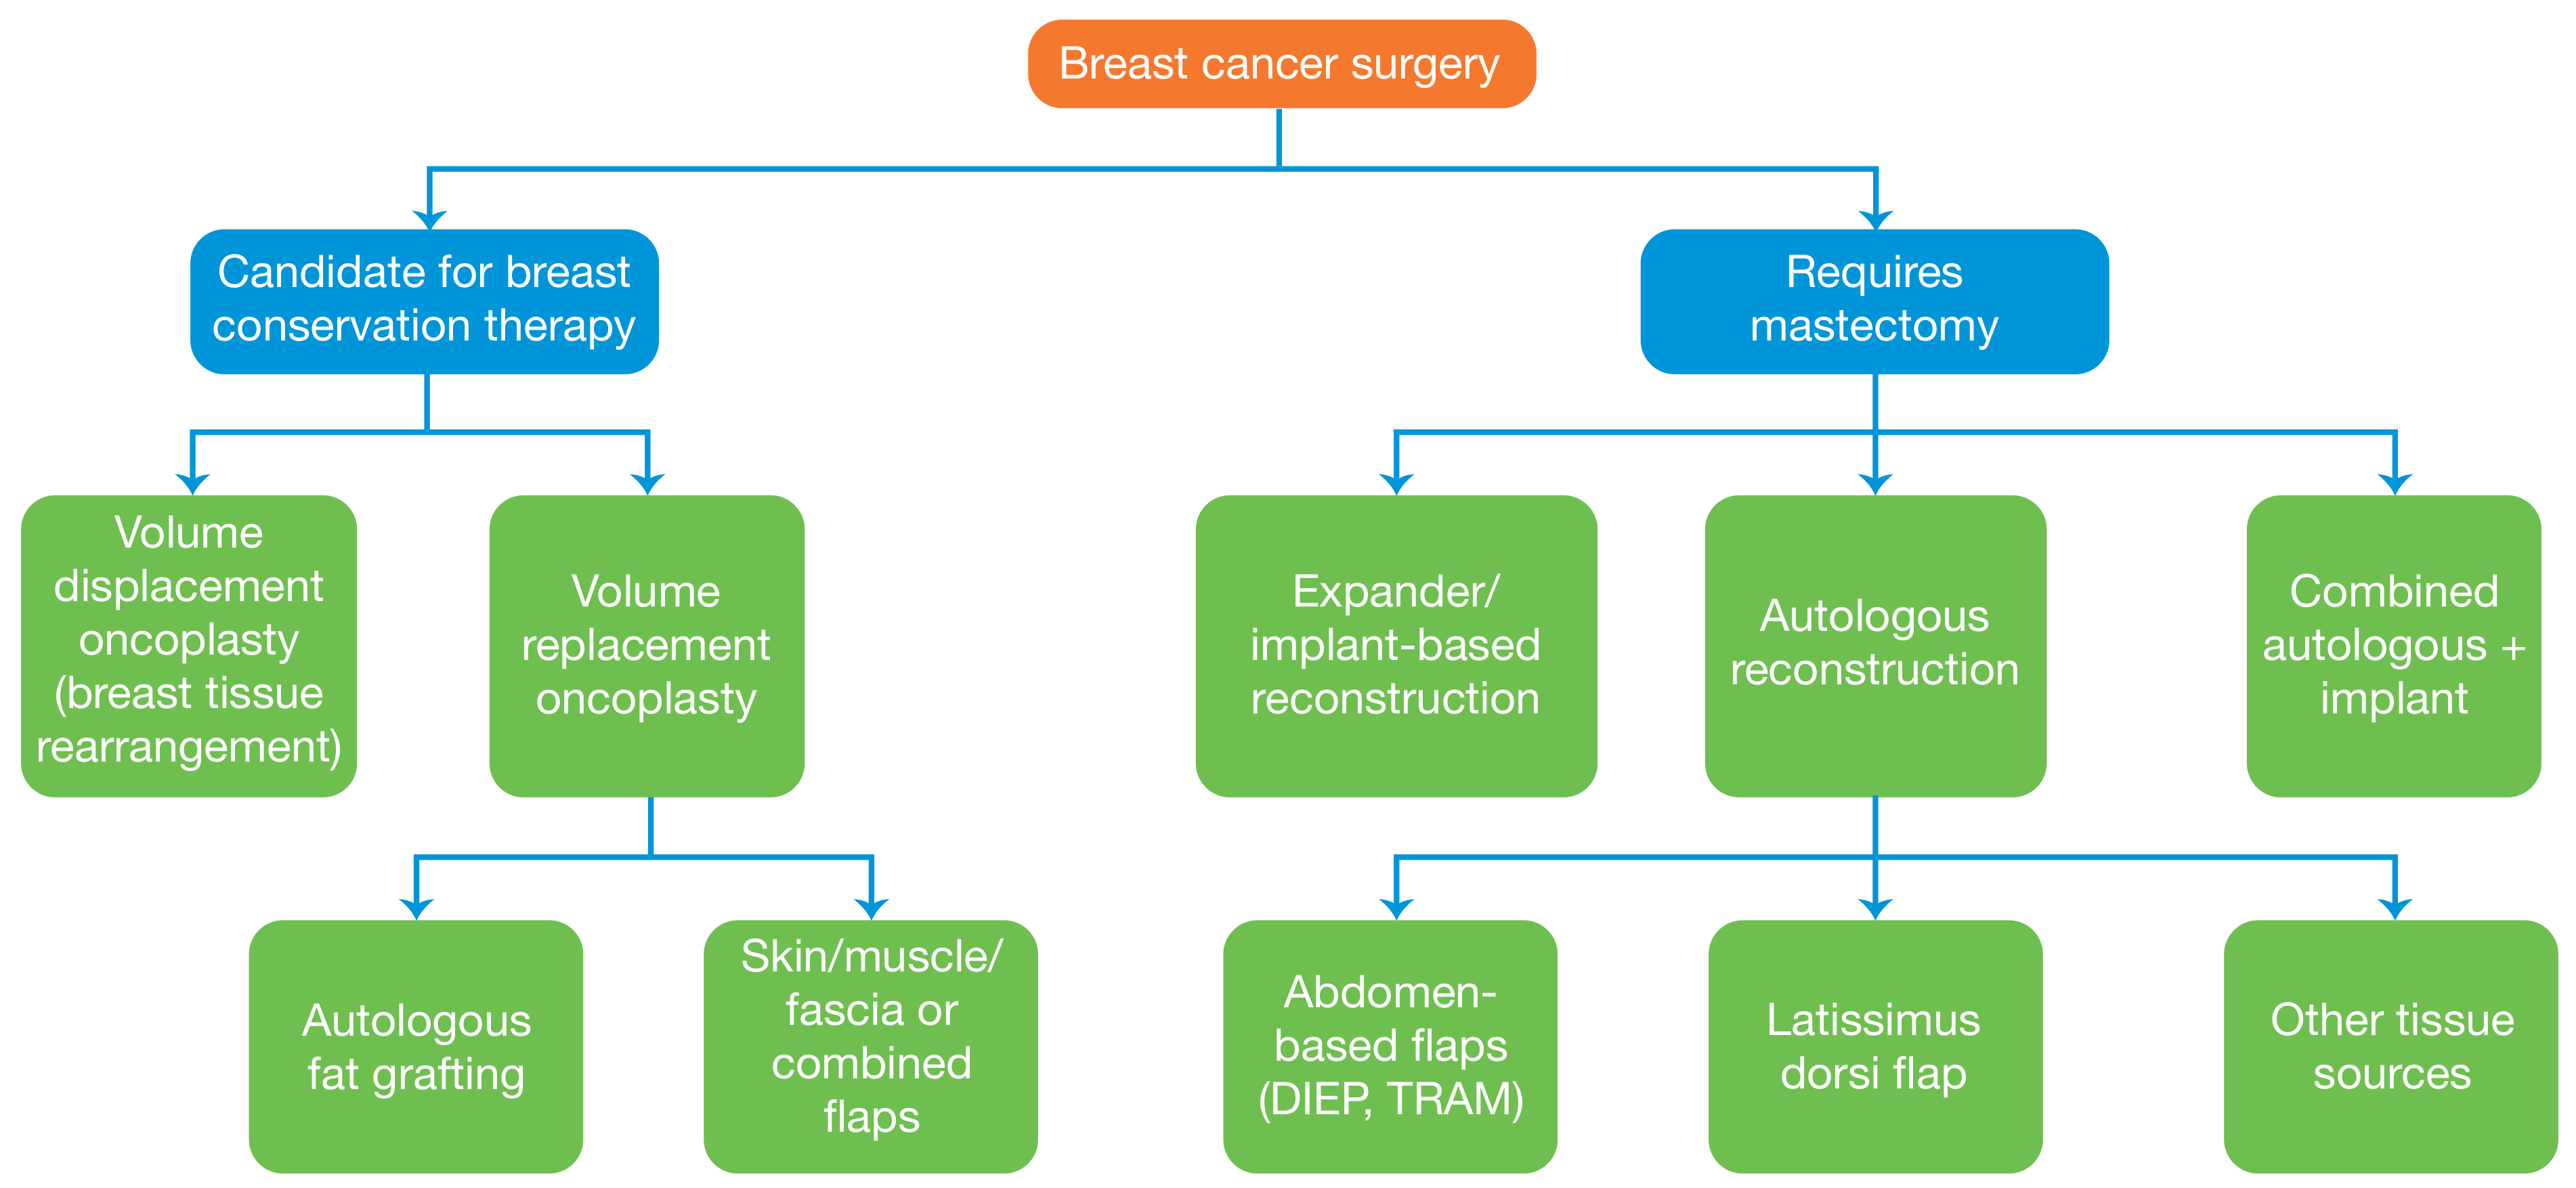
I now have all the content needed to compile a comprehensive answer. Let me also fetch the surgical options diagram which is directly relevant.
Loading Image
I now have everything needed for a thorough, well-structured answer. Here is the comprehensive content from Bailey & Love's Short Practice of Surgery, 28th Edition.
Breast Cancer - Bailey & Love's Short Practice of Surgery (28th Ed.)
1. Risk Factors
Risk factors are divided into modifiable and non-modifiable categories. The underlying mechanism for most is prolonged oestrogenic exposure.
Modifiable Risk Factors:
| Factor | Risk |
|---|---|
| Obesity (BMI >30) | RR = 1.29 in postmenopausal women |
| Nulliparity / first pregnancy >35 yrs | Increased risk |
| No breastfeeding (vs. >12 months) | Protective effect of breastfeeding is dose-dependent |
| HRT use >10 years | RR = 1.2 |
| Alcohol: light (<1 drink/day) | RR = 1.05 |
| Alcohol: moderate (3-4 drinks/day) | RR = 1.32 |
| Alcohol: heavy (>4 drinks/day) | RR = 1.46 |
| Tobacco (≥25 cig/day) | RR = 1.14 |
| Radiation exposure | RR = 6 |
Non-Modifiable Risk Factors:
| Factor | Risk |
|---|---|
| Age | Median age ~60 yrs (West); ~48 yrs (India/LMICs) |
| Sex | 0.5-1% of all breast cancers occur in males |
| Ethnicity | American white, African American <45 yrs, Ashkenazi Jews |
| One first-degree relative with BC | RR = 2 |
| Two first-degree relatives with BC | RR = 3 |
| Genetic (BRCA1/2) | 5-10% of all BCs are hereditary; BRCA1/2 = up to 70% of hereditary BCs |
| Early menarche <12 yrs | RR = 1.19 for age <11 yrs |
| Late menopause >55 yrs | ~3% increase in risk per year of delay |
2. Pathology
Breast carcinoma arises from:
- Milk ducts: 90% - ductal carcinoma
- Lobules: 10% - lobular carcinoma
In situ vs Invasive:
- In situ disease = confined to epithelium, no breach in basement membrane
- Invasive/infiltrative = breach through basement membrane
Grading (Modified Bloom-Richardson System):
Scores (1-3) are assigned for three variables:
- Tubule formation
- Nuclear pleomorphism
- Mitoses per HPF
- Grade I: Total score 3-5
- Grade II: Total score 6-7
- Grade III: Total score 8-9
Histological Types:
- Invasive NST (No Special Type): Most common
- Mucinous/colloid carcinoma: Better prognosis; cells produce abundant mucin
- Medullary carcinoma: Solid sheets of large cells, marked lymphocytic reaction
- Tubular carcinoma: Better prognosis
- Papillary carcinoma: Rare (0.5-1%), fibrovascular core, usually ER-positive, rarely spreads to lymph nodes
Receptor Status:
- ER, PR, HER2/neu, AR overexpression
- Ki-67 mitotic index reflects proliferation rate
3. Molecular Classification (Table 58.4)
| Subtype | Hormone Receptor | HER2/neu | Notes |
|---|---|---|---|
| Luminal A | ER/PR positive | Negative | Low Ki-67, best prognosis |
| Luminal B | ER/PR positive | Positive or negative | Higher Ki-67 |
| HER2-enriched | Negative | Positive | More aggressive |
| Triple-negative (TNBC) | Negative | Negative | BRCA1-associated; worst prognosis |
| Normal-like | Variable | Negative | Similar to Luminal A |
Gene array analysis (PAM-50) identifies these subtypes; immunohistochemistry is used as a surrogate when PAM-50 is unavailable.
4. Staging (AJCC TNM, 8th Edition)
T Category:
| T | Criteria |
|---|---|
| Tx | Cannot assess primary tumour |
| T0 | No evidence of primary tumour |
| Tis(DCIS) | Ductal carcinoma in situ |
| Tis(Paget's) | Paget's disease without associated invasive/in situ carcinoma |
| T1 | ≤20 mm (T1mi = ≤1 mm; T1a = >1 to ≤5 mm; T1b = >5 to ≤10 mm; T1c = >10 to ≤20 mm) |
| T2 | >20 mm to ≤50 mm |
| T3 | >50 mm |
| T4 | Any size with chest wall/skin extension; T4d = inflammatory carcinoma |
Key 8th Edition Points:
- LCIS is classified as a high-risk benign lesion, not a cancer
- Multiple synchronous tumours: (m) modifier
- Post-neoadjuvant status: (y) prefix
- Pathological complete response (pCR) = absence of tumour in breast and nodes
- Inflammatory carcinoma stays classified as such even after complete remission on NACT
- T1mi = invasive foci ≤1.0 mm; tumours >1 mm but <2 mm rounded up to 2 mm
The 8th edition also incorporates histological grade, ER/PR/HER2/Ki-67, multigene testing (Oncotype DX), and response to neoadjuvant therapy into prognostic staging.
5. Metastatic Work-up
- Locally advanced BC (T3, T4 / N2, N3): Contrast-enhanced CT chest/abdomen/pelvis + isotope bone scan
- Early BC (T1, T2, N0, N1): Metastatic work-up only if symptomatic or raised ALP
- PET-CT (18F-FDG) may be used for metastatic staging
6. Treatment - Multimodal Approach
Treatment is multimodal: surgery + systemic therapy (chemo, targeted, hormonal) + radiotherapy. A multidisciplinary team (MDT) is mandatory, including surgeon, radiologist, pathologist, radiation oncologist, medical oncologist, plastic surgeon, breast care nurse, and genetic counsellor.
A. Neoadjuvant Systemic Therapy (NAST)
Indications for NACT:
- Locally advanced BC (T3, T4 / N2, N3): to downsize tumour
- Selected early BC:
- To facilitate BCS
- HER2/neu-positive tumours
- Triple-negative BC (TNBC)
- Premenopausal women (<50 yrs)
- Axillary node metastasis
Neoadjuvant targeted therapy: Trastuzumab + pertuzumab for HER2/neu-positive tumours >5 mm.
Neoadjuvant hormonal therapy: For elderly/frail women with ER/PR-positive advanced tumours unfit for chemotherapy. Response takes 3-6 months to become clinically evident.
B. Surgery
Radical mastectomy (Halsted): Excision of breast + all axillary LN + pectoralis major and minor. Rarely indicated - causes excessive morbidity (limited shoulder movement, extensive lymphoedema) with no survival benefit over less radical surgery.
Modified Radical Mastectomy (MRM): Mastectomy + removal of level I, II, and III axillary LN.
Skin- and Nipple-Sparing Mastectomy: Option in DCIS and early BC when tumour is >1 cm from skin and >2 cm from nipple. Followed by reconstruction.
Breast Conservation Surgery (BCS):
- Removes tumour + 1-cm margin of normal tissue
- Specimen orientation: long suture = lateral; short suture = superior
- Positive margins → "cavity shave" re-excision
- All BCS patients receive radiotherapy: BCS + RT = Breast Conservation Therapy (BCT)
Contraindications to BCS:
- Multicentric tumour
- Diffuse microcalcifications on mammogram
- Large tumour-to-breast ratio
- Two positive surgical margins after re-excision
- Previous breast/chest wall radiation
- SLE or other collagen vascular disease
- Ankylosing spondylitis
- Severe orthopnoea (patient cannot lie on radiation table)
Wide Local Excision (WLE): Up to 20% of breast volume can be excised; >20% volume loss requires oncoplastic repair.
Oncoplasty:
- Volume displacement (level 1): Local breast tissue rearrangement
- Volume replacement (level 2): Distant/local flap
- Goal: Maintain shape and symmetry after wide-margin excision
C. Axilla Management
Sentinel Lymph Node Biopsy (SLNB):
- Standard of care for clinically node-negative axilla
- Uses dual tracers: radioisotope + blue dye (or fluorescein/ICG)
- If SLNB negative: no further axillary surgery needed
- If SLNB positive (1-2 nodes): axillary node dissection may be avoided in selected patients
Axillary Node Dissection (AND):
- Level I and II nodes routinely removed
- Level III dissection reserved for enlarged level I and II nodes
Post-NAST SLNB (targeted technique):
- A metal clip or India ink is applied to a positive node before NAST
- At surgery, the clipped/tattooed node is removed with SLNB
- Reduces false-negative rate if ≥3 sentinel nodes removed
D. Breast Reconstruction
Timing:
- Immediate: Patient wakes up with breast mound
- Delayed: 6-12 months post-adjuvant treatment
Implant-based: Silicone gel implants - prepectoral or subpectoral. Note: Radiotherapy post-implant causes high capsular contracture rates.
Autologous Tissue Flaps:
- Latissimus dorsi flap
- TRAM flap (transverse rectus abdominis myocutaneous)
- DIEP flap (deep inferior epigastric perforator) - most commonly used in the UK; requires microvascular skill; ~4 hours operative time
- Anterolateral thigh flap
For symmetry, a contralateral reduction/mastopexy may be performed simultaneously.
E. Adjuvant Radiotherapy
Indications:
- Locally advanced BC (T3, T4 / N1, N2, N3)
- Following all BCS
- After mastectomy if: tumour ≥5 cm; skin/chest wall involvement; LVI + grade 3; axillary LN positive
Dosing:
- Node-negative after BCS: 45-50.4 Gy in 25 fractions OR 40-42.5 Gy in 15-16 fractions (hypofractionation)
- Node-positive: locoregional RT covering chest wall, supraclavicular region, internal mammary nodes, and axilla
- Do not irradiate axilla after axillary node dissection - increases lymphoedema risk
APBI (Accelerated Partial Breast Irradiation) - ASTRO 2016 criteria:
- Women ≥50 years, T1 disease, negative margins (≥2 mm), invasive ductal carcinoma, no LVI, ER-positive
F. Adjuvant Systemic Therapy
Chemotherapy regimens:
- Anthracycline-based (AC/FAC) followed by taxane-based regimens
- HER2/neu-positive: add trastuzumab (targeted therapy)
Hormone Therapy:
- Tamoxifen (SERM): Used in premenopausal patients
- Low risk: 5 years
- High risk (node positive, tumour >5 cm, LVI): 10 years
- Aromatase inhibitors (anastrozole, letrozole, exemestane): Used in postmenopausal women
- Better relapse-free and overall survival vs. tamoxifen
- Associated with bone density loss; baseline bone scan required; bisphosphonates + Vit D + calcium given
7. Metastatic Breast Cancer (Stage IV)
Goals: palliation, quality of life, prevention of disabling complications, prolonging survival.
- Hormone receptor-positive + bony/limited visceral mets: Endocrine therapy preferred
- Hormone receptor-negative / hormone-refractory / visceral crisis: Systemic chemotherapy
- Bony metastasis: Palliative RT to weight-bearing areas (vertebra, femur) + bisphosphonates
- Symptomatic pleural effusion: Intercostal drainage + pleurodesis
- Solitary visceral metastasis (good performance status): Surgical resection may be considered
- Oral metronomic chemotherapy: Cytostatic + antiangiogenic; helps quality of life
8. Hereditary Breast Cancer (HBC)
- HBC (identifiable mutation): 5-10% of all BCs
- Familial BC (no known mutation): 20-30% of all BCs
- HBC features: more aggressive, earlier onset, more often multicentric and bilateral
BRCA1 (17q21):
- 50-85% lifetime risk of breast cancer
- Up to 40% risk of ovarian cancer
- Breast cancers mostly TNBC
BRCA2 (13q12.3):
- 50-60% lifetime risk of breast cancer
- 20% risk of ovarian cancer
- Also associated with prostate, colon, gallbladder, bile duct, stomach, and pancreatic cancer
- More common in male breast cancer
Management of BRCA Mutation Carriers:
- Bilateral risk-reducing mastectomy with immediate reconstruction: reduces BC risk by 90%
- Chemoprophylaxis (tamoxifen or anastrozole): reduces risk by ~50%
- Bilateral salpingo-oophorectomy: offered to premenopausal women after completing family (~35-40 years)
Indications for Genetic Risk Evaluation (Summary box 58.5):
- Known pathogenic variant in family
- BC diagnosed ≤50 years
- TNBC diagnosed ≤60 years
- Two breast cancer primaries
- BC + relative with BC ≤50 yrs, ovarian cancer, male BC, pancreatic or high-grade prostate cancer
- BC with two or more affected relatives
- Male breast cancer
9. Breast Cancer in Pregnancy
- Associated with aggressive biology (TNBC)
- Imaging: USS, mammogram + chest X-ray with abdominal shielding; MRI without gadolinium if bone/brain mets suspected
- Avoid: CT and PET-CT (high radiation dose)
- Surgery can be performed in any trimester
- Genetic counselling should be offered
10. Follow-up of Operable Breast Cancer
| Period | Frequency |
|---|---|
| First 2 years | Every 3 months |
| Years 3-5 | Every 6 months |
| Thereafter | Annually |
- Annual mammogram for all
- Annual contrast breast MRI for: implant patients, BRCA/other genetic mutation carriers
11. Screening
- UK: All women aged 50-70 years invited for mammographic screening every 3 years
- Screen-detected tumours: 90-95% long-term survival in high-income countries
- India: National multidisease screening for women aged 30-65 years (mouth, breast, cervix)
- In LMICs: Clinical breast examination (CBE) by trained healthcare professional + breast self-examination
- Suspicious mammogram lesion: image-guided biopsy; metal clip inserted for impalpable lesions; wire-guided excision if malignant
Source: Bailey and Love's Short Practice of Surgery, 28th Edition, Chapter 58 - The Breast
Recent Evidence Note: A 2025 meta-analysis (PMID 39878175) found that SLNB after NACT in clinically node-positive patients carries a higher false-negative rate than previously appreciated, reinforcing the importance of the targeted/clipped-node technique described above. A 2024 systematic review and meta-analysis (PMID 39370318) on surgical treatment in older breast cancer patients found that age alone should not drive decision-making, aligning with the MDT-based approach in Bailey & Love.
Tq
You're welcome! Feel free to ask anytime you need more detail on any section - staging, surgical techniques, chemo regimens, or anything else from Bailey & Love. Good luck with your studies! 😊
Yes
It seems like your message got cut off! What would you like to know? Feel free to ask about any topic - breast surgery, another chapter from Bailey & Love, or anything else entirely.
This is a shared conversation. Sign in to Orris to start your own chat.