
Diarrhea
Reading File
The query "Diarrhea" is broad. Let me clarify what's needed before diving into research.
Asking for Preferences
What aspect of diarrhea are you interested in?
Searching sources...
Finding Sources
Finding Sources
Good results. Let me read the key sections - the dedicated diarrhea chapter from Sleisenger & Fordtran, the classification from Frameworks for Internal Medicine (which has a diagram), and the physiology section.
Reading File
Reading File
Reading File
Excellent. Let me now read the core definition/pathophysiology and clinical classification sections from the Sleisenger & Fordtran chapter, plus fetch the classification diagram.
Reading File
Loading Image
I have a very rich set of information. Let me read a bit more of the clinical classification section from the Sleisenger chapter to get the full osmotic vs secretory distinction and the watery/fatty/inflammatory breakdown.
Reading File
I now have comprehensive information to write a thorough overview and classification of diarrhea. Let me compile the full answer.
Diarrhea: Overview & Classification
Definition
Diarrhea is a symptom, not a disease, that can arise from many conditions. Clinically, it is defined as:
- Three or more loose or liquid bowel movements per day, or
- Stool weight > 200 g/day in Western populations (though this alone is insufficient - consistency matters too)
Fecal incontinence is often mistaken for diarrhea and must be distinguished, particularly in older adults. - Sleisenger & Fordtran's Gastrointestinal and Liver Disease
Pathophysiology
Diarrhea results from excess stool water due to abnormal net intestinal water and electrolyte transport.
Normally, the small intestine and colon absorb 99% of the ~9-10 L of fluid that passes the ligament of Treitz daily (from oral intake + endogenous secretions). A reduction of net water absorption by as little as 1% is sufficient to cause diarrhea.
Three fundamental mechanisms underlie all diarrhea:
- Altered mucosal transport - impaired water/electrolyte absorption in the small intestine or colon
- Rapid transit - reduced contact time between luminal contents and the absorptive epithelium
- Altered stool composition - changes in insoluble fecal solids (e.g., steatorrhea reduces water-binding capacity)
Classification
Classification Diagram
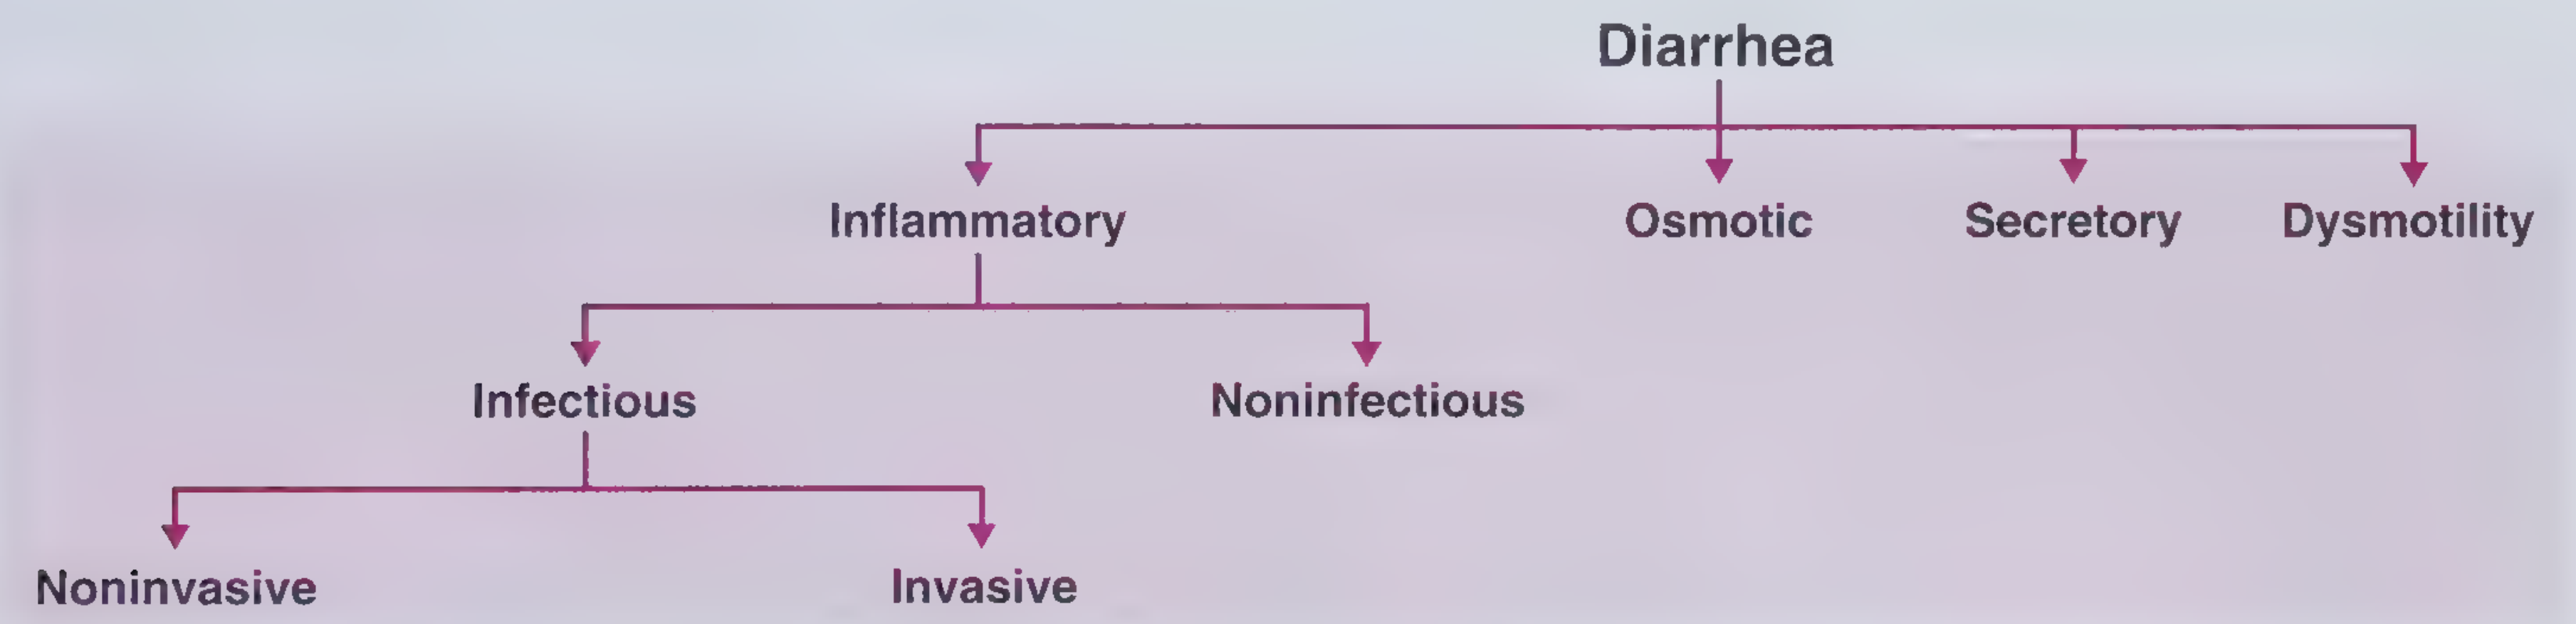
Classification of diarrhea by mechanism - Frameworks for Internal Medicine
1. Pathophysiologic Classification
A. Osmotic Diarrhea
Caused by nonabsorbable solutes in the intestinal lumen that retain water osmotically.
- Mechanism: Unabsorbed solutes create an osmotic gradient, drawing water into the lumen
- Example: Lactase deficiency - undigested lactose remains in the lumen; colonic bacteria may further degrade it to more osmotically active particles
- Key feature: Stops with fasting (the offending solute is removed)
- Other causes: Lactulose, sorbitol, magnesium-containing laxatives, malabsorption syndromes
B. Secretory Diarrhea
Caused by excessive secretion of fluid by intestinal crypt cells, rather than failure of absorption.
- Mechanism: Pathogenic bacteria (e.g., Vibrio cholerae, enterotoxigenic E. coli) produce toxins that activate adenylyl cyclase → ↑ cAMP → opens Cl⁻ channels in the apical membrane → massive Cl⁻ and water secretion into the lumen
- Endogenous causes: Endocrine tumors (VIPoma, carcinoid, gastrinoma), excess bile acids reaching the colon, inflammatory mediators
- Key feature: Persists with fasting; large-volume, watery stools
- Stool osmotic gap: Normal (< 50 mOsm/kg) - electrolytes account for the osmolality
C. Inflammatory Diarrhea
Caused by mucosal disruption with exudation of serum into the lumen, plus destruction of the absorptive epithelium leading to malabsorption.
- Mechanism: Invasion of or damage to the intestinal mucosa
- Features: Abdominal pain, fever, tenesmus, bloody or mucoid stools; fecal leukocytes/calprotectin/lactoferrin elevated
- Infectious: Invasive bacteria (Shigella, Salmonella, Campylobacter, C. difficile), parasites (Entamoeba histolytica)
- Noninfectious: IBD (Crohn's disease, ulcerative colitis), ischemic colitis, radiation colitis
- Life-threatening complication: Toxic megacolon (abdominal distention + systemic toxicity - fever, tachycardia, delirium)
D. Dysmotility Diarrhea
Caused by abnormal intestinal motility that impairs adequate contact time between luminal contents and the absorptive surface.
- Rapid transit ("intestinal hurry"): Oral-cecal transit may be as short as 10 minutes in severe cases; also adds an osmotic component due to nutrient malabsorption
- Causes: Diabetes mellitus (enteric neuropathy), post-vagotomy, hyperthyroidism, IBS, endocrine tumors
- Slow transit: Can paradoxically cause secretory diarrhea via small intestinal bacterial overgrowth (SIBO) - best example is scleroderma
Most etiologies of diarrhea act through a combination of these mechanisms. Pure osmotic or secretory diarrhea is uncommon in clinical practice. - Sleisenger & Fordtran's
2. Clinical Classification
| Criterion | Categories |
|---|---|
| Duration | Acute (< 4 weeks) vs. Chronic (≥ 4 weeks) |
| Volume | Large-volume (small bowel/proximal) vs. Small-volume (colorectal) |
| Stool character | Watery vs. Fatty (steatorrhea) vs. Inflammatory (bloody/mucoid) |
| Mechanism | Osmotic vs. Secretory |
By Duration
- Acute diarrhea: Most commonly infectious (viral > bacterial > parasitic); usually self-limited within 1-2 days
- Chronic diarrhea: Defined as loose stools for ≥ 4 weeks; affects ~6.6% of the population annually; causes include IBD, IBS, malabsorption, endocrine disorders, medications
By Volume/Location
- Large-volume (small bowel): Watery, voluminous; often periumbilical cramping; no blood
- Small-volume (colorectal): Frequent small stools; urgency, tenesmus; may contain blood/mucus
By Stool Character (Watery / Fatty / Inflammatory)
- Watery: Osmotic or secretory mechanism; most common subtype
- Fatty (steatorrhea): Malabsorption - greasy, floating, foul-smelling stools; causes include pancreatic exocrine insufficiency, celiac disease, Whipple's disease
- Inflammatory: Blood and/or mucus in stool; suggests mucosal damage
3. Osmotic Gap to Distinguish Osmotic from Secretory
Stool osmotic gap = Measured stool osmolality - 2 × (stool [Na⁺] + stool [K⁺])
| Gap | Interpretation |
|---|---|
| > 125 mOsm/kg | Osmotic diarrhea (poorly absorbed solutes present) |
| < 50 mOsm/kg | Secretory diarrhea (electrolytes account for osmolality) |
Metabolic Consequences
Diarrheal fluid is rich in:
- HCO₃⁻ (from salivary, pancreatic, intestinal secretions) - loss causes hyperchloremic, normal anion gap metabolic acidosis
- K⁺ (flow-rate-dependent colonic secretion) - loss causes hypokalemia
- Water - loss causes volume depletion and circulatory collapse in severe cases (e.g., cholera)
Epidemiology
- Acute gastroenteritis affects 7.5% of Americans in any given month
- Causes >3.5 million outpatient visits, >180,000 hospitalizations, and ~3,000 deaths per year in the USA
- Chronic diarrhea affects 6.6% of the population annually
- In developing countries, acute infectious diarrhea remains a leading cause of child mortality
Sources: Sleisenger & Fordtran's Gastrointestinal and Liver Disease; Frameworks for Internal Medicine; Costanzo Physiology 7th Edition
This is a shared conversation. Sign in to Orris to start your own chat.