How to use you properly

Here's how to get the best out of me:

What I Can Do

Research & Knowledge
  • Answer questions across all domains — science, history, law, technology, culture, math, and more
  • Search the web for current information (news, prices, recent events)
  • Search and summarize peer-reviewed medical literature (PubMed)
  • Look up content in a medical textbook library for clinical questions
Document & File Work
  • Create and edit Word documents (.docx), PowerPoint presentations (.pptx), Excel spreadsheets (.xlsx), and PDFs
  • Read and extract content from uploaded files (PDFs, Word docs, spreadsheets, images, etc.)
  • Generate images and visual diagrams from descriptions
Code & Data
  • Write, debug, and explain code in any language
  • Run code in a live sandbox (Python, Node.js, shell scripts, etc.)
  • Analyze data, generate charts, and produce reports

How to Get the Best Results

Be specific about your goal. Instead of "tell me about diabetes," try "explain the mechanism of insulin resistance in Type 2 diabetes for a medical student."
Mention the format you want. "Give me a bullet-point summary," "write this as a formal email," or "create a Word document" all produce different outputs.
Attach files when relevant. If you have a PDF, spreadsheet, or image, attach it and I'll work with it directly.
Ask follow-up questions. I iterate — if my first answer misses the mark, tell me what to adjust.
For medical questions, I consult authoritative textbooks and PubMed automatically before answering, so you'll get evidence-based responses.

Tips

  • You can ask me to do complex multi-step tasks ("research X, then create a PowerPoint from the findings")
  • I'll ask clarifying questions when your request is ambiguous — this saves time
  • I can run things in parallel (e.g. research multiple topics at once)
  • If I make a mistake, just point it out and I'll correct it
What would you like to work on?

Let’s study copd

Asking for Preferences

What's your background level? · What aspect of COPD do you want to focus on?

Reading File
Finding Sources
Searching PubMed

"chronic obstructive pulmonary disease"[MeSH Terms] AND "management"[MeSH Terms]

Good — I have strong textbook sources. Let me read the core sections in parallel.
Reading File
Reading File
Reading File
Now let me get the Fishman's detailed content on pathophysiology and staging:
Reading File
Finding Sources
Searching Images

COPD emphysema pathology diagram

I have comprehensive content. Let me now build the full study guide.

COPD — Complete Medical Student Study Guide


1. Definition

Chronic Obstructive Pulmonary Disease (COPD) is a progressive, not fully reversible airflow limitation caused by an abnormal inflammatory response of the lung to noxious particles or gases — most commonly cigarette smoke. It most commonly manifests as emphysema and/or chronic bronchitis, which frequently coexist.
Key distinction from asthma: COPD obstruction is not fully reversible with treatment.

2. Epidemiology & Risk Factors

FactorDetails
#1 Risk FactorCigarette smoking (15–30% of smokers develop COPD*)
Geneticα₁-antitrypsin (AAT) deficiency → panacinar emphysema
EnvironmentalOccupational dust, air pollution, biomass fuel smoke
AgeTypically older patients (>40 years)
Burden3rd most common cause of death in the US; >$40 billion/year in healthcare costs
*Note: CT studies now show progressive bronchial wall changes and lung tissue loss even in smokers with normal spirometry, challenging the classic 15–30% figure — Katzung's Pharmacology, 16th Ed.

3. Pathology: Two Major Subtypes

A. Emphysema ("Pink Puffer")

  • Definition: Permanent enlargement of airspaces distal to terminal bronchioles with destruction of alveolar walls
  • Mechanism: Proteases (especially neutrophil elastase) destroy elastic support → loss of elastic recoil → air trapping
  • Protease–antiprotease imbalance is the core concept: smoking activates neutrophils/macrophages → ↑ elastase; simultaneously, smoke inactivates α₁-antitrypsin
SubtypeLocationCause
Centriacinar (centrilobular)Upper lobes; central part of acinusSmoking (most common)
Panacinar (panlobular)Lower lobes; entire acinusAAT deficiency
ParaseptalSubpleuralAssociated with spontaneous pneumothorax
Clinical features:
  • Barrel chest (increased AP diameter)
  • Pursed-lip breathing, tripod positioning
  • Dyspnea >> cough
  • Relatively preserved oxygenation at rest ("pink puffer")
  • Hyperresonance on percussion

B. Chronic Bronchitis ("Blue Bloater")

  • Definition (clinical): Productive cough for ≥3 consecutive months in ≥2 consecutive years
  • Mechanism: Mucus overproduction from hyperplasia of tracheal/large airway mucous glands + goblet cell metaplasia; airway obstruction from small airway inflammation (chronic bronchiolitis)
  • Reid index (gland thickness / bronchial wall thickness) is increased (>0.4)
  • Histology: Enlarged mucus glands, goblet cell metaplasia, inflammation, bronchiolar wall fibrosis
Clinical features:
  • Prominent productive cough
  • Cyanosis (hypoxemia + hypercapnia → "blue bloater")
  • Frequent respiratory infections (impaired mucociliary clearance → persistent Haemophilus influenzae infection)
In practice, most patients have mixed features of both subtypes.

4. Pathophysiology

The core defect is obstructive ventilatory pattern:
ParameterCOPDNormal
FEV₁↓↓Normal
FVCNormal or mildly ↓Normal
FEV₁/FVC ratio< 0.70 (post-bronchodilator)≥ 0.70
TLC↑ (air trapping)Normal
RV↑↑Normal
DLCO↓ (emphysema destroys alveolar surface)Normal
V/Q mismatch is the central gas exchange defect:
  • Poorly ventilated alveoli receive blood → shunt-like effect → ↓ PaO₂
  • Compensatory hyperventilation (if possible) → ↓ PaCO₂ in early disease
  • As disease progresses → hypercapnia (CO₂ retention) + hypoxemia
Clinical physiology case (Costanzo Physiology): A 65-year-old with 40 pack-years had PaO₂ = 60 mmHg vs. calculated PAO₂ = 113 mmHg. The A-a gradient confirms V/Q mismatch. His low PaCO₂ (30 mmHg) reflects compensatory hyperventilation from hypoxic drive. FEV₁/FVC < 0.70 confirms obstructive disease.

5. GOLD Staging (Spirometry-Based)

Based on post-bronchodilator FEV₁ % predicted (all require FEV₁/FVC < 0.70):
GOLD GradeSeverityFEV₁ % predicted
GOLD 1Mild≥ 80%
GOLD 2Moderate50–79%
GOLD 3Severe30–49%
GOLD 4Very Severe< 30%
Staging also incorporates symptom burden (mMRC dyspnea scale or CAT score) and exacerbation history to guide treatment.

6. Clinical Features & Diagnosis

Symptoms:
  • Progressive exertional dyspnea (cardinal symptom)
  • Chronic productive cough and sputum
  • Wheezing
Signs:
  • Barrel chest, prolonged expiratory phase
  • Use of accessory muscles
  • Decreased breath sounds, wheeze on auscultation
  • Cyanosis (in bronchitic type)
  • Cor pulmonale (RV failure from pulmonary HTN) in advanced disease → JVD, peripheral edema
Investigations:
TestFinding
SpirometryFEV₁/FVC < 0.70 (confirmatory)
CXRHyperinflation, flattened diaphragms, bullae
CT chestGold standard for emphysema subtype; detects bullae, air trapping
ABG↓ PaO₂, ↑ or ↓ PaCO₂ depending on stage
α₁-AT levelScreen if young, non-smoker, or lower-lobe predominant emphysema
CBCSecondary polycythemia in chronic hypoxemia
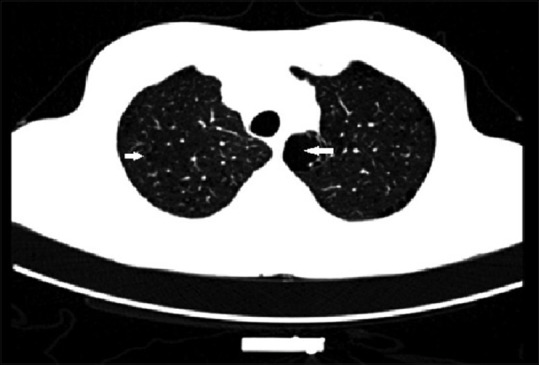
CT imaging of COPD — centrilobular emphysema:
COPD CT scan showing centrilobular emphysema with focal low-attenuation areas and paraseptal changes
CT chest: Centrilobular emphysema (focal low-attenuation intraparenchymal lucencies) and paraseptal emphysema (subpleural lucencies). Hallmark of smoking-related COPD.

7. Management

Non-Pharmacological (cornerstone)

  • Smoking cessation — only intervention proven to slow FEV₁ decline
  • Pulmonary rehabilitation
  • Supplemental O₂ if PaO₂ ≤55 mmHg (or ≤59 with cor pulmonale/polycythemia) → shown to reduce mortality
  • Vaccinations (influenza, pneumococcal, COVID-19)

Pharmacological (stepwise by symptom/severity)

SeverityDrug classExamples
All symptomaticSABA (rescue)Albuterol, salbutamol
Persistent dyspneaLAMATiotropium
Persistent dyspneaLABASalmeterol, formoterol
Severe/frequent exacerbationsLABA + LAMADual bronchodilator
High eosinophils + exacerbationsICS + LABAFluticasone/salmeterol
Triple therapyICS + LABA + LAMAMost severe patients
Chronic bronchitis + exacerbationsRoflumilast (PDE4 inhibitor)Reduces exacerbation frequency
Important caveats (Katzung, 16th Ed.):
  • ICS are less effective in COPD than asthma; associated with ↑ bacterial pneumonia risk → reserve for high exacerbation risk or high blood eosinophils
  • Low-dose theophylline failed to reduce exacerbations in a large RCT — no longer recommended as standard
  • Blood eosinophil count guides ICS use (low eosinophils = unlikely benefit; high eosinophils = reasonable benefit)

8. COPD Exacerbations

Definition: Acute worsening of respiratory symptoms beyond normal day-to-day variation, requiring a change in medication.
Triggers: Viral respiratory infections (most common), bacterial infections (H. influenzae, S. pneumoniae, M. catarrhalis), air pollution.
Management of acute exacerbation:
  1. O₂ — titrate to SpO₂ 88–92% (avoid over-oxygenation → hypercapnic drive suppression)
  2. SABA ± SAMA (nebulized bronchodilators)
  3. Systemic corticosteroids (oral prednisolone 40mg × 5 days)
  4. Antibiotics — β-lactams, doxycycline, azithromycin (cover H. influenzae) for purulent sputum or respiratory failure
  5. NIV (BiPAP) for hypercapnic respiratory failure (pH < 7.35, PaCO₂ > 45 mmHg)

9. Complications

ComplicationMechanism
Cor pulmonaleChronic hypoxemia → pulmonary vasoconstriction → right heart failure
Secondary polycythemiaChronic hypoxemia → ↑ EPO → ↑ RBC production
Spontaneous pneumothoraxRupture of subpleural blebs (especially paraseptal emphysema)
Respiratory failureProgressive loss of lung function
Malnutrition/cachexiaSystemic inflammation, increased WOB

10. Key Comparisons to Remember

FeatureEmphysemaChronic BronchitisAsthma
InflammationNeutrophilicNeutrophilicEosinophilic
ReversibilityIrreversiblePoorly reversibleReversible
Main complaintDyspneaCough/sputumEpisodic wheeze
PaO₂Relatively preserved (early)LowNormal (inter-episode)
PaCO₂Low (early), rises lateHighLow
PrognosisProgressiveProgressiveGenerally good

High-Yield Points for Exams

  • FEV₁/FVC < 0.70 post-bronchodilator = diagnostic criterion
  • Smoking cessation + long-term O₂ are the only interventions that reduce mortality
  • α₁-AT deficiency → panacinar emphysema, lower-lobe predominant
  • Roflumilast = PDE4 inhibitor, used when chronic bronchitis + frequent exacerbations
  • ICS use guided by eosinophil count (not routine in all COPD)
  • COPD exacerbations: treat with SABDs + steroids + antibiotics ± NIV; target SpO₂ 88–92%
  • Cor pulmonale = late complication; indicated by peripheral edema, JVD, elevated JVP

Sources: Robbins & Kumar Basic Pathology; Costanzo Physiology 7th Ed.; Katzung's Basic & Clinical Pharmacology 16th Ed.; Fishman's Pulmonary Diseases & Disorders.

Want me to go deeper on any section — pathophysiology, pharmacology, ABG interpretation in COPD, or practice questions?

Let’s study everything in detail in crisp, concise and conceptual way fromCOPD guidelines or gold that is required in MBBS level

Finding Sources
Searching the Web

GOLD 2024 2025 COPD guidelines summary MBBS key points

Searching PubMed

"COPD" AND "GOLD guidelines" AND "management"

Reading Web Page

https://pmc.ncbi.nlm.nih.gov/articles/PMC12097743/

Finding Sources
Finding Sources
Reading File
Reading File
Finding Sources
Finding Sources
Finding Sources
Searching Images

GOLD COPD spirometry staging ABE assessment

Excellent — I now have the actual GOLD 2025 figures from the official report. Let me fetch the key images and get the pharmacotherapy content.
Loading Image
Loading Image
Loading Image
Searching Images

COPD initial pharmacological treatment algorithm GOLD 2025 LABA LAMA ICS

Loading Image
Loading Image
Searching Images

COPD exacerbation management hospital assessment severity treatment algorithm

Loading Image
Searching Images

COPD exacerbation hospital treatment oxygen bronchodilator corticosteroid antibiotic NIV

Loading Image
I now have all the GOLD 2025 official figures + textbook content. Here's the complete, structured MBBS guide:

COPD — Complete GOLD 2025 Guide for MBBS

Based on GOLD 2025 Report + Harrison's + Katzung's + Robbins + Fishman's

CHAPTER 1 — DEFINITION & OVERVIEW

COPD = Common, preventable, treatable disease characterized by persistent respiratory symptoms and airflow limitation due to airway and/or alveolar abnormalities, usually caused by significant exposure to noxious particles/gases.
  • Airflow limitation is NOT fully reversible (contrast with asthma)
  • COPD is progressive — worsens with continued exposure
  • 3rd most common cause of death in the USA
Two main phenotypes (often coexist):
Emphysema ("Pink Puffer")Chronic Bronchitis ("Blue Bloater")
DefinitionPermanent airspace enlargement distal to terminal bronchioles with wall destructionProductive cough ≥3 months/year for ≥2 consecutive years
MechanismNeutrophil elastase destroys alveolar walls → loss of elastic recoilMucus gland hyperplasia + goblet cell metaplasia + small airway inflammation
Gas exchangeRelatively preserved O₂ (early)Hypoxemia + hypercapnia
SubtypesCentriacinar (smoking), Panacinar (AAT deficiency), Paraseptal—

CHAPTER 2 — DIAGNOSIS & ASSESSMENT

Step 1 — Suspect COPD

Suspect in any patient with:
  • Chronic dyspnea (especially exertional)
  • Chronic cough ± sputum
  • History of exposure to risk factors (smoking, biomass fuel, occupational dust)
  • Age >40 years
Key risk factors:
  • Cigarette smoking (#1)
  • Indoor/outdoor air pollution
  • α₁-antitrypsin (AAT) deficiency → panacinar emphysema, lower-lobe, young non-smokers
  • Occupational exposure, recurrent childhood infections

Step 2 — Spirometry (Confirmatory)

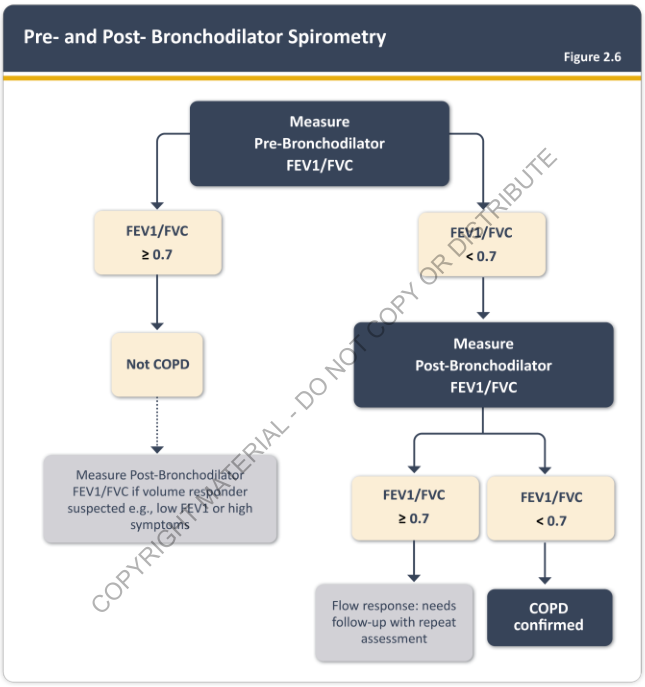
GOLD 2025 Spirometry Algorithm:
Pre- and Post-Bronchodilator Spirometry Flowchart — GOLD 2025 Fig 2.6
Key rules (GOLD 2025 update):
  • Pre-BD FEV₁/FVC ≥ 0.7 → NOT COPD (rule out)
  • Pre-BD FEV₁/FVC < 0.7 → Measure Post-BD spirometry for confirmation
  • Post-BD FEV₁/FVC < 0.7 → COPD confirmed
  • If post-BD FEV₁/FVC normalizes → "flow responder" → needs follow-up (may develop COPD)
  • Do NOT use bronchodilator reversibility testing to guide therapeutic decisions (GOLD 2025)
Spirometry pattern in COPD:
ParameterCOPD
FEV₁/FVC< 0.70 (diagnostic criterion)
FEV₁ % predicted↓ (grades COPD severity)
FVCNormal or mildly ↓
TLC / RV↑ (air trapping, hyperinflation)
DLCO↓ in emphysema (alveolar surface destroyed)

Step 3 — GOLD Grading (Airflow Obstruction Severity)

Based on post-BD FEV₁ % predicted (all require FEV₁/FVC < 0.70):
GOLD GradeSeverityFEV₁ % predicted
GOLD 1Mild≥ 80%
GOLD 2Moderate50–79%
GOLD 3Severe30–49%
GOLD 4Very Severe< 30%

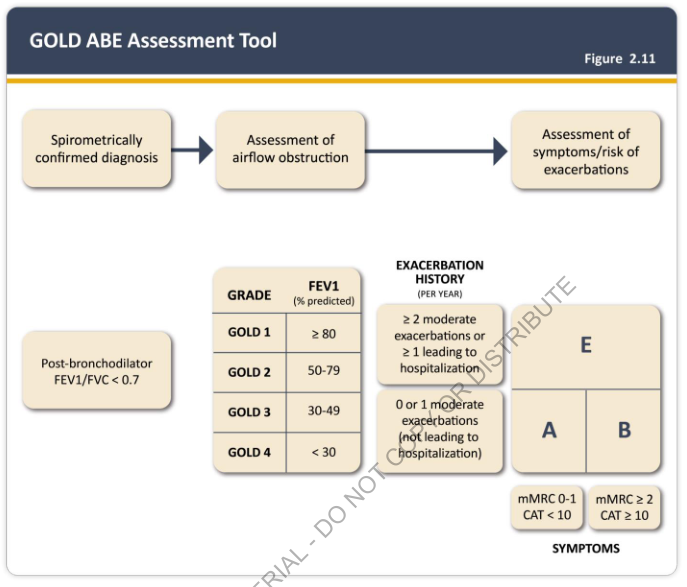
Step 4 — GOLD ABE Assessment (Symptom + Exacerbation Risk)

The GOLD ABE Tool — Fig 2.11 (GOLD 2025):
GOLD ABE Assessment Tool — GOLD 2025 Fig 2.11
Symptom tools:
  • mMRC 0–1 / CAT < 10 = low symptoms
  • mMRC ≥ 2 / CAT ≥ 10 = high symptoms
Group definitions:
GroupExacerbations/yearSymptomsSummary
A0–1 moderate (no hospitalization)Low (mMRC 0-1, CAT <10)Low risk, few symptoms
B0–1 moderate (no hospitalization)High (mMRC ≥2, CAT ≥10)Low risk, more symptoms
E≥2 moderate OR ≥1 leading to hospitalizationAnyHigh exacerbation risk
GOLD 2025 simplified from ABCD to ABE — "E" stands for Exacerbations, replacing the old C and D groups.
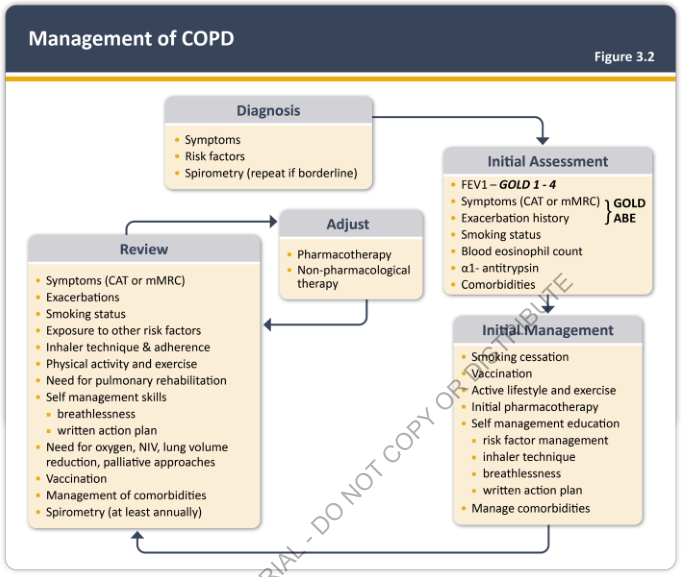
Overall Initial Assessment includes:
  • FEV₁ (GOLD 1–4)
  • Symptoms (CAT/mMRC) + Exacerbation history → GOLD ABE
  • Smoking status
  • Blood eosinophil count (guides ICS use)
  • α₁-antitrypsin level (if indicated)
  • Comorbidities

CHAPTER 3 — MANAGEMENT OF STABLE COPD

The GOLD Management Cycle

GOLD COPD Management Cycle — Fig 3.2
Cycle: Diagnose → Initial Assessment → Initial Management → Review → Adjust → Review (repeat)

Non-Pharmacological (Always First)

InterventionEvidence
Smoking cessationONLY intervention that slows FEV₁ decline; reduces mortality
VaccinationsInfluenza (annual), pneumococcal, COVID-19, Tdap, RSV
Pulmonary rehabilitationImproves exercise tolerance + quality of life
Long-term O₂ therapy (LTOT)Indicated if PaO₂ ≤55 mmHg, or ≤59 with cor pulmonale/polycythemia; reduces mortality
Active lifestyle/exerciseSlows functional decline
Self-management educationInhaler technique, written action plan, breathlessness management

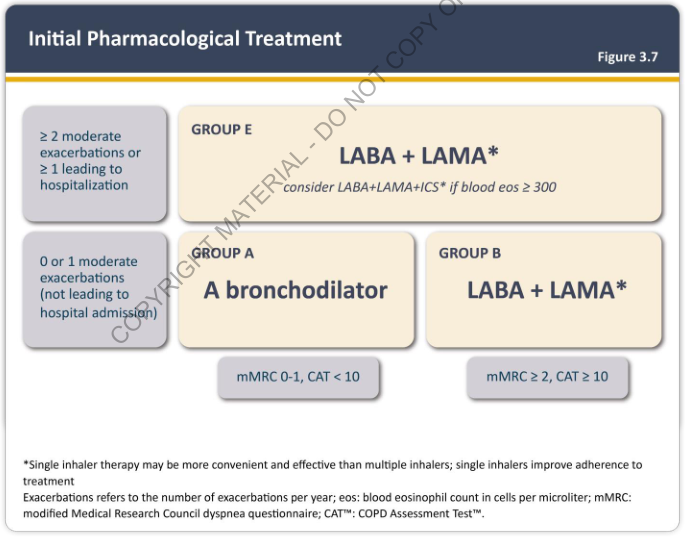
Initial Pharmacological Treatment

Initial Pharmacological Treatment — GOLD 2025 Fig 3.7
GroupInitial Treatment
AA single bronchodilator (SABA or LAMA)
BLABA + LAMA (dual bronchodilator)
ELABA + LAMA ± ICS if blood eos ≥ 300 cells/μL
Single-inhaler combination therapy preferred for adherence and convenience.

Follow-up Pharmacological Treatment

If initial response is adequate — maintain current therapy.
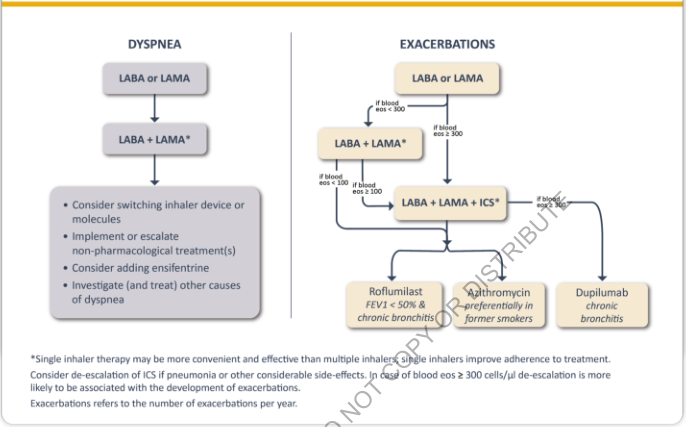
If inadequate — target the predominant "treatable trait":
Follow-up Pharmacological Treatment — GOLD 2025 (Dyspnea vs Exacerbations)
For DYSPNEA:
  • LABA or LAMA → LABA + LAMA → Consider switching inhaler/molecules, add ensifentrine, investigate other causes
For EXACERBATIONS (eosinophil-guided):
  • LABA or LAMA
    • Blood eos < 300 → LABA + LAMA
    • Blood eos ≥ 300 → LABA + LAMA + ICS (triple)
  • From LABA + LAMA:
    • Blood eos ≥ 100 → escalate to LABA + LAMA + ICS
  • From LABA + LAMA + ICS, if still exacerbating:
    • FEV₁ < 50% + chronic bronchitis → add Roflumilast (PDE4 inhibitor)
    • Non-smoker/ex-smoker → add Azithromycin
    • Blood eos ≥ 300 + chronic bronchitis → add Dupilumab (new 2025 biologic)

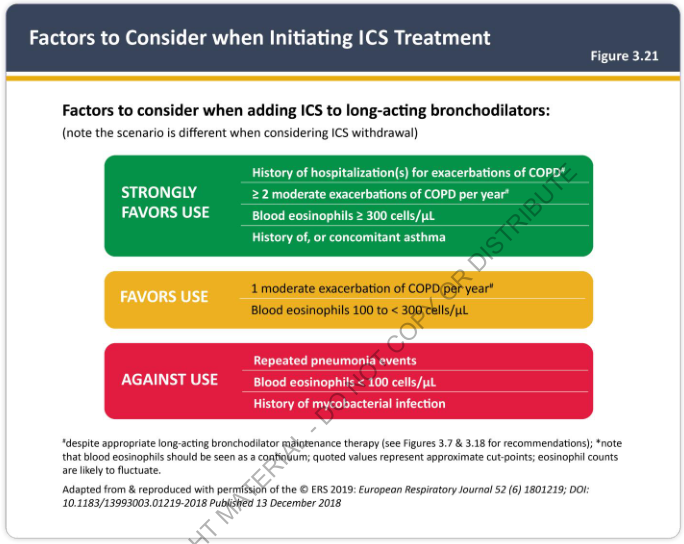
When to Use ICS — Decision Guide

Factors to Consider When Initiating ICS — GOLD 2025 Fig 3.21
ICS DecisionCriteria
Strongly favors useHospitalization for COPD exacerbation; ≥2 moderate exacerbations/year; eos ≥300; history of asthma
Favors use1 moderate exacerbation/year; eos 100–299
Against useRepeated pneumonia; eos <100; history of mycobacterial infection
ICS is not routine in COPD — less effective than in asthma, associated with ↑ pneumonia risk. Use only when indicated.

Drug Classes Summary

ClassDrug examplesRole
SABASalbutamol (albuterol), terbutalineRescue (all patients)
SAMAIpratropiumRescue, can combine with SABA
LABASalmeterol, formoterol, indacaterolMaintenance, reduce dyspnea
LAMATiotropium, umeclidinium, glycopyrroniumMaintenance, reduce exacerbations
ICSFluticasone, budesonide, beclomethasoneOnly with LABA when indicated
RoflumilastRoflumilastPDE4 inhibitor; chronic bronchitis + FEV₁ <50%, frequent exacerbations
AzithromycinAzithromycinMacrolide; ex-smokers with frequent exacerbations
DupilumabDupilumabIL-4/IL-13 biologic; eos ≥300 + chronic bronchitis (GOLD 2025 new)
EnsifentrineEnsifentrineDual PDE3/4 inhibitor; dyspnea not controlled on dual BD (GOLD 2025 new)
LTOTO₂PaO₂ ≤55 mmHg (or ≤59 with complications)

CHAPTER 4 — COPD EXACERBATIONS

Definition

ECOPD (Exacerbation of COPD) = Acute worsening of respiratory symptoms (dyspnea, cough, sputum) beyond normal daily variation, requiring a change in medications.
Triggers:
  • Viral infections (most common — rhinovirus, influenza, RSV, SARS-CoV-2)
  • Bacterial infections — H. influenzae, S. pneumoniae, M. catarrhalis
  • Air pollution, cold air

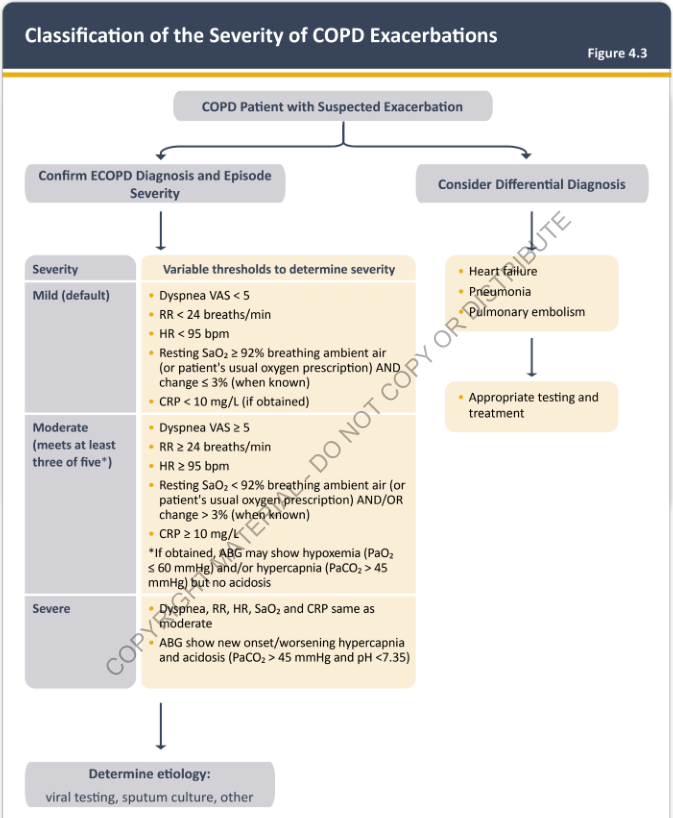
Classification of Severity — GOLD 2025

Classification of Severity of COPD Exacerbations — GOLD 2025 Fig 4.3
SeverityCriteria
MildDyspnea VAS <5, RR <24/min, HR <95 bpm, SpO₂ ≥92%, CRP <10 mg/L
Moderate≥3 of: VAS ≥5, RR ≥24, HR ≥95, SpO₂ <92%, CRP ≥10; ABG: hypoxemia/hypercapnia without acidosis
SevereSame as moderate + ABG: PaCO₂ >45 mmHg AND pH <7.35 (acidosis)
Differential diagnoses to exclude:
  • Heart failure (most common mimic)
  • Pneumonia
  • Pulmonary embolism

Management of Exacerbation

Mild (outpatient):
  • Increase bronchodilators (SABA ± SAMA)
  • Short course oral corticosteroids (prednisolone 40 mg × 5 days)
  • Antibiotics if: purulent sputum, CRP ↑, severe/hospitalized
Moderate–Severe (hospital):
InterventionDetails
O₂Target SpO₂ 88–92% (Venturi mask preferred); avoid over-oxygenation (suppresses hypoxic drive)
Nebulized SABASalbutamol 2.5–5 mg q20min initially
Nebulized SAMAIpratropium 0.5 mg
Systemic corticosteroidsPrednisolone 40 mg/day × 5 days (reduces treatment failure, shortens hospital stay)
Antibioticsβ-lactams (amoxicillin-clavulanate), doxycycline, or azithromycin (cover H. influenzae); given for purulent exacerbations or moderate/severe disease
NIV (BiPAP)First choice for hypercapnic respiratory failure: pH <7.35 + PaCO₂ >45 mmHg; reduces intubation rate, mortality
Invasive ventilationIf NIV fails or contraindicated
HelioxHelium-oxygen mixture; reduces airway resistance (adjunct)
NIV is the cornerstone of managing acute hypercapnic COPD exacerbations — reduces need for intubation and ICU mortality.

Indications for Hospitalization

  • Severe dyspnea not responding to initial treatment
  • SpO₂ <90% or worsening hypoxemia
  • Confusion, altered mental status
  • Failure to manage at home
  • Serious comorbidities (pneumonia, arrhythmia, cor pulmonale)

Indications for ICU Admission

  • Severe dyspnea not responding to NIV
  • pH < 7.25 (severe acidosis)
  • Hemodynamic instability
  • Altered consciousness

CHAPTER 5 — COMORBIDITIES

COPD rarely exists in isolation. Common comorbidities to always assess:
ComorbidityRelevance
Cardiovascular disease#1 cause of death in COPD; triple therapy shown to reduce CV events
Lung cancerAnnual low-dose CT screening if ≥50 years + 20 pack-years smoking history
Pulmonary hypertensionChronic hypoxemia → vasoconstriction → cor pulmonale
Metabolic syndrome / DMCommon, may affect outcomes
OsteoporosisICS use + immobility + smoking; assess DEXA in appropriate patients
Anxiety/DepressionVery common; affects adherence and outcomes
Obstructive sleep apnea"Overlap syndrome" — worse hypoxemia, higher mortality if untreated

RAPID RECALL — HIGH-YIELD MBBS POINTS

TopicKey Fact
Diagnostic criterionPost-BD FEV₁/FVC < 0.70
GOLD grades1: ≥80%, 2: 50–79%, 3: 30–49%, 4: <30% (FEV₁ % predicted)
GOLD ABE groupsA = low symptoms, low risk; B = high symptoms, low risk; E = ≥2 exacerbations/year OR ≥1 hospitalization
Initial Rx Group ASingle bronchodilator
Initial Rx Group BLABA + LAMA
Initial Rx Group ELABA + LAMA ± ICS if eos ≥300
ICS useGuided by eosinophils — use only when indicated; avoid if eos <100
Mortality-reducing RxSmoking cessation + LTOT (PaO₂ ≤55 mmHg)
Exacerbation: O₂ targetSpO₂ 88–92% (NOT 95–98%)
NIVFor pH <7.35 + hypercapnia — reduces intubation and death
AntibioticsCover H. influenzae; use azithromycin (ex-smokers), β-lactams, or doxycycline
RoflumilastPDE4 inhibitor; FEV₁ <50% + chronic bronchitis + frequent exacerbations
DupilumabNew 2025; IL-4/IL-13 biologic; eos ≥300 + chronic bronchitis
AAT deficiencyPanacinar emphysema, lower lobes, young patients; test all with early/atypical COPD
Cor pulmonaleRV failure from chronic hypoxemia → pulmonary HTN
Hypercapnia onsetPaCO₂ rises when FEV₁ falls to ~20–25% predicted
GOLD 2025 newEnsifentrine (PDE3/4), Dupilumab, updated spirometry flowchart

Sources: GOLD 2025 Report (goldcopd.org); Harrison's Principles of Internal Medicine 21st Ed.; Katzung's Pharmacology 16th Ed.; Robbins & Kumar Basic Pathology; Fishman's Pulmonary Diseases & Disorders

Want me to go deeper on any specific chapter — ABG interpretation in COPD, cor pulmonale, specific drug mechanisms, or COPD vs asthma differentiation?This is the complete GOLD 2025-aligned COPD guide for MBBS, organized exactly as the guidelines are structured — with official figures pulled directly from the GOLD 2025 report. Here's what's covered:
Chapter 1 — Definition, phenotypes (emphysema vs chronic bronchitis) Chapter 2 — Diagnosis: spirometry algorithm (new GOLD 2025 pre/post-BD flowchart), GOLD grades 1–4, ABE assessment tool Chapter 3 — Stable COPD management: non-pharmacological, initial treatment by ABE group, follow-up treatment by treatable trait (dyspnea vs exacerbations), ICS decision guide, all drug classes Chapter 4 — Exacerbations: severity classification with objective criteria (VAS, RR, HR, SpO₂, CRP, ABG), full hospital management including O₂ targets, NIV, antibiotics Chapter 5 — Comorbidities + rapid recall table
Key GOLD 2025 updates highlighted: new ABE system (replacing ABCD), ensifentrine, dupilumab, and the updated spirometry flowchart. Let me know which section to drill deeper on.

Let’s study everything in detail in crisp, concise and conceptual way fromCOPD guidelines or gold that is required in MBBS level Mainly from diagnosis Assesment and management

Your credits are exhausted. Your daily credits reset tomorrow, or you can purchase a top-up for more.

Let’s study everything in detail in crisp, concise and conceptual way fromCOPD guidelines or gold that is required in MBBS level

You've asked for a focused deep dive on Diagnosis, Assessment, and Management from GOLD guidelines. Let me pull everything fresh and structured.Your credits are exhausted. Your daily credits reset tomorrow, or you can purchase a top-up for more.
This is a shared conversation. Sign in to Orris to start your own chat.