Here is a comprehensive case-based discussion for Roxanne's case, addressing all 7 learning objectives.
Case #3 — Trichuris trichiura (Whipworm) Infection in a Child
Learning Objective 1: Most Likely Etiology
Diagnosis: Trichuriasis (Trichuris trichiura infection)
Roxanne's presentation is a classic textbook case. The key clues pointing to this diagnosis are:
| Clinical Feature | Significance |
|---|
| 9-year-old from rural farming community | High-risk age group and setting |
| Plays barefoot in soil | Direct route of egg ingestion via soil-contaminated hands/food |
| Poor sanitation, unimproved latrine | Fecal-oral contamination of soil |
| Nearby stream for washing/drinking | Environmental egg contamination |
| Chronic diarrhea — watery and mucoid | Hallmark of colonic mucosal irritation by worms |
| Lower abdominal pain, RLQ tenderness | Cecal localization of adult worms |
| Weight loss, pallor, fatigue | Chronic blood loss + nutritional depletion |
| Conjunctival pallor | Anemia |
| High community prevalence of intestinal worms | Epidemiological support |
T. trichiura is the second most prevalent soil-transmitted helminth worldwide, infecting ~600–800 million people, predominantly in tropical, low-sanitation regions — exactly Roxanne's environment.
— Red Book 2021, Report of the Committee on Infectious Diseases
Learning Objective 2: Life Cycle & Pathogenesis
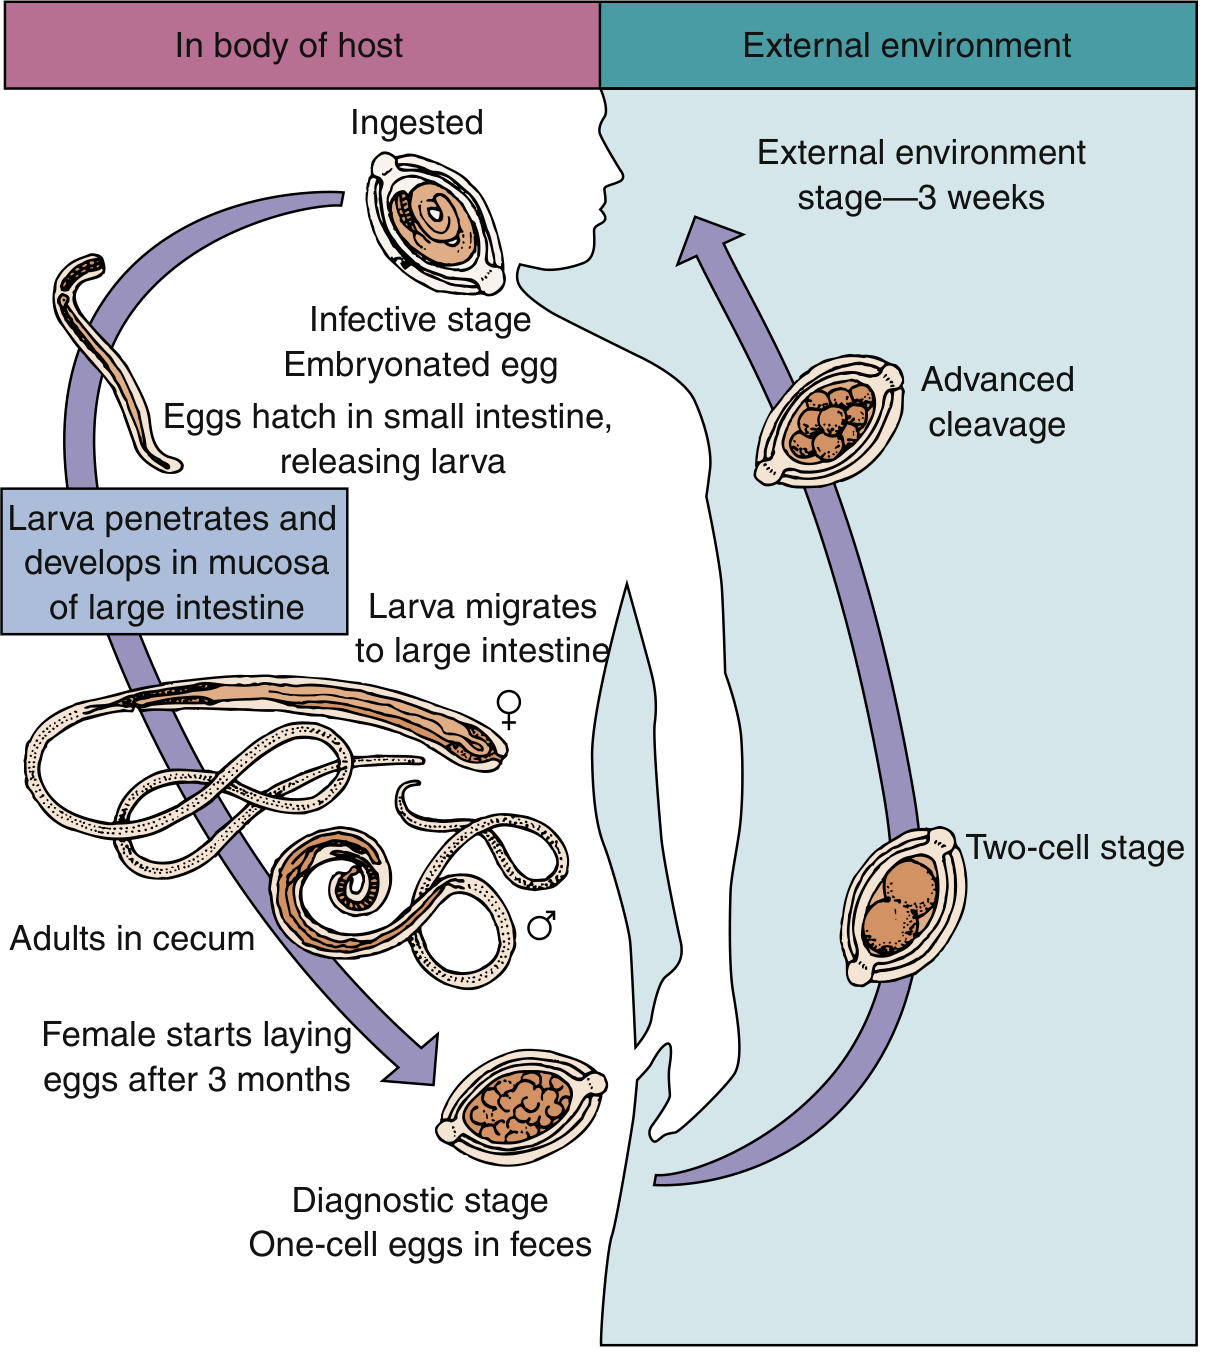
Life Cycle of Trichuris trichiura
Fig. 74.6 — Life cycle of Trichuris trichiura. (Medical Microbiology 9e)
Step-by-step:
- Ingestion — Embryonated eggs are swallowed (via contaminated soil on hands/food/water)
- Hatching — Eggs hatch in the small intestine, releasing larvae
- Migration — Larvae migrate to the cecum and ascending colon, penetrating the mucosa
- Maturation — Adults mature in ~8–12 weeks after infection
- Egg laying — Fertilized females lay 3,000–20,000 eggs/day; worms live 1–8 years
- Soil development — Eggs passed in feces reach the soil, embryonate in 2–6 weeks, and become infective
- No direct person-to-person transmission — Requires environmental maturation
"Ingested eggs hatch into a larval worm in the small intestine and then migrate to the cecum, in which they penetrate the mucosa and mature to adults." — Medical Microbiology 9e
Pathogenesis of Clinical Manifestations
The anterior (thin) end of the adult worm physically embeds into the colonic mucosa, causing:
- Mucosal disruption → chronic inflammation → diarrhea (watery and mucoid)
- Mechanical irritation → abdominal pain, RLQ tenderness (cecal location)
- Mucosal penetration → chronic microhemorrhage → iron deficiency anemia → pallor, fatigue, conjunctival pallor
- Protein-losing enteropathy + anorexia → weight loss, failure to thrive
- Th2 immune response (IL-4, IL-5, IL-13) attempts worm expulsion, driving eosinophilia
Severity is directly proportional to worm burden. In heavy infection, the syndrome is called Trichuris Dysentery Syndrome (TDS): severe bloody/mucoid diarrhea, tenesmus, abdominal pain, and in children — rectal prolapse.
Learning Objective 3: Diagnostic Methods & Expected Findings
CBC — Expected Findings
| Finding | Expected in Roxanne |
|---|
| Hemoglobin | ↓ (iron deficiency anemia) |
| MCV | ↓ (microcytic) |
| Eosinophils | ↑ (helminthic infection) |
| WBC | May be normal |
Stool Examination for Ova & Parasites — Key Finding
The pathognomonic finding is the Trichuris egg:
- Barrel-shaped (lemon-shaped)
- Dark bile staining
- Polar plugs at both ends of the egg shell
- Size: ~50 × 22 µm
"Stool examination reveals the characteristic bile-stained eggs with polar plugs. Light infestations may be difficult to detect because of the paucity of eggs in the stool specimens." — Medical Microbiology 9e
Diagnostic Methods
| Method | Details |
|---|
| Direct microscopy with stool concentration | First-line in clinical settings; detects characteristic eggs |
| Kato-Katz / McMaster / FLOTAC | Quantitative; used in research to determine worm burden |
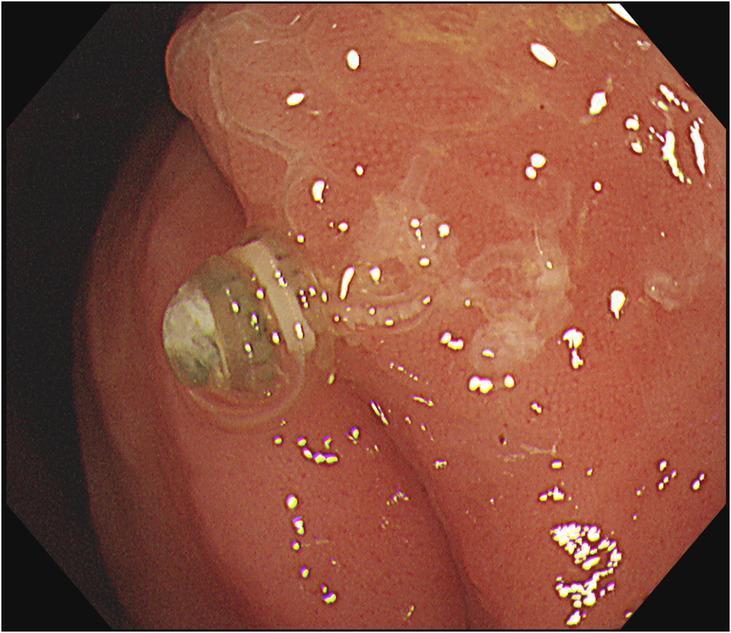
| Proctoscopy / Colonoscopy | Can directly visualize adult worms embedded in cecal/colonic mucosa |
Colonoscopic appearance of whipworms:
Colonoscopy showing T. trichiura with thin anterior end embedded in colonic mucosa
Learning Objective 4: Comprehensive Management Plan
Pharmacological Treatment
First-line drugs:
| Drug | Dose (Pediatric) | Regimen | Notes |
|---|
| Mebendazole | 100 mg | Twice daily × 3 days OR 500 mg single dose | Preferred — higher early cure rate (~11%) vs albendazole |
| Albendazole | 400 mg | Once daily × 3 days | Alternative; cure rate ~2% for single dose |
| Ivermectin | 200 µg/kg | Single dose | Alternative; avoid in children <15 kg |
"Mebendazole and albendazole are first-line therapies in the treatment of trichuriasis; some recommend mebendazole over albendazole given its higher early cure rate (11% vs 2%)." — Red Book 2021
For heavy infections (as suspected in Roxanne given 3 months of symptoms):
- Use 3–5 day course of mebendazole
- Consider combination therapy: albendazole + ivermectin OR albendazole + oxantel pamoate (markedly higher cure rates)
Follow-up: Recheck stool in ~2 weeks post-treatment. If positive, retreat.
Addressing Complications
| Complication | Management |
|---|
| Iron deficiency anemia | Oral iron supplementation (ferrous sulfate) |
| Malnutrition/weight loss | Nutritional counseling; ensure adequate caloric and protein intake |
| Dehydration (if significant diarrhea) | Oral rehydration therapy |
| Co-infections | Screen for Ascaris, hookworm (co-endemic); treat accordingly |
Learning Objective 5: Preventive Measures
Individual Level
- Hand hygiene: Wash hands with soap and water before eating and after using the toilet
- Footwear: Wear shoes/sandals at all times — Roxanne plays barefoot in soil
- Food safety: Wash fruits and vegetables thoroughly; avoid consuming raw produce from contaminated soil
- Water safety: Continue boiling water before drinking; ideally, switch to treated/piped water
- Nail hygiene: Keep fingernails short and clean to reduce egg accumulation
Community/Public Health Level
- Improved sanitation: Upgrade to hygienic latrines with proper fecal disposal to prevent soil contamination
- WHO Mass Drug Administration (MDA): Annual or biannual single-dose benzimidazoles (albendazole or mebendazole) for school-age children in endemic areas (WHO-recommended for communities with ≥20% prevalence)
- Health education: Community education on fecal-oral transmission and hygiene
- Safe water supply: Establishment of clean water infrastructure
- School-based deworming programs: Targeting children aged 1–14 years in endemic communities
"Annual (≥20% baseline prevalence) or biannual (≥50% baseline prevalence) administration of single doses of benzimidazoles in communities with endemic infection is recommended by the WHO." — Red Book 2021
Learning Objective 6: Long-Term Consequences in Children
Chronic T. trichiura infection in children, if untreated, can cause:
| Consequence | Mechanism |
|---|
| Iron deficiency anemia | Chronic mucosal microhemorrhage |
| Growth retardation / stunting | Malnutrition, anorexia, protein-energy deficiency |
| Cognitive impairment | Anemia + malnutrition affecting brain development |
| Rectal prolapse | In severe infection — straining from tenesmus and heavy worm burden |
| Trichuris Dysentery Syndrome (TDS) | Severe colitis with bloody diarrhea, mimicking IBD |
| Repeated infections | Without improved sanitation, reinfection is highly likely |
| Impaired school performance | Due to fatigue, anemia, and cognitive effects |
"Children with TDS have growth retardation... colonic biopsy specimens show an increase in mast cells and cells expressing TNF-α and calprotectin." — Sleisenger and Fordtran's Gastrointestinal and Liver Disease
Learning Objective 7: Communicating with the Grandmother
Here is a suggested communication framework for the healthcare provider:
Explain the diagnosis simply:
"Roxanne has an infection from tiny worms called whipworms, which live in the intestines. She likely got it by accidentally swallowing tiny worm eggs that were in the soil she plays in or in food or water. This is a common infection in this area."
Explain treatment:
"We will give her medicine — a tablet called mebendazole — for 3 days. It is safe for children. We need to check her stool again after 2 weeks to make sure the infection is cleared. We will also give her iron tablets because the worms have caused a mild anemia."
Explain prevention clearly:
"To prevent this from happening again: Roxanne must always wash her hands with soap before eating and after the toilet. She should wear shoes when playing outside. You should make sure she eats washed vegetables and drinks only boiled water. Fixing the latrine and disposing of toilet waste safely is very important for the whole family."
Address community risk:
"Other children in the home and community should also be checked and treated. This infection spreads through contaminated soil, not from person to person directly, but the whole family shares the same environment."
Summary Table
| Feature | Roxanne's Case |
|---|
| Diagnosis | Trichuriasis (T. trichiura) |
| Route of infection | Fecal-oral via soil-contaminated hands/food |
| Key symptoms | Chronic mucoid diarrhea, RLQ pain, weight loss, pallor, fatigue |
| Physical exam | RLQ tenderness, hyperactive bowel sounds, conjunctival pallor |
| Diagnostic finding | Barrel-shaped eggs with polar plugs on stool O&P exam |
| CBC finding | Microcytic anemia, eosinophilia |
| Treatment | Mebendazole 100 mg BID × 3 days + iron supplementation |
| Prevention | Hygiene, footwear, sanitation, MDA program |
Sources: Medical Microbiology 9e; Sleisenger and Fordtran's Gastrointestinal and Liver Disease; Red Book 2021 (Committee on Infectious Diseases); Katzung's Basic and Clinical Pharmacology 16e; Goodman & Gilman's Pharmacological Basis of TherapeuticsYour credits are exhausted. Your daily credits reset tomorrow, or you can purchase a top-up for more.