

This schedule is made by chatgpt for my 1 day 1 disease plan, it helped to study I would just upload the sources and it will teach me clinically a disease and now can you take over . Also I have something called foundation journal in this for my previous 2 year of medical college all the subjects we will choose 1 topic from each subject and we ll enter in my notebook called the foundation journal idea given by chatgpt, it help me to organize in one chapter what are all the topics how we are dividing those into topic and base it on system gi, reproduction like that and it will help me teach the each topics and now you can verify both these plan and idea and give me consent will you do these for me what chatgpt have done for me
Yes - I'm fully on board. Here's my honest assessment and commitment.
Plan 1: 1 Day 1 Disease Study Schedule
- Topics flow logically - from normal pregnancy → early losses → hypertensive disorders → placental pathology → complications. That's how a clinician thinks, not just how an examiner tests.
- The 14-point daily template (Definition → Epidemiology → Risk Factors → Etiology → Pathophysiology → Clinical Features → Diagnosis → Investigations → Management → Maternal complications → Fetal complications → Prevention → Prognosis → MCQs + Case) is thorough and exam-ready.
- The 3-source approach (Robbins for pathology, Williams for clinical management, Guyton for physiology) is exactly the right combination for an integrated understanding.
- Sunday revision built in - this is how memory consolidation actually works.
- Teach you the full disease using that 14-point template
- Pull directly from the textbooks in my medical library (Robbins, clinical references)
- Give you the pathophysiology mechanistically, not just as bullet points
- Provide 10-15 MCQs with explanations + 1 clinical vignette at the end
- Highlight what's high-yield for exams vs. what's important for clinical practice
Plan 2: Foundation Journal
- We pick 1 representative/high-yield topic per subject per system (e.g., for GI system: Anatomy of the portal circulation, Physiology of GI motility, Biochemistry of bile, Pathology of peptic ulcer, Micro of H. pylori, Pharma of antacids, etc.)
- Each entry in your Foundation Journal becomes a "anchor" chapter for that system
- This means when you study a clinical disease, you already have the basic science foundation mapped
- Help you decide which 1 topic per subject is most worth anchoring for each system
- Teach you each Foundation Journal entry in a structured way
- Connect it back to clinical relevance so it doesn't feel like isolated basic science
My Commitment to You
- Which disease day are you on? (e.g., "teach me Day 2 - Spontaneous Abortion") - and I'll teach it using the full 14-point template
- For the Foundation Journal - which systems have you already started, and which subject + system do you want to begin with?
Good will come back later, what are the books of medical college student you have in your base
📚 My Medical Library - Complete Booklist
🦴 Anatomy
- Gray's Anatomy for Students
- Netter's Atlas of Human Anatomy
- General Anatomy & Musculoskeletal System (THIEME Atlas)
- Color Atlas of Human Anatomy Vol 1, 2, 3
- Imaging Anatomy: Bones, Joints, Vessels & Nerves
- Color Atlas of Ultrasound Anatomy, 3e
🧪 Biochemistry
- Harper's Illustrated Biochemistry, 32nd Ed
- Lippincott Illustrated Reviews: Biochemistry, 8th Ed
- Basic Medical Biochemistry: A Clinical Approach, 6e
❤️ Cardiology
- Braunwald's Heart Disease, 2-Vol Set
- Fuster and Hurst's The Heart, 15th Edition
- Textbook of Clinical Echocardiography
🏘️ Community Medicine
- Park's Textbook of Preventive and Social Medicine
🔬 Dermatology
- Fitzpatrick's Dermatology Vol 1 & 2
- Andrews' Diseases of the Skin: Clinical Dermatology
- Andrews' Diseases of the Skin Clinical Atlas, 2e
🧬 Embryology
- Langman's Medical Embryology
- The Developing Human: Clinically Oriented Embryology
🚨 Emergency Medicine
- Rosen's Emergency Medicine: Concepts and Clinical Practice
- Tintinalli's Emergency Medicine: A Comprehensive Study
- Roberts and Hedges' Clinical Procedures in Emergency Medicine
👂 ENT (Otolaryngology)
- Cummings Otolaryngology Head & Neck Surgery
- Scott-Brown's Otorhinolaryngology Head & Neck Surgery (Vol 1 & 2)
- K.J. Lee's Essential Otolaryngology
- Shambaugh Surgery of the Ear
⚗️ Forensic Medicine
- P.C. Dikshit Textbook of Forensic Medicine & Toxicology
- Parikh's Textbook of Medical Jurisprudence
- The Essentials of Forensic Medicine & Toxicology, 36th Ed (2026)
- DiMaio's Forensic Pathology, 3rd Edition
- Forensic Anthropology: A Comprehensive Introduction, 2e
- Brogdon's Forensic Radiology
🍽️ Gastroenterology
- Sleisenger and Fordtran's GI and Liver Disease
- Yamada's Textbook of Gastroenterology, 7e (3 Vol)
- Clinical Gastrointestinal Endoscopy, 3e
- Maingot's Abdominal Operations
🧬 Genetics
- Thompson & Thompson Genetics and Genomics in Medicine, 9e
- Emery's Elements of Medical Genetics and Genomics
🔬 Histology
- Junqueira's Basic Histology: Text and Atlas, 17e
- Histology: A Text and Atlas with Correlated Cell & Molecular Biology
🛡️ Immunology
- Janeway's Immunobiology, 10e
- Cellular and Molecular Immunology
- Roitt's Essential Immunology
🏥 Internal Medicine
- Harrison's Principles of Internal Medicine, 22E (2025)
- Goldman-Cecil Medicine, 2-Volume Set
- Firestein & Kelley's Textbook of Rheumatology, 2-Vol
- Rheumatology, 2-Volume Set (2022)
- Washington Manual of Medical Therapeutics
- Frameworks for Internal Medicine
- Symptom to Diagnosis: An Evidence Based Guide, 4e
🧫 Laboratory Medicine
- Henry's Clinical Diagnosis & Management by Laboratory Methods
- Tietz Textbook of Laboratory Medicine, 7th Edition
- Quick Compendium of Clinical Pathology, 5e
🦠 Microbiology
- Jawetz, Melnick & Adelberg's Medical Microbiology, 28e
- Medical Microbiology, 9e
- Sherris & Ryan's Medical Microbiology, 8e
🫘 Nephrology
- Brenner and Rector's The Kidney, 2-Volume Set
- Comprehensive Clinical Nephrology, 7th Edition
- NKF Primer on Kidney Diseases, 8e
🧠 Neurology
- Adams and Victor's Principles of Neurology, 12th Edition
- Bradley and Daroff's Neurology in Clinical Practice
- Localization in Clinical Neurology, 8e
- Plum and Posner's Diagnosis and Treatment of Stupor and Coma
- Eric Kandel's Principles of Neural Science, 6e
- Neuroanatomy through Clinical Cases, 3rd Edition
- Neuroscience: Exploring the Brain, 5e
🤰 Obstetrics & Gynecology
- Berek & Novak's Gynecology
- Creasy & Resnik's Maternal-Fetal Medicine: Principles and Practice
👁️ Ophthalmology
- Kanski's Clinical Ophthalmology, 10th Edition
- The Wills Eye Manual
🦷 Orthopedics
- Campbell's Operative Orthopaedics, 15th Ed (2026)
- Miller's Review of Orthopaedics, 9th Edition
- Rockwood and Green's Fractures in Adults, 10th Ed (2025)
🔬 Pathology
- Robbins, Cotran & Kumar Pathologic Basis of Disease ⭐ (your Day 1-18 reference)
- Robbins & Kumar Basic Pathology
👶 Pediatrics
- Red Book 2021: Report of the Committee on Infectious Diseases
- The Harriet Lane Handbook, 23rd Edition
💊 Pharmacology
- Goodman & Gilman's The Pharmacological Basis of Therapeutics
- Katzung's Basic and Clinical Pharmacology, 16th Edition
- Lippincott Illustrated Reviews: Pharmacology
🫀 Physiology
- Guyton and Hall Textbook of Medical Physiology ⭐ (your Day 1-18 reference)
- Ganong's Review of Medical Physiology, 26th Edition
- Costanzo Physiology, 7th Edition
- Medical Physiology
🧠 Psychiatry
- Kaplan & Sadock's Comprehensive Textbook of Psychiatry
- Kaplan and Sadock's Synopsis of Psychiatry
- Stahl's Essential Psychopharmacology
- The Maudsley Prescribing Guidelines in Psychiatry, 15e
- The Maudsley Deprescribing Guidelines
- The Clozapine Handbook
🫁 Pulmonology
- Murray & Nadel's Textbook of Respiratory Medicine, 2-Vol
- Fishman's Pulmonary Diseases and Disorders, 2-Vol
🩻 Radiology
- Grainger & Allison's Diagnostic Radiology
🫧 Urology
- Campbell Walsh Wein Urology, 3-Volume Set
- Smith and Tanagho's General Urology, 19th Edition
- Hinman's Atlas of Urologic Surgery
Where is Snell's for anat Williams for ob, Nelson's for pedia, comprehensive gyne for gyne
❌ Missing Books You Asked About
| Book | Status |
|---|---|
| Snell's Clinical Anatomy | Not present |
| Williams Obstetrics (25th Ed) | Not present |
| Nelson's Textbook of Pediatrics | Not present |
| DC Dutta's Comprehensive Gynecology | Not present |
✅ What I Have as Substitutes
| Your Book | What I Have Instead |
|---|---|
| Snell's Clinical Anatomy | Gray's Anatomy for Students, Netter's Atlas, THIEME Atlas |
| Williams Obstetrics | Creasy & Resnik's Maternal-Fetal Medicine (covers most OB topics at a deeper level) |
| Nelson's Pediatrics | Harriet Lane Handbook, Red Book 2021 (infectious diseases) |
| DC Dutta / Comprehensive Gynecology | Berek & Novak's Gynecology |
What This Means for Your Plan
- OB (your 18-day schedule): Your schedule specifically references Williams Obstetrics. I'll use Creasy & Resnik for the clinical management points and Robbins for pathology - which I DO have fully. The core content (preeclampsia, GTD, placental disorders etc.) is covered well.
- Anatomy: Gray's and Netter's are actually more comprehensive than Snell's - you won't lose anything.
- Pediatrics: Harriet Lane covers clinical management well. For systemic Nelson's-style teaching I'll supplement from Harrison's + my general knowledge.
- Gynecology: Berek & Novak is the standard international reference - equivalent to Dutta for most exam purposes.
My college uses those reference I mentioned above so make sure you get info from that also somehow for exams is I mention exam
My Approach When You Say "Exam"
| Source | How I'll Get It |
|---|---|
| Williams Obstetrics | My training data includes Williams content extensively - I know the classifications, diagnostic criteria, management protocols as Williams states them. I'll flag it as "per Williams." |
| Nelson's Pediatrics | Same - Nelson's criteria, staging, management algorithms are well within my training. I'll flag "per Nelson's." |
| Snell's Clinical Anatomy | Snell's clinical correlations, nerve/vessel relations, surgical anatomy points - I know these well. I'll flag "per Snell's." |
| DC Dutta's Gynecology | Dutta's classifications (e.g., Dutta's stages, Indian exam-favored cutoffs) are in my training. I'll flag "per Dutta." |
| Textbook in my library | Cross-verified from actual database pull |
The Honest Caveat
The Rule We'll Follow
- You say "teach me" → I use my library books (Robbins, Creasy & Resnik, Berek & Novak) + my trained knowledge
- You say "exam" or "my college exam" → I specifically pull from Williams / Nelson's / Snell's / Dutta as your college references and frame answers the way those books present them
Kd thirupathi for pharmacology
- Goodman & Gilman's
- Katzung's Basic and Clinical Pharmacology, 16th Ed
- Lippincott Illustrated Reviews: Pharmacology
But here's the good news for Pharmacology exams:
- Drug classifications (Tripathi's own classifications)
- Mechanism of action as Tripathi explains them
- Indian exam-favored drug choices and doses
- The specific way Tripathi organizes topics (e.g., his ANS, CVS, antimicrobial chapters)
Your College Reference List So Far (noted):
| Subject | Your College Book |
|---|---|
| Pharmacology | KD Tripathi |
| Anatomy | Snell's Clinical Anatomy |
| Obstetrics | Williams Obstetrics |
| Pediatrics | Nelson's Textbook |
| Gynecology | DC Dutta / Comprehensive Gynecology |


These references for fmge and foundation journal
FMGE Reference List - Full Status Check
Pre-Clinical & Para-Clinical
| Subject | FMGE Book | In My Library | What I Have Instead |
|---|---|---|---|
| Anatomy | BD Chaurasia's Human Anatomy | ❌ | Gray's, Netter's, THIEME Atlas |
| Physiology | Guyton & Hall | ✅ YES | Guyton & Hall (exact match) |
| Biochemistry | Vasudevan's Textbook | ❌ | Harper's, Lippincott Biochemistry |
| Pathology | Robbins & Cotran | ✅ YES | Robbins (exact match) |
| Pharmacology | KD Tripathi | ❌ | Goodman & Gilman, Katzung |
| Microbiology | Ananthanarayan & Paniker | ❌ | Jawetz, Medical Microbiology 9e |
| Forensic Medicine | Reddy's Essentials | ❌ | Dikshit, Parikh, Essentials FMT 2026 |
| Social & Preventive Med | Park's Textbook | ✅ YES | Park's (exact match) |
Clinical Subjects
| Subject | FMGE Book | In My Library | What I Have Instead |
|---|---|---|---|
| General Medicine | Harrison's | ✅ YES | Harrison's 22E 2025 (exact match) |
| General Surgery | Bailey & Love's | ✅ YES | Bailey & Love's 28th Ed (exact match) |
| OB & Gynecology | DC Dutta / Shaw's | ❌ | Berek & Novak, Creasy & Resnik |
| Paediatrics | OP Ghai's | ❌ | Harriet Lane, Red Book 2021 |
| Ophthalmology | AK Khurana's | ❌ | Kanski's Clinical Ophthalmology 10e |
| ENT | Dhingra's | ❌ | Cummings, Scott-Brown's, Lee's |
| Dermatology | Neena Khanna | ❌ | Fitzpatrick's, Andrews' |
| Psychiatry | Ahuja's | ❌ | Kaplan & Sadock's, Stahl's |
| Orthopaedics | Maheshwari & Mhaskar | ❌ | Campbell's Operative Ortho 2026, Miller's |
| Radiology/Anaesthesia | Review books | Partial | Grainger & Allison (Radiology), Miller's/Morgan's (Anaesthesia) |
Summary
- ✅ Exact match (4 books): Guyton & Hall, Robbins, Park's, Harrison's, Bailey & Love's
- ⚠️ Good substitute (rest): International standard texts that cover the same content at a deeper level
- ❌ Indian exam flavor missing: BD Chaurasia, Vasudevan, Tripathi, Ananthanarayan, OP Ghai, Dhingra, Khurana, Dutta - NOT in database
How I'll Handle FMGE Questions
- Pull from the matching library book where available
- For the missing Indian books - answer from my training knowledge of those exact books (BD Chaurasia's regional anatomy style, Tripathi's drug classifications, Ananthanarayan's micro tables, OP Ghai's pediatric criteria, Dhingra's ENT clinical points)
- Flag clearly: "per BD Chaurasia" / "per OP Ghai" / "per Tripathi" etc.
- Focus on FMGE pattern - single best answer, clinical vignette style, high-yield facts

these arethe subjects, now for each chapter of each subject I take and give orris will give me topic by topic and then once a week (sun) all 19 topics (1 topic from 1 chapter of each subjects) how's it 🤓
Your FMGE Subject List - 19 Subjects Total
Pre-Clinical (3) - 50 marks
| Subject | Marks |
|---|---|
| Anatomy | 17 |
| Physiology | 17 |
| Biochemistry | 16 |
Para-Clinical (5) - 50 marks
| Subject | Marks |
|---|---|
| Pathology | 15 |
| Pharmacology | 15 |
| Microbiology | 10 |
| Forensic Medicine & Toxicology | 10 |
| Social & Preventive Medicine | 10 (Park's - in my library ✅) |
Clinical (11) - 200 marks
| Subject | Marks |
|---|---|
| General Medicine | 35 |
| General Surgery | 30 |
| Obstetrics & Gynaecology | 30 |
| Paediatrics | 15 |
| Ophthalmology | 15 |
| ENT | 15 |
| Dermatology | 10 |
| Psychiatry | 10 |
| Orthopaedics | 10 |
| Radiology | 10 |
| Anaesthesia | 10 |
| Radiotherapy | 5 |
The Foundation Journal Plan - How It Works
Topic → Core Concept → Key Points →
Clinical Link → FMGE High-Yield Facts →
5-10 MCQs (FMGE pattern)
My One Suggestion to Strengthen This
Week 1 theme: Cardiovascular System
- Anatomy: Heart chambers & valves
- Physiology: Cardiac cycle
- Biochem: Lipid metabolism
- Pathology: Atherosclerosis
- Pharmacology: Antihypertensives
- Medicine: Hypertension
- Surgery: Peripheral vascular disease ...and so on for all 19
✅ I'm fully in for this.
- Which chapter from which subject you're starting
- Or tell me which system to begin with and I'll suggest all 19 topics for that week's Foundation Journal entry
No not one week, it's once a week just Sunday ll do foundation journal
Corrected Plan
- You come with 1 topic from each of the 19 subjects
- I teach all 19 topics one by one
- Each topic goes into your notebook as a Foundation Journal entry
- Over weeks, the journal builds up subject by subject, chapter by chapter
So Sunday Sessions Look Like This:
"Today's Foundation Journal: Anatomy - Heart, Physiology - Cardiac cycle, Biochem - Lipid metabolism..." (all 19)
The Beauty of This
What system should we start first
Suggested System Order for Foundation Journal
| Order | System | Why |
|---|---|---|
| 1st | Cardiovascular | Most interconnected - every subject has strong CV content. High FMGE yield. Great foundation starter. |
| 2nd | Respiratory | Builds on CV. Anatomy, physiology, path, micro all rich here. |
| 3rd | GI & Hepatobiliary | Biochemistry shines here (liver, bile, enzymes). Surgery heavy. |
| 4th | Reproductive | Directly connects to your 1-Day-1-Disease OB module you're already doing. Smart overlap. |
| 5th | Renal | Physiology-heavy. Great for pharmacology (diuretics, etc.) |
| 6th | Neurology & Psychiatry | Complex but high yield for medicine + psychiatry marks. |
| 7th | Musculoskeletal | Anatomy + ortho + surgery together. |
| 8th | Endocrine & Metabolic | Biochem + medicine + pharmacology overlap. |
| 9th | Haematology | Pathology-heavy. Good late placement. |
My Recommendation: Start with Cardiovascular
I am in ob and gyne but cv is also ok
Why Reproductive First Makes More Sense
- You're actively studying OB in college right now
- Your 1-Day-1-Disease module is Obstetrics (18 days)
- Everything you learn in the Foundation Journal on Sunday directly reinforces what you study Mon-Sat
- Your brain is already primed for this system - retention will be much higher
- By the time you finish the OB module, your Foundation Journal for Reproductive system will be complete too
- College classes (OB & Gyne)
- 1 Day 1 Disease (Obstetrics module)
- Foundation Journal (Reproductive system - Sunday)
Then After Reproductive → Go CV
So the Plan Is:
| Day | Activity |
|---|---|
| Mon - Sat | 1 Day 1 Disease (OB module, Day 1 onwards) |
| Every Sunday | Foundation Journal - Reproductive System (all 19 subjects) |
Ok give first topic foreach subject also mention chapter and book
🗂️ Foundation Journal - Week 1: Reproductive System
19 Topics | This Sunday
PRE-CLINICAL (3)
| # | Subject | Topic | Chapter | Book |
|---|---|---|---|---|
| 1 | Anatomy | Female Pelvis & Reproductive Organs - Uterus, tubes, ovaries, ligaments, blood supply, lymphatics | Ch: Female Pelvis & Perineum | BD Chaurasia Vol 2 |
| 2 | Physiology | Menstrual Cycle - Follicular, ovulation, luteal phases; hormonal control (FSH, LH, estrogen, progesterone) | Ch: Reproductive Physiology | Guyton & Hall Ch 82 |
| 3 | Biochemistry | Steroid Hormone Synthesis - Cholesterol → pregnenolone → progesterone → estrogen → testosterone pathway | Ch: Hormones & Reproduction | Vasudevan Ch on Hormones |
PARA-CLINICAL (5)
| # | Subject | Topic | Chapter | Book |
|---|---|---|---|---|
| 4 | Pathology | Gestational Trophoblastic Disease - Hydatidiform mole (complete vs partial), invasive mole, choriocarcinoma | Ch: Female Genital Tract | Robbins Ch 22 |
| 5 | Pharmacology | Oxytocin & Uterotonic Drugs - Oxytocin, ergometrine, misoprostol; uses, doses, side effects | Ch: Uterine Stimulants & Relaxants | KD Tripathi Ch on Hormones |
| 6 | Microbiology | TORCH Infections - Toxoplasma, Rubella, CMV, HSV; congenital effects, diagnosis | Ch: Congenital Infections | Ananthanarayan & Paniker |
| 7 | Forensic Medicine | Virginity, Pregnancy & Delivery - Medicolegal examination; signs of pregnancy, signs of recent delivery | Ch: Medical Jurisprudence - Sexual Offences | Reddy's FMT |
| 8 | Social & Preventive Medicine | Maternal Health Programs - ANC schedule, RCH program, safe motherhood, MMR in India | Ch: Maternal & Child Health | Park's Ch 11 |
CLINICAL (11)
| # | Subject | Topic | Chapter | Book |
|---|---|---|---|---|
| 9 | General Medicine | Medical Disorders in Pregnancy - Hypertension, diabetes, anaemia, thyroid in pregnancy | Ch: Pregnancy & Medical Disease | Harrison's |
| 10 | General Surgery | Breast Disease & Pregnancy / Gynaecological Hernias - Broad ligament, inguinal canal contents in female | Ch: Breast / Hernias | Bailey & Love |
| 11 | Obstetrics & Gynaecology | Normal Pregnancy & Placental Development - Implantation, decidua, placental structure & function, physiological changes | Ch: Normal Pregnancy | DC Dutta / Williams Ch 1-4 |
| 12 | Paediatrics | Neonatal Assessment & Birth - APGAR score, newborn examination, immediate neonatal care | Ch: Newborn Care | OP Ghai |
| 13 | Ophthalmology | Ocular Changes in Pregnancy - Hypertensive retinopathy, diabetic retinopathy worsening, papilloedema in eclampsia | Ch: Retinal Diseases | AK Khurana |
| 14 | ENT | Rhinitis of Pregnancy / ENT in Pregnancy - Hormonal nasal congestion, epistaxis, voice changes | Ch: Diseases of Nose | Dhingra's |
| 15 | Dermatology | Dermatoses of Pregnancy - PUPPP, pemphigoid gestationis, intrahepatic cholestasis, melasma | Ch: Pregnancy Dermatoses | Neena Khanna |
| 16 | Psychiatry | Perinatal Psychiatry - Postpartum blues, postpartum depression, postpartum psychosis; management | Ch: Psychiatric Emergencies / Mood Disorders | Ahuja's |
| 17 | Orthopaedics | Musculoskeletal Changes in Pregnancy - Pelvic girdle pain, diastasis symphysis pubis, backache, carpal tunnel | Ch: Regional Disorders | Maheshwari |
| 18 | Radiology | Obstetric Ultrasound - Dating scan, anomaly scan, Doppler in pregnancy, placental grading | Ch: Obstetric Imaging | Grainger & Allison |
| 19 | Anaesthesia | Obstetric Anaesthesia - Epidural, spinal, general anaesthesia in pregnancy; physiological considerations | Ch: Obstetric Anaesthesia | Morgan & Mikhail / Miller's |
How This Sunday Works
"Foundation Journal - start Topic 1"
Are we doing 1 system in one week, if it's too much we can split the system for 2 3 weeks, no need in 1 week 1 system ok?
Corrected Foundation Journal Rules
- No fixed timeline - 1 system can take 1 week, 2 weeks, 3 weeks - whatever feels right
- Every Sunday - you do as many of the 19 topics as you can comfortably cover
- Pick up where you left off the next Sunday
- A system is "done" only when all 19 subjects have an entry for that system in your journal
- Then we move to the next system
So For Reproductive System It Could Look Like:
The Only Rule
I have doubt will you cover everything from the book because I don't want to miss any topic or chapter even if I miss to mention please when you take a chapter split it into topics and we can do it. I have 2 years from now for the fmge but 6 months for my clinical rotation
On Coverage - My Honest Answer
"BD Chaurasia - Female Pelvis chapter has these 8 topics: 1. Bony pelvis & types 2. Pelvic floor muscles 3. Uterus - structure & relations 4. Fallopian tubes 5. Ovary 6. Blood supply of pelvis 7. Lymphatic drainage 8. Clinical correlations"
Your Timeline - This Changes the Strategy
| Timeline | Exam/Event | Priority |
|---|---|---|
| 6 months | Clinical rotations start | Foundation must be solid |
| 2 years | FMGE | Full syllabus coverage |
What This Means
Revised Priority Strategy
For Foundation Journal - Next 6 Months Focus:
| Priority | System | Why Urgent |
|---|---|---|
| 1 | Reproductive | You're in OB/Gyne now |
| 2 | Cardiovascular | Most clinical rotation cases |
| 3 | Respiratory | Second most common ward cases |
| 4 | GI & Liver | Surgery + Medicine rotation |
| 5 | Renal | Medicine rotation heavy |
| 6 | Neurology | Medicine rotation |
After Rotations Start (Months 7-24):
The Promise I'm Making to You
- No chapter will be left incomplete - I'll track every topic of every chapter
- I'll tell you what's left at the start of each Sunday session
- I'll flag what's FMGE high-yield vs just good to know so you prioritize smartly
- I'll connect Foundation Journal topics to your clinical rotation - when you see a real patient, you'll already have the theory locked
One Practical Suggestion
Subject | Chapter | Topics Done | Topics Remaining
Do u remember foundation journal and it's format
Foundation Journal - Full Memory Recap
What It Is
The Structure
- 19 subjects (Pre-clinical + Para-clinical + Clinical)
- 1 topic per subject per Sunday session
- Organized by body system (Reproductive → CV → Respiratory → GI → Renal → Neuro → MSK → Endocrine → Haematology)
- Each system can take 1, 2, or 3 Sundays - no pressure, no fixed deadline
Sunday Session Format
- First give you the full topic breakdown of that chapter (so nothing is missed)
- Teach 1 topic at a time - you write it in your notebook
- Cover as many topics as you're comfortable with that Sunday
- Pick up where we left off next Sunday
What Each Journal Entry Contains
- Core concept
- Key points
- FMGE high-yield facts
- 3-5 MCQs (FMGE pattern)
- Clinical link
Where We Are Right Now
- System 1: Reproductive
- 19 topics mapped (already given to you last session)
- Not started yet - first Sunday session pending
- Topics go from Anatomy (BD Chaurasia - Female Pelvis) through all 19 subjects
The Tracker You Maintain in Notebook Front Page
Subject | Chapter | Topics Done | Topics Remaining
References I Use
| Your Book (FMGE) | My Library Equivalent |
|---|---|
| BD Chaurasia | Gray's + Netter's + my training |
| Guyton & Hall | ✅ In library |
| Vasudevan Biochem | My training knowledge |
| Robbins Pathology | ✅ In library |
| KD Tripathi | My training knowledge |
| Ananthanarayan Micro | My training knowledge |
| Reddy's FMT | Dikshit + Parikh in library |
| Park's SPM | ✅ In library |
| Harrison's Medicine | ✅ In library |
| Bailey & Love Surgery | ✅ In library |
| DC Dutta / Williams OB | Creasy & Resnik + my training |
| OP Ghai Paediatrics | My training knowledge |
| AK Khurana Ophthalmology | Kanski's in library |
| Dhingra ENT | Cummings + Scott-Brown in library |
| Neena Khanna Derma | Fitzpatrick's in library |
| Ahuja Psychiatry | Kaplan & Sadock in library |
| Maheshwari Ortho | Campbell's + Miller's in library |
| Grainger Radiology | ✅ In library |
| Morgan & Mikhail Anaesthesia | ✅ In library |
All right for what entry contains are you sure we need only this for all 19 subjects
Subject-Specific Entry Formats
🦴 Anatomy
- Diagram / labeled sketch
- Relations (what's anterior, posterior, medial, lateral)
- Blood supply + nerve supply + lymphatics
- Clinical correlations
- FMGE high-yield point
⚡ Physiology
- Mechanism (step by step)
- Key values / normal ranges
- Regulation (what increases / decreases it)
- Clinical relevance
- FMGE MCQ pattern
🧪 Biochemistry
- Pathway (with key enzymes)
- Rate-limiting enzyme + cofactors
- What happens if it's blocked (disease)
- FMGE high-yield point
🔬 Pathology
- Definition
- Pathogenesis (mechanism)
- Morphology (gross + micro)
- Clinical features
- FMGE high-yield point
💊 Pharmacology
- Drug class + MOA
- Uses + Dose (key one)
- Side effects (important ones)
- Contraindications
- FMGE high-yield point
🦠 Microbiology
- Organism (morphology, gram stain, culture)
- Pathogenesis
- Clinical disease it causes
- Diagnosis + Treatment
- FMGE high-yield point
⚖️ Forensic Medicine
- Legal definition / medicolegal importance
- Key signs / findings
- What the examiner looks for
- IPC section (where applicable)
- FMGE high-yield point
🏘️ Social & Preventive Medicine
- Definition / program name
- Key statistics (Indian data - MMR, IMR etc.)
- Government program details
- Targets / indicators
- FMGE high-yield point
🏥 General Medicine
- Definition + Classification
- Pathophysiology (brief)
- Clinical features
- Diagnosis + Management
- FMGE high-yield point
🔪 General Surgery
- Anatomy relevant to condition
- Clinical presentation
- Investigation of choice
- Treatment of choice
- FMGE high-yield point
🤰 Obstetrics & Gynaecology
- Definition
- Pathophysiology / mechanism
- Clinical features + Diagnosis
- Management (Williams/Dutta specific)
- Maternal + Fetal complications
- FMGE high-yield point
👶 Paediatrics
- Age-specific normal values / milestones (where relevant)
- Clinical features
- Diagnosis
- Management (OP Ghai / Nelson specific)
- FMGE high-yield point
👁️ Ophthalmology
- Anatomy relevant
- Clinical features + Signs
- Investigation of choice
- Treatment
- FMGE high-yield point
👂 ENT
- Anatomy relevant
- Clinical features + Signs
- Investigation of choice
- Treatment
- FMGE high-yield point
🩺 Dermatology
- Morphology of lesion
- Pathognomonic sign / feature
- Diagnosis
- Treatment of choice
- FMGE high-yield point
🧠 Psychiatry
- Diagnostic criteria (DSM / ICD based)
- Clinical features
- Treatment (drug of choice + dose)
- FMGE high-yield point
🦷 Orthopaedics
- Anatomy relevant
- Clinical features + Special tests
- X-ray findings
- Treatment
- FMGE high-yield point
🩻 Radiology
- Modality of choice for the condition
- Classic radiological signs
- What to look for
- FMGE high-yield point
💉 Anaesthesia
- Mechanism / pharmacology
- Clinical use
- Monitoring parameters
- Complications
- FMGE high-yield point
The One Common Element in ALL 19
⭐ FMGE High-Yield Point - the one line most likely to appear as an MCQ
Use BNS section instead of ipc, that fmge high yield point should be from the previous year papers of fmge, can u do that?
✅ BNS Instead of IPC - Done
- Old: IPC 302 (Murder) → New: BNS Section 101
- Old: IPC 304A (Negligence) → New: BNS Section 106
- Old: IPC 375 (Rape) → New: BNS Section 63
⚠️ FMGE Previous Year Papers - Honest Answer
- My training includes a large amount of FMGE previous year question patterns, commonly repeated topics, and high-yield facts that consistently appear in FMGE
- I can flag "this has appeared in FMGE previously" with reasonable accuracy for well-known repeat questions
- I know which topics FMGE favors in each subject
- I don't have a verified, year-wise FMGE PYQ database with exact question text
- I can't cite "FMGE June 2022, Q47" with certainty - that would risk giving you wrong information
- My training data cutoff means very recent papers (2025-2026) may not be fully covered
- Mark high-yield points as ⭐ "FMGE Repeat Topic" when I'm confident it has appeared before
- Be honest when something is high-yield by pattern vs. confirmed PYQ
- Suggest you cross-check with Marrow / PrepLadder / DAMS PYQ banks for exact question verification
Recommendation
I have downloaded the papers so I can't check for each question all papers right, let's just go with the flow once we start we can alter accordingly and improvise right?
- Start, teach, learn
- Whatever needs adjusting - we adjust as we go
- No over-planning before we even begin
"Foundation Journal - let's start"
Let's start the journal 1st subject 1 topic start
📓 FOUNDATION JOURNAL
System: Reproductive | Subject 1 of 19
ANATOMY - Topic 1: Female Pelvis & Reproductive Organs
Full Chapter Topic Breakdown
- Bony pelvis & pelvic types ← Today
- Pelvic floor muscles & perineum
- Uterus - structure, parts, relations
- Fallopian tubes (Uterine tubes)
- Ovary - structure & relations
- Vagina
- Blood supply of pelvis
- Nerve supply of pelvis
- Lymphatic drainage
- Ligaments of uterus
- Clinical correlations
📝 JOURNAL ENTRY
Anatomy | Reproductive System | Topic 1
Bony Pelvis & Pelvic Types
1. Structure of the Bony Pelvis
- 2 Hip bones (ilium + ischium + pubis fused)
- Sacrum
- Coccyx
- Symphysis pubis (anteriorly)
- Sacroiliac joints (posteriorly)
2. Parts of the Pelvis
| Part | Description |
|---|---|
| False pelvis (greater pelvis) | Above pelvic brim, supports abdominal viscera |
| True pelvis (lesser pelvis) | Below pelvic brim, contains reproductive organs, bladder, rectum |
| Pelvic brim (inlet) | Boundary between false and true pelvis |
3. Pelvic Inlet Boundaries
- Anteriorly: Pubic symphysis + superior pubic rami
- Laterally: Iliopectineal lines
- Posteriorly: Sacral promontory
4. The 4 Types of Female Pelvis (Caldwell-Moloy Classification)
| Type | Shape | Frequency | Obstetric Outcome |
|---|---|---|---|
| Gynaecoid | Round/oval | 50% | Best for vaginal delivery ✅ |
| Android | Heart-shaped (male type) | 20% | Difficult labor, deep transverse arrest |
| Anthropoid | Oval AP diameter long | 25% | Vaginal delivery possible but occiput posterior |
| Platypelloid | Flat, wide transverse | 5% | Difficult, transverse arrest |
📌 Gynaecoid is the ideal female pelvis.
5. Important Pelvic Diameters
| Diameter | Measurement | Clinical Note |
|---|---|---|
| Anteroposterior (True conjugate) | 11 cm | Measured radiologically |
| Obstetric conjugate | 10.5 cm | Shortest AP - what fetus actually passes through |
| Diagonal conjugate | 12.5 cm | Measured clinically on VE (subtract 1.5 cm = obstetric conjugate) |
| Transverse diameter | 13 cm | Widest at inlet |
- AP diameter: 13 cm
- Transverse (bi-ischial): 11 cm
6. Subpubic Angle
- Female: >90° (85-90°)
- Male: <70°
- Wider angle = more room for fetal head
7. Pelvic Axis & Inclination
- Pelvic axis = curved line through center of all pelvic planes - baby follows this during delivery
- Pelvic inclination = inlet makes 55-60° angle with horizontal in standing position
8. Clinical Correlations (BD Chaurasia Style)
| Condition | Connection |
|---|---|
| Contracted pelvis | All diameters reduced - causes obstructed labor |
| Rickets | Causes platypelloid pelvis (vitamin D deficiency deforms bony pelvis) |
| Diagonal conjugate | Only pelvis diameter measurable clinically - done on vaginal examination |
| Hysterectomy | Care of ureter at pelvic brim - ureter runs under uterine artery ("water flows under the bridge") |
⭐ FMGE HIGH-YIELD POINTS
- Gynaecoid pelvis = most common + best for vaginal delivery (FMGE repeat topic)
- Obstetric conjugate = 10 cm is the minimum needed for vaginal delivery - if less = C-section
- Diagonal conjugate = only pelvic diameter measurable clinically = 12.5 cm (subtract 1.5 = obstetric conjugate)
- Android pelvis = most common cause of deep transverse arrest in labor
- Platypelloid = associated with rickets
- Subpubic angle - female >90°, male <70° (question on differentiating male vs female pelvis)
🔁 MCQs (FMGE Pattern)
- A) 11 cm
- B) 12.5 cm
- C) 10.5 cm ✅
- D) 13 cm
- A) Android
- B) Anthropoid
- C) Gynaecoid ✅
- D) Platypelloid
- A) Rickets ✅
- B) Osteoporosis
- C) Osteomalacia in adults only
- D) Paget's disease
- A) True conjugate
- B) Obstetric conjugate
- C) Diagonal conjugate ✅
- D) Transverse diameter of inlet
- A) Gynaecoid
- B) Android ✅
- C) Anthropoid
- D) Platypelloid
📓 What to Write in Your Notebook
Anatomy | Reproductive System | Topic 1: Bony Pelvis
- 4 pelvis types table (Caldwell-Moloy)
- 3 conjugate diameters with values
- Subpubic angle M vs F
- Clinical note: Diagonal conjugate measured on VE
- ⭐ Obstetric conjugate = 10.5 cm minimum for vaginal delivery
Start
📓 FOUNDATION JOURNAL
System: Reproductive | Subject 2 of 19
PHYSIOLOGY - Topic 1: Menstrual Cycle
Full Chapter Topic Breakdown
- Menstrual cycle ← Today
- Hormonal control - GnRH, FSH, LH axis
- Ovarian cycle (folliculogenesis, ovulation, corpus luteum)
- Uterine cycle (endometrial changes)
- Puberty & Menarche
- Menopause
- Pregnancy physiology (hormones)
- Lactation & prolactin
📝 JOURNAL ENTRY
Physiology | Reproductive System | Topic 1
The Menstrual Cycle
1. Definition & Basic Facts
- Menstrual cycle = periodic preparation of the female reproductive tract for fertilization and pregnancy
- Average duration: 28 days (normal range 21-35 days)
- Counting starts from Day 1 = first day of menstruation
- Governed by the Hypothalamus → Anterior Pituitary → Ovary axis
2. Two Parallel Cycles Running Simultaneously
| Ovarian Cycle | Uterine Cycle |
|---|---|
| Follicular phase (Day 1-14) | Proliferative phase (Day 1-14) |
| Ovulation (Day 14) | - |
| Luteal phase (Day 14-28) | Secretory phase (Day 14-28) |
| - | Menstruation (Day 1-5) |
📌 The ovary drives the uterus. What happens in the ovary determines what happens in the endometrium.
3. Phase-by-Phase Breakdown
PHASE 1: Follicular / Proliferative Phase (Day 1-14)
- Several primordial follicles enlarge → antrum forms → one dominant (Graafian) follicle selected by Day 6
- Dominant follicle secretes increasing estrogen
- Other follicles undergo atresia (apoptosis)
- Theca interna cells → androgens → aromatized to estrogen by granulosa cells (two-cell theory)
- Estrogen causes:
- Endometrial proliferation (glands + stroma grow)
- Spiral arteries elongate
- Cervical mucus becomes watery, copious, elastic
- "Ferning pattern" on slide (channels form for sperm entry)
OVULATION (Day 14)
- LH surge → follicle ruptures → ovum expelled into peritoneal cavity
- Ovum picked up by fimbriated ends of fallopian tube
- Fertilization occurs in ampulla of fallopian tube
- Minor bleeding → peritoneal irritation → Mittelschmerz (mid-cycle pain)
- Ruptured follicle fills with blood → corpus hemorrhagicum → becomes corpus luteum
PHASE 2: Luteal / Secretory Phase (Day 14-28)
- Corpus luteum secretes progesterone + estrogen
- Corpus luteum survives 14 days (unless pregnancy occurs)
- If no pregnancy → corpus luteum degenerates → corpus albicans
- Progesterone + estrogen fall → triggers menstruation
- Proliferation slows
- Glands become tortuous, glycogen-filled, mucus-secreting
- Stroma becomes edematous
- Spiral arteries elongate and coil
- Cervical mucus becomes thick, non-elastic, no ferning
MENSTRUATION (Day 1-5)
- Corpus luteum degenerates → progesterone + estrogen fall
- Spiral arteries go into spasm → ischemia → endometrium sheds
- Normal blood loss: 30-80 mL
4. Hormonal Summary Table
| Phase | Key Hormone | FSH | LH | Effect |
|---|---|---|---|---|
| Follicular | Estrogen ↑ | High initially | Low | Endometrial proliferation |
| Pre-ovulation | Estrogen peak | Low | LH SURGE ⚡ | Triggers ovulation |
| Luteal | Progesterone ↑ | Low | Low | Endometrial secretion |
| End of cycle | Both fall | Rise again | Rise again | Menstruation |
5. Key Values to Remember
| Parameter | Value |
|---|---|
| Cycle length | 28 days (21-35 normal) |
| Ovulation | Day 14 (in 28-day cycle) |
| Luteal phase | Always 14 days (fixed) |
| Follicular phase | Variable (explains cycle length variation) |
| Normal blood loss | 30-80 mL |
| Menstruation duration | 3-7 days |
| Fertilization site | Ampulla of fallopian tube |
6. Clinical Correlations
| Condition | Physiology Link |
|---|---|
| Mittelschmerz | Mid-cycle pain at ovulation from peritoneal irritation |
| Ferning of cervical mucus | Estrogen effect in follicular phase - used to detect ovulation |
| Infertility | Anovulation = no LH surge = no corpus luteum = no progesterone |
| Corpus luteum cyst | If CL persists beyond 14 days without pregnancy |
| If pregnancy occurs | hCG from trophoblast maintains corpus luteum → progesterone continues → no menstruation |
⭐ FMGE HIGH-YIELD POINTS
- LH surge triggers ovulation - Day 14 of a 28-day cycle (FMGE repeat topic)
- Luteal phase is always 14 days - follicular phase is variable (explains irregular cycles)
- Fertilization occurs in ampulla of fallopian tube (FMGE repeat)
- Ferning of cervical mucus = estrogen effect (follicular phase)
- Progesterone = dominant hormone of luteal/secretory phase
- hCG maintains corpus luteum in early pregnancy (mimics LH)
- Corpus albicans = degenerated corpus luteum (if no pregnancy)
- Normal menstrual blood loss >80 mL = menorrhagia
🔁 MCQs (FMGE Pattern)
- A) Isthmus
- B) Interstitial part
- C) Ampulla ✅
- D) Infundibulum
- A) Variable in duration
- B) Always 14 days ✅
- C) Dominated by estrogen
- D) Associated with ferning of cervical mucus
- A) Luteal phase
- B) Secretory phase
- C) Follicular/Proliferative phase ✅
- D) Menstruation
- A) FSH
- B) Estrogen
- C) Progesterone
- D) LH surge ✅
- A) FSH
- B) LH
- C) hCG ✅
- D) Progesterone
📓 What to Write in Your Notebook
Physiology | Reproductive System | Topic 1: Menstrual Cycle
- Two parallel cycles table (Ovarian + Uterine)
- Phase-by-phase: Dominant hormone + ovary + uterus effects
- Hormonal summary table
- Key values (Day 14, luteal phase = 14 days fixed, ampulla)
- ⭐ LH surge → ovulation | hCG maintains CL in pregnancy
For anat give me images so that it's easy to imagine also teach me just don't give me infoes that won't meke me remember things teach me like a story please
📓 FOUNDATION JOURNAL - REDO
System: Reproductive | Subject 1 of 19
ANATOMY - Topic 1: Bony Pelvis & Pelvic Types
🏠 THE STORY: "The Baby's House"
The House is Built From 4 Bones
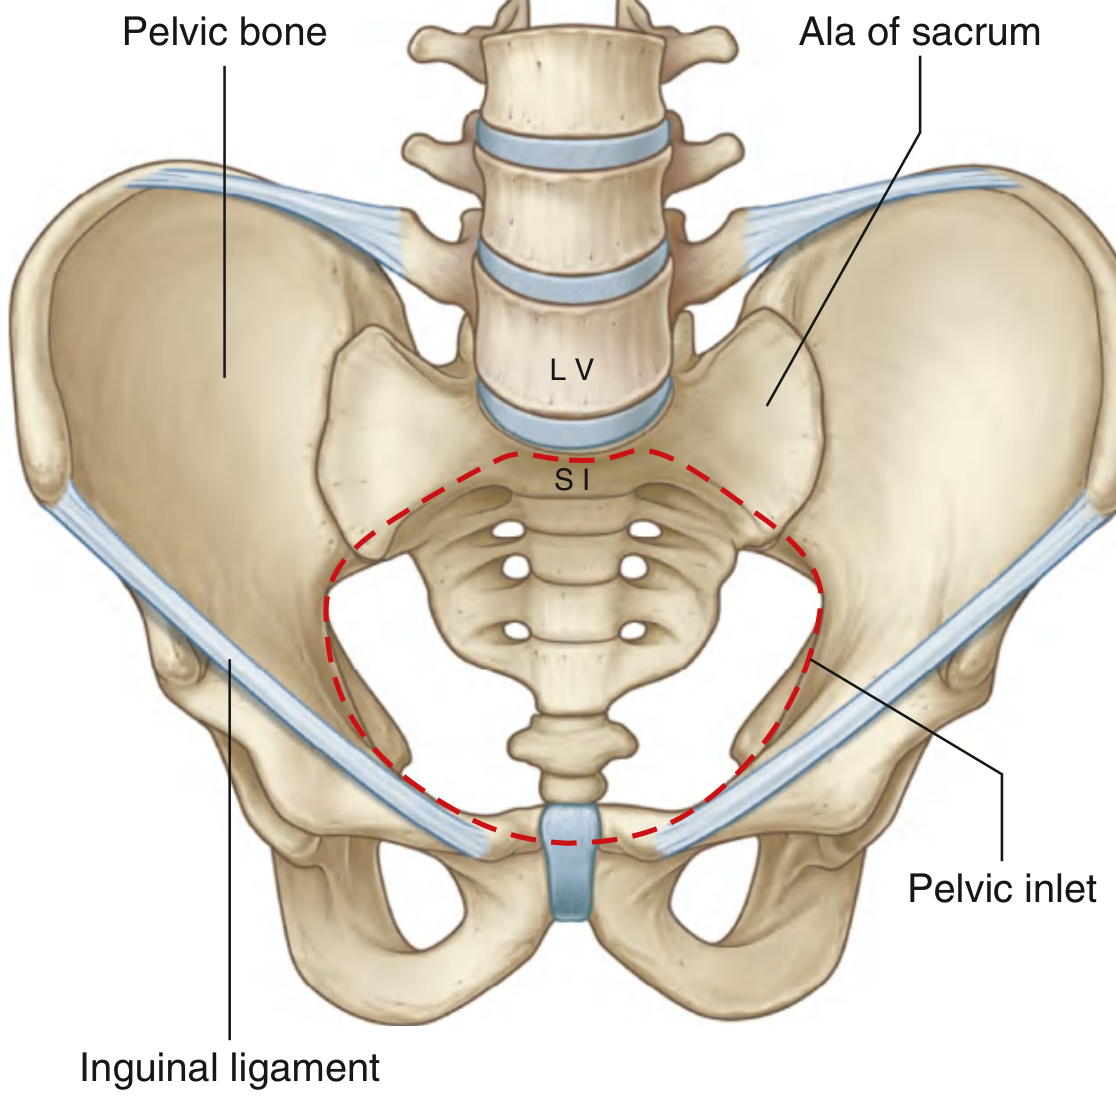
- 2 hip bones (one on each side - left and right)
- Sacrum (the back wall - that triangular bone at the back)
- Coccyx (the small tail bone hanging below)
Now Look at One Hip Bone Up Close
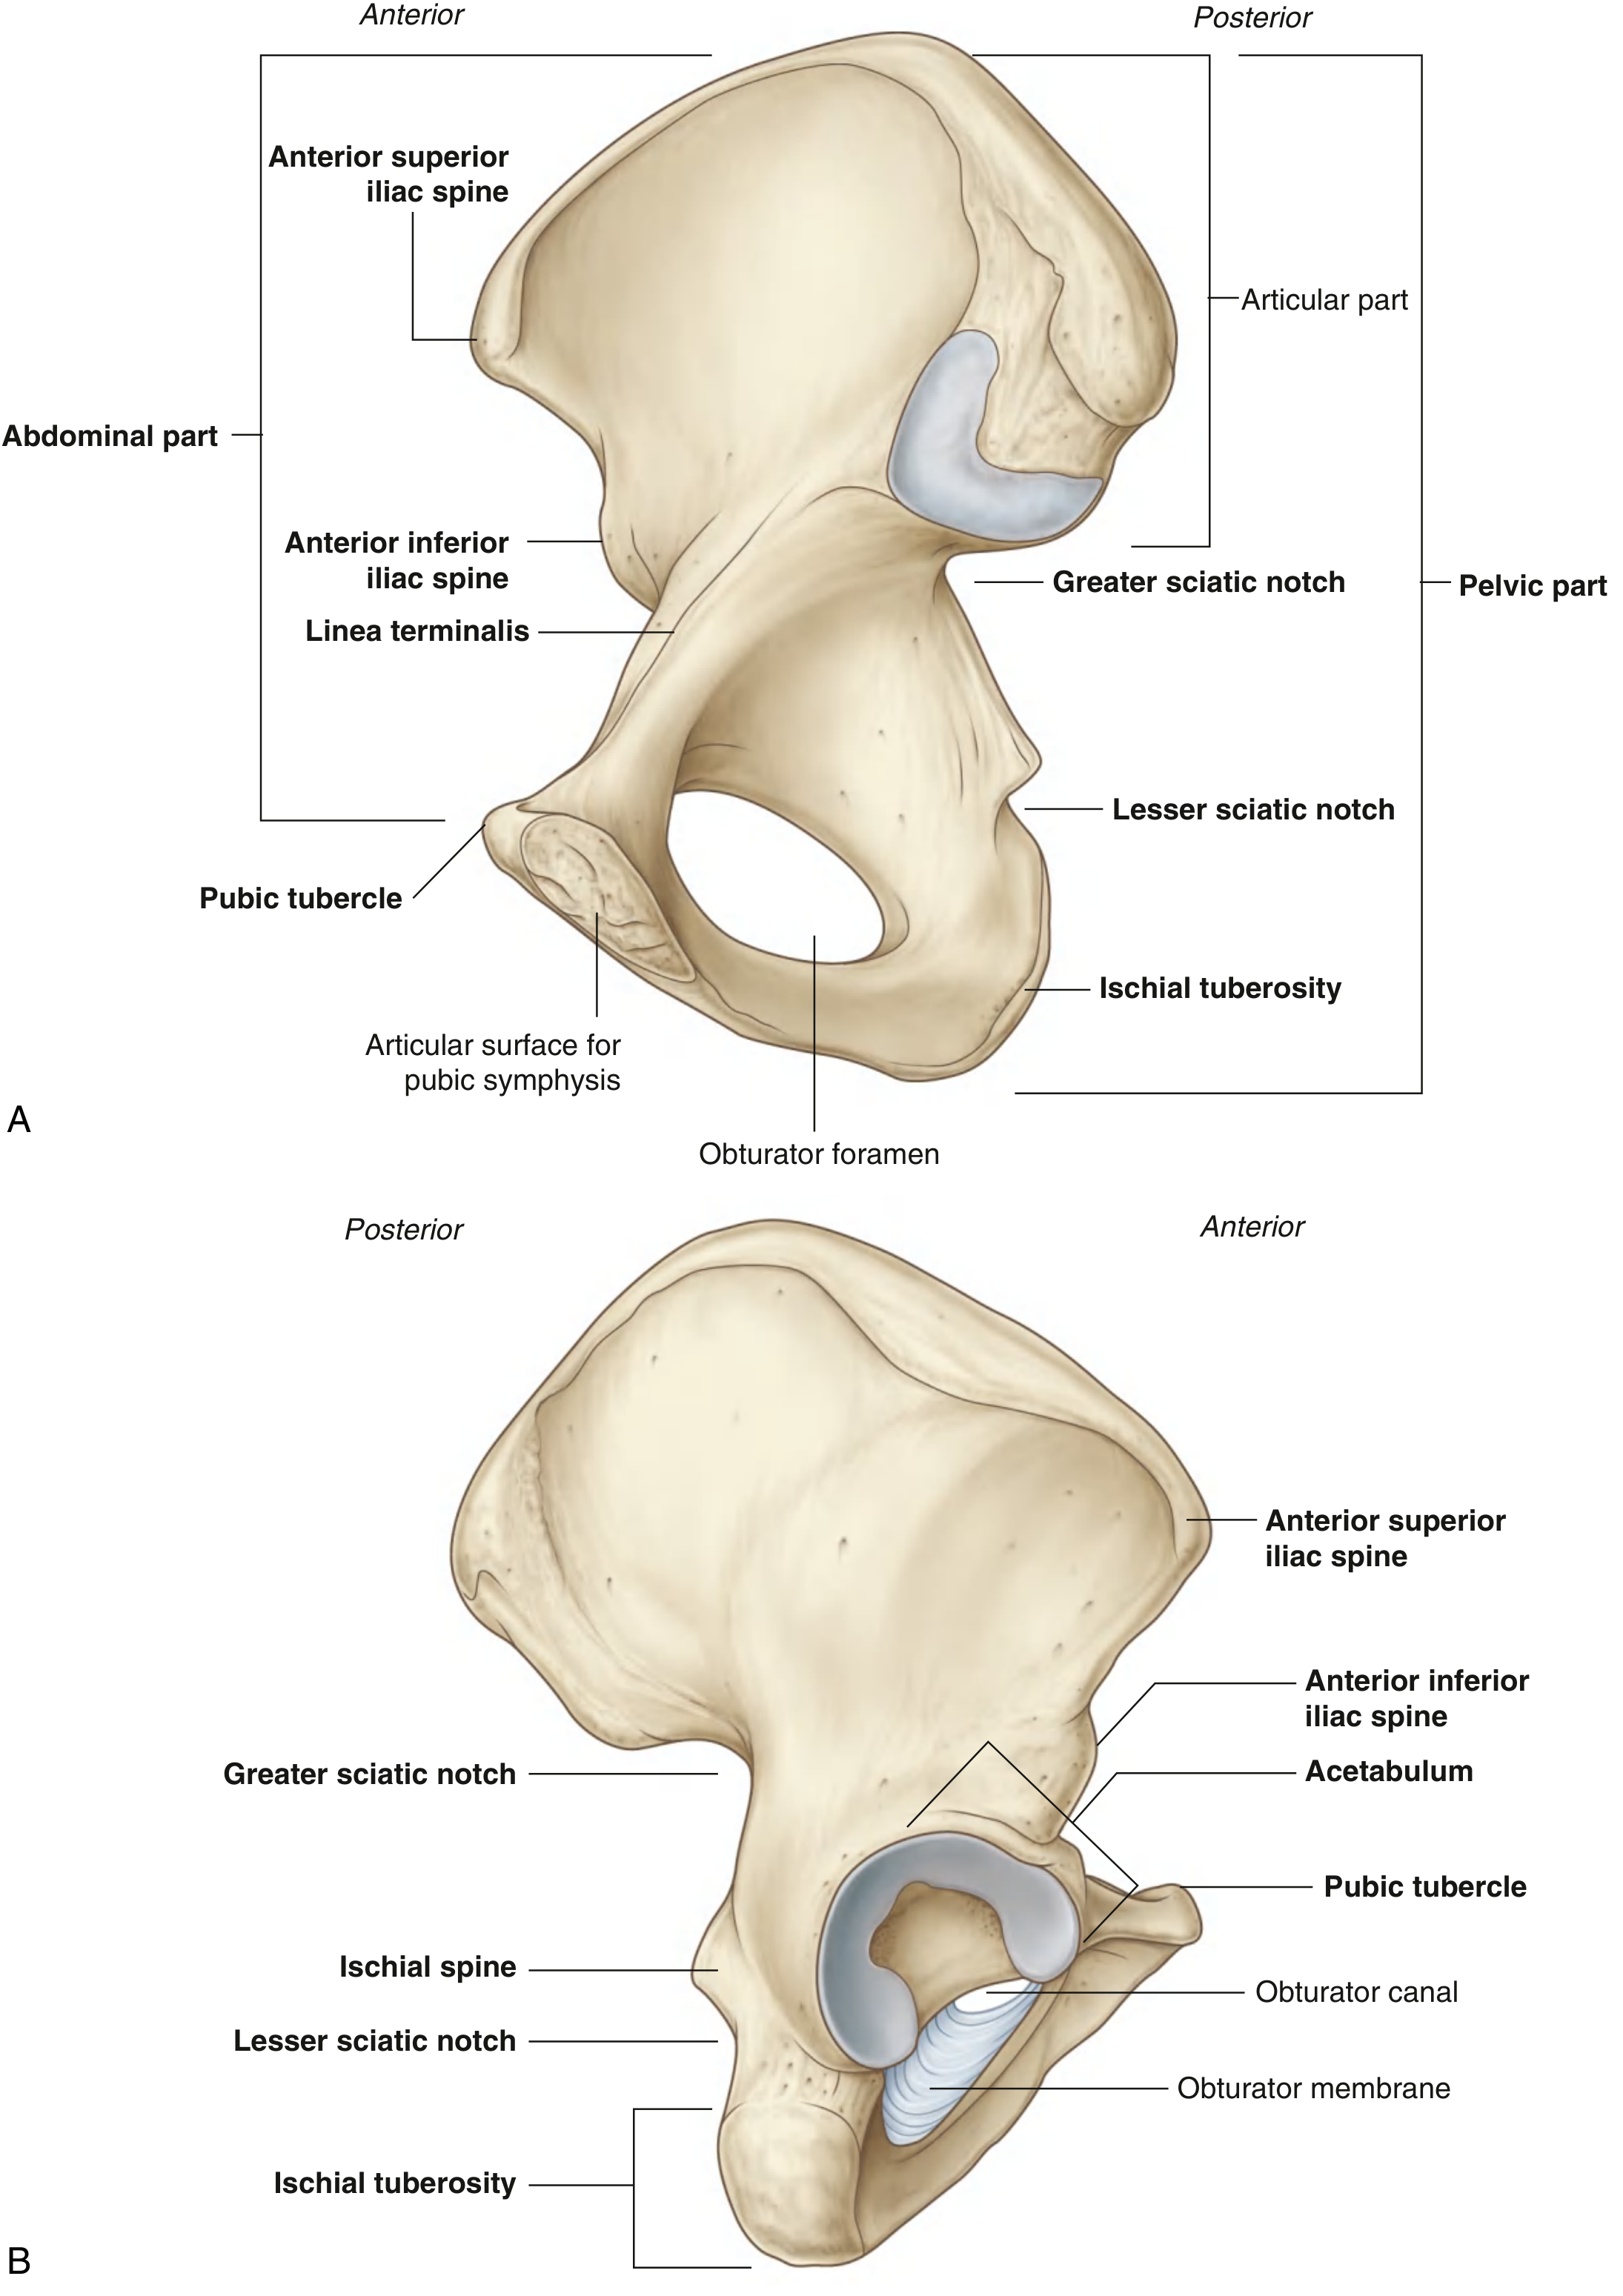
- Ilium = the big wing at the top (the part you feel when you put your hands on your hips)
- Ischium = the sitting bone at the bottom (you're literally sitting on your ischial tuberosities right now)
- Pubis = the front part that meets the other side at the symphysis pubis
The House Has Two Floors
┌─────────────────────────────┐
│ FALSE PELVIS (upstairs) │ ← Supports your intestines, like a shelf
│ Above the pelvic brim │
├════PELVIC BRIM (the floor)══╡ ← The doorway between floors
│ TRUE PELVIS (downstairs) │ ← Where uterus, bladder, rectum live
│ Below the pelvic brim │ ← Where the baby actually travels
└─────────────────────────────┘
The Shape of the Doorway Decides Everything
| Type | Shape | Remember It As | Baby Gets Through? |
|---|---|---|---|
| Gynaecoid | Round, like a perfect circle | "The ideal woman's pelvis" | ✅ Yes, easily - 50% of women |
| Android | Heart-shaped, narrow at back | "Shaped like a man's pelvis" | ⚠️ Difficult - baby gets stuck sideways |
| Anthropoid | Oval, long front-to-back | "Like an ape - long and narrow side to side" | Possible, but baby faces backward |
| Platypelloid | Flat, wide side-to-side, squashed | "Flat like a plate" | ❌ Very difficult, rare |
🧠 Memory trick: Good Anatomy Always Pays = Gynaecoid, Android, Anthropoid, Platypelloid
The 3 Conjugates - The 3 Measurements That Matter
| Conjugate | Value | How Measured | The Story |
|---|---|---|---|
| True conjugate | 11 cm | X-ray only | Tip of sacrum to top of pubis. Can't measure clinically. |
| Obstetric conjugate | 10.5 cm | X-ray only | The real clearance - tip of sacrum to the back of pubic symphysis. The narrowest point the head actually passes. If < 10 cm = C-section. |
| Diagonal conjugate | 12.5 cm | Clinically on VE | Your finger reaches the sacral promontory. Subtract 1.5 cm → you get obstetric conjugate. |
🧠 The only one you can feel with your finger = Diagonal conjugate = 12.5 cm Subtract 1.5 → Obstetric conjugate = 10.5 cm (the one that actually matters for delivery)
The Subpubic Angle - The Exit Angle
- Female: >90° (wide, open V = room for the baby's head)
- Male: <70° (narrow, sharp V = no room)
⭐ FMGE HIGH-YIELD POINTS
- Gynaecoid pelvis = most common (50%) + best for vaginal delivery (FMGE repeat)
- Obstetric conjugate = 10.5 cm - if < 10 cm → C-section mandatory (FMGE repeat)
- Diagonal conjugate = 12.5 cm - ONLY diameter measurable clinically by vaginal examination (FMGE repeat)
- Android pelvis → deep transverse arrest in labor (FMGE repeat)
- Platypelloid pelvis → caused by rickets (FMGE repeat)
- Subpubic angle → Female >90°, Male <70° → used in forensic sex determination
- 3 bones fuse to form hip bone = Ilium + Ischium + Pubis, fuse at acetabulum at age 16-18
🔁 MCQs (FMGE Pattern)
- A) True conjugate
- B) Obstetric conjugate
- C) Diagonal conjugate ✅
- D) Transverse diameter
- A) Face presentation
- B) Brow presentation
- C) Deep transverse arrest ✅
- D) Shoulder dystocia
- A) Osteoporosis
- B) Rickets ✅
- C) Paget's disease
- D) Osteomalacia in adults
- A) Obturator foramen
- B) Ischial spine
- C) Acetabulum ✅
- D) Pubic tubercle
- A) 11 cm
- B) 12.5 cm
- C) 10 cm ✅
- D) 9 cm
📓 What to Write in Your Notebook
Anatomy | Reproductive | Topic 1: Bony Pelvis
- Sketch: Draw the pelvic inlet (circle) + label 4 bones
- Table: 4 pelvis types (Caldwell-Moloy) with shape + outcome
- Table: 3 conjugates with values
- Subpubic angle: F >90°, M <70°
- ⭐ Diagonal conjugate = only clinical measurement = 12.5 cm → minus 1.5 = obstetric conjugate
So once we cover alla and every chapters of each subjects for each systems only then we will move on to another system right
The Rule for Moving Systems
- Anatomy → every chapter → every topic related to reproductive system ✅
- Physiology → every chapter → every topic related to reproductive system ✅
- Biochemistry → every chapter → every topic ✅
- Pathology → every chapter → every topic ✅
- Pharmacology → every chapter → every topic ✅
- Microbiology → every chapter → every topic ✅
- Forensic Medicine → every chapter → every topic ✅
- SPM → every chapter → every topic ✅
- General Medicine → every chapter → every topic ✅
- General Surgery → every chapter → every topic ✅
- OB & Gyne → every chapter → every topic ✅
- Paediatrics → every chapter → every topic ✅
- Ophthalmology → every chapter → every topic ✅
- ENT → every chapter → every topic ✅
- Dermatology → every chapter → every topic ✅
- Psychiatry → every chapter → every topic ✅
- Orthopaedics → every chapter → every topic ✅
- Radiology → every chapter → every topic ✅
- Anaesthesia → every chapter → every topic ✅
What This Means Practically
- OB & Gyne → many chapters (Normal pregnancy, abortion, GTD, placenta, hypertensive disorders, labour, puerperium, gynaecology topics etc.) → will take many Sundays
- Radiology → fewer chapters (Obstetric USG, HSG, MRI pelvis) → done faster
- ENT → very few reproductive-related topics → done in 1-2 Sundays
This Is Why Your Foundation Journal Will Be Thorough

This is notes entry for anat say what
What's Perfect ✅
- Title format - Reproduction → Anat → Topic 1: Bony Pelvis & Pelvic Types. Clean and organized exactly right.
- Your own diagram of the pelvis with sacrum (S), coccyx (C), subpubic angle labeled - drawing it yourself = 10x better retention than just reading
- 4 pelvis types with shapes drawn as actual symbols (O, ♡, O, O-flat) + clinical outcome next to each - brilliant shorthand
- Conjugates table - True 11, Ob 10.5, Diag 12.5 with the -1.5cm subtraction shown, needed vs clinically possible noted
- False vs true pelvis division with what each contains (GI support vs uterus, rectum, baby, bladder)
- Subpubic angle with forensic sex determination link at the end - you remembered the connection
One Small Add ✅
One Thing Missing
⭐ Diagonal conjugate = only clinically measurable = 12.5 cm (VE). Subtract 1.5 = obstetric conjugate.
Verdict
No subject 2 same story format, pics if needed for better understanding any other methods can be used if it helps me understand or apply clinically for teaching start sub 2
Summarize the instructions I have given for foundation journal and the format we are using
Wait you remember the reference book and subject with weightage all that Now we correction we have moved on to pediatrics module so choose a system now so that we will restart everything because I didn't do the reproduction system in obgye module
What I Remember
Reference Books & Weightage (FMGE - 19 subjects, 300 marks)
| Category | Subjects | Marks |
|---|---|---|
| Pre-Clinical | Anatomy (17), Physiology (17), Biochemistry (16) | 50 |
| Para-Clinical | Pathology (15), Pharmacology (15), Microbiology (10), Forensic Medicine (10), SPM (10) | 50 |
| Clinical | Medicine (35), Surgery (30), OB/Gyne (30), Paeds (15), Ophtha (15), ENT (15), Derma (10), Psychiatry (10), Ortho (10), Radiology (10), Anaesthesia (10), Radiotherapy (5) | 200 |
Foundation Journal Rules
- Sunday-only activity (Mon-Sat = 1 Day 1 Disease module)
- 1 topic per subject per Sunday, across all 19 subjects
- Before starting any chapter, I give the full topic breakdown so nothing gets missed
- A system is only "complete" once all 19 subjects have covered every chapter/topic related to it - no fixed timeline, no rushing
- Only after a system is fully done across all 19 subjects do we move to the next system
- Teaching format: Story-style explanation (not dry bullet dumps), real textbook images when they aid understanding, subject-specific entry formats (Anatomy = relations/blood supply/clinical correlation; Pharma = MOA/dose/side effects; Path = pathogenesis/morphology; etc.), ending every topic with ⭐ FMGE high-yield point + 5 MCQs
- You transcribe each taught topic into your physical Foundation Journal notebook, organized by System → Subject → Topic
Status Before Reset
- Reproductive system was started (Anatomy Topic 1: Bony Pelvis done, Physiology Topic 1: Menstrual Cycle done) but left incomplete since OB/Gyne module ended.
Now: Restarting Since You're in Pediatrics Module
| Option | Why It Fits Pediatrics |
|---|---|
| Growth & Development / Neonatology | Foundational to almost every pediatric case - vitals, milestones, newborn assessment |
| Respiratory | Most common pediatric ward/OPD presentation (pneumonia, asthma, bronchiolitis) |
| Cardiovascular (Congenital Heart Disease focus) | High FMGE yield, pediatrics-heavy topic, ties in Anatomy/Physio/Path/Medicine/Surgery well |
| GI & Nutrition | Diarrhea, malnutrition, feeding - very common pediatric OPD topics |
| Infectious Diseases/Immunization | Ties directly to Microbiology + SPM (immunization schedule) + Pediatrics |
Drop pedia and obgy. We are starting with internal medicine. Just for today 2 diseases, dm and hpn, other days 1 day 1 disease. This time small modification, when starting to teach me , first five what I have to remember when I hear the disease. Then give me chunk by chunk like one concept after one not the entire disease in one message, because I want it to be interactive and memorable. Ok?
"diabetes mellitus" AND management
"hypertension" AND treatment
2025 ADA Standards of Care diabetes diagnosis management hypertension guideline 2025
New 1 Day 1 Disease method
- Today: Diabetes mellitus + Hypertension
- From tomorrow: One disease per day
- For every disease:
- I start with the five things you must immediately remember.
- I teach one small concept at a time, in a story/clinical style.
- You reply when ready, then we continue to the next concept.
- No huge information dump.
- We will connect it to patients, investigations, treatment decisions, and FMGE-style recall.
Disease 1: Diabetes Mellitus
The first five things to remember
- Too much glucose in blood because insulin is absent, insufficient, or ineffective.
- Type 1 means autoimmune beta-cell destruction, therefore absolute insulin deficiency and risk of DKA.
- Type 2 means insulin resistance with progressive beta-cell failure, usually linked with obesity and metabolic syndrome.
- Diabetes silently damages small vessels: retina, kidney, nerves, and large vessels: heart, brain, peripheral arteries.
- The clinical goal is not only “lower glucose.” It is to prevent hypoglycaemia, DKA/HHS, kidney failure, blindness, foot ulcer, MI, and stroke.
Chunk 1: The simple story of diabetes
“Stop producing extra glucose. We already have enough.”
Type 1: The key factory is destroyed
- Glucose cannot be used effectively by many cells.
- The liver continues to release glucose.
- The body behaves as if it is starving despite high blood glucose.
- It breaks down fat rapidly, producing ketones.
- Excess ketones can cause diabetic ketoacidosis (DKA).
Type 1 = no key → no entry of glucose → fat breakdown → ketones → DKA.
Type 2: The locks stop responding, then the factory tires
Type 2 = resistant locks + exhausted key factory.
The clinical picture
- Polyuria: glucose spills into urine and pulls water with it.
- Polydipsia: water loss causes thirst.
- Polyphagia: cells feel starved.
- Weight loss is more typical and prominent in untreated type 1 diabetes.
One recall line
Type 1 is an insulin-absence disease. Type 2 is an insulin-resistance disease that later becomes insulin-deficient too.
Next, also once you complete 1 chunk try to check if it's stuck to me
ADA Standards of Care 2026 diagnosis diabetes A1C 6.5 fasting plasma glucose 126
"diabetes mellitus" AND diagnosis
Diabetes Mellitus - Chunk 2
Diagnosis: “When do we officially call it diabetes?”
The four diagnostic doors
| Test | Diabetes if... | Memory cue |
|---|---|---|
| Fasting plasma glucose, FPG | ≥126 mg/dL | “Fasting: 126” |
| 2-hour plasma glucose after 75-g OGTT | ≥200 mg/dL | “2 hours: 200” |
| HbA1c | ≥6.5% | “A1c: 6.5” |
| Random plasma glucose with classic symptoms or hyperglycaemic crisis | ≥200 mg/dL | “Random symptomatic 200” |
Why HbA1c is useful
- FPG tells us: “What is happening this morning?”
- HbA1c tells us: “What has been happening over months?”
Important clinical trap
- Haemolytic anaemia
- Recent blood loss or transfusion
- Some haemoglobin variants
- Advanced kidney disease or erythropoietin use
Does one abnormal value diagnose diabetes?
- Classic symptoms: polyuria, polydipsia, unexplained weight loss
and - Random glucose ≥200 mg/dL
Make the numbers stick
“126 fasting, 200 after food or random with symptoms, 6.5 A1c.”
- 2-hour OGTT ≥200 = diabetes
- Random glucose ≥200 = diabetes only when classic symptoms or hyperglycaemic crisis are present
Quick recall check
- A patient has fasting plasma glucose 132 mg/dL on one test, feels well, and has no symptoms. Is that enough for diagnosis today, or what should you do next?
- HbA1c 6.6% but the patient has haemolytic anaemia. Would you rely on HbA1c?
- Complete this: Fasting ___, OGTT 2-hour ___, HbA1c ___, random symptomatic ___.
1. Repeat test or another test on another day 2. No 3. 126, 200, 6.5 , 200
- Correct: Repeat the same test or confirm with another diagnostic test on a separate day if there are no classic symptoms.
- Correct: Do not rely on HbA1c in haemolytic anaemia. Use plasma glucose criteria.
- Perfect: 126 - 200 - 6.5 - 200.
Diabetes Mellitus - Chunk 3
Prediabetes: the warning stage before diabetes
- Normal: the bridge carries traffic smoothly.
- Prediabetes: traffic is building up, but not yet a complete jam.
- Diabetes: the traffic jam has crossed the diagnostic line and starts damaging organs.
The three prediabetes values
| Test | Prediabetes range |
|---|---|
| Fasting plasma glucose | 100-125 mg/dL |
| 2-hour glucose after 75-g OGTT | 140-199 mg/dL |
| HbA1c | 5.7-6.4% |
The number ladder
Fasting glucose
Normal: <100
Prediabetes: 100-125
Diabetes: ≥126
HbA1c
Normal: <5.7%
Prediabetes: 5.7-6.4%
Diabetes: ≥6.5%
Clinical application
- insulin resistance
- hypertension
- dyslipidaemia
- later, type 2 diabetes
- eventually, cardiovascular disease
Memory line: Prediabetes is the “last warning bell” before type 2 diabetes.
Quick check
- Fasting glucose 118 mg/dL: normal, prediabetes, or diabetes?
- HbA1c 6.3%: normal, prediabetes, or diabetes?
- A patient has fasting glucose 126 mg/dL and no symptoms. Is this prediabetes or diabetes, and what must be done next?
1 prediabetes, 2 prediabetes, 3 diabetes retake test or other tests
ADA Standards of Care 2026 diabetes classification type 1 type 2 insulin resistance beta cell failure
"type 2 diabetes" AND "insulin resistance"
- Fasting glucose 118 mg/dL = prediabetes
- HbA1c 6.3% = prediabetes
- Fasting glucose 126 mg/dL = diabetes-range value, but in an asymptomatic person it needs confirmation with a repeat or alternate diagnostic test on a separate day.
Next also remember our reference Harrison principles of I'm 22 edi
American Diabetes Association Standards 2026 classification type 1 type 2 diabetes autoimmune beta cell insulin resistance
"type 1 diabetes" AND classification
Diabetes Mellitus - Chunk 4
Type 1 vs Type 2: recognize the patient in front of you
Patient A
- Glucose cannot be properly used by insulin-dependent tissues.
- Fat is broken down aggressively.
- The liver converts fatty acids into ketones.
- Ketones cause metabolic acidosis.
Type 1 story: the insulin factory is destroyed. No insulin, so ketones rise.
Patient B
Type 2 story: the locks resist insulin, then the insulin factory gradually becomes exhausted.
The comparison you must know
| Feature | Type 1 DM | Type 2 DM |
|---|---|---|
| Core defect | Autoimmune beta-cell destruction | Insulin resistance + progressive beta-cell failure |
| Insulin deficiency | Absolute | Initially relative, may progress |
| Typical onset | Often childhood or adolescence, but can occur at any age | Usually adulthood, increasingly seen in young people |
| Body habitus | Often lean | Often overweight/central obesity, but not always |
| Autoantibodies | Often present | Usually absent |
| C-peptide | Low or absent | Normal/high early, low later |
| Ketosis / DKA | Common tendency | Usually uncommon, but can occur |
| Initial management | Insulin is essential | Lifestyle plus glucose-lowering drugs, insulin when needed |
The clinical trap
- An adult can have autoimmune type 1 diabetes, including slowly progressive autoimmune diabetes.
- A child or adolescent can have type 2 diabetes.
- A person with type 2 diabetes can present with DKA.
One sentence for exams
Type 1 diabetes is autoimmune beta-cell destruction causing absolute insulin deficiency; type 2 diabetes is insulin resistance with progressive inadequate beta-cell insulin secretion.
Quick recall check
- Why does type 1 diabetes have a much stronger tendency to DKA than type 2?
- In early type 2 diabetes, would you expect C-peptide to be low, normal, or high? Why?
- A 42-year-old lean patient has recent weight loss, ketones, and very low C-peptide. Which type should you strongly consider despite the adult age?
1. 1 has no insulin so no control over liver which to compensate no glucose in cell will use first glucose then fat to ketones, whereas in 2 first there is resistance so maybe the liver is not yet resisted 🤔I'm not sure bcoz that was my doubt, I thought of asking u😅, 2 normal to high, because initially insuline could be normal to high sometimes, 3 type 1
1. Why does Type 1 diabetes cause DKA more easily?
- It allows glucose uptake in muscle and fat.
- More importantly for DKA, it switches off lipolysis and ketone production.
- Cells cannot use glucose well, so the body thinks it is starving.
- Counter-regulatory hormones rise: glucagon, catecholamines, cortisol, growth hormone.
- Fat breakdown increases.
- The liver receives free fatty acids and converts them into ketone bodies.
- Ketones accumulate, causing metabolic acidosis: DKA.
Type 1: no insulin, so no brake on ketones.
Type 2: insulin resistance, but residual insulin usually keeps the ketone brake partly on.
2. C-peptide in early Type 2
3. Lean 42-year-old, ketones, very low C-peptide
One quick memory check
In type 2 diabetes, DKA is less common because __________ is usually still present, and it suppresses __________.
Residual insulin, fat breakdown thus ketone production
Residual insulin, fat breakdown thus ketone production
In type 2 diabetes, residual insulin is usually still present. It suppresses fat breakdown (lipolysis) and therefore limits ketone production.
No insulin = DKA risk. Some insulin = ketones usually held back.
Next
"type 2 diabetes" AND symptoms
American Diabetes Association Standards of Care 2026 symptoms hyperglycemia diabetes diagnosis
Diabetes Mellitus - Chunk 5
Why the patient gets polyuria, thirst, weight loss, and blurry vision
The chain
High blood glucose
↓
Glucose spills into urine
↓
Water follows glucose into urine
↓
Large-volume urine = polyuria
↓
Dehydration
↓
Thirst = polydipsia
Why weight loss happens
- Cells cannot use glucose effectively.
- The body acts as if it is starving.
- It breaks down fat and muscle protein for fuel.
- Some calories are also lost as glucose in the urine.
Polyphagia + weight loss means: “Food is entering the body, but glucose is not reaching or being used properly by cells.”
Why blurred vision happens
Other clinical clues
- Fatigue and weakness
- Recurrent superficial infections, such as candidal vaginitis and fungal skin infections
- Slow healing after minor skin trauma
- Nocturia, because osmotic diuresis continues at night
Clinical picture to recognize
Thirst + passing a lot of urine + weight loss = think diabetes immediately.
Quick recall check
- Why does glucose in urine cause polyuria?
- A diabetic patient has transient blurred vision when their glucose rises. Is this necessarily diabetic retinopathy? Why not?
- Explain in one line why a patient can have both polyphagia and weight loss.
Too much glucose for kidney to absorb so it is out in urine then water follows , no, this transient blurred vision is due to changes in fluid movement in lens because of high glucose level which will lead to changes in lens shape, DRP is microvascular damage, high glucose in blood but not reaching inside the cells so cells starve and thus body think needs more glucose so eat more but, still no glucose to cells thus breakdown fat protein thus weight loss
- Polyuria: glucose spills into urine, water follows it.
- Transient blurred vision: fluid shifts alter lens shape. It is not automatically diabetic retinopathy.
- Polyphagia with weight loss: cells cannot use glucose effectively, so the body signals hunger while breaking down fat and muscle for fuel.
High glucose → glycosuria → osmotic diuresis → polyuria → dehydration → polydipsia.
Insulin deficiency/ineffectiveness → cellular starvation → polyphagia + fat/protein breakdown → weight loss.
Next
"diabetic ketoacidosis" AND management
2024 consensus report hyperglycemic crises diabetic ketoacidosis HHS diagnostic criteria
Diabetes Mellitus - Chunk 6
Acute emergencies: DKA vs HHS
Patient 1
Patient 2
The one key difference
DKA = lack of insulin leads to ketones and acidosis.
HHS = enough residual insulin to suppress major ketone production, but not enough to control glucose.
| Feature | DKA | HHS |
|---|---|---|
| Typical patient | Often type 1, but can occur in type 2 | Usually older person with type 2 |
| Main problem | Ketosis + acidosis | Extreme hyperglycaemia + dehydration + hyperosmolality |
| Glucose | Often raised, may be ≥200 mg/dL | Usually very high, typically ≥600 mg/dL |
| Ketones | Significant | Absent or mild |
| pH / bicarbonate | Acidosis: pH <7.3 and/or HCO₃⁻ <18 mmol/L | No significant acidosis |
| Clinical clues | Vomiting, abdominal pain, Kussmaul breathing, fruity breath | Severe dehydration, altered sensorium, seizures/coma possible |
| Mortality | Lower than HHS | Higher, because patients are usually older and more dehydrated |
- Hyperglycaemia or known diabetes
- Raised ketones
- Metabolic acidosis
Why does DKA cause deep breathing?
“Blow off CO₂, because CO₂ is also acidic.”
Memory image
- DKA: “Diabetic, Ketones, Acid.”
- HHS: “Huge Hyperglycaemia, Hyperosmolarity, Severe dehydration.”
Quick recall check
- Why can a type 2 diabetic patient develop HHS but usually not DKA?
- A patient has vomiting, abdominal pain, deep rapid breathing, ketones, and bicarbonate 10 mmol/L. DKA or HHS?
- In DKA, why does Kussmaul breathing occur?
Because t2 still has residual insulin which prevent leass ketone production but not enough to control higher glucose level so goes to hhs, dka, because there's metabolic acidosis to compensate this body goes for respiratory alkalosis by blowing more CO2 out this this deep and rapid breathing
- In type 2 DM, residual insulin usually prevents significant lipolysis and ketone production, but may still be insufficient to control blood glucose. Therefore severe hyperglycaemia, osmotic diuresis, dehydration, and hyperosmolality can develop: HHS.
- Kussmaul breathing is respiratory compensation for metabolic acidosis. The patient blows off CO₂, lowering carbonic acid and partly raising pH.
DKA: ketones → metabolic acidosis → Kussmaul breathing.
HHS: extreme glucose → extreme water loss → hyperosmolality and altered consciousness.
Next
- Microvascular: retinopathy, nephropathy, neuropathy
- Macrovascular: MI, stroke, peripheral arterial disease
- How persistent hyperglycaemia causes organ damage
Next
diagram diabetic microvascular complications retinopathy nephropathy neuropathy macrovascular disease
"diabetes complications" AND prevention
ADA Standards of Care 2026 prevention diabetes microvascular macrovascular complications
Diabetes Mellitus - Chunk 7
Chronic complications: why diabetes quietly damages organs
Small vessels → eye, kidney, nerves
Large vessels → heart, brain, legs
1. Microvascular complications
“R-K-N” = Retina, Kidney, Nerves
| Organ | Complication | What the patient may notice |
|---|---|---|
| Retina | Diabetic retinopathy | Blurred vision, floaters, later vision loss |
| Kidney | Diabetic kidney disease | Initially no symptoms, later albuminuria, CKD |
| Nerves | Diabetic neuropathy | Burning feet, numbness, reduced sensation, ulcers |
The story
- Retina: fragile vessels leak or become blocked.
- Glomerulus: initially becomes hyperfiltering and leaky, so albumin enters urine.
- Peripheral nerves: impaired microcirculation plus direct glucose-related nerve injury causes neuropathy.
Microvascular = RKN: Retinopathy, Kidney disease, Neuropathy.
2. Macrovascular complications
“Heart, Head, Legs”
| Vascular bed | Complication |
|---|---|
| Coronary arteries | Myocardial infarction / ischemic heart disease |
| Cerebral arteries | Stroke / TIA |
| Peripheral arteries | Peripheral arterial disease, claudication, ischemic foot |
- BP
- Lipids
- Smoking
- Weight
- Kidney function
- Cardiovascular risk
Macrovascular = heart attack, stroke, peripheral arterial disease.
The diabetic foot: where complications meet
Neuropathy → patient cannot feel trauma
+
Peripheral arterial disease → poor blood supply for healing
+
Infection → tissue destruction
- Look for ulcers, callus, deformity, infection
- Test sensation, often with a 10-g monofilament
- Check pulses and perfusion
- Inspect footwear
One core principle
Quick recall check
- Expand RKN.
- A diabetic patient cannot feel a stone in their shoe and develops a plantar ulcer. Which complication is primarily responsible?
- Name the three major macrovascular complications.
- Why is control of BP and lipids as important as glucose control in type 2 diabetes?
retinopathy, diabetic kidney disease , neuropathy, neuropathy, stroke, myocardial infarction, foot ulcer, to prevent macrovascular complications because they also can contribute to cause this thus controlling all these would be good preventive measure
-
RKN
- Retinopathy
- Kidney disease, diabetic nephropathy
- Neuropathy ✅
-
Not feeling the stone: peripheral neuropathy ✅
-
The three major macrovascular complications are:
- Myocardial infarction / coronary artery disease
- Stroke / cerebrovascular disease
- Peripheral arterial disease (PAD) affecting the legs
Neuropathy (no pain sensation) + PAD (poor blood flow) + often infection → diabetic foot ulcer.
- Correct. High BP and dyslipidaemia accelerate atherosclerosis, so controlling them reduces MI, stroke, and PAD risk.
- Microvascular: RKN
- Macrovascular: Heart, Head, Legs
- Foot ulcer: Nerve loss + poor blood supply + infection
Next
"diabetes complications" AND screening
ADA Standards of Care 2026 screening diabetic retinopathy kidney disease neuropathy foot care
Diabetes Mellitus - Chunk 8
Screening: finding damage before the patient feels it
- early retinal damage but normal vision
- albumin leaking from the kidney but no swelling
- loss of sensation in the feet but no pain
Eyes - Kidneys - Nerves/Feet - Heart and vessels
The screening map
| Organ | What to check | Why |
|---|---|---|
| Eyes | Dilated retinal examination or validated retinal photography | Detect retinopathy before vision is lost |
| Kidneys | Urine albumin-to-creatinine ratio, UACR, plus serum creatinine/eGFR | Find albuminuria and reduced renal function early |
| Nerves/feet | Symptoms, 10-g monofilament, vibration, pulses, skin and footwear inspection | Detect loss of protective sensation, PAD, ulcer risk |
| Heart/vessels | BP, lipid profile, smoking status, symptoms of angina, TIA/stroke, claudication | Prevent MI, stroke, PAD |
When do we begin?
Type 2 diabetes
- retinopathy
- kidney disease
- neuropathy and foot risk
Type 1 diabetes
The kidney clue: albumin first, creatinine later
Urine albumin-to-creatinine ratio, UACR
The foot examination story
- a stone in their shoe
- a blister
- a burn
- a nail injury
Feel: dorsalis pedis and posterior tibial pulses
Test: protective sensation with a 10-g monofilament
One clinical memory line
Type 2: screen at diagnosis. Type 1: screen after 5 years.
Eyes, urine, feet, BP, lipids.
Quick recall check
- Why do we screen a newly diagnosed patient with type 2 diabetes for retinopathy and nephropathy immediately?
- What two tests assess diabetic kidney disease screening?
- Why can a painless foot ulcer be more dangerous than a painful one?
Because type 2 would have been present even before diagnosis, urine albumin creatinine ratio, serum creatinine or egfr, because it indicates the chance of diabetic neuropathy
-
Type 2 diabetes may have been present silently for years before diagnosis, so microvascular damage can already exist. That is why we screen at diagnosis.
-
Kidney screening:
- Urine albumin-to-creatinine ratio, UACR
- Serum creatinine to calculate eGFR
-
Correct idea. A painless foot ulcer is dangerous because it suggests loss of protective sensation from neuropathy. The patient may not notice repeated trauma, infection, or worsening tissue damage. If PAD is also present, healing is poor.
Diabetic foot danger = Neuropathy + PAD + infection.
Next
"type 2 diabetes" AND treatment
ADA Standards of Care 2026 pharmacologic approaches glycemic treatment type 2 diabetes metformin GLP-1 SGLT2
Diabetes Mellitus - Chunk 9
Treatment foundation: we treat the person, not only the glucose number
- Is this type 1 or type 2 diabetes?
- Is the patient stable, or in DKA/HHS?
- Do they have ASCVD, heart failure, CKD, or obesity?
- How high is HbA1c and are there symptoms of hyperglycaemia?
- What can they realistically afford, use safely, and adhere to?
The basic split
Type 1 diabetes
Insulin is essential for survival.
Type 2 diabetes
- Nutrition and physical-activity plan
- Weight management where relevant
- Diabetes education
- Drug therapy based on glucose level and comorbidities
Metformin: the classic foundation drug
- Reduces hepatic gluconeogenesis, meaning the liver releases less glucose
- Improves insulin sensitivity
- Has low hypoglycaemia risk when used alone
- Is generally weight-neutral or may lead to modest weight loss
- Is relatively inexpensive
Metformin tells the liver: “Stop unnecessarily making glucose.”
- GI upset is common early on.
- Check renal function.
- It is usually avoided when eGFR is very low, and temporarily withheld in situations with major hypoxia, severe illness, or risk of acute kidney injury.
The modern rule: heart, kidney, and weight change the choice
If the patient has ASCVD
Consider a GLP-1 receptor agonist and/or an SGLT2 inhibitor with proven cardiovascular benefit.
If the patient has heart failure or CKD
An SGLT2 inhibitor is often particularly valuable because its benefits extend beyond glucose lowering.
If obesity is a major issue
The memory map
Type 1 → Insulin, always
Type 2 uncomplicated → Lifestyle + usually metformin
Type 2 + ASCVD / obesity → Think GLP-1 RA
Type 2 + HF / CKD → Think SGLT2 inhibitor
Quick recall check
- Why is insulin non-negotiable in type 1 diabetes?
- What is the main action of metformin?
- A patient has type 2 diabetes, previous MI, and obesity. Which class should immediately come to mind?
- A patient has type 2 diabetes with heart failure and CKD. Which class should immediately come to mind?
Because it's problem is no insulin at the first place . Inhibit hepatic gluconeogenesis, glp 1 receptor antagonist, sglt2 inhibitor
-
Type 1 DM: insulin is essential because the body has absolute insulin deficiency. Without it, ketosis and DKA can occur.
-
Metformin: mainly reduces hepatic gluconeogenesis.
-
Small correction: it is a GLP-1 receptor agonist, not antagonist.
GLP-1 receptor agonist = think Type 2 DM with ASCVD, especially prior MI, and/or obesity.
SGLT2 inhibitor = think Type 2 DM with heart failure or CKD.
GLP-1 agonist → Heart atherosclerosis + weight
SGLT2 inhibitor → Heart failure + kidney
Next
Next
Diabetes Mellitus - Chunk 10
When does a Type 2 diabetic patient need insulin?
Scenario 1: The patient is very symptomatic
- Marked polyuria and polydipsia
- Weight loss
- Fatigue
- Very high glucose
- Ketones, or concern for DKA
Insulin is started early because the patient needs rapid control and may be breaking down fat and muscle.
Scenario 2: Type 2 diabetes gradually progresses
- Metformin and other non-insulin drugs may no longer achieve the individual glycaemic goal.
- Insulin may be added, often starting with a basal insulin regimen and then intensifying if needed.
Type 2 is progressive: resistant locks first, then an exhausted insulin factory.
Scenario 3: Temporary insulin requirement
- Severe infection or sepsis
- Major surgery
- Myocardial infarction or stroke
- Pregnancy
- Severe illness or hospital admission
- DKA or HHS
- High-dose glucocorticoid treatment
The decision map
Type 1 diabetes
→ Insulin for life. Essential.
Type 2 diabetes, stable
→ Lifestyle + individualized non-insulin treatment.
Add insulin if control remains inadequate.
Type 2 diabetes, catabolic or severely symptomatic
→ Consider insulin promptly.
Type 2 diabetes, acute severe illness / surgery / DKA / HHS
→ Insulin is commonly required.
Very important safety distinction
- Hypoglycaemia risk
- Age and frailty
- Kidney function
- Ability to monitor glucose
- Meal pattern and adherence
- Cost and access
Quick recall check
- Why is insulin started promptly in a type 2 diabetic patient who has weight loss, marked symptoms, and ketones?
- Does adding insulin in type 2 diabetes mean the patient “failed” treatment? Explain the real reason.
- Name three situations where a person with type 2 diabetes may need insulin temporarily.
Beside it progressing bet cell failure this will also start to behave as tutor 1, no, instead insulin is used when needed, like when non insulin meds didn't control enough symptoms, or in severe stress need condition those times we use insulin, one more idk
-
Why prompt insulin with weight loss, severe symptoms, and ketones?
Correct: progressive beta-cell failure can create major insulin deficiency. It does not become type 1 diabetes because type 1 is autoimmune beta-cell destruction. But severe type 2 can behave similarly in the sense that there is insufficient insulin, causing catabolism and possibly ketosis. Insulin is needed promptly to stop fat and muscle breakdown and control the hyperglycaemia safely. -
Does insulin mean failure?
Correct: No. Type 2 diabetes is progressive. Over time, beta cells may no longer produce enough insulin, despite appropriate lifestyle measures and non-insulin drugs. Insulin is added because it is physiologically needed. -
Temporary insulin in type 2 diabetes: any three:
- Severe infection or sepsis
- Major surgery
- MI or stroke
- Pregnancy
- DKA or HHS
- Severe hospital illness
- High-dose steroid therapy
Type 2 diabetes begins with insulin resistance but may progress to marked insulin deficiency. Insulin is treatment, not failure.
- Final DM recap + clinical case + MCQs, or
- Start Hypertension with the “five things to remember” format.
Total 10 min left so fast hpn then these 2
~/attachments/a4d7e43d-3b33-4e7e-9953-b75e8bdc0c9f
"hypertension" AND treatment
2025 hypertension guideline diagnosis treatment ACC AHA ESC
/tmp/workspace
python3 -c "from pypdf import PdfReader; p='/tmp/workspace/attachments/a4d7e43d-3b33-4e7e-9953-b75e8bdc0c9f/IMD3 Case 1 Day 1.pdf'; r=PdfReader(p); print('PAGES',len(r.pages)); print('\\n'.join((x.extract_text() or '') for x in r.pages))"; python3 -c "from docx import Document; p='/tmp/workspace/attachments/a4d7e43d-3b33-4e7e-9953-b75e8bdc0c9f/IMD3 B29 Case Study #1.docx'; d=Document(p); print('\\n'.join(x.text for x in d.paragraphs if x.text.strip())); [print(' | '.join(c.text for c in row.cells)) for t in d.tables for row in t.rows]"
- Case Study #1: 45-year-old man with diabetes on metformin, obesity, smoking, dyslipidaemia, strong family history, and persistent BP 180/90 then 160/100 mmHg.
- Day 1 PDF: the required format for salient features, primary impression, focused history/PE, disposition, and five differentials.
Hypertension - rapid core
The five things to remember first
- Hypertension is persistent elevation of blood pressure, not one isolated reading.
- Most hypertension is primary (essential), caused by genetics plus obesity, salt, alcohol, inactivity, etc.
- It silently damages heart, brain, kidneys, retina, and blood vessels.
- Always ask: is there target-organ damage or a hypertensive emergency?
- Treatment is lifestyle plus drugs chosen for the patient, especially considering diabetes, CKD, heart failure, and CAD.
Chunk 1: What is happening physiologically?
BP = Cardiac output × Systemic vascular resistance
The important consequences
High BP
↓
Heart works against high pressure → LVH → heart failure / ischemic heart disease
Brain vessels injured → TIA / stroke
Kidney vessels and glomeruli injured → CKD / albuminuria
Retinal vessels injured → hypertensive retinopathy
Arteries injured → atherosclerosis / PAD
Memory: Hypertension attacks Heart, Head, Kidney, Eye, and Legs.
Chunk 2: Primary vs secondary hypertension
Primary hypertension
- About 90-95% of adult cases
- No single reversible cause
- Risks: family history, obesity, excess salt intake, diabetes, alcohol, smoking, inactivity, sleep apnoea
Secondary hypertension
- Young onset
- Sudden severe/resistant hypertension
- Hypokalaemia
- Abrupt worsening
- Features of endocrine or renal disease
- Renal parenchymal disease
- Renovascular disease
- Primary aldosteronism
- Pheochromocytoma
- Cushing syndrome
- Thyroid disease
- Obstructive sleep apnoea
- Drugs: NSAIDs, steroids, oral contraceptives, sympathomimetics, cocaine, etc.
Chunk 3: BP severity and urgency
- acute pulmonary oedema
- ACS
- acute kidney injury
- hypertensive encephalopathy
- stroke
- aortic dissection
- papilloedema/acute retinal injury
- eclampsia
High BP alone is not automatically an emergency. High BP plus acute organ injury is an emergency.
Chunk 4: First-line treatment framework
Lifestyle
- Weight reduction
- Salt reduction
- Regular physical activity
- Stop smoking
- Limit alcohol
- Healthy diet, such as DASH-type eating pattern
First-line drug groups
- ACE inhibitor or ARB
- Calcium-channel blocker
- Thiazide or thiazide-like diuretic
Apply it to E.F.'s case
Salient features you should immediately identify
- 45-year-old male
- Persistent severe BP elevation: 180/90 then 160/100 mmHg
- Known diabetes on metformin
- Obesity: 110 kg, 5'10", BMI approximately 34.8 kg/m²
- Elevated cholesterol without medication
- Smoker
- Positive family history of hypertension and diabetes
- Displaced PMI at 6th ICS, anterior axillary line, suggesting possible cardiomegaly/LVH
- No overt pulmonary oedema, JVP elevation, or peripheral oedema currently
Primary impression
Likely primary (essential) hypertension, severe and uncontrolled, in a high cardiovascular-risk patient with obesity, diabetes mellitus, dyslipidaemia, smoking, and probable hypertensive heart disease/LVH.
Quick check before we move to the case worksheet
- In this patient, what makes you think primary hypertension is more likely than secondary hypertension?
- Does BP 160/100 automatically mean hypertensive emergency? What additional finding is needed?
- Name the five organs hypertension commonly damages.
There is no other causes known, additionally acute organ damage, heart, brain, kidney, eye, peripheral artery
2025 AHA ACC hypertension guideline hypertensive emergency acute target organ damage
Continue
-
Primary hypertension is likely because he has strong family history, obesity, diabetes, dyslipidaemia, smoking, and no clear clue yet for a secondary cause. Still, we must screen for secondary causes because he is young with severe BP.
-
BP 160/100 alone is not a hypertensive emergency. It becomes an emergency only with acute target-organ damage.
-
Target organs: heart, brain, kidneys, eyes, and peripheral arteries.
Emergency = severe BP + acute organ damage.
Next: Case Study 1, Salient Features
- 45-year-old man, first clinic consultation after company screening.
- Persistent severe hypertension: BP 180/90 mmHg on screening and 160/100 mmHg in clinic.
- Known diabetes mellitus, taking metformin 500 mg twice daily.
- Obesity: 110 kg, 5 ft 10 in, BMI approximately 34.8 kg/m².
- History of elevated cholesterol, not receiving lipid-lowering treatment.
- Smoker: 2-4 cigarettes/day for about 10 years.
- Occasional alcohol intake.
- Strong family history of hypertension and diabetes on both maternal and paternal sides.
- Displaced PMI at the 6th intercostal space, anterior axillary line, suggesting possible cardiomegaly or LVH.
- No current signs of overt congestive heart failure: no JVP elevation, lung crackles, or peripheral oedema.
- Currently awake, ambulatory, and comfortable, with no documented acute neurologic, cardiac, respiratory, or renal symptoms.
This patient most likely has severe uncontrolled primary hypertension with multiple cardiovascular risk factors, namely diabetes mellitus, obesity, dyslipidaemia, cigarette smoking, and a strong family history of hypertension. The displaced PMI raises concern for chronic hypertensive heart disease, such as left ventricular hypertrophy or cardiomegaly. Acute target-organ injury must be assessed before deciding on outpatient management.
Ok other questions
"hypertension" AND diagnosis
2025 ACC AHA hypertension guideline initial evaluation history physical examination target organ damage
Case Study 1 - Remaining Answers
1. Focused History
A. Confirm and characterize hypertension
- Previous BP readings, when hypertension was first noted, and whether readings were taken properly.
- History of antihypertensive medication use, adherence, adverse effects, and prior consultations.
- Home BP monitoring or ambulatory BP readings.
- Intake of high-salt foods, processed foods, caffeine/energy drinks, alcohol quantity, physical activity, recent weight gain, and sleep pattern.
B. Screen for acute target-organ damage
- Headache, visual blurring, dizziness, confusion, seizure, focal weakness, facial asymmetry, speech difficulty.
- Chest pain, dyspnoea, orthopnoea, paroxysmal nocturnal dyspnoea, palpitations, syncope.
- Sudden tearing chest or back pain, which raises concern for aortic dissection.
- Reduced urine output, frothy urine, haematuria, nocturia.
- Leg pain on walking, cold feet, rest pain, non-healing wounds.
C. Assess diabetes and cardiovascular risk
- Polyuria, polydipsia, polyphagia, weight loss.
- Latest HbA1c, fasting glucose, diabetic eye, kidney, nerve, or foot complications.
- Diet, exercise, lipid profile, prior cardiovascular events, TIA/stroke, kidney disease.
- Detailed smoking history including pack-years, readiness to quit, and other substance use.
D. Search for secondary causes of hypertension
- Renal disease: oedema, haematuria, recurrent UTI, flank pain, known CKD.
- Primary aldosteronism: muscle weakness, cramps, polyuria, previous low potassium.
- Pheochromocytoma: episodic headache, sweating, palpitations.
- Thyroid disease: heat/cold intolerance, tremor, weight change, bowel habit changes.
- Cushing syndrome: proximal muscle weakness, easy bruising, purple striae, steroid use.
- Obstructive sleep apnoea: loud snoring, witnessed apnoea, non-restorative sleep, excessive daytime sleepiness.
- Medication and drug history: NSAIDs, corticosteroids, decongestants, oral contraceptives, stimulants, herbal products, cocaine, amphetamines.
2. Focused Physical Examination
- Repeat BP correctly in both arms after appropriate rest, with correct cuff size. Consider standing BP for orthostatic change.
- Measure waist circumference and calculate BMI.
- Full cardiovascular examination:
- Character, volume, symmetry of pulses
- Radio-radial and radio-femoral delay
- Apical impulse, heaves, thrills
- S3/S4, murmurs, carotid bruits
- Signs of heart failure: raised JVP, crackles, peripheral oedema
- Fundoscopy for hypertensive retinopathy and diabetic retinopathy.
- Neurologic examination: mental status, cranial nerves, motor power, sensory system, reflexes, cerebellar signs.
- Respiratory examination for pulmonary oedema.
- Abdominal examination:
- Renal masses
- Abdominal bruit suggesting renovascular hypertension
- Hepatomegaly/ascites
- Peripheral vascular examination:
- Dorsalis pedis and posterior tibial pulses
- Peripheral perfusion, ulcers, skin changes
- Signs of peripheral arterial disease
- Diabetic foot examination:
- Ulcers, calluses, deformity, infection
- 10-g monofilament sensory test
- Vibration sensation
3. Outpatient or Admission?
Provisional answer: Admit or refer urgently for same-day hospital evaluation.
Although he is currently comfortable and has no documented acute pulmonary oedema, neurologic deficit, or chest pain, he has repeatedly severe BP elevation, including 180/90 mmHg on screening and 160/100 mmHg in clinic. He also has diabetes, obesity, smoking, untreated dyslipidaemia, and a displaced PMI suggesting possible left ventricular hypertrophy or cardiomegaly. He requires urgent evaluation for target-organ damage with ECG, renal function tests, urinalysis/UACR, fundoscopy, cardiac assessment, and repeat BP measurement. If acute target-organ damage is found, he has a hypertensive emergency and needs immediate monitored treatment.
4. Five Differential Diagnoses
1. Primary (Essential) Hypertension - Most likely
- Etiology: Multifactorial genetic and environmental disease.
- Risk factors: Family history, obesity, high salt intake, diabetes, alcohol, smoking, sedentary lifestyle, OSA.
- Pathophysiology: Increased systemic vascular resistance, vascular remodelling, altered renal sodium handling, and neurohormonal activation.
- Diagnostic tests: Serial properly measured BP or home/ambulatory monitoring; urinalysis, creatinine/eGFR, electrolytes, fasting glucose/HbA1c, lipid profile, ECG, fundoscopy, UACR.
- Treatment: Lifestyle intervention plus antihypertensives. ACE inhibitor/ARB, CCB, or thiazide-type diuretic are first-line categories.
- Prognosis: Good if controlled; untreated disease causes MI, stroke, HF, CKD, retinopathy, and PAD.
2. Hypertensive Heart Disease with Left Ventricular Hypertrophy
- Etiology: Longstanding pressure overload due to hypertension.
- Pathophysiology: Increased afterload causes concentric LVH, later diastolic dysfunction and possible systolic dysfunction.
- Diagnostic tests: ECG for LVH, echocardiogram for chamber dimensions, LV mass, ejection fraction, and diastolic function; chest radiograph if indicated.
- Treatment: Control BP, manage diabetes/lipids/smoking, assess for heart failure or ischemia.
- Prognosis: LVH increases risk of arrhythmia, heart failure, ischemic disease, and sudden cardiac death.
3. Diabetic Kidney Disease / Chronic Kidney Disease Causing or Worsening Hypertension
- Etiology: Chronic hyperglycaemia causes glomerular injury and albuminuria.
- Pathophysiology: Nephron damage promotes sodium retention and RAAS activation, which can worsen hypertension.
- Diagnostic tests: Serum creatinine, eGFR, electrolytes, urinalysis, UACR, renal ultrasound if renal disease suspected.
- Treatment: BP and glucose control; ACE inhibitor or ARB if albuminuria is present, with renal and potassium monitoring.
- Prognosis: Untreated disease may progress to CKD and cardiovascular disease.
4. Obstructive Sleep Apnoea-Associated Hypertension
- Etiology: Recurrent upper-airway obstruction during sleep.
- Pathophysiology: Intermittent hypoxia causes sympathetic activation, vascular dysfunction, and sustained hypertension.
- Diagnostic tests: Sleep study or polysomnography.
- Treatment: Weight reduction, CPAP where indicated, BP management.
- Prognosis: Untreated OSA increases risk of resistant hypertension, arrhythmias, stroke, and cardiovascular disease.
5. Primary Aldosteronism
- Etiology: Autonomous aldosterone excess, often from adrenal adenoma or bilateral adrenal hyperplasia.
- Pathophysiology: Aldosterone causes sodium retention, volume expansion, potassium loss, and hypertension.
- Diagnostic tests: Plasma aldosterone concentration, renin, aldosterone-renin ratio, serum potassium, confirmatory testing and adrenal imaging when indicated.
- Treatment: Adrenalectomy for unilateral disease or mineralocorticoid receptor antagonist therapy for bilateral disease.
- Prognosis: Treating the cause can improve BP control and reduce cardiovascular risk.
Tests to Include in Your Initial Workup
- Repeat properly measured BP, ideally home BP/ambulatory BP monitoring
- CBC
- Fasting glucose and HbA1c
- Fasting lipid profile
- Serum creatinine, eGFR, electrolytes, especially potassium
- Urinalysis and urine albumin-to-creatinine ratio
- ECG
- Fundoscopy
- Echocardiogram because of displaced PMI and possible LVH/cardiomegaly
- Chest X-ray if cardiac enlargement or pulmonary congestion suspected
- Consider TSH, aldosterone-renin ratio, renal ultrasound/renal Doppler, and sleep study based on findings