
Hello orris
I’m emergency medicine final year student appearing for exams can you help me
- Explain concepts - pathophysiology, mechanisms, clinical presentations
- Work through cases - clinical scenarios and decision-making
- Review protocols - ACLS, trauma (ATLS), toxicology, sepsis, etc.
- Quiz you - spot questions, MCQs, or SAQs on any topic
- Clarify guidelines - latest management protocols
- High-yield topics - help you focus on what matters most for exams
Okay if I feel difficulty i will ask you
Can you explain all about stemi and latest stemi guidelines
"ST-elevation myocardial infarction" AND "guidelines"
ACC AHA 2025 STEMI guidelines update latest recommendations
https://www.jacc.org/doi/10.1016/j.jacc.2025.01.018
PMID: 40014670
STEMI - Complete Guide for EM Finals
1. Definition & Pathophysiology
- Atherosclerotic plaque vulnerability → rupture/erosion
- Platelet aggregation → thrombus formation
- Complete coronary occlusion
- Myocardial ischemia starts within minutes
- Irreversible necrosis begins at ~20 min (subendocardium first) and progresses toward epicardium ("wavefront" phenomenon)
- After 6 hours: near-complete transmural necrosis of at-risk territory
2. Clinical Presentation
| Feature | Classic | Atypical (watch for these!) |
|---|---|---|
| Chest pain | Crushing, pressure, radiation to arm/jaw | Absent (especially diabetics, elderly, women) |
| Associated | Diaphoresis, nausea, vomiting, dyspnea | Epigastric pain, fatigue, syncope |
| Duration | >20 minutes, not relieved by nitrates | Variable |
3. ECG Diagnosis
| Lead Group | Elevation Threshold | Territory |
|---|---|---|
| 2 contiguous limb leads | ≥1 mm | Inferior (II, III, aVF) or lateral (I, aVL) |
| 2 contiguous precordial leads (V1-V4) | ≥2 mm men, ≥1.5 mm women | Anterior |
| V4R | ≥0.5 mm | Right ventricle |
- Hyperacute T waves (earliest, minutes)
- ST elevation (injury pattern)
- Q wave formation (necrosis, hours)
- T wave inversion
- ST normalization, persistent Q waves
- De Winter pattern - upsloping ST depression + peaked T waves in V1-V6 (LAD occlusion - no classic STE)
- Posterior MI - ST depression V1-V3 + tall R wave (do posterior leads V7-V9)
- Wellens syndrome - biphasic or deeply inverted T waves in V2-V3 (critical LAD stenosis, pre-infarction)
- LBBB (new or presumed new) - treat as STEMI
- Sgarbossa criteria - diagnose MI in LBBB
| Territory | Leads | Artery |
|---|---|---|
| Anterior | V1-V4 | LAD |
| Lateral | I, aVL, V5-V6 | LCx |
| Inferior | II, III, aVF | RCA (80%), LCx (20%) |
| Posterior | V7-V9, STD V1-V3 | RCA/LCx |
| Right ventricle | V4R | RCA |
4. Diagnosis in ED
- 12-lead ECG: acquire and interpret within 10 minutes
- Serial ECGs if initial non-diagnostic
- High-sensitivity troponin (hs-cTn): measure ASAP; repeat at 1-2 hours (rapid rule-in/out) or 3-6 hours (standard protocol)
- CBC, BMP, coagulation, CXR
- Echo at bedside if diagnosis uncertain or to assess wall motion
5. Reperfusion - The Core of STEMI Management
Primary PCI (pPCI) - Preferred Strategy
| Scenario | Target |
|---|---|
| PCI-capable hospital | First medical contact (FMC) to balloon ≤90 minutes |
| Transfer from non-PCI hospital | FMC to balloon ≤120 minutes |
| Fibrinolysis if PCI not achievable | FMC to needle ≤30 minutes |
Note: The concept of "first medical contact to device time" replaces the old "door to balloon" or "door to needle" terminology.
Fibrinolysis - When PCI is Not Available in Time
- Prior intracranial hemorrhage (any time)
- Ischemic stroke within 3 months
- Structural cerebrovascular lesion / intracranial neoplasm
- Active internal bleeding (not menses)
- Suspected aortic dissection
- Significant closed-head/facial trauma within 3 months
- If successful (≥50% ST resolution at 60-90 min) → angiography within 3-24 hours ("pharmacoinvasive strategy")
- If failed reperfusion → rescue PCI immediately
6. Pharmacotherapy
ACS Treatment Flowchart
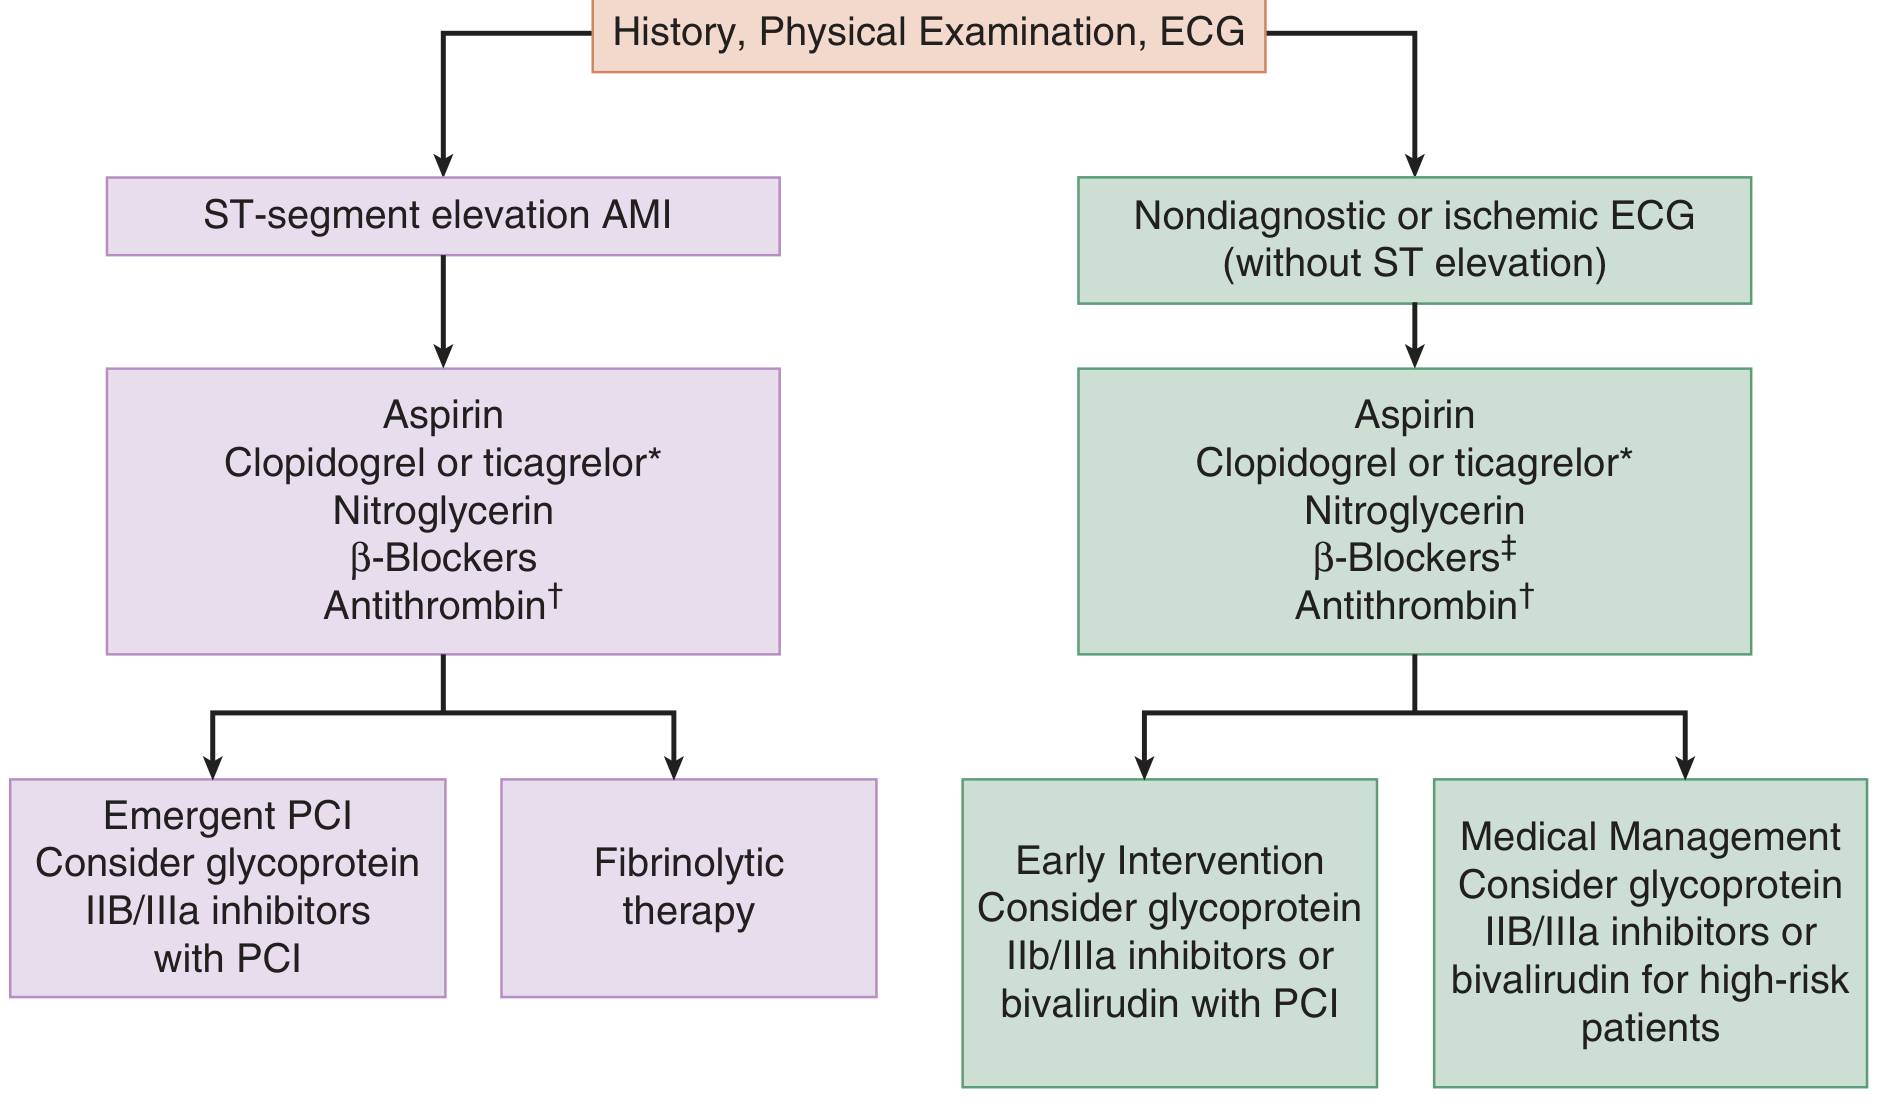
Antiplatelet Therapy (DAPT - mandatory)
| Drug | Dose | Notes |
|---|---|---|
| Aspirin | 162-325 mg loading, then 75-100 mg daily | Give immediately |
| Ticagrelor | 180 mg load, then 90 mg BD | Preferred with pPCI (2025 guidelines) |
| Prasugrel | 60 mg load, then 10 mg daily | Preferred with pPCI; avoid if prior stroke/TIA, age >75, weight <60 kg |
| Clopidogrel | 600 mg load, then 75 mg daily | Use if ticagrelor/prasugrel unavailable; no loading dose if >75 yrs + fibrinolysis |
- DAPT for ≥12 months post-ACS for low bleeding risk
- Transition to ticagrelor monotherapy ≥1 month post-PCI is now Class I to reduce bleeding (new recommendation)
- Shorter DAPT (1-3 months) reasonable in selected high-bleeding-risk patients, then P2Y12 monotherapy
Anticoagulation
| Drug | Setting | Dose |
|---|---|---|
| UFH (unfractionated heparin) | Primary PCI | 70-100 U/kg IV bolus (without GPI); 50-70 U/kg if with GPI |
| Bivalirudin | Primary PCI | Alternative to UFH |
| Enoxaparin | Medical/fibrinolysis | 30 mg IV + 1 mg/kg SC Q12H |
| Fondaparinux | Medical management | 2.5 mg SC daily (avoid as sole anticoagulant for PCI) |
Other Drugs
| Drug | Indication | Notes |
|---|---|---|
| Beta-blockers | All STEMI (oral, within 24h) | Reduce VT/VF, reinfarction; avoid in cardiogenic shock, acute HF, PR >240ms, 2nd/3rd degree block, active asthma |
| ACE inhibitor / ARB | All STEMI, especially EF <40% | Start within 24h; reduces MACE |
| High-intensity statin | All STEMI | Start immediately (Class I, 2025 guidelines) |
| Nitrates | Chest pain relief | Avoid if RV infarction, hypotension, recent PDE5 inhibitor use |
| Morphine | Refractory pain | Use cautiously - may delay P2Y12 absorption |
| Oxygen | O2 sat <90% | Avoid routine O2 if sat ≥90%; may cause harm |
Lipid Lowering (2025 Update)
- High-intensity statin: Class I for all ACS
- Add ezetimibe if LDL not at goal on statin
- For recurrent atherothrombotic events within 2 years on max statin: LDL target <40 mg/dL may be considered (new 2025 recommendation)
7. Multivessel Disease in STEMI (Major 2025 Update!)
| Scenario | Recommendation | Class |
|---|---|---|
| Hemodynamically stable STEMI + MVD | Complete revascularization (infarct + noninfarct arteries) recommended - either at index PCI or within 45 days | Class I |
| Cardiogenic shock + MVD | Routine PCI of noninfarct artery at time of primary PCI should NOT be performed (higher risk of death/renal failure) | Class III (Harm) |
| Low-complexity MVD, hemodynamically stable | Multivessel PCI at time of primary PCI may be preferred over staged approach | Class 2b |
8. Complications of STEMI
Early (first 24-72 hours)
- Arrhythmias: VF (leading cause of early death), VT, AF, complete heart block (inferior MI)
- Right ventricular infarction (inferior STEMI + RV infarct): hypotension, JVD, clear lungs - treat with fluids, avoid nitrates/diuretics
- Cardiogenic shock: SBP <90, low CO, high wedge pressure - treat with pPCI, vasopressors, MCS (IABP/Impella)
Mechanical Complications (days 3-7)
- Free wall rupture - sudden cardiac death, Beck's triad
- Ventricular septal defect (VSD) - new harsh holosystolic murmur, step-up in O2 saturation RA→RV
- Papillary muscle rupture / acute MR - acute pulmonary edema, soft murmur
Subacute
- Dressler syndrome (post-MI pericarditis) - weeks after MI, fever + pericardial rub + pleurisy, treat with aspirin/NSAIDs
- LV thrombus - anticoagulate if detected
- LV aneurysm - persistent ST elevation, paradoxical wall motion
9. Special Situations
- Occurs in 30-50% of inferior STEMIs
- Clinical triad: hypotension + JVD + clear lungs
- Check right-sided leads (V4R is most sensitive)
- Treatment: fluids (preload dependent), avoid nitrates/diuretics, early pPCI
- Early revascularization is the only intervention proven to reduce mortality
- Intra-aortic balloon pump (IABP) - not shown to improve mortality in recent RCTs
- Newer MCS (Impella, ECMO) under study
10. 2025 ACC/AHA ACS Guideline - Key Changes Summary
- DAPT transition: Ticagrelor monotherapy ≥1 month post-PCI is now Class I to reduce bleeding
- Complete revascularization in MVD-STEMI: Class I - do it at index PCI or within 45 days
- Lipid targets: High-intensity statin for all ACS (Class I); LDL <40 mg/dL for recurrent events
- Aspirin dosing: Low-dose aspirin (≤100 mg) preferred for long-term therapy
- Cardiogenic shock + MVD: Staged PCI confirmed - NO routine noninfarct artery PCI at time of primary PCI
- ECG and troponin timing: 10-minute ECG, rapid hs-troponin protocols (0h/1-2h)
Quick Memory Aids for Exams
- Morphine - use cautiously (not routinely)
- Oxygen - only if SpO2 <90%
- Nitrates - avoid in RV infarct/hypotension
- Aspirin - give immediately (Class I)
- ECG: 10 min
- PCI-capable hospital balloon: 90 min
- Transfer + balloon: 120 min
- Fibrinolysis needle: 30 min
- Fibrinolytic bolus from STEMI diagnosis: 10 min
| Class | Signs | Mortality |
|---|---|---|
| I | No HF signs | ~5% |
| II | S3, basal rales | ~10% |
| III | Pulmonary edema | ~20-40% |
| IV | Cardiogenic shock | ~80% |
Can you give it in a pdf
ls /home/daytona/workspace/ 2>/dev/null || echo "workspace empty or not found"
mkdir -p /home/daytona/workspace/stemi-guide && python3 -c "import reportlab; print('reportlab ok')" && python3 -c "import markdown; print('markdown ok')" || echo "checking libs"
~/stemi-guide/generate_stemi_pdf.py
from reportlab.lib.pagesizes import A4
from reportlab.lib.styles import getSampleStyleSheet, ParagraphStyle
from reportlab.lib.units import cm
from reportlab.lib import colors
from reportlab.platypus import (
    SimpleDocTemplate, Paragraph, Spacer, Table, TableStyle,
    HRFlowable, PageBreak
)
from reportlab.lib.enums import TA_LEFT, TA_CENTER, TA_JUSTIFY
from reportlab.platypus import KeepTogether

OUTPUT = "/home/daytona/workspace/stemi-guide/STEMI_EM_Study_Guide.pdf"

doc = SimpleDocTemplate(
    OUTPUT,
    pagesize=A4,
    rightMargin=2*cm, leftMargin=2*cm,
    topMargin=2.5*cm, bottomMargin=2.5*cm,
    title="STEMI – Complete EM Study Guide",
    author="Orris AI"
)

W = A4[0] - 4*cm  # usable width

# ── Colour palette ──────────────────────────────────────────────────────────
RED      = colors.HexColor("#C0392B")
DARKRED  = colors.HexColor("#922B21")
BLUE     = colors.HexColor("#1A5276")
LBLUE    = colors.HexColor("#D6EAF8")
ORANGE   = colors.HexColor("#E67E22")
GREEN    = colors.HexColor("#1E8449")
LGREEN   = colors.HexColor("#D5F5E3")
LGREY    = colors.HexColor("#F2F3F4")
MGREY    = colors.HexColor("#BDC3C7")
WHITE    = colors.white

# ── Styles ───────────────────────────────────────────────────────────────────
base = getSampleStyleSheet()

def S(name, parent="Normal", **kw):
    return ParagraphStyle(name, parent=base[parent], **kw)

Title  = S("Title2",  fontSize=26, textColor=WHITE, leading=32,
           alignment=TA_CENTER, fontName="Helvetica-Bold")
Sub    = S("Sub",     fontSize=12, textColor=WHITE, leading=16,
           alignment=TA_CENTER, fontName="Helvetica")
H1     = S("H1",      fontSize=14, textColor=WHITE, leading=18,
           fontName="Helvetica-Bold", spaceAfter=2)
H2     = S("H2",      fontSize=11, textColor=BLUE, leading=15,
           fontName="Helvetica-Bold", spaceBefore=8, spaceAfter=3)
H3     = S("H3",      fontSize=10, textColor=DARKRED, leading=13,
           fontName="Helvetica-Bold", spaceBefore=4, spaceAfter=2)
Body   = S("Body",    fontSize=9,  leading=13, spaceAfter=3,
           alignment=TA_JUSTIFY)
Bullet = S("Bullet",  fontSize=9,  leading=13, leftIndent=14,
           firstLineIndent=-10, spaceAfter=2)
Small  = S("Small",   fontSize=7.5, textColor=colors.HexColor("#555555"),
           leading=10, alignment=TA_CENTER)
Bold9  = S("Bold9",   fontSize=9,  fontName="Helvetica-Bold", leading=13)
Warn   = S("Warn",    fontSize=9,  textColor=RED, fontName="Helvetica-Bold",
           leading=13)
Note   = S("Note",    fontSize=8.5, textColor=BLUE, leading=12,
           leftIndent=8)

def bullet(txt):
    return Paragraph(f"• {txt}", Bullet)

def h1_block(text, bg=BLUE):
    tbl = Table([[Paragraph(text, H1)]], colWidths=[W])
    tbl.setStyle(TableStyle([
        ("BACKGROUND", (0,0), (-1,-1), bg),
        ("TOPPADDING",    (0,0), (-1,-1), 5),
        ("BOTTOMPADDING", (0,0), (-1,-1), 5),
        ("LEFTPADDING",   (0,0), (-1,-1), 8),
        ("RIGHTPADDING",  (0,0), (-1,-1), 8),
        ("ROUNDEDCORNERS", [4]),
    ]))
    return tbl

def section_table(rows, col_widths, header_bg=BLUE, alt=True):
    """Styled table with coloured header row."""
    style = [
        ("BACKGROUND",    (0,0), (-1,0),  header_bg),
        ("TEXTCOLOR",     (0,0), (-1,0),  WHITE),
        ("FONTNAME",      (0,0), (-1,0),  "Helvetica-Bold"),
        ("FONTSIZE",      (0,0), (-1,-1), 8.5),
        ("LEADING",       (0,0), (-1,-1), 11),
        ("TOPPADDING",    (0,0), (-1,-1), 4),
        ("BOTTOMPADDING", (0,0), (-1,-1), 4),
        ("LEFTPADDING",   (0,0), (-1,-1), 5),
        ("RIGHTPADDING",  (0,0), (-1,-1), 5),
        ("GRID",          (0,0), (-1,-1), 0.4, MGREY),
        ("VALIGN",        (0,0), (-1,-1), "MIDDLE"),
    ]
    if alt:
        for i in range(1, len(rows), 2):
            style.append(("BACKGROUND", (0,i), (-1,i), LGREY))
    tbl = Table(
        [[Paragraph(str(c), Bold9 if r==0 else Body) for c in row]
         for r, row in enumerate(rows)],
        colWidths=col_widths
    )
    tbl.setStyle(TableStyle(style))
    return tbl

def warning_box(text):
    tbl = Table([[Paragraph(f"⚠ {text}", Warn)]], colWidths=[W])
    tbl.setStyle(TableStyle([
        ("BACKGROUND",    (0,0), (-1,-1), colors.HexColor("#FDEDEC")),
        ("LEFTPADDING",   (0,0), (-1,-1), 8),
        ("RIGHTPADDING",  (0,0), (-1,-1), 8),
        ("TOPPADDING",    (0,0), (-1,-1), 5),
        ("BOTTOMPADDING", (0,0), (-1,-1), 5),
        ("BOX",           (0,0), (-1,-1), 1, RED),
    ]))
    return tbl

def info_box(text, bg=LBLUE, tc=BLUE):
    style = S("IB", fontSize=9, textColor=tc, leading=13, leftIndent=4)
    tbl = Table([[Paragraph(text, style)]], colWidths=[W])
    tbl.setStyle(TableStyle([
        ("BACKGROUND",    (0,0), (-1,-1), bg),
        ("LEFTPADDING",   (0,0), (-1,-1), 8),
        ("RIGHTPADDING",  (0,0), (-1,-1), 8),
        ("TOPPADDING",    (0,0), (-1,-1), 5),
        ("BOTTOMPADDING", (0,0), (-1,-1), 5),
        ("BOX",           (0,0), (-1,-1), 0.8, tc),
    ]))
    return tbl

# ════════════════════════════════════════════════════════════════════════════
# CONTENT
# ════════════════════════════════════════════════════════════════════════════
story = []

# ── COVER PAGE ───────────────────────────────────────────────────────────────
cover = Table(
    [[Paragraph("STEMI", Title)],
     [Paragraph("Complete Emergency Medicine Study Guide", Sub)],
     [Spacer(1, 0.3*cm)],
     [Paragraph("Based on 2025 ACC/AHA/ACEP/NAEMSP/SCAI Guidelines", Sub)],
    ],
    colWidths=[W]
)
cover.setStyle(TableStyle([
    ("BACKGROUND",    (0,0), (-1,-1), RED),
    ("TOPPADDING",    (0,0), (-1,-1), 18),
    ("BOTTOMPADDING", (0,0), (-1,-1), 18),
    ("ROUNDEDCORNERS", [6]),
]))
story += [Spacer(1, 1*cm), cover, Spacer(1, 0.5*cm)]

meta = Table([[
    Paragraph("For: Emergency Medicine Final Year Students", Small),
    Paragraph("Date: July 2026", Small),
    Paragraph("Sources: Tintinalli · Braunwald · Fuster & Hurst · PubMed", Small),
]], colWidths=[W/3]*3)
story += [meta, Spacer(1, 0.8*cm), HRFlowable(width=W, color=MGREY), Spacer(1, 0.3*cm)]

# ── 1. DEFINITION & PATHOPHYSIOLOGY ─────────────────────────────────────────
story += [h1_block("1. Definition & Pathophysiology"), Spacer(1, 0.2*cm)]
story.append(Paragraph(
    "STEMI (ST-Elevation Myocardial Infarction) is a full-thickness (transmural) MI caused by "
    "complete and sustained occlusion of a coronary artery, almost always due to atherosclerotic "
    "plaque rupture with superimposed thrombus formation.", Body))
story.append(Paragraph("<b>Pathological sequence:</b>", Bold9))
for b in [
    "Plaque vulnerability → rupture/erosion",
    "Platelet aggregation → thrombus formation → complete occlusion",
    "Myocardial ischemia starts within minutes",
    "Irreversible necrosis begins at ~20 min (subendocardium first) — 'wavefront phenomenon'",
    "Near-complete transmural necrosis after ~6 hours without reperfusion",
]:
    story.append(bullet(b))
story.append(Spacer(1, 0.4*cm))

# ── 2. CLINICAL PRESENTATION ─────────────────────────────────────────────────
story += [h1_block("2. Clinical Presentation"), Spacer(1, 0.2*cm)]
rows = [
    ["Feature", "Classic", "Atypical (watch for!)"],
    ["Chest pain", "Crushing, pressure, radiation to left arm/jaw", "Absent — especially in diabetics, elderly, women"],
    ["Associated", "Diaphoresis, nausea, vomiting, dyspnea", "Epigastric pain, fatigue, syncope"],
    ["Duration", ">20 min, not relieved by nitrates", "Variable"],
]
story.append(section_table(rows, [3*cm, 7.5*cm, 6*cm]))
story.append(Spacer(1, 0.3*cm))
story.append(warning_box("High-risk for atypical presentation: Diabetics · Elderly · Women · Post-transplant patients"))
story.append(Spacer(1, 0.4*cm))

# ── 3. ECG DIAGNOSIS ─────────────────────────────────────────────────────────
story += [h1_block("3. ECG Diagnosis"), Spacer(1, 0.2*cm)]
story.append(Paragraph("<b>STEMI Diagnostic Criteria:</b>", H2))
rows = [
    ["Lead Group", "Elevation Threshold", "Territory"],
    ["2 contiguous limb leads (II,III,aVF or I,aVL)", "≥1 mm", "Inferior or Lateral"],
    ["2 contiguous precordial leads V1-V4", "≥2 mm men / ≥1.5 mm women", "Anterior"],
    ["V4R (right-sided lead)", "≥0.5 mm", "Right Ventricle"],
    ["V7-V9 (posterior leads)", "≥0.5 mm", "Posterior"],
]
story.append(section_table(rows, [6.5*cm, 5*cm, 5*cm]))
story.append(Spacer(1, 0.3*cm))

story.append(Paragraph("<b>ECG Evolution:</b>", H2))
evo = Table([[
    Paragraph("1\nHyperacute\nT waves", Small),
    Paragraph("→", Small),
    Paragraph("2\nST\nElevation", Small),
    Paragraph("→", Small),
    Paragraph("3\nPathological\nQ waves", Small),
    Paragraph("→", Small),
    Paragraph("4\nT wave\nInversion", Small),
    Paragraph("→", Small),
    Paragraph("5\nST normalises\nQ persists", Small),
]], colWidths=[2.5*cm, 0.6*cm, 2.5*cm, 0.6*cm, 2.5*cm, 0.6*cm, 2.5*cm, 0.6*cm, 2.5*cm])
evo.setStyle(TableStyle([
    ("BACKGROUND",    (0,0), (0,0),  colors.HexColor("#FDEDEC")),
    ("BACKGROUND",    (2,0), (2,0),  colors.HexColor("#FDEBD0")),
    ("BACKGROUND",    (4,0), (4,0),  colors.HexColor("#D5F5E3")),
    ("BACKGROUND",    (6,0), (6,0),  colors.HexColor("#D6EAF8")),
    ("BACKGROUND",    (8,0), (8,0),  LGREY),
    ("ALIGN",         (0,0), (-1,-1), "CENTER"),
    ("VALIGN",        (0,0), (-1,-1), "MIDDLE"),
    ("FONTSIZE",      (0,0), (-1,-1), 8),
    ("TOPPADDING",    (0,0), (-1,-1), 6),
    ("BOTTOMPADDING", (0,0), (-1,-1), 6),
    ("BOX",           (0,0), (-1,-1), 0.5, MGREY),
]))
story += [evo, Spacer(1, 0.3*cm)]

story.append(Paragraph("<b>STEMI Equivalents (Critical for EM!):</b>", H2))
rows = [
    ["Pattern", "ECG Finding", "Vessel / Notes"],
    ["De Winter", "Upsloping STD + peaked T waves V1-V6", "LAD occlusion — NO classic STE"],
    ["Posterior MI", "STD V1-V3 + tall R waves", "Do posterior leads V7-V9"],
    ["Wellens Syndrome", "Biphasic or deeply inverted T waves V2-V3", "Critical LAD stenosis — pre-infarction!"],
    ["New LBBB", "New or presumed new left bundle branch block", "Treat as STEMI"],
    ["Sgarbossa criteria", "Concordant STE ≥1 mm; STE ≥5 mm discordant", "Diagnose MI in LBBB"],
]
story.append(section_table(rows, [3.5*cm, 6*cm, 7*cm], header_bg=DARKRED))
story.append(Spacer(1, 0.3*cm))

story.append(Paragraph("<b>Territory Localisation:</b>", H2))
rows = [
    ["Territory", "Leads", "Artery"],
    ["Anterior",  "V1-V4",            "LAD"],
    ["Lateral",   "I, aVL, V5-V6",    "LCx"],
    ["Inferior",  "II, III, aVF",      "RCA (80%), LCx (20%)"],
    ["Posterior", "V7-V9 / STD V1-V3","RCA or LCx"],
    ["Right Ventricle", "V4R",         "RCA proximal"],
]
story.append(section_table(rows, [4*cm, 5*cm, 7.5*cm]))
story.append(Spacer(1, 0.4*cm))

# ── 4. ED DIAGNOSIS ──────────────────────────────────────────────────────────
story += [h1_block("4. Diagnosis in the ED"), Spacer(1, 0.2*cm)]
story.append(info_box(
    "⏱  KEY: 12-lead ECG must be acquired and interpreted within <b>10 minutes</b> of arrival (Class I — 2025 ACC/AHA).",
    bg=LGREEN, tc=GREEN
))
story.append(Spacer(1, 0.2*cm))
for b in [
    "<b>ECG:</b> 12-lead within 10 min; serial ECGs if initial non-diagnostic",
    "<b>hs-Troponin:</b> Measure ASAP — repeat at <b>1-2 hours</b> (rapid protocol) or 3-6 hours (standard)",
    "<b>Labs:</b> CBC, BMP, coagulation, BNP, lipid panel",
    "<b>CXR:</b> Portable — assess for pulmonary oedema, widened mediastinum",
    "<b>Bedside Echo:</b> If diagnosis uncertain — assess wall motion abnormalities, EF, pericardial effusion",
]:
    story.append(bullet(b))
story.append(Spacer(1, 0.4*cm))

# ── 5. REPERFUSION ──────────────────────────────────────────────────────────
story += [h1_block("5. Reperfusion Strategy — The Core of STEMI Management", bg=DARKRED), Spacer(1, 0.2*cm)]
story.append(Paragraph(
    "Timely reperfusion is the most effective method to restore myocardial oxygen supply. "
    "Every 30-minute delay in reperfusion increases mortality. Timely reperfusion has reduced "
    "in-hospital STEMI mortality from ~20% to ~5% over three decades.", Body))
story.append(Spacer(1, 0.2*cm))

story.append(Paragraph("<b>Time Targets (2025 ACC/AHA — Class I):</b>", H2))
rows = [
    ["Scenario", "Target", "Note"],
    ["PCI-capable hospital", "FMC → Balloon ≤ 90 min", "First medical contact to device"],
    ["Transfer from non-PCI hospital", "FMC → Balloon ≤ 120 min", "Accounts for transfer time"],
    ["Fibrinolysis (if PCI unavailable)", "FMC → Needle ≤ 30 min", "If PCI can't meet 120 min target"],
    ["Fibrinolytic bolus from diagnosis", "STEMI Dx → Bolus ≤ 10 min", "Prehospital lysis if feasible"],
]
story.append(section_table(rows, [5*cm, 5*cm, 6.5*cm], header_bg=DARKRED))
story.append(Spacer(1, 0.2*cm))
story.append(info_box(
    'ℹ "First Medical Contact to Device Time" replaces the old "door to balloon" / "door to needle" terminology.',
    bg=LBLUE, tc=BLUE
))
story.append(Spacer(1, 0.3*cm))

story.append(Paragraph("<b>Primary PCI vs Fibrinolysis:</b>", H2))
story.append(Paragraph(
    "In a large meta-analysis of 23 RCTs, pPCI was superior to thrombolytics at reducing "
    "death, reinfarction, and stroke. pPCI is always preferred when achievable within time targets.", Body))

story.append(Paragraph("<b>Absolute Contraindications to Fibrinolysis:</b>", H3))
for b in [
    "Prior intracranial haemorrhage (any time)",
    "Ischaemic stroke within 3 months",
    "Structural cerebrovascular lesion or intracranial neoplasm",
    "Active internal bleeding (not menses)",
    "Suspected aortic dissection",
    "Significant closed-head or facial trauma within 3 months",
]:
    story.append(bullet(b))

story.append(Paragraph("<b>Post-Fibrinolysis Strategy:</b>", H3))
for b in [
    "Successful lysis (≥50% ST resolution at 60-90 min) → Angiography within 3-24 hours (pharmacoinvasive strategy)",
    "Failed reperfusion → Rescue PCI IMMEDIATELY",
]:
    story.append(bullet(b))
story.append(Spacer(1, 0.4*cm))

# ── 6. PHARMACOTHERAPY ──────────────────────────────────────────────────────
story += [h1_block("6. Pharmacotherapy"), Spacer(1, 0.2*cm)]

story.append(Paragraph("<b>Antiplatelet Therapy (DAPT — Give Immediately):</b>", H2))
rows = [
    ["Drug", "Loading Dose", "Maintenance", "Notes"],
    ["Aspirin", "162-325 mg", "75-100 mg daily", "Give immediately to all"],
    ["Ticagrelor", "180 mg PO", "90 mg BD", "Preferred with pPCI (2025 Class I)"],
    ["Prasugrel", "60 mg PO", "10 mg daily", "Preferred with pPCI; AVOID if prior stroke/TIA, age >75, wt <60 kg"],
    ["Clopidogrel", "600 mg PO", "75 mg daily", "If ticagrelor/prasugrel unavailable; no load >75 yrs + fibrinolysis"],
]
story.append(section_table(rows, [2.8*cm, 2.8*cm, 3.5*cm, 7.4*cm], header_bg=GREEN))
story.append(Spacer(1, 0.2*cm))

story.append(info_box(
    "⭐ 2025 NEW (Class I): Transition to ticagrelor monotherapy ≥1 month post-PCI reduces bleeding risk. "
    "DAPT ≥12 months for low bleeding risk; shorter (1-3 months) for high bleeding risk.", bg=LGREEN, tc=GREEN))
story.append(Spacer(1, 0.3*cm))

story.append(Paragraph("<b>Anticoagulation:</b>", H2))
rows = [
    ["Drug", "Setting", "Dose"],
    ["UFH (Unfractionated Heparin)", "Primary PCI", "70-100 U/kg IV bolus (without GPI); 50-70 U/kg with GPI"],
    ["Bivalirudin", "Primary PCI", "Alternative to UFH; lower bleeding risk"],
    ["Enoxaparin", "Fibrinolysis/Medical", "30 mg IV + 1 mg/kg SC Q12H"],
    ["Fondaparinux", "Medical management", "2.5 mg SC daily — AVOID as sole agent for PCI"],
]
story.append(section_table(rows, [4*cm, 3.5*cm, 9*cm], header_bg=GREEN))
story.append(Spacer(1, 0.3*cm))

story.append(Paragraph("<b>Other Essential Drugs:</b>", H2))
rows = [
    ["Drug", "Indication", "Key Notes / Contraindications"],
    ["Beta-blockers (oral)", "All STEMI — within 24h", "Reduce VT/VF; AVOID in cardiogenic shock, acute HF, PR >240ms, 2°/3° block, active asthma"],
    ["ACE inhibitor / ARB", "All STEMI, esp. EF <40%", "Start within 24h; reduces MACE"],
    ["High-intensity statin", "All STEMI (Class I — 2025)", "Start immediately; goal LDL <70 mg/dL (or <40 if recurrent event)"],
    ["Nitrates", "Chest pain relief", "AVOID in RV infarction, hypotension (SBP <90), recent PDE5 inhibitor use"],
    ["Morphine", "Refractory pain only", "Use cautiously — may delay P2Y12 absorption"],
    ["Oxygen", "SpO2 <90% only", "Do NOT give routinely if SpO2 ≥90% — may cause harm"],
]
story.append(section_table(rows, [3.5*cm, 4*cm, 9*cm], header_bg=GREEN))
story.append(Spacer(1, 0.4*cm))

# ── 7. MULTIVESSEL DISEASE ───────────────────────────────────────────────────
story += [h1_block("7. Multivessel Disease in STEMI (2025 Major Update!)", bg=ORANGE), Spacer(1, 0.2*cm)]
story.append(Paragraph(
    "Approximately 50% of STEMI patients have multivessel disease (MVD). Management of noninfarct "
    "arteries is now well-defined by the 2025 guidelines.", Body))
rows = [
    ["Scenario", "Recommendation", "Class"],
    ["Haemodynamically STABLE STEMI + MVD",
     "Complete revascularisation recommended — at index PCI or within 45 days",
     "Class I"],
    ["Stable STEMI + low-complexity MVD",
     "Multivessel PCI at time of primary PCI may be preferred over staged approach",
     "Class 2b"],
    ["Cardiogenic SHOCK + MVD",
     "Routine PCI of noninfarct artery at time of primary PCI SHOULD NOT be performed — higher risk of death/renal failure",
     "Class III (HARM)"],
]
story.append(section_table(rows, [5.5*cm, 8.5*cm, 2.5*cm], header_bg=ORANGE))
story.append(Spacer(1, 0.4*cm))

# ── 8. COMPLICATIONS ────────────────────────────────────────────────────────
story += [h1_block("8. Complications of STEMI"), Spacer(1, 0.2*cm)]

story.append(Paragraph("<b>Early Complications (0-72 hours):</b>", H2))
rows = [
    ["Complication", "Key Features", "Management"],
    ["Ventricular Fibrillation (VF)", "Leading cause of early death", "Defibrillation, ACLS"],
    ["Complete Heart Block (inferior MI)", "Bradycardia, hypotension, wide QRS escape", "Atropine, temporary pacing"],
    ["RV Infarction", "Hypotension + JVD + clear lungs — 30-50% of inferior STEMIs", "IV fluids, avoid nitrates/diuretics, early pPCI"],
    ["Cardiogenic Shock", "SBP <90, cold/clammy, oliguria, low CO", "Primary PCI, vasopressors (noradrenaline), MCS"],
]
story.append(section_table(rows, [4.5*cm, 6*cm, 6*cm]))
story.append(Spacer(1, 0.2*cm))

story.append(Paragraph("<b>Mechanical Complications (Days 3-7 — free wall weakest):</b>", H2))
rows = [
    ["Complication", "Clinical Features", "Management"],
    ["Free Wall Rupture", "Sudden cardiac death; Beck's triad (tamponade)", "Emergency surgery / pericardiocentesis"],
    ["VSD (Ventricular Septal Defect)", "New harsh holosystolic murmur; step-up O2 sat RA→RV", "Emergency surgical repair; MCS bridge"],
    ["Papillary Muscle Rupture / Acute MR", "Acute pulmonary oedema; soft or no murmur", "Emergency MV surgery; IABP bridge"],
]
story.append(section_table(rows, [4.5*cm, 5.5*cm, 6.5*cm]))
story.append(Spacer(1, 0.2*cm))

story.append(Paragraph("<b>Subacute / Late Complications:</b>", H2))
rows = [
    ["Complication", "Timing", "Features & Treatment"],
    ["Dressler Syndrome (Post-MI Pericarditis)", "Weeks after MI", "Fever + pericardial rub + pleurisy; treat with aspirin/NSAIDs/colchicine"],
    ["LV Thrombus", "Days to weeks", "Echo diagnosis; anticoagulate with warfarin or NOAC x 3 months"],
    ["LV Aneurysm", "Weeks to months", "Persistent ST elevation; paradoxical wall motion; anticoagulate if thrombus"],
]
story.append(section_table(rows, [5*cm, 2.5*cm, 9*cm]))
story.append(Spacer(1, 0.4*cm))

# ── 9. KILLIP CLASSIFICATION ────────────────────────────────────────────────
story += [h1_block("9. Killip Classification"), Spacer(1, 0.2*cm)]
rows = [
    ["Class", "Signs", "In-Hospital Mortality"],
    ["I",   "No heart failure signs",          "~5%"],
    ["II",  "S3 gallop, basal rales <50% lung fields", "~10%"],
    ["III", "Pulmonary oedema (rales >50%)",    "~20-40%"],
    ["IV",  "Cardiogenic shock",                "~80%"],
]
story.append(section_table(rows, [2*cm, 9.5*cm, 5*cm]))
story.append(Spacer(1, 0.4*cm))

# ── 10. 2025 GUIDELINE KEY CHANGES ──────────────────────────────────────────
story += [h1_block("10. 2025 ACC/AHA ACS Guideline — Key Changes", bg=DARKRED), Spacer(1, 0.2*cm)]
story.append(Paragraph(
    "Published February 27, 2025 in Circulation (PMID: 40014670) and JACC. This landmark unified "
    "guideline replaces the 2013 STEMI, 2014 NSTEMI, 2015 PCI, and 2016 DAPT guidelines.", Body))
story.append(Spacer(1, 0.2*cm))
changes = [
    ("1. DAPT Transition (NEW — Class I)",
     "Ticagrelor monotherapy ≥1 month post-PCI is now Class I to reduce bleeding. DAPT ≥12 months for low bleeding risk."),
    ("2. Complete Revascularisation in MVD-STEMI (Class I)",
     "For haemodynamically stable STEMI + MVD: complete revascularisation at index PCI or within 45 days."),
    ("3. Cardiogenic Shock + MVD (Class III Harm)",
     "Do NOT routinely PCI the noninfarct artery at the time of primary PCI — increases death/renal failure."),
    ("4. Lipid Targets Updated",
     "High-intensity statin for all ACS (Class I). For recurrent events within 2 years on max statin: LDL target <40 mg/dL."),
    ("5. Aspirin Dosing",
     "Low-dose aspirin (≤100 mg/day) preferred for long-term maintenance therapy."),
    ("6. ECG + Troponin Protocols",
     "ECG within 10 minutes (Class I). Rapid hs-troponin protocols: 0h/1-2h or 0h/3-6h."),
]
for title, body in changes:
    story.append(Paragraph(f"<b>{title}</b>", H3))
    story.append(Paragraph(body, Body))
story.append(Spacer(1, 0.4*cm))

# ── 11. QUICK MEMORY AIDS ────────────────────────────────────────────────────
story += [h1_block("11. Quick Memory Aids for Exams"), Spacer(1, 0.2*cm)]

story.append(Paragraph("<b>Time Targets (Memorise These!):</b>", H2))
times = Table([
    [Paragraph("ECG", Bold9), Paragraph("10 min", Bold9)],
    [Paragraph("pPCI (PCI hospital)", Body), Paragraph("FMC → Balloon ≤ 90 min", Body)],
    [Paragraph("pPCI (transfer)", Body), Paragraph("FMC → Balloon ≤ 120 min", Body)],
    [Paragraph("Fibrinolysis", Body), Paragraph("FMC → Needle ≤ 30 min", Body)],
    [Paragraph("Lytic bolus from Dx", Body), Paragraph("STEMI Dx → Bolus ≤ 10 min", Body)],
], colWidths=[8*cm, 8.5*cm])
times.setStyle(TableStyle([
    ("BACKGROUND",    (0,0), (-1,0),  RED),
    ("TEXTCOLOR",     (0,0), (-1,0),  WHITE),
    ("BACKGROUND",    (0,1), (-1,1),  colors.HexColor("#FDEDEC")),
    ("BACKGROUND",    (0,2), (-1,2),  colors.HexColor("#FDEBD0")),
    ("BACKGROUND",    (0,3), (-1,3),  colors.HexColor("#FDFEFE")),
    ("BACKGROUND",    (0,4), (-1,4),  LGREY),
    ("GRID",          (0,0), (-1,-1), 0.5, MGREY),
    ("TOPPADDING",    (0,0), (-1,-1), 5),
    ("BOTTOMPADDING", (0,0), (-1,-1), 5),
    ("LEFTPADDING",   (0,0), (-1,-1), 8),
    ("FONTSIZE",      (0,0), (-1,-1), 9),
]))
story += [times, Spacer(1, 0.3*cm)]

story.append(Paragraph("<b>MONA — Updated for 2025:</b>", H2))
mona_data = [
    ["M", "Morphine", "Use CAUTIOUSLY — not routinely (delays P2Y12 absorption)"],
    ["O", "Oxygen", "Only if SpO2 <90% — AVOID routine O2 if ≥90%"],
    ["N", "Nitrates", "AVOID in RV infarction, hypotension, PDE5i use"],
    ["A", "Aspirin", "Give IMMEDIATELY — Class I, 162-325 mg load"],
]
mona = Table(
    [[Paragraph(f"<b>{r[0]}</b>", S("MC", fontSize=18, textColor=WHITE, fontName="Helvetica-Bold", alignment=TA_CENTER)),
      Paragraph(f"<b>{r[1]}</b>", S("MD", fontSize=10, textColor=DARKRED, fontName="Helvetica-Bold")),
      Paragraph(r[2], Body)] for r in mona_data],
    colWidths=[1.2*cm, 3*cm, 12.3*cm]
)
mona.setStyle(TableStyle([
    ("BACKGROUND",    (0,0), (0,-1), DARKRED),
    ("BACKGROUND",    (1,0), (-1,-1), LGREY),
    ("GRID",          (0,0), (-1,-1), 0.5, MGREY),
    ("VALIGN",        (0,0), (-1,-1), "MIDDLE"),
    ("TOPPADDING",    (0,0), (-1,-1), 6),
    ("BOTTOMPADDING", (0,0), (-1,-1), 6),
    ("LEFTPADDING",   (0,0), (-1,-1), 6),
]))
story += [mona, Spacer(1, 0.4*cm)]

story.append(Paragraph("<b>RV Infarction — Triad to Remember:</b>", H2))
story.append(info_box(
    "Hypotension  +  Elevated JVP  +  Clear Lungs (no pulmonary oedema)\n"
    "→ Occurs in 30-50% of inferior STEMIs  |  Check V4R lead  |  Give IV FLUIDS — AVOID nitrates/diuretics",
    bg=colors.HexColor("#FEF9E7"), tc=ORANGE
))
story.append(Spacer(1, 0.4*cm))

# ── REFERENCES ───────────────────────────────────────────────────────────────
story += [HRFlowable(width=W, color=MGREY), Spacer(1, 0.2*cm)]
story.append(Paragraph("<b>References</b>", H2))
refs = [
    "Tintinalli JE et al. Tintinalli's Emergency Medicine: A Comprehensive Study Guide, 9th Ed. McGraw-Hill.",
    "Fuster V et al. Fuster and Hurst's The Heart, 15th Edition. McGraw-Hill.",
    "Braunwald E et al. Braunwald's Heart Disease: A Textbook of Cardiovascular Medicine, 12th Ed. Elsevier.",
    "Rao SV et al. 2025 ACC/AHA/ACEP/NAEMSP/SCAI Guideline for the Management of Patients With Acute Coronary Syndromes. Circulation. 2025. PMID: 40014670",
    "Faro DC et al. Complete PCI Revascularization in ACS With MVD: Systematic Review. JACC Cardiovasc Interv. 2023. PMID: 37821180",
]
for r in refs:
    story.append(bullet(r))

story.append(Spacer(1, 0.3*cm))
story.append(Paragraph(
    "Generated by Orris AI · July 2026 · For educational use only — always verify clinical decisions against current guidelines.",
    Small
))

# ── BUILD ─────────────────────────────────────────────────────────────────────
doc.build(story)
print(f"PDF saved: {OUTPUT}")
cd /home/daytona/workspace/stemi-guide && python3 generate_stemi_pdf.py
ls -lh /home/daytona/workspace/stemi-guide/STEMI_EM_Study_Guide.pdf
STEMI EM Study Guide
PDF Document · PDF
- Definition & Pathophysiology
- Clinical Presentation (classic vs atypical)
- ECG Diagnosis - criteria, evolution, STEMI equivalents, territory localisation
- ED Diagnosis workflow
- Reperfusion strategy with time targets
- Full pharmacotherapy tables (antiplatelets, anticoagulation, other drugs)
- Multivessel disease - 2025 guideline updates
- Complications (early, mechanical, subacute)
- Killip Classification
- 2025 ACC/AHA key guideline changes
- Quick memory aids (MONA updated, time targets, RV infarction triad)
Ur great
Hey hii
Hypertensive emergency any recent updates and treatment in ed
"hypertensive emergency" AND management
hypertensive emergency 2024 2025 guidelines treatment ED updates
https://www.ahajournals.org/doi/10.1161/CIR.0000000000001356
https://home.hippoed.com/blog/asymptomatic-hypertension-ed-m…
Hypertensive Emergency - Complete EM Guide + Latest Updates
1. Definitions (Updated 2025 Terminology!)
| Term | Definition | Key Point |
|---|---|---|
| Hypertensive Emergency | Severe BP elevation (SBP ≥180 or DBP ≥120 mmHg) WITH acute target organ damage (TOD) | Requires IV therapy + admission |
| Severe Hypertension without TOD | Severe BP elevation WITHOUT acute TOD | ⚠️ "Hypertensive urgency" is now retired (2025 AHA/ACC) |
| Asymptomatic Hypertension | Elevated BP without symptoms or TOD | ACEP 2025: Consider starting oral therapy at discharge |
Exam tip: The term "hypertensive urgency" has been officially retired in the 2025 AHA/ACC Hypertension Guidelines and replaced with "severe hypertension without acute target-organ damage." This is a major terminology shift - expect it in MCQs!
2. Pathophysiology
- Abrupt rise in BP overwhelms vascular autoregulation
- Endothelial injury → fibrinoid necrosis of arterioles → ischemia
- Brain: failure of cerebral autoregulation → vasogenic oedema (PRES/hypertensive encephalopathy)
- Kidney: afferent arteriole injury → activation of RAAS → further BP rise (vicious cycle)
- Heart: increased afterload → LV strain → acute HF/ACS
3. Target Organ Systems Involved
| Organ System | Conditions | Approximate Incidence |
|---|---|---|
| Brain | Hypertensive encephalopathy, ischaemic stroke, intracranial haemorrhage | 37-45% |
| Heart | Acute HF/pulmonary oedema, ACS | 27-49% |
| Kidney | Acute kidney injury | 8-15% |
| Vascular | Aortic dissection | 1-2% |
| Other | Eclampsia, hypertensive retinopathy | 2-3% |
Critical point: Headache, dizziness, and epistaxis alone do NOT constitute a hypertensive emergency and do NOT mandate acute BP reduction. - Rosen's Emergency Medicine
4. ED Assessment
- History: onset, symptoms (chest pain, SOB, headache, vision changes, focal neuro deficits, oliguria)
- Physical exam: fundoscopy (papilloedema, haemorrhages), neuro exam, JVP, lung auscultation
- Bilateral arm BP measurements
- ECG (LVH, ischaemia, arrhythmia)
- CXR (pulmonary oedema, widened mediastinum)
- Urinalysis + urine microscopy (haematuria, casts)
- Serum creatinine, BUN, electrolytes
- Troponin if chest pain
- CBC, peripheral smear (MAHA - microangiopathic haemolytic anaemia)
- CT head (if altered mentation, focal deficits)
- CT chest/angio (if aortic dissection suspected)
- Urine pregnancy test (all women of reproductive age)
5. BP Reduction Targets (Critical for Exams!)
| Phase | Target | Timeframe |
|---|---|---|
| First hour | Reduce MAP by no more than 25% | Over 1 hour |
| Next 2-6 hours | Target BP ~160/100 mmHg | Gradual |
| Next 24-48 hours | Slow further reduction toward normal | Avoid overcorrection |
Why not lower faster? Overly rapid BP reduction can precipitate ischaemia in organs adapted to high pressure (especially brain, kidneys). The autoregulation curve has shifted rightward in chronic hypertensives.
| Condition | Target | Agent |
|---|---|---|
| Aortic dissection | SBP <120 mmHg in 20 min | Esmolol + nitroprusside/nicardipine |
| Ischaemic stroke (eligible for thrombolysis) | <185/110 before tPA | Labetalol or nicardipine |
| Ischaemic stroke (NOT for thrombolysis) | Only treat if BP >220/120 | Labetalol |
| Hypertensive encephalopathy/PRES | 25% MAP reduction over 1h | Nicardipine, labetalol |
| Eclampsia/pre-eclampsia | <160/110 | Hydralazine, labetalol, nifedipine |
| Acute pulmonary oedema | Aggressive reduction | GTN/nitroglycerin, clevidipine |
6. IV Drugs for Hypertensive Emergency
First-Line Agents
| Drug | Dose | Onset | Duration | Best For | Avoid |
|---|---|---|---|---|---|
| Labetalol | 20 mg IV bolus Q10min (max 300 mg); or 2 mg/min infusion | 5-10 min | 3-6 hrs | Most emergencies, aortic dissection, pregnancy | Asthma, acute HF, bradycardia |
| Nicardipine | 5 mg/hr IV, titrate by 2.5 mg/hr Q5-15 min; max 15 mg/hr | 5-15 min | 30-40 min | Stroke, encephalopathy, eclampsia | Acute HF |
| Clevidipine | 1-2 mg/hr, double Q90 sec; max 32 mg/hr | 2-4 min | 5-15 min | Peri-operative, acute HF | Soya/egg allergy, severe aortic stenosis |
| Sodium nitroprusside | 0.3-0.5 mcg/kg/min, titrate | Seconds | 1-2 min | Most emergencies (versatile) | Increased ICP, renal failure (prolonged use - cyanide toxicity), pregnancy |
| Nitroglycerin (GTN) | 5-100 mcg/min IV infusion | 2-5 min | 3-5 min | Acute pulmonary oedema, ACS | Hypotension, RV infarction, PDE5i |
| Esmolol | 250-500 mcg/kg bolus then 50-100 mcg/kg/min | 1-2 min | 10-20 min | Aortic dissection, tachycardia + HT | Asthma, acute HF |
| Hydralazine | 10-20 mg IV Q20-30 min | 10-30 min | 2-4 hrs | Eclampsia/pre-eclampsia | Aortic dissection (reflex tachycardia), coronary disease |
| Fenoldopam | 0.1-0.3 mcg/kg/min | 5-15 min | 30-60 min | Renal impairment (preserves renal blood flow) | Glaucoma |
| Phentolamine | 5-15 mg IV Q5 min | 1-2 min | 10-30 min | Phaeochromocytoma, cocaine/sympathomimetic | CAD |
Drug Selection by Clinical Scenario
| Scenario | Drug of Choice | Avoid |
|---|---|---|
| Hypertensive encephalopathy / PRES | Nicardipine, labetalol | Nitroprusside (ICP) |
| Aortic dissection | Esmolol + vasodilator (nitroprusside/nicardipine) | Hydralazine, dihydralazine |
| Acute LV failure / pulmonary oedema | Nitroglycerin, clevidipine, loop diuretics | Labetalol, beta-blockers |
| ACS + hypertensive emergency | Nitroglycerin, beta-blocker | Hydralazine |
| Ischaemic stroke (tPA eligible) | Labetalol or nicardipine | Nitroprusside |
| Intracerebral haemorrhage | Nicardipine, labetalol | Nitroprusside |
| Eclampsia / pre-eclampsia | Hydralazine, labetalol, nifedipine | ACE inhibitors, nitroprusside |
| Phaeochromocytoma / cocaine | Phentolamine, benzodiazepines | Beta-blockers alone (unopposed alpha) |
| Acute kidney injury | Fenoldopam, nicardipine | NSAIDs |
| Sympathomimetic crisis (cocaine) | Benzodiazepines ± phentolamine | Beta-blockers alone |
Classic trap: In cocaine-induced hypertensive emergency, never give beta-blockers alone - this causes unopposed alpha-adrenergic stimulation and worsens hypertension and coronary spasm.
7. Condition-Specific Management
Hypertensive Encephalopathy / PRES
- Altered consciousness, severe headache, visual disturbance, seizures
- MRI: T2/FLAIR hyperintensity - posterior white matter (occipital, parietal)
- Treatment: IV nicardipine or labetalol; reduce MAP 25% over 1 hour
- Usually reversible with BP control
Aortic Dissection
- Most time-critical hypertensive emergency
- Target SBP <120 mmHg and HR <60 within 20 minutes
- Two-drug strategy: IV beta-blocker FIRST (esmolol/labetalol), then vasodilator (nitroprusside/nicardipine)
- Never give vasodilator alone - causes reflex tachycardia and worsens shear force
Intracerebral Haemorrhage (ICH)
- Target SBP <140 mmHg (safe and reduces haematoma expansion per ATACH-2/INTERACT2 trials)
- Agent: IV nicardipine preferred for smooth BP control
Ischaemic Stroke
- If tPA eligible: reduce BP to <185/110 mmHg before giving tPA; maintain <180/105 for 24h after
- If NOT for thrombolysis: permissive hypertension (only treat if BP >220/120 mmHg)
- "Let it be" - abrupt reduction worsens penumbral ischaemia
Eclampsia
- Deliver the baby - definitive treatment
- IV labetalol (20 mg bolus), hydralazine (5-10 mg IV), or oral nifedipine
- IV magnesium sulphate for seizure prevention/treatment (NOT an antihypertensive)
- Target BP <160/110 mmHg
8. Latest 2025 Updates - High Yield for Exams
2025 AHA/ACC Hypertension Guidelines (Published 2025)
- "Hypertensive urgency" is RETIRED - now called "severe hypertension without acute target-organ damage"
- IV nicardipine > labetalol for short-term BP target achievement (RCT evidence)
- Clevidipine > nicardipine for speed of BP reduction
- Drug selection should be based on pharmacology, mechanism, degree of TOD, and comorbidities
- Asymptomatic inpatient hypertension: Exercise extreme caution - 40-50% of cases normalise spontaneously; IV as-needed antihypertensives associated with increased in-hospital mortality, AKI, and prolonged stay
ACEP July 2025 Clinical Policy - Asymptomatic Hypertension in ED
- Replaces the 2013 ACEP guideline
- New recommendation: Consider initiating oral antihypertensive therapy at ED discharge for select patients with asymptomatic elevated BP
- Evidence: Initiating therapy leads to mean 11 mmHg reduction at follow-up without increased adverse events
- Mandatory: Refer ALL patients for outpatient follow-up
- Not a universal mandate - use clinical judgement
2024 ESC Hypertension Guidelines
- New simplified BP classification
- Lower treatment targets
- Risk-driven management approach
- Emphasis on better detection strategies
9. Special Situations
- Fenoldopam preferred (renal protective - increases renal blood flow)
- Avoid nitroprusside (cyanide/thiocyanate accumulation)
- Benzodiazepines are first-line (decrease sympathetic drive)
- Phentolamine for alpha blockade
- Beta-blockers CONTRAINDICATED alone - unopposed alpha stimulation
- Safe agents: Hydralazine, labetalol, nifedipine, methyldopa
- AVOID: ACE inhibitors, ARBs, nitroprusside, direct renin inhibitors
10. Quick Memory Aid
- A - Aorta (dissection? CT chest)
- B - Brain (encephalopathy, stroke? CT head)
- C - Cardiac (HF, ACS? ECG, troponin, CXR)
- D - Drugs/toxins (cocaine, amphetamines, phaeo?)
- E - Eclampsia (pregnancy test)
- Reduce MAP by ≤25% in first hour
- Target ~160/100 by 6 hours
- Normal over 24-48 hours (except dissection/eclampsia - faster!)
Pathophysiology in flowchar manner
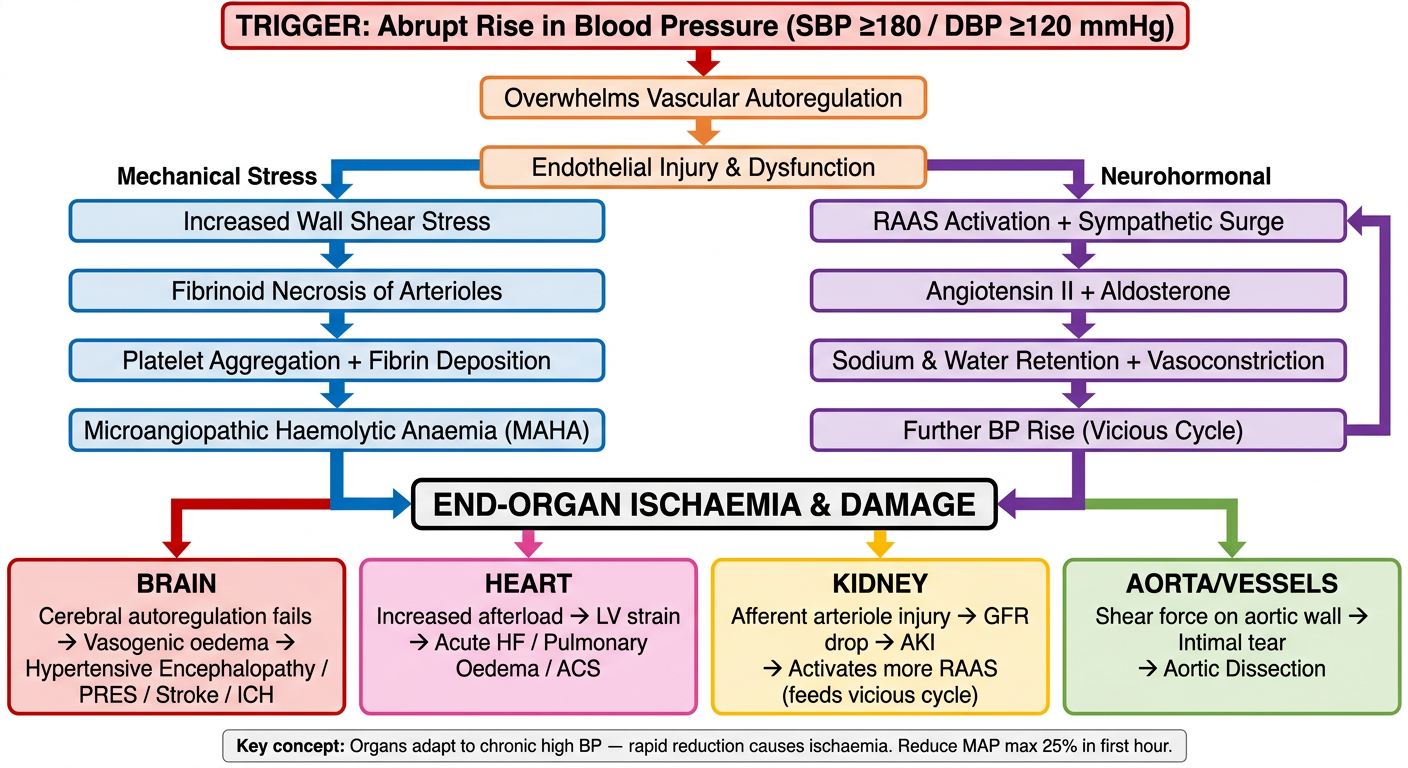
A detailed medical pathophysiology flowchart of hypertensive emergency for medical students. Clean white background, professional medical style with colored boxes and arrows. The flowchart should show: TOP: "TRIGGER: Abrupt Rise in Blood Pressure (SBP ≥180 / DBP ≥120 mmHg)" in a red box Arrow down to: "Overwhelms Vascular Autoregulation" in orange box Arrow down to: "Endothelial Injury & Dysfunction" in orange box Then splits into TWO parallel branches: LEFT BRANCH (Blue - Mechanical Stress): - "Increased Wall Shear Stress" - Arrow down: "Fibrinoid Necrosis of Arterioles" - Arrow down: "Platelet Aggregation + Fibrin Deposition" - Arrow down: "Microangiopathic Haemolytic Anaemia (MAHA)" RIGHT BRANCH (Purple - Neurohormonal): - "RAAS Activation + Sympathetic Surge" - Arrow down: "Angiotensin II + Aldosterone" - Arrow down: "Sodium & Water Retention + Vasoconstriction" - Arrow down: "Further BP Rise (Vicious Cycle)" with a curved arrow looping back up Both branches converge to a central box: "END-ORGAN ISCHAEMIA & DAMAGE" Then splits into FOUR organ-specific outcome boxes at bottom: 1. BRAIN (red): "Cerebral autoregulation fails → Vasogenic oedema → Hypertensive Encephalopathy / PRES / Stroke / ICH" 2. HEART (pink): "Increased afterload → LV strain → Acute HF / Pulmonary Oedema / ACS" 3. KIDNEY (yellow): "Afferent arteriole injury → GFR drop → AKI → Activates more RAAS (feeds vicious cycle)" 4. AORTA/VESSELS (green): "Shear force on aortic wall → Intimal tear → Aortic Dissection" Use color-coded boxes, bold labels, clear directional arrows, and include a small note at bottom: "Key concept: Organs adapt to chronic high BP — rapid reduction causes ischaemia. Reduce MAP max 25% in first hour."
-
Mechanical pathway - High pressure physically damages arteriolar walls → fibrinoid necrosis → MAHA (look for schistocytes on blood smear!)
-
Neurohormonal pathway - Endothelial injury activates RAAS → more angiotensin II → more vasoconstriction → BP rises further → the vicious cycle that makes hypertensive emergencies self-perpetuating
- Brain - Autoregulation fails, cerebral oedema → encephalopathy/PRES
- Heart - Sudden afterload increase → LV can't cope → acute HF or ACS
- Kidney - Arteriole necrosis → AKI → activates even MORE RAAS (feeds the cycle)
- Aorta - Shear stress tears the intima → dissection (most time-critical!)