No worries at all! Here are your complete notes:
🫅 THE TONGUE - Complete Study Notes
(Snell's Clinical Anatomy | Prof's Exam Pattern)
PART 1: QUICK ORIENTATION (Read this first!)
Think of the tongue as a muscular carpet on the floor of the mouth. It has:
- A TOP (dorsum) - you can see it
- A BOTTOM (ventral/inferior surface) - with veins visible
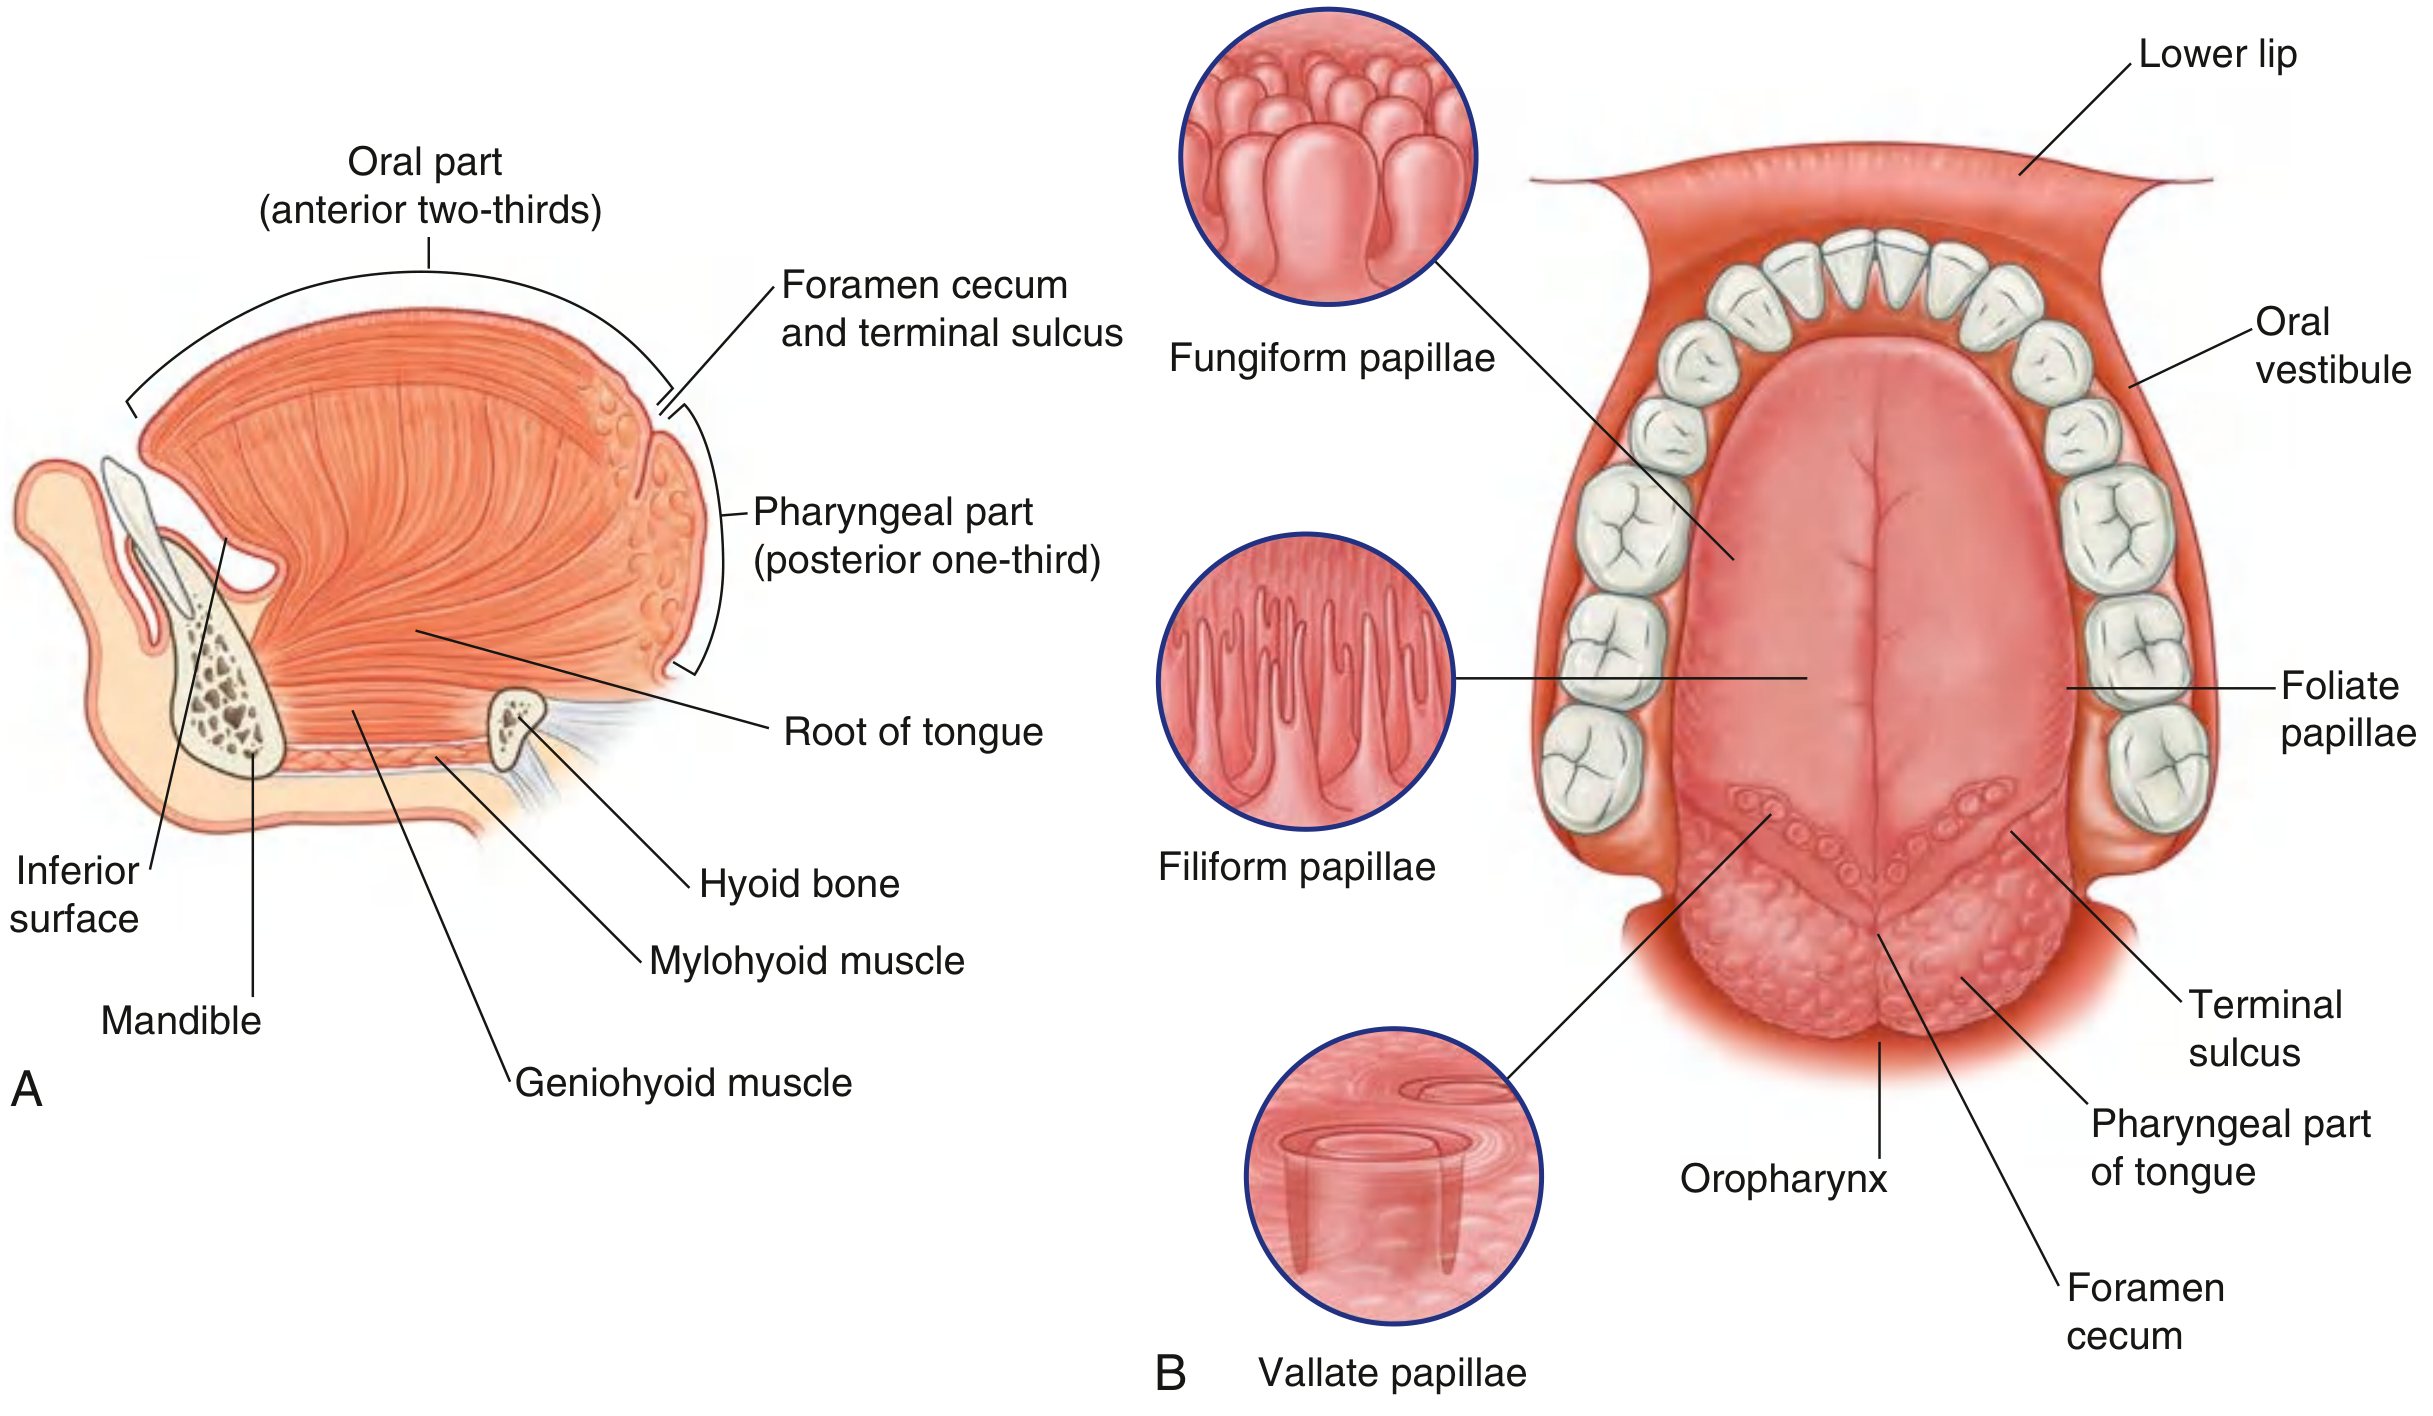
- A FRONT 2/3 (oral part) - in the mouth
- A BACK 1/3 (pharyngeal part) - in the throat
- A ROOT - attached to mandible + hyoid
PART 2: BASIC ANATOMY
The Two Parts - THE MOST IMPORTANT DIVISION
| Feature | Anterior 2/3 (Oral Part) | Posterior 1/3 (Pharyngeal Part) |
|---|
| Location | In oral cavity | In oropharynx |
| Surface | Horizontal plane | Vertical plane |
| Separated by | Terminal sulcus (V-shaped groove) | |
| General sensation | Lingual nerve (V3) | Glossopharyngeal (IX) |
| Taste | Chorda tympani (VII) | Glossopharyngeal (IX) |
| Mucosa | Has papillae | NO papillae (has lingual tonsil instead) |
Prof Point: The terminal sulcus is V-shaped. At the apex of this V is the Foramen Cecum - this is where the thyroid gland descended in the embryo. This is why thyroglossal cysts exist!
Key Landmarks
- Foramen Cecum - apex of terminal sulcus, marks origin of thyroid
- Frenulum - midline fold on undersurface connecting tongue to floor of mouth
- Median Septum - internal connective tissue dividing tongue into RIGHT and LEFT halves (important for spread of cancer)
- Lingual Tonsil - lymphoid tissue on posterior 1/3 (no papillae here)
PART 3: PAPILLAE (Exam Favourite!)
🧠 Mnemonic for Papillae: "Very Fine Food Fun"
Vallate - Filiform - Foliate - Fungiform
| Papilla | Shape | Location | Taste Buds? | Key Fact |
|---|
| Filiform | Small cone-shaped, pointed | All over dorsum | ❌ NO | Most numerous; NO taste buds |
| Fungiform | Rounded, mushroom-like | Margins/edges of tongue | ✅ YES | "Fungi" = mushroom shape |
| Vallate (Circumvallate) | Large, blunt, cylinder-shaped, surrounded by a trench | V-line just ANTERIOR to terminal sulcus | ✅ YES | Only 8-12 in number; largest |
| Foliate | Linear folds | Sides of tongue near terminal sulcus | ✅ YES | Near terminal sulcus |
Prof Point: Filiform papillae have NO taste buds - this is a classic MCQ trap! All other papillae DO have taste buds.
Prof Point: Vallate papillae are located anterior to the terminal sulcus (not posterior) - another common trap.
PART 4: MUSCLES OF THE TONGUE
First, the Golden Rule:
ALL muscles of the tongue = Hypoglossal nerve (CN XII)
EXCEPT Palatoglossus = Vagus nerve (CN X)
🧠 Mnemonic for Extrinsic Muscles: "Good Habits Should Persist"
Genioglossus - Hyoglossus - Styloglossus - Palatoglossus
EXTRINSIC MUSCLES (Origin OUTSIDE tongue)
| Muscle | Origin | Action | Nerve | Memory Hook |
|---|
| Genioglossus | Superior mental spine (mandible) | Protrudes tongue (sticks it out); depresses center | CN XII | "Genio = chin → chin pushes tongue out" |
| Hyoglossus | Greater horn + body of hyoid | Depresses tongue | CN XII | "Hyo = hyoid → pulls tongue down" |
| Styloglossus | Styloid process | Retracts + Elevates tongue | CN XII | "Stylo = style, pulls tongue back stylishly" |
| Palatoglossus | Palatine aponeurosis | Elevates back of tongue; closes oropharyngeal isthmus | CN X (Vagus!) | "Palato = palate → different boss (CN X)" |
INTRINSIC MUSCLES (Origin AND insertion INSIDE tongue)
🧠 Mnemonic: "Super Intelligent Tight Verticals"
Superior longitudinal - Inferior longitudinal - Transverse - Vertical
| Muscle | Action |
|---|
| Superior longitudinal | Shortens tongue; CURLS tip UP |
| Inferior longitudinal | Shortens tongue; CURLS tip DOWN |
| Transverse | Narrows and ELONGATES tongue |
| Vertical | FLATTENS and widens tongue |
All 4 intrinsic muscles = CN XII
PART 5: NERVE SUPPLY (Most Important for Profs!)
🧠 Master Mnemonic: "Lingual General, Chorda Taste, Glosso Back, Hypoglossal Motor"
| Nerve | Function | Region |
|---|
| Lingual nerve (V3) | General sensation (touch, pain, temp) | Anterior 2/3 |
| Chorda tympani (VII) | TASTE | Anterior 2/3 |
| Glossopharyngeal (IX) | General sensation + TASTE | Posterior 1/3 |
| Vagus (X) | Motor to palatoglossus only | - |
| Hypoglossal (XII) | Motor to ALL other muscles | Whole tongue |
How to Remember the Route of Chorda Tympani:
Chorda tympani is a branch of facial nerve (VII) → it joins the lingual nerve in the infratemporal fossa → hitchhikes with lingual nerve → carries taste from anterior 2/3 to geniculate ganglion → nucleus solitarius (in brainstem)
Prof Point: The lingual nerve loops UNDER the submandibular duct ("the nerve winds under the duct like a skipping rope") - important in surgery!
PART 6: BLOOD SUPPLY
Artery:
- Lingual artery - branch of External Carotid Artery (2nd branch)
- Passes DEEP to hyoglossus muscle
- Travels between hyoglossus and genioglossus muscles
- Supplies: tongue + sublingual gland + floor of mouth gingiva
Veins:
- Deep lingual vein - visible through mucosa on undersurface (the blue veins you can see under your own tongue!)
- Dorsal lingual vein
- Both drain into Internal Jugular Vein
🧠 Mnemonic: "Lingual Artery = External Carotid's 2nd Branch"
(Superior thyroid → Lingual → Facial → Occipital → Ascending pharyngeal... = "Some Lovely Faces Often Appear")
PART 7: LYMPHATIC DRAINAGE (Prof LOVES this!)
This is high-yield because it determines spread of tongue cancer.
| Region | Drains to | Side |
|---|
| Tip of tongue | Submental nodes | Bilateral |
| Lateral borders | Submandibular nodes → Deep cervical | Ipsilateral (same side) |
| Midline / Base | Deep cervical nodes | Bilateral |
| Posterior 1/3 | Upper deep cervical nodes | Bilateral |
Prof Point - KEY RULE:
- Lateral tongue → IPSILATERAL nodes (cancer stays same side)
- Tip, midline, base → BILATERAL nodes (cancer can spread to BOTH sides)
- This is WHY surgeons do bilateral neck dissection for midline tongue tumors!
PART 8: DEVELOPMENT (Embryology - Short but Exam-worthy)
- Tongue develops from branchial arches:
- Anterior 2/3: from 1st branchial arch (mandibular) → that's why V3 supplies it
- Posterior 1/3: from 3rd and 4th branchial arches → that's why CN IX supplies it
- Foramen cecum = site of thyroid descent → thyroglossal duct forms here
Prof Point: The nerve supply of the tongue REFLECTS its embryological origin - this is the conceptual reason, not just a fact to memorize!
PART 9: CLINICAL CORRELATIONS (Prof Pattern)
1. Hypoglossal Nerve (CN XII) Lesion
- LMN (Lower Motor Neuron) lesion (e.g., nerve cut, tumor):
- Tongue DEVIATES toward the SIDE OF LESION on protrusion
- Wasting (atrophy) + fasciculations on affected side
- Genioglossus on normal side pushes tongue toward lesion side
- UMN (Upper Motor Neuron) lesion (e.g., stroke):
- Tongue deviates toward OPPOSITE side of lesion
🧠 Mnemonic: "LMN = Loves the lesion" (deviates TOWARD lesion)
"UMN = Unhappy, goes AWAY from lesion"
2. Lingual Nerve Injury
- Loss of general sensation anterior 2/3 of tongue
- If injury is PROXIMAL to where chorda tympani joins → also lose TASTE from anterior 2/3 + lose submandibular/sublingual gland secretion
- Common in wisdom tooth (3rd molar) extraction - nerve lies right next to last molar!
3. Tongue Cancer (Carcinoma of Tongue)
- Most common site: lateral border, middle third of oral tongue
- 90% are squamous cell carcinoma
- Risk factors: tobacco + alcohol
- Spreads to: ipsilateral cervical nodes (if lateral), bilateral (if midline/tip)
- Midline septum LIMITS spread to opposite side initially
4. Thyroglossal Duct Cyst
- Remnant of thyroid descent from foramen cecum
- Moves UP on swallowing and on protruding the tongue (key clinical sign!)
5. Ankyloglossia (Tongue-tie)
- Short/tight frenulum
- Limits tongue protrusion
- Causes speech and feeding difficulties
PART 10: MCQs - PROF PATTERN
Q1. All muscles of the tongue are supplied by the hypoglossal nerve EXCEPT:
- A) Genioglossus
- B) Styloglossus
- C) Palatoglossus
- D) Hyoglossus
Answer: C - Palatoglossus (supplied by Vagus CN X)
Q2. The foramen cecum of the tongue represents:
- A) Opening of submandibular duct
- B) Site of origin of thyroid gland
- C) Junction of lingual and glossopharyngeal nerves
- D) Origin of lingual artery
Answer: B - Site of thyroid gland origin (thyroid descends from here)
Q3. Taste sensation from the anterior two-thirds of the tongue is carried by:
- A) Lingual nerve (V3)
- B) Glossopharyngeal nerve (IX)
- C) Chorda tympani branch of facial nerve (VII)
- D) Hypoglossal nerve (XII)
Answer: C - Chorda tympani (branch of CN VII)
Q4. Which papillae of the tongue have NO taste buds?
- A) Vallate
- B) Fungiform
- C) Foliate
- D) Filiform
Answer: D - Filiform (only papillae with NO taste buds)
Q5. The lingual artery is a branch of:
- A) Internal carotid artery
- B) External carotid artery
- C) Facial artery
- D) Maxillary artery
Answer: B - External Carotid Artery
Q6. The muscle responsible for protruding the tongue is:
- A) Styloglossus
- B) Hyoglossus
- C) Palatoglossus
- D) Genioglossus
Answer: D - Genioglossus
Q7. General sensation from the posterior one-third of the tongue is carried by:
- A) Lingual nerve
- B) Chorda tympani
- C) Glossopharyngeal nerve (IX)
- D) Vagus nerve
Answer: C - Glossopharyngeal nerve (CN IX)
Q8. The hyoglossus muscle originates from:
- A) Styloid process
- B) Inferior mental spine
- C) Greater horn and body of hyoid
- D) Palatine aponeurosis
Answer: C - Greater horn and adjacent body of hyoid bone
Q9. The lingual nerve loops around which structure in the floor of the mouth?
- A) Submandibular duct
- B) Lingual artery
- C) Hypoglossal nerve
- D) Sublingual gland duct
Answer: A - Submandibular duct (it winds under it)
Q10. Which of the following regarding lymphatic drainage of the tongue is CORRECT?
- A) Lateral borders drain bilaterally
- B) Tip of tongue drains only ipsilaterally
- C) Midline and base drain bilaterally
- D) All parts drain to submandibular nodes only
Answer: C - Midline and base drain bilaterally
PART 11: SCENARIO-BASED MCQs
Scenario 1:
A 45-year-old man is asked to stick out his tongue during a neurological examination. His tongue deviates to the LEFT side. He has wasting and fasciculations on the left side of the tongue. Which nerve is most likely damaged?
- A) Right hypoglossal nerve (UMN lesion)
- B) Left hypoglossal nerve (LMN lesion)
- C) Left lingual nerve
- D) Right glossopharyngeal nerve
Answer: B - Left hypoglossal nerve LMN lesion
Explanation: Wasting + fasciculations = LMN lesion. LMN tongue deviation = toward the side of lesion. Left side wasting + left deviation = left CN XII LMN lesion.
Scenario 2:
A dental surgeon performs extraction of the lower third molar (wisdom tooth). Post-operatively, the patient complains of loss of sensation on the anterior two-thirds of the tongue AND loss of taste on the same side. Which nerve was most likely damaged?
- A) Chorda tympani only
- B) Glossopharyngeal nerve
- C) Lingual nerve proximal to where chorda tympani joins it
- D) Hypoglossal nerve
Answer: C - Lingual nerve proximal to chorda tympani junction
Explanation: If the lingual nerve is cut proximal to where chorda tympani joins it, BOTH general sensation (V3 fibers) AND taste (VII fibers traveling via chorda tympani) are lost from anterior 2/3.
Scenario 3:
A 60-year-old smoker presents with a painful ulcer on the lateral border of the tongue. Biopsy confirms squamous cell carcinoma. The surgeon plans neck dissection. Which lymph nodes should be dissected?
- A) Bilateral deep cervical nodes
- B) Ipsilateral deep cervical nodes only
- C) Submental nodes only
- D) Bilateral submandibular nodes
Answer: B - Ipsilateral deep cervical nodes only
Explanation: Lateral tongue drains IPSILATERALLY. If the tumor were on the tip or midline, bilateral dissection would be needed.
Scenario 4:
During swallowing, a patient's tongue base elevates to push the food bolus backward. A tumor compresses the nerve supplying this movement. Which muscle and nerve are MOST likely involved?
- A) Genioglossus - CN XII
- B) Styloglossus - CN XII
- C) Palatoglossus - CN X
- D) Hyoglossus - CN XII
Answer: C - Palatoglossus - CN X (Vagus)
Explanation: Palatoglossus elevates the back of the tongue and closes the oropharyngeal isthmus during swallowing. It is the ONLY tongue muscle supplied by Vagus (CN X).
Scenario 5:
A 3-year-old child has difficulty feeding and speech problems. Examination shows that the tongue cannot be protruded beyond the lower incisors and the frenulum is very short. Diagnosis?
- A) Hypoglossal nerve palsy
- B) Ankyloglossia (tongue-tie)
- C) Macroglossia
- D) Lingual nerve injury
Answer: B - Ankyloglossia (tongue-tie)
Explanation: Short frenulum restricts tongue protrusion. Tongue-tie is common in infants and can cause feeding and speech issues. No nerve damage - purely anatomical.
PART 12: QUICK REVISION SUMMARY TABLE
| Topic | Key Fact |
|---|
| Anterior 2/3 sensation | Lingual nerve (V3) |
| Anterior 2/3 taste | Chorda tympani (VII) |
| Posterior 1/3 sensation + taste | Glossopharyngeal (IX) |
| All muscles motor | Hypoglossal (XII) |
| Exception muscle | Palatoglossus = Vagus (X) |
| Tongue protrudes | Genioglossus |
| Tongue retracts | Styloglossus |
| Tongue depresses | Hyoglossus |
| Blood supply | Lingual artery (from ECA) |
| LMN lesion deviation | Toward side of lesion |
| UMN lesion deviation | Away from side of lesion |
| No taste buds | Filiform papillae |
| Thyroid origin marker | Foramen cecum |
| Bilateral lymph drainage | Tip, midline, base |
| Ipsilateral drainage | Lateral borders |
FINAL EXAM TIPS FROM PROF'S PERSPECTIVE
- Nerve supply is the #1 MCQ topic - know the 2/3 vs 1/3 rule cold
- Palatoglossus exception comes up EVERY year
- Filiform = no taste buds - classic trap
- Tongue deviation in CN XII lesion - know UMN vs LMN difference
- Lymphatic drainage - lateral = ipsilateral; midline/tip/base = bilateral
- Foramen cecum and its embryological significance
- Lingual nerve wrapping under submandibular duct - surgical anatomy favourite
- Chorda tympani joins lingual nerve in infratemporal fossa - not inside the mouth
Sources: Gray's Anatomy for Students, Scott-Brown's Otorhinolaryngology Head & Neck Surgery, Developing Human (Moore), S Das Manual of Clinical Surgery
Good luck in your proffs! You've got this! 💪