
Treatment for equino cavovarus deformity of foot
cavovarus AND treatment
cavovarus foot treatment review adult pediatric orthopaedic
1. Assess before treatment
- Standing and gait assessment, callosities, ankle instability, peroneal weakness, claw toes, sensory loss, ulcers.
- Weight-bearing AP, lateral, and hindfoot alignment radiographs.
- Coleman block test:
- Hindfoot varus corrects: it is largely forefoot-driven, usually from a plantar-flexed first ray.
- Varus remains: there is a fixed/independent hindfoot varus, requiring hindfoot correction in addition to forefoot correction.
- Determine whether ankle equinus is gastrocnemius-only or Achilles contracture with the Silfverskiöld test.
2. Nonoperative treatment
- Physiotherapy: calf stretching, strengthening of weak dorsiflexors/evertors, gait training.
- Custom orthosis: accommodate the cavus arch, first-ray recess/cutout, and lateral hindfoot posting to reduce varus loading.
- Lace-up ankle brace for instability; an AFO when there is foot drop, substantial weakness, or fixed deformity.
- Wide, deep toe-box footwear and padding for claw toes/callosities.
- Regular skin and neuropathy surveillance.
3. Operative treatment
A. Flexible deformity
| Deformity component | Common procedure |
|---|---|
| Plantar fascial contracture/cavus | Plantar fascia release, sometimes intrinsic release |
| Plantar-flexed first ray | Dorsiflexion osteotomy of the first metatarsal |
| Persistent hindfoot varus | Lateralizing calcaneal slide or lateral closing-wedge calcaneal osteotomy |
| Peroneus longus overpowering peroneus brevis | Peroneus longus-to-brevis tendon transfer |
| Dorsiflexor weakness/foot drop | Tendon transfer selected according to residual muscle strength, commonly posterior tibial tendon transfer in selected patients |
| Equinus | Gastrocnemius recession if isolated gastrocnemius tightness; Achilles tendon lengthening if true Achilles contracture |
| Flexible claw hallux/toes | Tendon balancing; Jones procedure for a flexible claw hallux in selected cases |
B. Stiff but joint-preserving deformity
- Combined first-ray, midfoot, and/or calcaneal osteotomies.
- Tendon balancing and soft-tissue release as required.
- Address equinus concurrently if it prevents a plantigrade foot.
C. Rigid deformity, arthritis, or failed reconstruction
- Triple arthrodesis is a salvage option for a completely rigid cavovarus foot, particularly when joints are painful or degenerated.
- It may be combined with Achilles lengthening and tendon transfer where appropriate.
- Fusion sacrifices hindfoot motion, so joint-preserving correction is preferred when feasible. Campbell's Operative Orthopaedics, 15th ed., p. 1740.
Practical principle
How is flexible versus rigid cavovarus deformity assessed?
cavovarus foot assessment
cavovarus foot clinical assessment Coleman block test flexible rigid hindfoot
1. Clinical manual examination
-
hindfoot varus toward neutral/valgus
-
forefoot pronation and plantar-flexed first ray
-
ankle dorsiflexion, with knee extended and flexed, to identify gastrocnemius versus Achilles contracture
-
Flexible cavovarus: the heel can be manually brought to neutral or valgus, and the forefoot/first ray is correctable.
-
Rigid cavovarus: the heel and/or forefoot cannot be brought to plantigrade neutral alignment. Check for subtalar arthritis, tarsal coalition, prior trauma, contracture, and fixed muscle imbalance.
2. Coleman block test: key dynamic test
- Patient stands with the heel and lateral border of the foot on a block, usually about 1 inch high.
- The medial forefoot and first metatarsal are unsupported, so the plantar-flexed first ray can drop freely.
- Observe heel alignment from behind, and compare with normal standing.
| Finding | Meaning |
|---|---|
| Heel varus corrects to neutral or slight valgus | Flexible, forefoot-driven hindfoot varus. The plantar-flexed first ray creates a tripod effect that pushes the heel into varus. |
| Heel varus partly corrects | Mixed deformity: a forefoot contribution plus some hindfoot stiffness. |
| Heel remains in varus | Rigid or hindfoot-driven varus. The hindfoot itself needs correction or there may be a structural cause such as subtalar pathology. |
Why it matters
- Flexible, forefoot-driven deformity: correction can focus on the plantar-flexed first ray and muscle balance, such as first-metatarsal dorsiflexion osteotomy with indicated soft-tissue or tendon procedures.
- Persistent hindfoot varus on the block: hindfoot correction, commonly a lateralizing or lateral closing-wedge calcaneal osteotomy, is generally needed in addition to forefoot correction.
- Completely rigid foot with arthritic joints: may require joint-sacrificing reconstruction such as triple arthrodesis in selected patients.
.
How is flexible versus rigid cavovarus deformity assessed?
Manual assessment
-
Hindfoot varus
-
Forefoot pronation and plantar-flexed first ray
-
Ankle equinus, including the Silfverskiöld test
-
Flexible deformity: heel and forefoot can be corrected manually to a plantigrade, neutral position.
-
Rigid deformity: correction to neutral is not possible because of fixed bony deformity, joint stiffness/arthritis, contracture, or longstanding muscle imbalance.
Coleman block test
- Heel varus corrects to neutral or valgus: flexible, forefoot-driven hindfoot varus. The plantar-flexed first ray is driving the heel into varus.
- Heel varus remains unchanged: rigid or hindfoot-driven varus.
- Partial correction: combined forefoot-driven deformity and a stiff hindfoot component.
Create a quick-reference PDF on cavovarus assessment
cavovarus foot assessment Coleman block test review
~/
mkdir -p "/tmp/workspace/cavovarus-assessment-pdf/src" "/tmp/workspace/cavovarus-assessment-pdf/output" && python - <<'PY' from reportlab.lib import colors from reportlab.lib.enums import TA_CENTER from reportlab.lib.pagesizes import A4 from reportlab.lib.styles import getSampleStyleSheet, ParagraphStyle from reportlab.lib.units import mm from reportlab.platypus import SimpleDocTemplate, Paragraph, Spacer, Table, TableStyle, KeepTogether, PageBreak from reportlab.pdfbase.ttfonts import TTFont from reportlab.pdfbase import pdfmetrics from reportlab.lib.colors import HexColor out='/tmp/workspace/cavovarus-assessment-pdf/output/Cavovarus_Assessment_Quick_Reference.pdf' PAGE_W, PAGE_H=A4 navy=HexColor('#12324A'); teal=HexColor('#007C83'); pale=HexColor('#EAF4F4'); light=HexColor('#F4F7F9'); amber=HexColor('#FFF4D8'); red=HexColor('#8B2E2E'); gray=HexColor('#58636B') styles=getSampleStyleSheet() styles.add(ParagraphStyle(name='TitleQR', parent=styles['Title'], fontName='Helvetica-Bold', fontSize=21, leading=25, textColor=navy, spaceAfter=4)) styles.add(ParagraphStyle(name='SubQR', parent=styles['Normal'], fontName='Helvetica', fontSize=9.5, leading=13, textColor=gray, spaceAfter=10)) styles.add(ParagraphStyle(name='HeadQR', parent=styles['Heading2'], fontName='Helvetica-Bold', fontSize=12, leading=14, textColor=colors.white, backColor=teal, borderPadding=(5,6,4), spaceBefore=8, spaceAfter=6)) styles.add(ParagraphStyle(name='BodyQR', parent=styles['Normal'], fontName='Helvetica', fontSize=8.5, leading=11.2, textColor=HexColor('#1F2D36'), spaceAfter=3)) styles.add(ParagraphStyle(name='SmallQR', parent=styles['Normal'], fontName='Helvetica', fontSize=7.3, leading=9.2, textColor=gray)) styles.add(ParagraphStyle(name='CellQR', parent=styles['Normal'], fontName='Helvetica', fontSize=8, leading=10, textColor=HexColor('#1F2D36'))) styles.add(ParagraphStyle(name='CellHeadQR', parent=styles['Normal'], fontName='Helvetica-Bold', fontSize=8, leading=10, textColor=colors.white, alignment=TA_CENTER)) def P(t,style='BodyQR'): return Paragraph(t, styles[style]) def bullet(t): return P('• '+t) def footer(canvas, doc): canvas.saveState() canvas.setStrokeColor(HexColor('#C7D7DC')); canvas.line(16*mm, 13*mm, PAGE_W-16*mm, 13*mm) canvas.setFont('Helvetica', 7.2); canvas.setFillColor(gray) canvas.drawString(16*mm, 8.5*mm, 'Cavovarus assessment quick reference | Educational use only') canvas.drawRightString(PAGE_W-16*mm, 8.5*mm, f'Page {doc.page}') canvas.restoreState() doc=SimpleDocTemplate(out,pagesize=A4,rightMargin=16*mm,leftMargin=16*mm,topMargin=14*mm,bottomMargin=18*mm,title='Cavovarus Assessment Quick Reference',author='Orris') story=[] story += [P('Cavovarus Foot Assessment','TitleQR'), P('Quick-reference guide: determine flexibility, localize the driver, and identify features that require further work-up.','SubQR')] # Definition/cycle box=Table([[P('<b>Core assessment question</b><br/>Is the heel varus <b>forefoot-driven and flexible</b>, or is there a <b>fixed hindfoot component</b>?','BodyQR'), P('<b>Do not assess the heel alone.</b><br/>Evaluate the cavus, plantar-flexed first ray, hindfoot, equinus, toe deformity, muscle balance, sensation, and alignment under weight-bearing.','BodyQR')]], colWidths=[87*mm,87*mm]) box.setStyle(TableStyle([('BACKGROUND',(0,0),(-1,-1),pale),('BOX',(0,0),(-1,-1),0.5,HexColor('#9FC6C8')),('INNERGRID',(0,0),(-1,-1),0.4,HexColor('#BFDADD')),('VALIGN',(0,0),(-1,-1),'TOP'),('LEFTPADDING',(0,0),(-1,-1),7),('RIGHTPADDING',(0,0),(-1,-1),7),('TOPPADDING',(0,0),(-1,-1),6),('BOTTOMPADDING',(0,0),(-1,-1),6)])) story += [box, Spacer(1,7), P('1. Standing and gait examination','HeadQR')] for x in [ '<b>Inspect standing alignment:</b> high medial arch, hindfoot varus viewed from behind, forefoot adduction/pronation, plantar-flexed first ray, claw toes, and callosities (often lateral border or first/fifth metatarsal heads).', '<b>Observe gait and function:</b> recurrent ankle sprains or instability, lateral overload, foot drop/steppage gait, ability to heel walk and toe walk.', '<b>Compare both sides:</b> asymmetry, progression, skin integrity, previous scars, footwear wear pattern, and limb rotation.' ]: story.append(bullet(x)) story += [P('2. Suppleness and component examination','HeadQR')] t=Table([[P('Component','CellHeadQR'),P('How to assess','CellHeadQR'),P('What to record','CellHeadQR')], [P('<b>Hindfoot</b>','CellQR'),P('Manually bring calcaneus from varus toward neutral/valgus with the subtalar joint controlled.','CellQR'),P('Fully correctable, partially correctable, or fixed.','CellQR')], [P('<b>Forefoot / first ray</b>','CellQR'),P('Assess whether first ray is plantar-flexed and whether forefoot pronation/cavus can be passively corrected.','CellQR'),P('Flexible versus fixed plantar-flexed first ray; claw toes.','CellQR')], [P('<b>Equinus</b>','CellQR'),P('Measure ankle dorsiflexion with hindfoot held neutral, knee extended and then flexed (Silfverskiöld test).','CellQR'),P('Gastrocnemius tightness if dorsiflexion improves with knee flexion; persistent restriction suggests Achilles/ankle contracture.','CellQR')], [P('<b>Neuromuscular</b>','CellQR'),P('Test dorsiflexors, evertors, invertors, plantarflexors; assess sensation, reflexes, and balance.','CellQR'),P('Muscle imbalance, sensory loss, foot drop, areflexia, or neuropathy signs.','CellQR')]], colWidths=[29*mm,72*mm,73*mm], repeatRows=1) t.setStyle(TableStyle([('BACKGROUND',(0,0),(-1,0),navy),('BACKGROUND',(0,1),(-1,-1),light),('GRID',(0,0),(-1,-1),0.35,HexColor('#B9C8CF')),('VALIGN',(0,0),(-1,-1),'TOP'),('LEFTPADDING',(0,0),(-1,-1),5),('RIGHTPADDING',(0,0),(-1,-1),5),('TOPPADDING',(0,0),(-1,-1),4),('BOTTOMPADDING',(0,0),(-1,-1),4)])) story += [t, Spacer(1,7), P('3. Coleman block test: key test for hindfoot flexibility','HeadQR')] story += [bullet('<b>Set-up:</b> with the patient weight-bearing, place a block, commonly about 1 inch high, under the heel and lateral border of the foot. The medial forefoot/first ray hangs free off the block.'), bullet('<b>Purpose:</b> removes the plantar-flexed first ray “tripod” effect and tests whether heel varus is secondary to the forefoot or intrinsic to the hindfoot.')] res=Table([[P('Result','CellHeadQR'),P('Interpretation','CellHeadQR'),P('Implication','CellHeadQR')], [P('<b>Heel corrects to neutral or slight valgus</b>','CellQR'),P('<b>Flexible, forefoot-driven hindfoot varus.</b> The plantar-flexed first ray is a principal driver.','CellQR'),P('Focus correction planning on the forefoot/first ray and muscle balance; confirm all components.','CellQR')], [P('<b>Partial correction</b>','CellQR'),P('<b>Mixed deformity.</b> There is a forefoot contribution plus residual hindfoot stiffness or deformity.','CellQR'),P('Plan may need both forefoot and hindfoot correction.','CellQR')], [P('<b>Heel remains in varus</b>','CellQR'),P('<b>Rigid or hindfoot-driven varus.</b> Evaluate for subtalar stiffness/arthritis, coalition, prior fracture, spasm, or fixed structural deformity.','CellQR'),P('A hindfoot procedure may be required if operative correction is indicated.','CellQR')]],colWidths=[47*mm,74*mm,53*mm],repeatRows=1) res.setStyle(TableStyle([('BACKGROUND',(0,0),(-1,0),navy),('BACKGROUND',(0,1),(-1,-1),colors.white),('GRID',(0,0),(-1,-1),0.35,HexColor('#B9C8CF')),('VALIGN',(0,0),(-1,-1),'TOP'),('LEFTPADDING',(0,0),(-1,-1),5),('RIGHTPADDING',(0,0),(-1,-1),5),('TOPPADDING',(0,0),(-1,-1),5),('BOTTOMPADDING',(0,0),(-1,-1),5)])) story += [res, Spacer(1,7), P('4. Imaging and additional work-up','HeadQR')] for x in [ '<b>Weight-bearing foot radiographs:</b> AP, lateral, and hindfoot alignment views. Document cavus (for example, Meary angle on lateral view), forefoot adduction, hindfoot varus, joint congruity, and arthritis.', '<b>Coleman-block radiographs:</b> can corroborate clinical correction of the hindfoot.', '<b>Consider weight-bearing CT:</b> when 3-dimensional alignment, subtalar pathology, coalition, or operative planning is unclear.', '<b>Neurologic assessment:</b> particularly important in bilateral or progressive cavovarus. Consider neurology/genetics evaluation for suspected Charcot-Marie-Tooth disease.' ]: story.append(bullet(x)) warn=Table([[P('<b>Red flags / prompt further evaluation</b><br/>New or progressive <b>unilateral</b> cavus, neurologic deficit or sensory loss, ulceration/infection, rapidly progressive deformity, severe pain, or suspected spinal/central neurologic disease.','BodyQR')]],colWidths=[174*mm]) warn.setStyle(TableStyle([('BACKGROUND',(0,0),(-1,-1),amber),('BOX',(0,0),(-1,-1),0.5,HexColor('#DBB66E')),('LEFTPADDING',(0,0),(-1,-1),7),('RIGHTPADDING',(0,0),(-1,-1),7),('TOPPADDING',(0,0),(-1,-1),6),('BOTTOMPADDING',(0,0),(-1,-1),6)])) story += [Spacer(1,5),warn,Spacer(1,7),P('Document in one line','HeadQR'),P('<b>Example:</b> “Right cavovarus with plantar-flexed first ray and flexible claw toes; heel varus corrects to neutral on Coleman block test, consistent with flexible forefoot-driven hindfoot varus. Ankle dorsiflexion improves with knee flexion. Peroneal weakness and reduced vibration sensation present.”','BodyQR'),Spacer(1,6),P('<b>Sources:</b> Campbell’s Operative Orthopaedics, 15th ed., Clinical Evaluation and Radiographic Evaluation of cavovarus foot, p. 1740. Miller’s Review of Orthopaedics, 9th ed., Pes Cavus and Coleman block assessment, p. 147. Foran IM et al. Impact of Coleman Block Test on Adult Hindfoot Alignment. Foot & Ankle Orthopaedics. 2020.','SmallQR'),P('This is an educational quick reference, not a substitute for examination, imaging interpretation, or specialist clinical judgment.','SmallQR')] doc.build(story,onFirstPage=footer,onLaterPages=footer) print(out) PY python - <<'PY' from pypdf import PdfReader p='/tmp/workspace/cavovarus-assessment-pdf/output/Cavovarus_Assessment_Quick_Reference.pdf' r=PdfReader(p) print('pages',len(r.pages),'bytes',__import__('os').path.getsize(p)) print(r.pages[0].extract_text()[:250]) PY
Cavovarus Assessment Quick Reference
PDF Document · PDF
Treatment for neurogenic clubfoot age wise
myelomeningocele clubfoot treatment
myelomeningocele neurogenic clubfoot treatment Ponseti age surgical management review
PMID: 39365806
https://pmc.ncbi.nlm.nih.gov/articles/PMC12777138
Neurogenic clubfoot: age-wise treatment
| Age / presentation | Main treatment | Key points |
|---|---|---|
| Newborn to 3 months | Start Ponseti serial manipulation and long-leg casting early | Correct cavus, adduction, varus, then equinus. Neurogenic feet are stiffer than idiopathic clubfeet and often need more casts. Perform percutaneous Achilles tenotomy when residual equinus persists. |
| After initial correction: infancy to walking age | Foot-abduction brace or AFO, physiotherapy, close surveillance | Bracing must be individualized for sensory loss and skin vulnerability. Monitor for pressure sores and recurrence. Tendon imbalance persists, so recurrence is common. |
| Infant or young child with residual/recurrent but still flexible deformity | Repeat Ponseti casting, repeat Achilles tenotomy or limited posterior release if needed | Recasting should generally be attempted before extensive surgery when the foot remains reducible. Identify and address brace nonadherence, progressive spasticity, tethered cord, and muscle imbalance. |
| Toddler to early school age with resistant deformity | Limited soft-tissue surgery plus muscle balancing, selected tendon lengthening or tendon excision/transfer | Surgery is for an unbraceable, painful, progressive, or non-plantigrade foot after casting. In myelomeningocele, tendon balancing or removal of deforming forces may be more reliable than tendon transfer alone. Avoid excessive releases where possible because a stiff, insensate foot is vulnerable to skin breakdown. |
| School-age child with fixed structural deformity | Osteotomy-based, joint-preserving reconstruction | Correct residual varus, cavus, adduction, and equinus using targeted soft-tissue procedures and osteotomies. Aim to preserve motion and obtain a braceable foot. |
| Adolescent with severe rigid, recurrent, or neglected clubfoot | Major joint-preserving reconstruction when feasible; salvage procedures only if necessary | Consider multi-level osteotomy and soft-tissue balancing. Arthrodesis is generally avoided in insensate myelomeningocele feet because of ulceration and Charcot-type joint risk. Talectomy or fusion may be rare salvage options for a severely rigid, unbraceable deformity. |
| Any age: ulceration, infection, rapidly progressive deformity, loss of function | Urgent multidisciplinary review | Evaluate skin, vascular status, infection/osteomyelitis, orthotic fit, neurologic progression or tethered cord, and caregiver ability to maintain treatment. |
Practical treatment sequence
- Early Ponseti casting for all reducible neurogenic clubfeet, including many with myelomeningocele.
- Achilles tenotomy is frequently needed to obtain dorsiflexion.
- Long-term bracing and follow-up are mandatory.
- Recast early at relapse, while the foot is still flexible.
- Use limited soft-tissue balancing and joint-preserving osteotomies for resistant or fixed deformity.
- Reserve arthrodesis/talectomy-type salvage for exceptional severe, rigid feet.
Important difference from idiopathic clubfoot
Sequestrum when formed and when it is visible on xray
chronic osteomyelitis sequestrum radiograph
sequestrum visible radiograph 2 3 weeks osteomyelitis
- Formation: bone necrosis and sequestrum formation usually begin at about 10-14 days after onset of acute osteomyelitis, due to vascular thrombosis and periosteal stripping.
- Visible on plain X-ray: usually only after several weeks, classically around 3-4 weeks. It appears as a dense bony fragment surrounded by a radiolucent rim of granulation tissue/pus, often with involucrum in established chronic osteomyelitis.
Sequestrum forms by about 2 weeks and becomes apparent on radiograph by about 3-4 weeks.
Cubitus valgus examination cause management and treatment
cubitus valgus AND osteotomy
cubitus valgus examination causes management corrective osteotomy ulnar neuropathy
Cubitus valgus
- Normal physiological carrying angle: usually about 5-15° in males and 10-20° in females.
- It is considered pathological when clearly greater than the opposite side, progressive, cosmetically unacceptable, or associated with tardy ulnar nerve palsy.
Examination
1. Inspection
- Increased carrying angle and asymmetry compared with the opposite elbow
- Healed scars or deformity from an old lateral condyle/supracondylar fracture
- Prominence around the medial epicondyle
- Wasting of hypothenar muscles and first dorsal interosseous muscle, suggesting ulnar neuropathy
- Clawing of ring and little fingers in advanced ulnar palsy
2. Measure the carrying angle
- Use a goniometer.
- One arm follows the longitudinal axis of the humerus; the other follows the axis of the forearm.
- Record the angle on both sides and the side-to-side difference.
- Ensure the elbow is fully extended and forearm supinated, as rotation alters the apparent angle.
3. Palpation
- Palpate medial and lateral epicondyles, distal humerus, and ulnar nerve in the cubital tunnel.
- Look for tenderness, instability, crepitus, or a palpable nonunion around the lateral condyle.
4. Range of movement and stability
- Flexion and extension
- Pronation and supination
- Varus-valgus stability
- Functional effect during activities
5. Ulnar nerve examination
- Tingling/numbness in the little finger and ulnar half of ring finger
- Hand weakness, clumsiness, weak grip
- Symptoms worsened by sustained elbow flexion
- Sensation in the ulnar one-and-a-half digits
- First dorsal interosseous and hypothenar bulk
- Finger abduction/adduction
- Froment sign
- Tinel sign over cubital tunnel
- Ulnar nerve subluxation during elbow flexion
6. Investigations
- AP and lateral radiographs of both elbows: measure carrying angle, identify lateral condyle nonunion, malunion, growth arrest, deformity, or arthritis.
- CT may assist surgical planning in complex deformity/nonunion.
- Nerve-conduction studies and EMG are useful when ulnar neuropathy is suspected.
Causes
Common acquired causes
-
Nonunion of a lateral humeral condyle fracture in childhood
- The classic and most important cause.
- The lateral condyle migrates proximally, increasing valgus and predisposing to tardy ulnar palsy.
-
Malunion of distal humeral fractures
- Especially lateral condylar fractures.
- Less commonly a supracondylar fracture.
-
Lateral distal humeral physeal arrest or growth disturbance
- Due to trauma, infection, surgery, or osteonecrosis.
-
Post-traumatic deformity after elbow dislocation or fracture.
Congenital/systemic causes
- Physiological familial increased carrying angle
- Turner syndrome
- Skeletal dysplasias or congenital hypoplasia of the lateral distal humerus
- Post-infective growth disturbance
Management
Observation
- The deformity is mild and non-progressive
- It is painless
- Elbow motion and function are normal
- There is no ulnar nerve dysfunction
- The main issue is only minor cosmetic asymmetry
Treat the underlying cause
- Established lateral condyle nonunion: evaluate for fixation with bone grafting and stable internal fixation where feasible.
- Growth disturbance or malunion: assess progression and functional impact.
Indications for surgery
- Significant or progressive cosmetic deformity
- Symptomatic tardy ulnar nerve palsy
- Functional limitation or elbow instability
- Painful nonunion/malunion
- Marked deformity, commonly a difference of roughly 15-20° or more, though the decision is primarily clinical rather than based on one absolute angle.
Operative treatment
-
Corrective distal humeral supracondylar osteotomy
- Usually a lateral closing-wedge, dome, step-cut, or other planned corrective osteotomy.
- Restores the carrying angle toward the contralateral side.
- Fixed with plate-and-screw, K-wire, or external fixation depending on age and technique.
-
Ulnar nerve decompression and usually anterior transposition
- Indicated in established tardy ulnar palsy, severe valgus correction, or an unstable/tethered ulnar nerve.
- Often combined with corrective osteotomy.
-
Lateral condyle nonunion surgery
- Debridement/freshening of the nonunion, bone grafting, and fixation may be performed, sometimes with valgus correction.
Key principle
Post polio residual palsy deformity in foot examination and treatment with
Post polio residual palsy deformites in foot examination and treatment with age
Post-polio residual paralysis (PPRP): foot deformities, examination, and age-wise treatment
Common deformities and muscle imbalance
| Deformity | Typical muscle imbalance |
|---|---|
| Equinus | Weak dorsiflexors, with functioning gastrocnemius-soleus |
| Calcaneus | Weak plantarflexors, with relatively functioning dorsiflexors |
| Equinovarus | Weak dorsiflexors and evertors; relatively strong tendo-Achilles, tibialis posterior, and often tibialis anterior imbalance |
| Cavovarus | Weak intrinsic muscles/peronei with relative overaction of tibialis posterior and peroneus longus |
| Planovalgus / calcaneovalgus | Weak tibialis posterior and plantarflexors with relative peroneal/dorsiflexor pull |
| Claw toes | Intrinsic muscle weakness with long flexor and extensor overactivity |
Examination of the foot in PPRP
1. History
- Age at poliomyelitis and duration of paralysis
- Progression of deformity
- Pain, callosity, ulceration, footwear difficulty
- Walking endurance, frequent falls, use of calipers/AFO
- Previous casting, tendon transfer, osteotomy, or arthrodesis
- New weakness, fatigue, or pain suggesting post-polio syndrome
2. Inspection: standing and walking
- Limb shortening, muscle wasting, scars
- Foot posture: equinus, calcaneus, varus, valgus, cavus, planus, adduction
- Callosities under metatarsal heads, lateral border, heel, or toes
- Claw toes and shoe wear pattern
- Whether heel contacts the ground
- Gait: foot drop, steppage gait, knee hyperextension, varus/valgus thrust, instability
3. Determine whether deformity is flexible or fixed
- Passively correct the hindfoot, forefoot, ankle equinus, and toe deformities.
- A flexible deformity can be brought to plantigrade alignment manually.
- A fixed deformity cannot be fully corrected because of contracture, bony deformity, or joint stiffness.
4. Muscle charting
| Motion | Main muscles to test |
|---|---|
| Dorsiflexion | Tibialis anterior, extensor hallucis longus, extensor digitorum longus |
| Plantarflexion | Gastrocnemius, soleus |
| Inversion | Tibialis posterior, tibialis anterior |
| Eversion | Peroneus longus and brevis |
| Toe flexion/extension | Long flexors and extensors |
| Intrinsic function | Interossei and lumbricals |
5. Joint examination
- Ankle dorsiflexion and plantarflexion
- Subtalar inversion/eversion
- Midfoot mobility
- Toe flexibility
- Knee and hip deformities, since these influence gait and orthotic planning
6. Investigations
- Weight-bearing AP and lateral foot radiographs, plus hindfoot alignment view.
- Assess cavus, calcaneal pitch, hindfoot varus/valgus, arthritis, and bony deformity.
- Gait assessment and orthotic review when available.
Age-wise treatment
1. Infant and very young child: under about 2-3 years
Aim
Treatment
- Gentle stretching and physiotherapy
- Serial manipulation and plaster casting for a flexible equinus/equinovarus or other correctable deformity
- Night splints and appropriate footwear
- AFO or caliper when needed for foot drop or ankle instability
- Regular reassessment because the imbalance may change with growth
2. Preschool child: about 3-5 years
Flexible deformity
- Continue physiotherapy, stretching, serial casts, and orthoses.
- Treat recurrence early with repeat casting.
- Limited soft-tissue release may be considered for a resistant contracture, but avoid overlengthening weak muscles.
Principles
- Do not operate merely for appearance.
- Surgery is considered if the foot is progressively deforming, cannot be braced, causes skin pressure, or impairs walking.
3. Child: about 5-10 years
Flexible equinus / foot drop
- AFO if dorsiflexors are weak.
- Achilles or gastrocnemius lengthening only if a true fixed equinus contracture is present.
- Selected tendon transfer may restore active dorsiflexion when there is a suitable donor muscle.
Flexible varus/equinovarus
- Release/lengthening of contracted structures as indicated.
- Tendon transfer to neutralize deforming forces, such as transfer of a functioning tibialis posterior or peroneal tendon, depending on the individual muscle chart.
- Correct associated cavus and claw toes.
Flexible calcaneus
- AFO to control calcaneus and stabilize the ankle.
- Tendon balancing/transfer or tenodesis may be considered in selected ambulatory children.
4. Older child: about 10-12 years to skeletal maturity
Fixed deformity with preserved joints
- Calcaneal osteotomy for hindfoot varus or valgus
- First metatarsal or midfoot osteotomy for cavus
- Supramalleolar osteotomy for ankle malalignment
- Combined soft-tissue balancing plus osteotomy for multi-level deformity
5. Adolescent or skeletally mature patient
Rigid deformity, recurrent deformity, painful arthritic foot, or non-braceable foot
- Corrective osteotomy if joint preservation remains possible
- Triple arthrodesis for severe, rigid hindfoot deformity when other reconstruction cannot give a stable plantigrade foot
- Selected ankle or midfoot fusion only for major pain/instability or severe deformity
Treatment by deformity
| Deformity | Nonoperative | Operative options if indicated |
|---|---|---|
| Equinus | Stretching, serial cast, AFO | Gastrocnemius recession/Achilles lengthening, tendon balancing |
| Foot drop | AFO, footwear modification | Tendon transfer if donor strength is adequate |
| Equinovarus | Cast, AFO | Soft-tissue release, tendon transfer, calcaneal/foot osteotomy if fixed |
| Cavovarus | Orthosis, lateral posting, stretching | Plantar fascia release, tendon transfer, first-ray and/or calcaneal osteotomy |
| Calcaneus/calcaneovalgus | AFO to prevent excessive dorsiflexion | Tendon balancing, tenodesis, selected osteotomy |
| Rigid painful deformity | Custom brace/shoe | Osteotomy or, as salvage in mature patients, arthrodesis |
Important principles
- Correct contracture before tendon transfer.
- Balance the deforming forces, rather than simply correcting the visible position.
- Preserve joints whenever possible.
- Provide an AFO or caliper when muscle weakness remains despite surgical correction.
- Treat associated knee, hip, limb-length, and rotational deformities because foot treatment alone may not normalize gait.
- In an adult with new progressive weakness or fatigue, assess for post-polio syndrome and avoid overly aggressive strengthening that produces prolonged fatigue.
Detailed treatment
poliomyelitis foot deformity treatment
post polio residual paralysis foot deformity treatment tendon transfer osteotomy arthrodesis
https://posna.org/physician-education/study-guide/poliomyeli…
Detailed treatment of foot deformity in post-polio residual paralysis
Treatment goals
- Plantigrade foot
- Stable foot during stance
- Painless, shoeable and braceable foot
- Foot with preserved useful motion where possible
- Correction that is matched to the patient's remaining muscle power and ambulatory needs
- Age and skeletal maturity
- Exact pattern of paralysis on muscle charting
- Flexible versus fixed deformity
- Presence of equinus, cavus, varus/valgus, calcaneus, and claw toes
- Strength of possible donor muscles
- Whether the patient walks independently, with calipers, or uses a wheelchair
- Limb-length discrepancy, knee instability, and hip deformity
1. Nonoperative treatment
Physiotherapy
- Daily stretching of tendo-Achilles, plantar fascia, toe flexors, and contracted invertors/evertors.
- Maintain ankle, subtalar, midfoot, and toe range of motion.
- Strengthen muscles with useful residual power, without fatiguing weak post-polio muscles.
- Gait training and fall prevention.
- Skin-care education, especially under orthoses and at callosities.
Serial manipulation and casting
- Gentle serial casting can correct flexible equinus, equinovarus, and some cavovarus deformities.
- Cast in progressive correction, avoiding forceful manipulation and skin pressure.
- Follow with night splint or AFO to maintain correction.
Orthoses and footwear
| Problem | Orthotic treatment |
|---|---|
| Foot drop / weak dorsiflexors | Posterior leaf-spring AFO or solid AFO |
| Equinus or ankle instability | Solid AFO or articulated AFO with plantarflexion stop |
| Calcaneus / weak plantarflexors | AFO designed to prevent excessive dorsiflexion, often with a plantarflexion stop |
| Varus or valgus hindfoot | Custom AFO with appropriate corrective posting |
| Mild cavus / callosity | Accommodative insole, metatarsal pad, lateral or medial posting as indicated |
| Limb shortening | Shoe raise or sole lift |
| Severe weakness involving knee and ankle | KAFO or caliper, sometimes floor-reaction design |
2. Treatment according to age
A. Infant and child younger than about 3 years
Main approach
- Stretching
- Manipulation and serial casting
- Night splints
- AFO when the child begins standing/walking
- Monitor every few months for recurrence and change in muscle imbalance
Surgery
- Tendo-Achilles lengthening for true fixed equinus
- Limited posterior or medial release for resistant equinovarus
- Plantar fascia release for significant fixed cavus
B. Young child, about 3-6 years
Flexible deformity
- AFO/appropriate caliper
- Repeat casting if deformity recurs
- Stretching and footwear modification
Soft-tissue balancing
- Release a contracted tendon/fascia only if it is preventing plantigrade alignment.
- Transfer a muscle only if it has reliable power, commonly MRC grade 4 or greater.
- Balance forces across both the ankle and subtalar joints.
C. Older child, about 6-10 years
Indications for surgery
- Progressive fixed equinus or varus/valgus
- Inability to fit an AFO or shoe
- Repeated callosities or ulceration
- Recurrent falls or impaired gait
- Foot becoming non-plantigrade
- Pain from abnormal loading
D. Older child near maturity and adolescent
Fixed or recurrent structural deformity
- Calcaneal osteotomy for hindfoot varus or valgus
- First metatarsal dorsiflexion osteotomy for cavus caused by a plantar-flexed first ray
- Midfoot/tarsal wedge osteotomy for rigid cavus, adduction, or complex deformity
- Supramalleolar osteotomy if ankle malalignment is a major component
- Combined soft-tissue release plus osteotomy for multi-level deformity
Severe rigid or painful foot
- Subtalar arthrodesis in selected deformities
- Triple arthrodesis for severe rigid hindfoot deformity
- Ankle arthrodesis only in exceptional cases of severe ankle instability, deformity, or painful arthritis
3. Deformity-specific treatment
A. Equinus deformity
Cause
Flexible equinus
- Stretching
- Serial casting
- AFO with plantarflexion control
- Night splint
Fixed equinus
- Gastrocnemius recession if tightness corrects with knee flexion on Silfverskiöld testing
- Tendo-Achilles lengthening if true Achilles contracture persists with both knee positions
- Posterior capsular release only for severe residual ankle contracture
Caution
B. Foot drop
Cause
Nonoperative
- AFO is first-line for many patients.
- Shoe modifications and physiotherapy.
Operative
- Tendon transfer to restore active dorsiflexion and reduce inversion.
- The exact donor and insertion are selected from the muscle chart. Posterior tibial tendon transfer is one common concept when the muscle is strong and a balanced foot can be achieved.
- Correct contracture first.
- Use an AFO, osteotomy, or, in selected mature patients with severe instability, arthrodesis.
C. Equinovarus deformity
Cause
Flexible equinovarus
- Serial casting if appropriate.
- Lengthen/release contracted tendo-Achilles if equinus is fixed.
- Release contracted medial soft tissues or plantar fascia only as required.
- Tendon balancing:
- Transfer or rebalance a functioning tendon to counter inversion and/or plantarflexion.
- The procedure must account for both ankle and subtalar mechanics.
Fixed equinovarus
- Soft-tissue release plus calcaneal or tarsal osteotomy if the hindfoot/forefoot remains structurally deformed.
- Triple arthrodesis is considered only for a severe rigid, unbraceable foot near skeletal maturity.
D. Cavus and cavovarus deformity
Cause
Flexible cavovarus
- Custom orthosis with first-ray accommodation and lateral posting
- Stretching of plantar fascia and calf
- Treat ankle instability with brace/AFO
- Plantar fascia release if contracture prevents correction
- Tendon balancing based on muscle chart
- First metatarsal dorsiflexion osteotomy if a persistent plantar-flexed first ray is the main structural driver
Fixed hindfoot varus
- Add lateralizing or lateral closing-wedge calcaneal osteotomy.
- A Coleman block test helps decide whether hindfoot varus is forefoot-driven or fixed.
Severe rigid cavovarus
- Multi-level osteotomy or, in a mature painful foot with degeneration, triple arthrodesis.
E. Calcaneus or calcaneovalgus deformity
Cause
Nonoperative
- AFO with plantarflexion restraint
- Shoe modification, such as heel elevation where appropriate
- Correct limb-length discrepancy
- Gait training
Operative
- Tendon balancing or tenodesis in carefully selected patients
- Calcaneal osteotomy where hindfoot valgus/structural malalignment predominates
- Stabilizing fusion in severe rigid deformity near maturity
F. Planovalgus deformity
Cause
Treatment
- Medial arch-support orthosis or AFO
- Achilles/gastrocnemius stretching when equinus contributes
- Tendon balancing if a suitable donor exists
- Calcaneal osteotomy and selected midfoot osteotomy for fixed symptomatic deformity
- Fusion is reserved for severe rigid or painful deformity in a mature patient.
G. Claw toes
Flexible claw toes
- Wide toe-box footwear
- Toe pads and accommodative orthoses
- Stretching
- Flexor/extensor tendon balancing or transfer if symptomatic
Fixed claw toes
- Tendon lengthening/release
- Interphalangeal joint arthrodesis or resection arthroplasty in selected older patients
- Correct the proximal cavus/equinus driver, otherwise toe deformity may recur.
4. Principles of tendon transfer in PPRP
- Paralysis has been stable.
- The foot is fully or nearly passively correctable.
- The donor muscle has useful strength, preferably MRC grade 4 or more.
- The donor is not essential for stance, crutch walking, or another vital function.
- The line of pull will correct the actual deforming force.
- Contractures and major bony deformity have been corrected first.
- The patient will follow postoperative immobilization and rehabilitation.
5. Postoperative care
- Immobilization in a well-padded below-knee or long-leg cast, depending on the procedure
- Strict skin surveillance
- Protected weight-bearing until osteotomy/fusion healing is confirmed
- Gradual physiotherapy after cast removal
- Temporary, and sometimes lifelong, AFO use
- Gait re-education
- Reassessment for recurrence during growth
Exam summary
In post-polio residual paralysis, foot deformities are treated according to age, flexibility, muscle charting, and ambulatory requirement. In young children, treatment consists of stretching, serial casting, splintage, and limited soft-tissue release. In flexible deformities of older children, tendon lengthening, release, and carefully selected tendon transfers are used after correction of contracture. In fixed deformity, joint-preserving osteotomy is preferred. Triple arthrodesis or other fusion is reserved for severe rigid, painful, unstable, or unbraceable deformity near skeletal maturity.
Sciatic nerve palsy examination deformites and treatment
sciatic nerve palsy management
sciatic nerve palsy clinical examination foot deformity management tendon transfer
Sciatic nerve palsy: examination, deformities, and treatment
1. Clinical anatomy and pattern of paralysis
- Tibial division: hamstrings, plantarflexors, invertors, toe flexors, and intrinsic muscles of the sole.
- Common peroneal division: short head of biceps femoris, dorsiflexors, toe extensors, and evertors.
2. Examination
A. History
- Trauma: posterior hip dislocation, acetabular fracture, penetrating injury, pelvic or femoral fracture
- Hip surgery or injection in the gluteal region
- Lumbar disc disease, pelvic mass, prolonged compression, or neuropathy
- Onset: immediate, delayed, progressive, or painful
- Falls, foot slap, difficulty clearing toes, inability to push off
- Numbness, burning pain, ulcers, footwear problems
- Duration of palsy and evidence of recovery
B. Inspection and gait
Inspect
- Gluteal, hamstring, calf, anterior compartment, and intrinsic foot muscle wasting
- Foot posture: foot drop, equinus, equinovarus, cavus, claw toes
- Callosity over the lateral border, metatarsal heads, or dorsum of toes
- Skin injury or ulcers in sensory loss
- Limb shortening, scars, or evidence of hip trauma/surgery
Gait
- Steppage gait: exaggerated hip and knee flexion to clear a dropped forefoot.
- Foot slap: uncontrolled plantarflexion after heel strike.
- Reduced push-off or inability to toe walk indicates tibial-division involvement.
- Varus thrust or lateral-border weight-bearing suggests evertor weakness with relatively preserved invertors.
C. Motor examination and muscle chart
| Function | Muscles | Division |
|---|---|---|
| Knee flexion | Hamstrings: semitendinosus, semimembranosus, biceps femoris long head | Tibial division |
| Knee flexion | Biceps femoris short head | Peroneal division |
| Ankle dorsiflexion | Tibialis anterior | Deep peroneal |
| Great-toe extension | Extensor hallucis longus | Deep peroneal |
| Toe extension | Extensor digitorum longus | Deep peroneal |
| Eversion | Peroneus longus and brevis | Superficial peroneal |
| Plantarflexion | Gastrocnemius and soleus | Tibial |
| Inversion | Tibialis posterior | Tibial |
| Toe flexion | Flexor hallucis longus and flexor digitorum longus | Tibial |
| Intrinsic foot muscles | Interossei, lumbricals, abductor hallucis | Tibial |
Distinguish incomplete from complete palsy
- Predominantly peroneal division palsy: dorsiflexion, toe extension, and eversion weak; plantarflexion and inversion relatively preserved.
- Complete sciatic palsy: weakness of hamstrings plus loss of dorsiflexion, eversion, plantarflexion, inversion, and toe movements.
D. Sensory examination
| Area | Main nerve |
|---|---|
| Lateral calf and dorsum of foot | Common peroneal division |
| First dorsal web space | Deep peroneal nerve |
| Sole of foot and heel | Tibial division |
| Posterolateral calf | Sural contribution |
E. Reflexes and special tests
- Ankle jerk: reduced or absent in tibial-division/sciatic involvement.
- Knee jerk: usually preserved because the femoral nerve is intact.
- Straight-leg raise may be positive if there is an associated radicular lesion.
- Examine the lumbar spine, hip, pelvis, and common peroneal nerve at the fibular neck.
F. Differentiate sciatic palsy from common mimics
| Finding | Sciatic nerve palsy | Common peroneal palsy | L5 radiculopathy |
|---|---|---|---|
| Dorsiflexion | Weak | Weak | Weak |
| Eversion | Weak | Weak | Weak |
| Inversion | May be weak in complete palsy | Usually preserved | Often weak |
| Plantarflexion | Weak in complete palsy | Preserved | Usually preserved or variably weak |
| Hamstrings | May be weak | Preserved | May be weak |
| Sole sensation | Reduced in complete palsy | Preserved | May be altered |
| Ankle reflex | May be lost | Preserved | Often preserved, unless S1 involved |
3. Deformities
A. Foot drop
- Plantarflexed ankle during swing
- Toe dragging
- Steppage gait
- Foot slap at heel strike
B. Equinovarus deformity
- Equinus from unopposed Achilles tendon
- Inversion/varus from unopposed tibialis posterior
- Lateral border overload and recurrent ankle instability
C. Calcaneus or calcaneovalgus deformity
- Excessive ankle dorsiflexion during stance
- Weak push-off
- Heel overload
- Knee may fall into flexion during stance due to loss of plantarflexion control
D. Cavus/cavovarus
- High arch
- Plantar-flexed first ray
- Hindfoot varus
- Claw toes
- Callosities under metatarsal heads and lateral foot border
E. Claw toes
- Hyperextension at metatarsophalangeal joints
- Flexion at interphalangeal joints
- Dorsal toe pressure in footwear and painful corns
4. Investigations
- Serial clinical examination and muscle charting: most important to document recovery.
- EMG and nerve-conduction studies: help localize lesion, determine severity, identify denervation/reinnervation, and distinguish sciatic neuropathy from root/plexus disease. These are usually informative after approximately 3-4 weeks from injury.
- X-rays: hip/pelvis and foot/ankle as indicated after trauma or for established deformity.
- Ultrasound or MRI neurography: for nerve continuity, hematoma, scar, mass, entrapment, or focal compression.
- CT: particularly useful after acetabular or hip surgery when hardware or fracture fragments could be impinging on the nerve.
5. Treatment
A. Acute sciatic palsy
Immediate measures
- Identify and treat the cause.
- Document motor and sensory status before and after any reduction or surgery.
- Maintain the ankle in neutral with a posterior splint or AFO.
- Protect the anaesthetic foot from heat, pressure sores, and injury.
- Analgesia and treatment of neuropathic pain if present.
- Physiotherapy to maintain range of motion and prevent equinus contracture.
Indications for urgent exploration/decompression
- Open injury or penetrating trauma
- Suspected nerve laceration
- Entrapment by fracture fragment
- Expanding hematoma
- New palsy after hip surgery with suspected hardware, cement, lengthening, or compression
- Progressive severe neurologic deficit
- A compressive mass identified on imaging
B. Conservative management during nerve recovery
Orthosis
- AFO is first-line for foot drop.
- A solid AFO is useful when there is significant ankle instability or combined tibial and peroneal weakness.
- An articulated AFO may be appropriate if plantarflexion strength/control is adequate.
- Custom footwear and accommodative insoles for callosity or cavus.
Physiotherapy
- Maintain passive ankle dorsiflexion, subtalar movement, and toe mobility.
- Strengthen recovering muscles without over-fatiguing them.
- Gait training, balance training, and fall prevention.
- Electrical stimulation may be used in selected rehabilitation programs, though it does not replace reinnervation or tendon transfer.
C. Nerve repair or reconstruction
- Primary nerve repair, when clean ends can be approximated without tension
- Nerve grafting if a gap prevents direct repair
- Neurolysis/decompression for selected scarred or compressed nerves
- Nerve transfer in specialized peripheral nerve centers
6. Treatment of established foot deformity
Principle
- Contracture
- Bony deformity
- Muscle imbalance
A. Flexible foot drop
- AFO if adequate function is achieved with bracing.
- Tendon transfer if there is no meaningful recovery and a suitable functioning donor muscle is present.
Tendon transfer
- The foot is supple and can reach neutral
- Posterior tibial tendon is strong enough, generally MRC grade 4 or more
- There is no major fixed equinus, cavus, or varus
- The patient has adequate rehabilitation potential
B. Flexible equinovarus
- Stretching/casting if early
- Tendo-Achilles or gastrocnemius lengthening only for a true fixed equinus contracture
- Selective tendon balancing if a functioning donor exists
- Orthosis if no donor muscle is available
C. Fixed cavovarus or equinovarus
- Plantar fascia release for fixed cavus if needed
- Achilles/gastrocnemius lengthening for fixed equinus
- Calcaneal osteotomy for fixed hindfoot varus/valgus
- First-ray dorsiflexion osteotomy for a plantar-flexed first ray
- Midfoot osteotomy for major structural cavus/adduction
D. Severe rigid, painful, unstable, or unbraceable foot
- Subtalar or triple arthrodesis may create a stable plantigrade foot.
- Ankle arthrodesis is reserved for exceptional severe ankle instability, deformity, or painful arthrosis.
- Fusion provides stability but sacrifices movement and should follow careful assessment of knee strength, contralateral limb function, and gait needs.
Exam summary
Sciatic nerve palsy is examined by assessing gait, hamstring function, ankle and toe movements, sensory loss over the dorsum and sole of the foot, ankle jerk, and associated hip/spine pathology. Common deformities include foot drop, equinovarus, cavovarus, calcaneus/calcaneovalgus, and claw toes. Acute compression or laceration requires prompt identification and possible nerve exploration. During recovery, treatment consists of splintage/AFO, physiotherapy, skin protection, and serial EMG. In established palsy, flexible deformity is treated by contracture release and selected tendon transfer where a strong donor exists; fixed deformity requires osteotomy, while severe rigid unbraceable deformity may need arthrodesis.
Hip extension flexion abduction knee flexion extension ankle flexion extension toe flexion extension root values
lower limb myotomes examination
lower limb myotomes hip flexion knee extension ankle dorsiflexion toe extension root values
Lower-limb movements and root values
| Movement | Main muscle(s) | Root value(s) | Key root for clinical testing |
|---|---|---|---|
| Hip flexion | Iliopsoas | L1-L3 | L2 |
| Hip extension | Gluteus maximus, hamstrings | L5-S2 | L5-S1 |
| Hip abduction | Gluteus medius and minimus | L4-S1 | L5 |
| Knee extension | Quadriceps | L2-L4 | L3-L4 |
| Knee flexion | Hamstrings | L5-S2 | S1 |
| Ankle dorsiflexion | Tibialis anterior | L4-L5 | L4 |
| Ankle plantarflexion | Gastrocnemius, soleus | S1-S2 | S1 |
| Great-toe extension | Extensor hallucis longus | L5 | L5 |
| Toe extension | Extensor digitorum longus/brevis | L5-S1 | L5 |
| Great-toe flexion | Flexor hallucis longus/brevis | S1-S2 | S2 |
| Lesser-toe flexion | Flexor digitorum longus/brevis | S1-S2 | S2 |
Quick myotome sequence for examination
- L2: hip flexion
- L3: knee extension
- L4: ankle dorsiflexion
- L5: great-toe extension
- S1: ankle plantarflexion
- S2: knee flexion and toe flexion
Skyline view merchants view
patellofemoral radiography Merchant view
Merchant skyline patellofemoral radiographic view technique indications
Skyline view / Merchant view of the knee
Position and technique
- Patient is usually supine or semi-recumbent.
- Both knees are flexed, commonly around 45° for the classic Merchant technique.
- X-ray beam is directed tangentially through the patellofemoral joints, classically about 30° caudad from horizontal.
- Both knees are often imaged together for comparison.
What it shows
- Patellofemoral joint space
- Patellar tilt
- Lateral patellar subluxation/displacement
- Trochlear dysplasia, including a shallow trochlear sulcus
- Patellar fracture, especially vertical fracture
- Patellofemoral osteoarthritis: joint-space narrowing, osteophytes, sclerosis
- Bipartite patella and separation at the bipartite site
Indications
- Recurrent patellar dislocation or instability
- Anterior knee pain / suspected patellofemoral disorder
- Suspected patellar maltracking, tilt, or subluxation
- Patellofemoral osteoarthritis
- Suspected patellar fracture
Terms
- Skyline view = general name for tangential/axial patellofemoral view.
- Merchant view = a specific standardized bilateral skyline projection.
- Sunrise view = often used interchangeably with skyline view, though exact patient position and beam angle vary by technique.
Different views and their angles
patellar skyline views Merchant Laurin Settegast Hughston angles knee flexion x ray
patellar axial radiography Merchant Laurin
Patellar axial (skyline/sunrise) views and angles
| View | Patient / knee position | Knee flexion | Central-ray angle | Main use |
|---|---|---|---|---|
| Merchant view | Supine, both knees flexed over a dedicated support | 45° | 30° caudad from horizontal toward the patella | Standard bilateral patellofemoral assessment: patellar tilt, subluxation, trochlear morphology, patellofemoral OA |
| Laurin view | Semi-recumbent, knee flexed; detector held above knee | 20° | 30° from horizontal, inferosuperior through patellofemoral joint | Detects subtle patellar tilt, lateral subluxation, and early maltracking because it is taken in relatively low flexion |
| Settegast view | Prone or sitting, knee flexed maximally, often difficult/painful after trauma | About 90-105° | Beam tangential to patellofemoral joint, commonly about 15-20° to the long axis of lower leg, adjusted to flexion | Patellar fracture, particularly vertical fracture; patellofemoral joint assessment |
| Hughston view | Prone, knee flexed around 55°; beam directed from posterior | 55° | About 45° cephalad to lower leg | Patellofemoral articulation and patellar tracking |
| Knutsson view | Usually sitting/semi-recumbent | 30-40° | Beam directed tangentially, generally around 15-20° depending on knee flexion | Patellofemoral alignment and joint space |
| Sunrise / Skyline view | Generic term, not one single standardized technique | Usually 20-45° | Depends on the specific method used | General axial evaluation of patella and trochlea |
High-yield exam points
- Merchant: knee flexion 45°, X-ray beam 30° caudad.
- Laurin: knee flexion 20°, useful for subtle lateral patellar maltracking.
- Settegast: knee flexion 90-105°, useful for patellar fracture.
- For patellofemoral instability, lower flexion views such as Laurin can reveal maltracking better, because greater flexion tends to reduce the patella into the trochlea.
Beighton score
Beighton score joint hypermobility
Beighton score 9 points criteria 2017 hypermobile Ehlers Danlos
Beighton score
Scoring: total = 9 points
| Test | Score |
|---|---|
| Passive dorsiflexion of the little finger beyond 90° - right | 1 |
| Passive dorsiflexion of the little finger beyond 90° - left | 1 |
| Passive apposition of the thumb to the flexor aspect of forearm - right | 1 |
| Passive apposition of the thumb to the flexor aspect of forearm - left | 1 |
| Elbow hyperextension beyond 10° - right | 1 |
| Elbow hyperextension beyond 10° - left | 1 |
| Knee hyperextension beyond 10° - right | 1 |
| Knee hyperextension beyond 10° - left | 1 |
| With knees straight, place both palms flat on the floor on forward bending | 1 |
Interpretation
- Children and adolescents: ≥ 6/9
- Adults aged 18-50 years: ≥ 5/9
- Adults over 50 years: ≥ 4/9
Important limitation
Lateral condyle humerus fracture classification
pediatric lateral condyle humerus fracture classification
pediatric lateral humeral condyle fracture classification Milch Jakob Song
Lateral humeral condyle fracture in children: classifications
1. Milch classification
| Type | Fracture line | Stability |
|---|---|---|
| Milch I | Passes lateral to the trochlear groove, through the lateral part of the trochlea/ossific nucleus | Usually more stable because the trochlea remains intact |
| Milch II | Passes medially into or through the trochlear groove | More common and potentially unstable because trochlear integrity is disrupted |
2. Jakob classification
| Stage | Displacement / appearance | Cartilage hinge and rotation |
|---|---|---|
| Jakob I | < 2 mm displacement | Intact cartilaginous hinge, stable |
| Jakob II | 2-4 mm displacement | Articular disruption may be present, but no fragment rotation |
| Jakob III | > 4 mm displacement | Fragment is completely displaced and usually rotated, unstable |
- Stage I: often managed in cast with close radiographic follow-up.
- Stage II and III: usually need fixation after confirming articular reduction.
3. Weiss classification
| Type | Displacement | Articular surface | Usual management principle |
|---|---|---|---|
| Weiss I | < 2 mm | Intact | Cast and close follow-up |
| Weiss II | > 2 mm, usually <4 mm | Intact cartilage hinge/articular surface | Closed reduction and percutaneous fixation may be possible |
| Weiss III | > 2 mm, often >4 mm | Articular surface disrupted | Open reduction and internal fixation generally required |
4. Song classification
| Stage | Description |
|---|---|
| Song 1 | ≤2 mm displacement, metaphyseal fracture line, stable |
| Song 2 | ≤2 mm displacement, extends toward cartilage, stability uncertain |
| Song 3 | ≤2 mm displacement but fracture line reaches articular surface, unstable |
| Song 4 | >2 mm displacement without rotation, unstable |
| Song 5 | >2 mm displacement with rotation, grossly unstable |
High-yield summary
- Milch = fracture line relative to trochlea.
- Jakob = displacement and rotation.
- Weiss = displacement plus articular congruity, useful for treatment.
- Song = radiographic stability, especially in minimally displaced fractures.
Timing for surgery in cubitus varus and valgus
cubitus varus osteotomy children timing
cubitus varus cubitus valgus corrective osteotomy timing child lateral condyle nonunion tardy ulnar palsy
Timing of surgery in cubitus varus and cubitus valgus
1. Cubitus varus
When to operate
- Significant cosmetic deformity unacceptable to child/family
- Functional limitation, elbow pain, or instability
- Progressive deformity due to growth disturbance
- Associated rotational deformity or hyperextension that is clinically important
- Recurrent lateral condyle fracture or posterolateral rotatory instability
Timing
- Not an emergency.
- Allow the original fracture to unite and elbow motion to recover first.
- Corrective osteotomy is usually done after about 6-12 months from injury, once the deformity is established and range of motion has returned.
- It can be performed in childhood when indicated. Earlier correction, once motion is recovered, may be technically easier and may avoid a long period of cosmetic concern.
- It does not have to wait until skeletal maturity if the deformity is substantial or symptomatic.
- Mild, asymptomatic deformity can be observed.
2. Cubitus valgus
When to operate
- Tardy ulnar neuropathy: paresthesia in ring/little fingers, intrinsic hand weakness or wasting, clawing
- Progressive or marked valgus deformity, often approximately >20° or clearly greater than the opposite side
- Pain, elbow instability, loss of function, or unacceptable cosmesis
- Symptomatic lateral condyle nonunion
Timing
- Cubitus valgus without symptoms: observe if mild and non-progressive. Corrective osteotomy may be planned electively once the deformity is established, particularly for a large cosmetic deformity.
- Valgus with symptomatic lateral condyle nonunion: treat when diagnosed, rather than waiting for skeletal maturity. Treatment may include fixation and bone grafting of the nonunion, with or without valgus corrective osteotomy.
- Tardy ulnar nerve palsy: operate promptly after diagnosis, because recovery becomes less predictable once denervation and intrinsic muscle wasting are longstanding. Treatment usually includes ulnar nerve decompression/anterior transposition, and correction of marked valgus by supracondylar osteotomy where indicated.
- In an older child, adolescent, or adult with a longstanding rigid deformity, corrective osteotomy can still be done if symptoms or major deformity justify it.
Comparison
| Feature | Cubitus varus | Cubitus valgus |
|---|---|---|
| Usual cause | Supracondylar humeral fracture malunion | Lateral condyle fracture nonunion/malunion |
| Main reason for surgery | Cosmetic deformity, instability, functional symptoms | Tardy ulnar palsy, marked deformity, nonunion, pain/instability |
| Urgency | Elective after union and return of motion | Elective if asymptomatic; prompt if ulnar neuropathy or symptomatic nonunion |
| Typical timing | About 6-12 months after injury, once deformity is established | At diagnosis of symptomatic nonunion or tardy ulnar palsy; otherwise elective |
| Typical operation | Corrective distal humeral osteotomy | Corrective osteotomy ± lateral condyle nonunion fixation/bone grafting ± ulnar nerve transposition |
Cubitus varus correction is an elective corrective osteotomy after fracture union and recovery of elbow movement, usually around 6-12 months after injury if the deformity is cosmetically or functionally significant. Cubitus valgus is observed if mild and asymptomatic, but should be corrected when severe, associated with lateral condyle nonunion, or when tardy ulnar nerve palsy develops.
Clinical how to test lateral condyle humerus non union
clinical examination lateral humeral condyle nonunion child elbow instability cubitus valgus
Clinical examination for suspected lateral humeral condyle nonunion
1. Inspection
- Cubitus valgus: increased carrying angle compared with the other side
- Prominent or proximally migrated lateral condyle
- Lateral elbow fullness/deformity
- Muscle wasting of the hand, especially hypothenar and interossei, suggesting late ulnar neuropathy
- Scars of old injury or surgery
2. Palpation
- Palpate the lateral condyle and radiocapitellar region for:
- Local tenderness
- Irregular bony prominence
- A palpable gap or abnormal mobility over the old fracture site
- In a mobile nonunion, gentle pressure over the lateral condyle during elbow movement may reproduce pain or reveal motion at the pseudarthrosis. Do not force this manoeuvre.
3. Range of movement
- Flexion and extension
- Pronation and supination
4. Test elbow stability
- A lateral condyle nonunion can produce lateral instability and abnormal valgus/varus movement.
- Pain, apprehension, or increased movement during stress testing supports instability, but a normal stress test does not exclude nonunion.
5. Ulnar nerve examination: essential
- Tingling or numbness in the little finger and ulnar half of ring finger
- Weak grip or poor hand dexterity
- Progressive clawing of ring and little fingers
- Sensation over the little finger and ulnar side of ring finger
- First dorsal interosseous and hypothenar wasting
- Finger abduction/adduction
- Froment sign and Wartenberg sign
- Tinel sign at the cubital tunnel
- Ulnar nerve subluxation during elbow flexion
6. Neurovascular examination
- Radial pulse and capillary refill
- Median, radial, and ulnar nerve motor and sensory function
Examination finding summary
“Old lateral elbow injury with increased carrying angle/cubitus valgus, lateral condylar prominence and tenderness, painful or unstable elbow on stress testing, and assess specifically for tardy ulnar nerve palsy.”
Confirmation
Instruments used in anterolateral decompression of spine with images
anterolateral spinal decompression surgical instruments curette pituitary rongeur high speed burr Kerrison rongeur
anterolateral decompression spine instruments curette pituitary rongeur Kerrison high speed drill
Instruments used for anterolateral decompression of spine
Core instrument set
| Instrument | Main use |
|---|---|
| Scalpel with No. 10/15 blade | Skin incision and soft-tissue dissection |
| Artery forceps, sponge holder, suction | Haemostasis, swab handling, clearance of blood/debris |
| Periosteal elevator | Subperiosteal elevation from rib, vertebral body, and transverse process |
| Rib cutter / rib shears | Resection of a segment of rib when a costotransverse approach is used |
| Rib raspatory / Doyen raspatory | Elevation of periosteum and protection of pleura around the rib |
| Cobb elevator / broad periosteal elevator | Deep exposure and soft-tissue elevation |
| Self-retaining retractor, such as Gelpi or rib spreader where needed | Maintains the surgical corridor |
| Hohmann retractors | Retract paraspinal soft tissues and protect adjacent structures |
| Finochietto rib spreader | Used only if thoracotomy exposure is required |
| Bone-holding forceps | Hold rib or bony fragments during resection |
| Leksell rongeur / bone nibblers | Remove posterior rib, transverse process, pedicle, and cancellous bone |
| Kerrison rongeur | Controlled removal of small bone portions near the spinal canal, especially the posterior lip or residual compressive bone |
| Osteotomes and mallet | Remove bone, pedicle, or diseased vertebral elements in a controlled fashion |
| High-speed burr with diamond burr | Controlled bony decompression and smoothing of residual bone, particularly near neural structures |
| Curettes, straight and angled | Remove caseous material, granulation tissue, disc material, and necrotic cancellous bone |
| Penfield dissectors / angled dissectors | Gentle separation of epidural granulation tissue from the dura |
| Pituitary rongeur | Remove loose disc, pus debris, caseous material, and granulation tissue from a deep cavity |
| Disc forceps | Removal of disc material where disc-space debridement is required |
| Nerve root retractor / dural dissector | Neural tissue protection during final decompression, when required |
| Suction cannula, including fine Frazier-type suction | Maintains visualization and removes pus/debris |
| C-arm fluoroscopy | Confirms spinal level and guides instrumentation, if stabilization is performed |
| Pedicle screw and rod system | Posterior stabilization, often combined with anterolateral decompression in unstable disease |
| Titanium mesh cage / structural graft instruments | Anterior column reconstruction when significant vertebral-body loss exists |
Instrument recognition
1. Kerrison rongeur
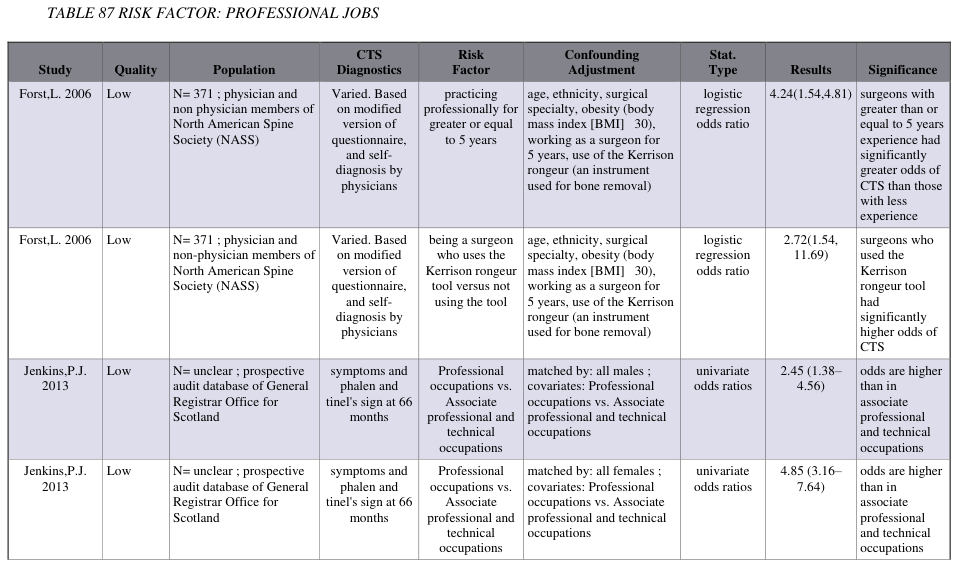
2. Pituitary rongeur
3. Curettes
- Straight curette: debrides accessible disc and vertebral-body cavity.
- Angled/ring curette: removes material from corners of a cavity while avoiding excessive traction on the dura.
4. Leksell rongeur
5. High-speed burr
High-yield operative sequence and instruments
| Step | Common instruments |
|---|---|
| Exposure through costotransverse/anterolateral route | Scalpel, periosteal elevator, retractors, rib cutter, rib raspatory |
| Remove posterior rib/transverse process and gain access | Leksell rongeur, osteotome, mallet, Kerrison |
| Debride abscess, caseation, granulation tissue, and disc | Suction, curettes, pituitary rongeur, disc forceps |
| Decompress anterior epidural compression | Angled curette, Penfield dissector, Kerrison, high-speed burr |
| Reconstruct/stabilize if needed | Cage/graft instruments, pedicle screws, rods, C-arm |
Safety points
- The goal is adequate anterior decompression without dural traction or cord manipulation.
- Do not use a Kerrison or curette blindly within the canal.
- Protect the pleura, segmental vessels, dura, and nerve roots.
- In tuberculous spine, obtain tissue for histopathology, AFB testing, culture, and molecular testing when feasible.
- Surgical approach, extent of debridement, and need for reconstruction depend on spinal level, neurological status, instability, kyphosis, and disease extent.
Create a one-page instrument identification PDF
~/
mkdir -p "/tmp/workspace/anterolateral-spine-instruments-pdf/src" "/tmp/workspace/anterolateral-spine-instruments-pdf/output" && python - <<'PY' from reportlab.lib.pagesizes import A4 from reportlab.lib import colors from reportlab.lib.colors import HexColor from reportlab.lib.units import mm from reportlab.pdfgen import canvas from reportlab.pdfbase.pdfmetrics import stringWidth from pypdf import PdfReader import os out='/tmp/workspace/anterolateral-spine-instruments-pdf/output/Anterolateral_Spine_Decompression_Instruments.pdf' W,H=A4 navy=HexColor('#14394D'); teal=HexColor('#087F82'); light=HexColor('#F3F7F8'); line=HexColor('#B7CDD0'); ink=HexColor('#1D2B34'); gray=HexColor('#5D6D75'); amber=HexColor('#FFF2D2') c=canvas.Canvas(out,pagesize=A4) c.setTitle('Anterolateral Spine Decompression: Instrument Identification') # Header c.setFillColor(navy); c.rect(0,H-35*mm,W,35*mm,fill=1,stroke=0) c.setFillColor(colors.white); c.setFont('Helvetica-Bold',18); c.drawString(15*mm,H-16*mm,'ANTEROLATERAL SPINE DECOMPRESSION') c.setFont('Helvetica',9.2); c.drawString(15*mm,H-23*mm,'One-page instrument identification guide | Educational reference') c.setFillColor(HexColor('#BCE6E4')); c.setFont('Helvetica-Bold',8); c.drawRightString(W-15*mm,H-16*mm,'THORACIC / THORACOLUMBAR') # brief bar c.setFillColor(amber); c.roundRect(15*mm,H-47*mm,W-30*mm,7*mm,2*mm,fill=1,stroke=0) c.setFillColor(ink); c.setFont('Helvetica-Bold',7.7); c.drawString(18*mm,H-43*mm,'Aim: expose safely, remove bone and anterior compressive material, protect neural tissue, then reconstruct/stabilize when indicated.') # drawings in cells def label(x,y,name,tag,lines,kind): cw=57*mm; ch=49*mm c.setFillColor(light); c.roundRect(x,y,cw,ch,3*mm,fill=1,stroke=0) c.setStrokeColor(line); c.roundRect(x,y,cw,ch,3*mm,fill=0,stroke=1) # picture panel px=x+5*mm; py=y+22*mm; pw=cw-10*mm; ph=21*mm c.setFillColor(colors.white); c.roundRect(px,py,pw,ph,2*mm,fill=1,stroke=0) c.setStrokeColor(HexColor('#D5E2E5')); c.roundRect(px,py,pw,ph,2*mm,fill=0,stroke=0.5) draw_inst(px,py,pw,ph,kind) c.setFillColor(navy); c.setFont('Helvetica-Bold',9.2); c.drawString(x+5*mm,y+16.5*mm,name) c.setFillColor(teal); c.setFont('Helvetica-Bold',6.5); c.drawRightString(x+cw-5*mm,y+16.5*mm,tag.upper()) c.setFillColor(gray); c.setFont('Helvetica',6.7) ty=y+12*mm for s in lines: c.drawString(x+5*mm,ty,s); ty-=3.5*mm def draw_inst(x,y,w,h,k): c.setStrokeColor(navy); c.setFillColor(HexColor('#D9E9EA')); c.setLineWidth(1.4) cy=y+h/2 if k=='kerrison': # handle rings & shaft angled jaw c.circle(x+9*mm,cy+4*mm,3.1*mm,fill=0); c.circle(x+9*mm,cy-4*mm,3.1*mm,fill=0) c.line(x+12*mm,cy+3*mm,x+25*mm,cy+1.3*mm);c.line(x+12*mm,cy-3*mm,x+25*mm,cy-1.3*mm) c.rect(x+25*mm,cy-2*mm,17*mm,4*mm,fill=1);c.line(x+42*mm,cy,x+45*mm,cy+4*mm);c.line(x+45*mm,cy+4*mm,x+47*mm,cy+4*mm) elif k=='pituitary': c.circle(x+8*mm,cy+3.8*mm,2.7*mm,fill=0);c.circle(x+8*mm,cy-3.8*mm,2.7*mm,fill=0) c.line(x+11*mm,cy+2.8*mm,x+26*mm,cy+1.2*mm);c.line(x+11*mm,cy-2.8*mm,x+26*mm,cy-1.2*mm) c.rect(x+26*mm,cy-1.7*mm,16*mm,3.4*mm,fill=1); c.setFillColor(HexColor('#B5D7D9')); c.circle(x+45*mm,cy,3*mm,fill=1) elif k=='curette': c.roundRect(x+5*mm,cy-3*mm,14*mm,6*mm,2*mm,fill=1); c.line(x+19*mm,cy,x+43*mm,cy) c.arc(x+41*mm,cy-3*mm,x+48*mm,cy+5*mm,0,240); c.line(x+43*mm,cy,x+46*mm,cy+3*mm) elif k=='leksell': c.circle(x+8*mm,cy+4*mm,3*mm,fill=0);c.circle(x+8*mm,cy-4*mm,3*mm,fill=0) c.line(x+11*mm,cy+3*mm,x+27*mm,cy+1.5*mm);c.line(x+11*mm,cy-3*mm,x+27*mm,cy-1.5*mm) c.rect(x+27*mm,cy-3*mm,12*mm,6*mm,fill=1); c.setFillColor(HexColor('#B5D7D9'));c.rect(x+39*mm,cy-4*mm,7*mm,8*mm,fill=1) elif k=='burr': c.roundRect(x+5*mm,cy-4*mm,16*mm,8*mm,2*mm,fill=1);c.line(x+21*mm,cy,x+41*mm,cy);c.setFillColor(HexColor('#B5D7D9'));c.circle(x+45*mm,cy,4*mm,fill=1) c.setStrokeColor(teal);c.line(x+11*mm,cy+4*mm,x+11*mm,cy+9*mm) elif k=='osteotome': c.rect(x+5*mm,cy-5*mm,12*mm,10*mm,fill=1);c.line(x+17*mm,cy,x+42*mm,cy);c.setFillColor(HexColor('#B5D7D9'));c.wedge(x+42*mm,cy-4*mm,x+50*mm,cy+4*mm,180,360,fill=1) elif k=='retractor': c.setLineWidth(2);c.line(x+9*mm,cy,x+37*mm,cy);c.line(x+9*mm,cy,x+9*mm,cy+7*mm);c.line(x+37*mm,cy,x+43*mm,cy+7*mm);c.line(x+43*mm,cy+7*mm,x+48*mm,cy+7*mm) elif k=='suction': c.setLineWidth(2);c.line(x+5*mm,cy,x+35*mm,cy);c.line(x+35*mm,cy,x+45*mm,cy+5*mm);c.setFillColor(HexColor('#B5D7D9'));c.circle(x+47*mm,cy+6*mm,1.8*mm,fill=1) cols=[15*mm,76*mm,137*mm] # rows y positions rows=[H-105*mm,H-159*mm,H-213*mm] items=[ ('Kerrison rongeur','BONE','Fine controlled bone removal near canal.','Angled biting jaws; not used blindly.' ,'kerrison'), ('Pituitary rongeur','SOFT TISSUE','Grasps loose disc, caseation and debris.','Cupped jaws: not for dense cortical bone.','pituitary'), ('Angled ring curette','DEBRIDEMENT','Removes disc, granulation and necrotic bone.','Work under direct vision, away from dura.','curette'), ('Leksell rongeur','BONE','Removes rib, transverse process, cancellous bone.','Heavy rongeur for bulk bony removal.','leksell'), ('High-speed burr','BONE','Thins residual posterior vertebral cortex.','Diamond burr preferred near neural tissue.','burr'), ('Osteotome + mallet','BONE','Controlled osteotomy and bony resection.','Protect pleura, vessels and dura before use.','osteotome'), ('Hohmann / deep retractor','EXPOSURE','Maintains deep corridor and retracts tissue.','Place on bone and avoid sustained neural pressure.','retractor'), ('Frazier suction','VISUALIZATION','Clears blood, pus and fine debris.','Fine tip permits controlled deep suction.','suction'), ] for idx,it in enumerate(items): r=idx//3;cidx=idx%3 # last row only 2 label(cols[cidx],rows[r],*it) # safety / workflow footer c.setFillColor(navy);c.roundRect(15*mm,14*mm,W-30*mm,18*mm,2*mm,fill=1,stroke=0) c.setFillColor(colors.white);c.setFont('Helvetica-Bold',8.3);c.drawString(19*mm,25*mm,'RECOGNITION PEARLS') c.setFont('Helvetica',7.4);c.drawString(19*mm,20*mm,'Kerrison = fine biting bone punch | Pituitary = cupped tissue grasper | Curette = scraping/debridement | Leksell = bulk bone rongeur') c.setFillColor(HexColor('#CAEDEC'));c.setFont('Helvetica-Oblique',6.7);c.drawString(15*mm,8*mm,'Educational instrument-recognition aid. Instrument selection and surgical use require formal training, supervision, and local protocol.') c.save() r=PdfReader(out) print('pages',len(r.pages),'bytes',os.path.getsize(out)) print(r.pages[0].extract_text()[:180]) PY
python - <<'PY' from reportlab.lib.pagesizes import A4 from reportlab.lib import colors from reportlab.lib.colors import HexColor from reportlab.lib.units import mm from reportlab.pdfgen import canvas from pypdf import PdfReader import os out='/tmp/workspace/anterolateral-spine-instruments-pdf/output/Anterolateral_Spine_Decompression_Instruments.pdf' W,H=A4; navy=HexColor('#14394D'); teal=HexColor('#087F82'); light=HexColor('#F3F7F8'); line=HexColor('#B7CDD0'); ink=HexColor('#1D2B34'); gray=HexColor('#5D6D75'); amber=HexColor('#FFF2D2') c=canvas.Canvas(out,pagesize=A4); c.setTitle('Anterolateral Spine Decompression: Instrument Identification') c.setFillColor(navy); c.rect(0,H-35*mm,W,35*mm,fill=1,stroke=0) c.setFillColor(colors.white); c.setFont('Helvetica-Bold',18); c.drawString(15*mm,H-16*mm,'ANTEROLATERAL SPINE DECOMPRESSION') c.setFont('Helvetica',9.2); c.drawString(15*mm,H-23*mm,'One-page instrument identification guide | Educational reference') c.setFillColor(HexColor('#BCE6E4')); c.setFont('Helvetica-Bold',8); c.drawRightString(W-15*mm,H-16*mm,'THORACIC / THORACOLUMBAR') c.setFillColor(amber); c.roundRect(15*mm,H-47*mm,W-30*mm,7*mm,2*mm,fill=1,stroke=0) c.setFillColor(ink); c.setFont('Helvetica-Bold',7.7); c.drawString(18*mm,H-43*mm,'Aim: expose safely, remove bone and anterior compressive material, protect neural tissue, then reconstruct/stabilize when indicated.') def draw_inst(x,y,w,h,k): c.setStrokeColor(navy); c.setFillColor(HexColor('#D9E9EA')); c.setLineWidth(1.4); cy=y+h/2 if k=='kerrison': c.circle(x+9*mm,cy+4*mm,3.1*mm,fill=0); c.circle(x+9*mm,cy-4*mm,3.1*mm,fill=0); c.line(x+12*mm,cy+3*mm,x+25*mm,cy+1.3*mm);c.line(x+12*mm,cy-3*mm,x+25*mm,cy-1.3*mm);c.rect(x+25*mm,cy-2*mm,17*mm,4*mm,fill=1);c.line(x+42*mm,cy,x+45*mm,cy+4*mm);c.line(x+45*mm,cy+4*mm,x+47*mm,cy+4*mm) elif k=='pituitary': c.circle(x+8*mm,cy+3.8*mm,2.7*mm,fill=0);c.circle(x+8*mm,cy-3.8*mm,2.7*mm,fill=0);c.line(x+11*mm,cy+2.8*mm,x+26*mm,cy+1.2*mm);c.line(x+11*mm,cy-2.8*mm,x+26*mm,cy-1.2*mm);c.rect(x+26*mm,cy-1.7*mm,16*mm,3.4*mm,fill=1);c.setFillColor(HexColor('#B5D7D9'));c.circle(x+45*mm,cy,3*mm,fill=1) elif k=='curette': c.roundRect(x+5*mm,cy-3*mm,14*mm,6*mm,2*mm,fill=1);c.line(x+19*mm,cy,x+43*mm,cy);c.arc(x+41*mm,cy-3*mm,x+48*mm,cy+5*mm,0,240);c.line(x+43*mm,cy,x+46*mm,cy+3*mm) elif k=='leksell': c.circle(x+8*mm,cy+4*mm,3*mm,fill=0);c.circle(x+8*mm,cy-4*mm,3*mm,fill=0);c.line(x+11*mm,cy+3*mm,x+27*mm,cy+1.5*mm);c.line(x+11*mm,cy-3*mm,x+27*mm,cy-1.5*mm);c.rect(x+27*mm,cy-3*mm,12*mm,6*mm,fill=1);c.setFillColor(HexColor('#B5D7D9'));c.rect(x+39*mm,cy-4*mm,7*mm,8*mm,fill=1) elif k=='burr': c.roundRect(x+5*mm,cy-4*mm,16*mm,8*mm,2*mm,fill=1);c.line(x+21*mm,cy,x+41*mm,cy);c.setFillColor(HexColor('#B5D7D9'));c.circle(x+45*mm,cy,4*mm,fill=1);c.setStrokeColor(teal);c.line(x+11*mm,cy+4*mm,x+11*mm,cy+9*mm) elif k=='osteotome': c.rect(x+5*mm,cy-5*mm,12*mm,10*mm,fill=1);c.line(x+17*mm,cy,x+42*mm,cy);c.setFillColor(HexColor('#B5D7D9'));c.wedge(x+42*mm,cy-4*mm,x+50*mm,cy+4*mm,180,360,fill=1) elif k=='retractor': c.setLineWidth(2);c.line(x+9*mm,cy,x+37*mm,cy);c.line(x+9*mm,cy,x+9*mm,cy+7*mm);c.line(x+37*mm,cy,x+43*mm,cy+7*mm);c.line(x+43*mm,cy+7*mm,x+48*mm,cy+7*mm) else: c.setLineWidth(2);c.line(x+5*mm,cy,x+35*mm,cy);c.line(x+35*mm,cy,x+45*mm,cy+5*mm);c.setFillColor(HexColor('#B5D7D9'));c.circle(x+47*mm,cy+6*mm,1.8*mm,fill=1) def label(x,y,name,tag,use,pearl,kind): cw=57*mm;ch=49*mm;c.setFillColor(light);c.roundRect(x,y,cw,ch,3*mm,fill=1,stroke=0);c.setStrokeColor(line);c.roundRect(x,y,cw,ch,3*mm,fill=0,stroke=1) px=x+5*mm;py=y+22*mm;pw=cw-10*mm;ph=21*mm;c.setFillColor(colors.white);c.roundRect(px,py,pw,ph,2*mm,fill=1,stroke=0);c.setStrokeColor(HexColor('#D5E2E5'));c.roundRect(px,py,pw,ph,2*mm,fill=0,stroke=0.5);draw_inst(px,py,pw,ph,kind) c.setFillColor(navy);c.setFont('Helvetica-Bold',9.2);c.drawString(x+5*mm,y+16.5*mm,name);c.setFillColor(teal);c.setFont('Helvetica-Bold',6.5);c.drawRightString(x+cw-5*mm,y+16.5*mm,tag.upper());c.setFillColor(gray);c.setFont('Helvetica',6.7);c.drawString(x+5*mm,y+12*mm,use);c.drawString(x+5*mm,y+8.5*mm,pearl) cols=[15*mm,76*mm,137*mm];rows=[H-105*mm,H-159*mm,H-213*mm] items=[('Kerrison rongeur','BONE','Fine controlled bone removal near canal.','Angled biting jaws; not used blindly.','kerrison'),('Pituitary rongeur','SOFT TISSUE','Grasps loose disc, caseation and debris.','Cupped jaws: not for dense cortical bone.','pituitary'),('Angled ring curette','DEBRIDEMENT','Removes disc, granulation and necrotic bone.','Work under direct vision, away from dura.','curette'),('Leksell rongeur','BONE','Removes rib, transverse process, cancellous bone.','Heavy rongeur for bulk bony removal.','leksell'),('High-speed burr','BONE','Thins residual posterior vertebral cortex.','Diamond burr preferred near neural tissue.','burr'),('Osteotome + mallet','BONE','Controlled osteotomy and bony resection.','Protect pleura, vessels and dura first.','osteotome'),('Hohmann / deep retractor','EXPOSURE','Maintains deep corridor and retracts tissue.','Place on bone; avoid neural pressure.','retractor'),('Frazier suction','VISUALIZATION','Clears blood, pus and fine debris.','Fine tip permits controlled deep suction.','suction')] for i,it in enumerate(items): label(cols[i%3],rows[i//3],*it) c.setFillColor(navy);c.roundRect(15*mm,14*mm,W-30*mm,18*mm,2*mm,fill=1,stroke=0);c.setFillColor(colors.white);c.setFont('Helvetica-Bold',8.3);c.drawString(19*mm,25*mm,'RECOGNITION PEARLS');c.setFont('Helvetica',7.4);c.drawString(19*mm,20*mm,'Kerrison = fine biting bone punch | Pituitary = cupped tissue grasper | Curette = scraping/debridement | Leksell = bulk bone rongeur');c.setFillColor(HexColor('#CAEDEC'));c.setFont('Helvetica-Oblique',6.7);c.drawString(15*mm,8*mm,'Educational instrument-recognition aid. Instrument selection and surgical use require formal training, supervision, and local protocol.');c.save() r=PdfReader(out); print('pages',len(r.pages),'bytes',os.path.getsize(out));print(r.pages[0].extract_text()[:240]) PY
python - <<'PY' from reportlab.pdfgen import canvas from reportlab.lib.pagesizes import A4 from reportlab.lib.units import mm from reportlab.lib import colors from reportlab.lib.colors import HexColor from pypdf import PdfReader import os p='/tmp/workspace/anterolateral-spine-instruments-pdf/output/Anterolateral_Spine_Decompression_Instruments.pdf' W,H=A4 navy=HexColor('#14394D'); teal=HexColor('#087F82'); light=HexColor('#F3F7F8'); border=HexColor('#B7CDD0'); gray=HexColor('#53646D'); amber=HexColor('#FFF2D2') c=canvas.Canvas(p,pagesize=A4); c.setTitle('Anterolateral Spine Decompression Instrument Identification') c.setFillColor(navy);c.rect(0,H-35*mm,W,35*mm,fill=1,stroke=0) c.setFillColor(colors.white);c.setFont('Helvetica-Bold',17);c.drawString(15*mm,H-16*mm,'ANTEROLATERAL SPINE DECOMPRESSION') c.setFont('Helvetica',9);c.drawString(15*mm,H-23*mm,'One-page instrument identification guide | Thoracic and thoracolumbar procedures') c.setFillColor(amber);c.roundRect(15*mm,H-47*mm,W-30*mm,7*mm,2*mm,fill=1,stroke=0) c.setFillColor(navy);c.setFont('Helvetica-Bold',7.5);c.drawString(18*mm,H-43*mm,'Aim: safe exposure, removal of bone and anterior compressive material, neural protection, and reconstruction when indicated.') def instrument_icon(x,y,w,h,typ): cy=y+h/2;c.setStrokeColor(navy);c.setFillColor(HexColor('#D9E9EA'));c.setLineWidth(1.3) if typ in ('kerrison','pituitary','leksell'): c.circle(x+8*mm,cy+3.7*mm,2.6*mm,fill=0);c.circle(x+8*mm,cy-3.7*mm,2.6*mm,fill=0) c.line(x+11*mm,cy+2.7*mm,x+25*mm,cy+1.2*mm);c.line(x+11*mm,cy-2.7*mm,x+25*mm,cy-1.2*mm) c.rect(x+25*mm,cy-2*mm,15*mm,4*mm,fill=1) if typ=='kerrison': c.line(x+40*mm,cy,x+44*mm,cy+4*mm);c.line(x+44*mm,cy+4*mm,x+48*mm,cy+4*mm) elif typ=='pituitary': c.setFillColor(HexColor('#B7DCDE'));c.circle(x+45*mm,cy,3*mm,fill=1) else: c.setFillColor(HexColor('#B7DCDE'));c.rect(x+40*mm,cy-4*mm,7*mm,8*mm,fill=1) elif typ=='curette': c.roundRect(x+5*mm,cy-3*mm,14*mm,6*mm,2*mm,fill=1,stroke=0);c.line(x+19*mm,cy,x+42*mm,cy);c.arc(x+40*mm,cy-3*mm,x+48*mm,cy+5*mm,0,240) elif typ=='burr': c.roundRect(x+5*mm,cy-4*mm,16*mm,8*mm,2*mm,fill=1,stroke=0);c.line(x+21*mm,cy,x+41*mm,cy);c.setFillColor(HexColor('#B7DCDE'));c.circle(x+45*mm,cy,4*mm,fill=1) elif typ=='osteotome': c.rect(x+5*mm,cy-5*mm,12*mm,10*mm,fill=1);c.line(x+17*mm,cy,x+42*mm,cy);c.setFillColor(HexColor('#B7DCDE'));c.circle(x+46*mm,cy,4*mm,fill=1) elif typ=='retractor': c.setLineWidth(2);c.line(x+8*mm,cy,x+37*mm,cy);c.line(x+8*mm,cy,x+8*mm,cy+7*mm);c.line(x+37*mm,cy,x+43*mm,cy+7*mm);c.line(x+43*mm,cy+7*mm,x+49*mm,cy+7*mm) else: c.setLineWidth(2);c.line(x+5*mm,cy,x+36*mm,cy);c.line(x+36*mm,cy,x+46*mm,cy+5*mm);c.setFillColor(HexColor('#B7DCDE'));c.circle(x+48*mm,cy+6*mm,2*mm,fill=1) def card(x,y,name,category,use,tip,typ): cw,ch=57*mm,49*mm c.setFillColor(light);c.roundRect(x,y,cw,ch,3*mm,fill=1,stroke=0) c.setStrokeColor(border);c.roundRect(x,y,cw,ch,3*mm,fill=0,stroke=1) px,py,pw,ph=x+5*mm,y+22*mm,cw-10*mm,20*mm c.setFillColor(colors.white);c.roundRect(px,py,pw,ph,2*mm,fill=1,stroke=0) c.setStrokeColor(HexColor('#D6E3E5'));c.roundRect(px,py,pw,ph,2*mm,fill=0,stroke=1) instrument_icon(px,py,pw,ph,typ) c.setFillColor(navy);c.setFont('Helvetica-Bold',9);c.drawString(x+5*mm,y+16*mm,name) c.setFillColor(teal);c.setFont('Helvetica-Bold',6);c.drawRightString(x+cw-5*mm,y+16*mm,category) c.setFillColor(gray);c.setFont('Helvetica',6.6);c.drawString(x+5*mm,y+11.5*mm,use);c.drawString(x+5*mm,y+8*mm,tip) items=[ ('Kerrison rongeur','BONE','Fine controlled bone removal near canal.','Angled biting jaws: never use blindly.','kerrison'), ('Pituitary rongeur','SOFT TISSUE','Grasps loose disc, caseation and debris.','Cupped jaws: not for dense cortical bone.','pituitary'), ('Angled ring curette','DEBRIDEMENT','Removes disc, granulation and necrotic bone.','Use under direct vision, away from dura.','curette'), ('Leksell rongeur','BONE','Removes rib, transverse process, cancellous bone.','Heavy rongeur for bulk bony removal.','leksell'), ('High-speed burr','BONE','Thins posterior vertebral cortex.','Diamond burr is safer near neural tissue.','burr'), ('Osteotome + mallet','BONE','Controlled osteotomy and bony resection.','Protect pleura, vessels and dura first.','osteotome'), ('Hohmann / deep retractor','EXPOSURE','Maintains corridor and retracts tissue.','Place on bone: avoid sustained neural pressure.','retractor'), ('Frazier suction','VISUALIZATION','Clears blood, pus and fine debris.','Fine tip permits controlled deep suction.','suction')] cols=[15*mm,76*mm,137*mm]; ys=[H-105*mm,H-159*mm,H-213*mm] for i,item in enumerate(items): card(cols[i%3],ys[i//3],*item) c.setFillColor(navy);c.roundRect(15*mm,14*mm,W-30*mm,18*mm,2*mm,fill=1,stroke=0) c.setFillColor(colors.white);c.setFont('Helvetica-Bold',8);c.drawString(19*mm,25*mm,'RECOGNITION PEARLS') c.setFont('Helvetica',7.2);c.drawString(19*mm,20*mm,'Kerrison = fine biting bone punch | Pituitary = cupped tissue grasper | Curette = scraping/debridement | Leksell = bulk bone rongeur') c.setFillColor(HexColor('#A5CACB'));c.setFont('Helvetica-Oblique',6.5);c.drawString(15*mm,8*mm,'Educational instrument-recognition aid. Instrument selection and use require formal training, direct supervision, and local protocol.') c.save() r=PdfReader(p) assert len(r.pages)==1, len(r.pages) assert os.path.getsize(p)>2500 print('Verified:',len(r.pages),'page,',os.path.getsize(p),'bytes') PY
Anterolateral Spine Decompression Instruments
PDF Document · PDF