
explain in detail about enviroment and health community medicine
I'll start by reading the medical library skill, then search for comprehensive content on environment and health in community medicine.
Searching sources...
Reading File
Now let me search the library for environment and health content in community medicine, running parallel searches:
Finding Sources
Finding Sources
Finding Sources
Park's Textbook of Preventive and Social Medicine is the key community medicine reference. Let me search its table of contents for environment and health sections:
Finding Sources
Finding Sources
Now let me read the key environment section and also search for more specific sub-topics:
Finding Sources
Reading File
Good, I have the foundational environment section. Now let me search for more specific environmental health topics in Park's textbook - air pollution, water, housing, occupational health:
Finding Sources
Finding Sources
Excellent! Block 10 has the key air pollution and environmental health content. Let me read the major sections now:
Reading File
Reading File
Now let me gather water pollution and housing/environmental sanitation sections:
Finding Sources
Finding Sources
Now let me read the housing and environmental sections, and the broader environment chapter context:
Reading File
Reading File
I now have comprehensive content from Park's Textbook. Let me read the water-related disease section and the broader environment intro to complete the picture:
Reading File
Reading File
I now have rich, comprehensive content from Park's Textbook. Let me compile the full detailed answer:
Environment and Health - Community Medicine
Based on Park's Textbook of Preventive and Social Medicine
1. Introduction
It was Hippocrates who first related disease to the environment - noting the role of climate, water, and air in causing illness. Centuries later, Pettenkofer in Germany revived the concept of the disease-environment association. Today, environment and health is one of the foundational chapters of community medicine because environmental factors profoundly shape population health.
2. Classification of Environment
The environment of man is broadly classified into two types:
A. Internal Environment
Pertains to every component part, tissue, organ, and organ system and their harmonious functioning within the body. This is the domain of internal medicine.
B. External (Macro) Environment
Defined as "all that which is external to the individual human host". It encompasses:
- Micro-environment (domestic/personal environment): The individual's lifestyle, eating habits, smoking, drinking, drug use, etc.
- Physical environment: Non-living things and physical factors (air, water, soil, housing, climate, heat, light, noise, radiation).
- Biological environment: All living organisms surrounding man - viruses, bacteria, insects, rodents, animals and plants.
- Psychosocial environment: Cultural values, customs, habits, beliefs, attitudes, morals, family structure, social relationships, and economic conditions.
Other recognized sub-categories include occupational environment, socio-economic environment, and moral environment.
3. Components of External Environment
A. Physical Environment
Applied to non-living things and physical factors including air, water, soil, housing, climate, geography, heat, light, noise, debris, and radiation with which man is in constant interaction.
Man's progress over his physical environment has been responsible for most health improvements over the last century. However, in doing so, he has created new health problems such as:
- Air pollution
- Water pollution
- Noise pollution
- Urbanization
- Radiation hazards
- Electromagnetic exposure from telecommunications and broadcasting
In most developing countries, defective physical environment (lack of sanitation) remains the main health problem.
B. Biological Environment
The universe of living things surrounding man, including:
- Viruses and microbial agents
- Insects (vectors), rodents, animals, and plants
These organisms act as disease-producing agents, reservoirs of infection, intermediate hosts and vectors. When the ecological balance between host and these organisms is disturbed, ill-health results.
C. Psychosocial Environment
Includes complex psychosocial factors defined as "those factors affecting personal health, health care and community well-being that stem from the psychosocial make-up of individuals and the structure and functions of social groups."
Covers:
- Cultural values, customs, habits, beliefs, attitudes
- Family structure and community networks
- Social and economic support systems
- Organization of health and welfare services
4. Environment as a Determinant of Health
Environment is recognized as the third major determinant of health (after genetic/hereditary factors and lifestyle):
"It is an established fact that environment has a direct impact on the physical, mental and social well-being of those living in it."
- Park's Textbook of Preventive and Social Medicine
Environmental factors range from:
- Housing and water supply
- Psychosocial stress and family structure
- Social and economic support systems
- Organization of health and social welfare services
The physical, biological, and psychological components are not watertight compartments - they are inextricably linked and must be viewed holistically when considering environmental influence on health.
5. Air Pollution
Definition
Air pollution is the presence of substances in the atmosphere that cause harm to human health, other living organisms, or the environment.
Major Air Pollutants
| Pollutant | Sources | Health Effects |
|---|---|---|
| Particulate Matter (PM2.5/PM10) | Vehicles, industry, power plants, domestic coal burning | Respiratory and cardiovascular disease, lung cancer |
| Sulphur dioxide (SO₂) | Fossil fuels, industrial processes | Respiratory irritation, acid rain |
| Nitrogen dioxide (NO₂) | Motor vehicles, combustion | Respiratory disease |
| Carbon monoxide (CO) | Incomplete combustion | Hypoxia, cardiac effects |
| Lead | Leaded fuel, smelting | Neurotoxicity (especially children - IQ loss, behavioural issues) |
| Ozone (O₃) | Secondary pollutant (photochemical) | Respiratory irritation |
| Polycyclic Aromatic Hydrocarbons (PAH) | Combustion, vehicles | Carcinogenic |
Particulate Matter - Key Facts
- PM10: particles < 10 µm; penetrate to thoracic region
- PM2.5: particles < 2.5 µm; deposit in smaller airways and alveoli - more dangerous
- WHO AQG (2005): PM2.5 annual mean = 10 µg/m³; 24-hour mean = 25 µg/m³
- PM10 annual mean = 20 µg/m³; 24-hour mean = 50 µg/m³
- No safe threshold for PM has been identified
Health Effects of Air Pollution
(a) Immediate/Acute Effects:
- Borne mainly by the respiratory system
- Acute bronchitis
- In extreme pollution events - death by suffocation (e.g., London Smog Disaster, 1952)
(b) Delayed/Chronic Effects:
- Chronic bronchitis
- Lung cancer
- Bronchial asthma
- Emphysema
- Respiratory allergies
- Cardiovascular diseases
- Neurological effects (from lead)
(c) Environmental Effects:
- Acid rain
- Climate change
- Ecosystem damage
"Mortality in cities with high pollution levels exceeds that in relatively cleaner cities by 15-20%." - Park's Textbook
Indoor Air Pollution
The indoor environment is a critical microenvironment where people spend the majority of their time. Indoor air pollution originates from both outdoor and indoor sources:
Major indoor sources worldwide:
- Combustion of solid fuels (wood, coal, dung) on open fires or traditional stoves
- Tobacco smoke
- Building materials (asbestos, formaldehyde)
- Radon from soil
- Biological contaminants (mold, dust mites)
Health consequences:
- Acute lower respiratory infections in young children
- Chronic Obstructive Pulmonary Disease (COPD) in adults
- Lung cancer
6. Water and Health
Water-Related Diseases Classified by Mode
| Category | Examples |
|---|---|
| Waterborne diseases (contaminants in drinking water) | Cholera, typhoid, hepatitis A, dysentery, polio |
| Water-washed diseases (inadequate water for hygiene) | Shigellosis, trachoma, conjunctivitis, scabies, ascariasis |
| Water-based diseases (host in water) | Schistosomiasis, Guinea worm (dracunculiasis) |
| Water-related insect vector diseases | Malaria, filariasis, arboviral diseases, onchocerciasis, African trypanosomiasis |
Chemical Contamination of Water
- Fluoride at 1 mg/L: Protective against dental caries
- Excess fluoride: Dental fluorosis (mottled enamel), skeletal fluorosis
- Nitrates: Cause methaemoglobinaemia in infants (cyanosis)
- Hard water (Ca/Mg): Appears to have a beneficial effect against cardiovascular diseases
- Heavy metals (lead, arsenic, mercury): Neurotoxic, carcinogenic at high levels
Water Pollution Law - India
The Water (Prevention and Control of Pollution) Act, 1974 provides for:
- Central and State Water Boards with wide powers to control pollution
- Legal deterrents against water contamination
7. Housing and Health
Housing is part of the total environment and directly influences health and well-being. Poor housing is strongly associated with:
- Respiratory infections: Tuberculosis, common cold, influenza, diphtheria, bronchitis, measles, whooping cough
- Skin infections: Scabies, ringworm, impetigo, leprosy
- Rat infestation: Plague
- Arthropods: Houseflies, mosquitoes, fleas, bugs (vectors of disease)
- Accidents: A substantial proportion of domestic accidents are due to environmental defects in the home
- High morbidity and mortality: Observed where housing conditions are sub-standard
- Psychosocial effects: Sense of isolation, neurosis, and behaviour disorders - particularly in high-rise dwellers and densely populated urban areas
Overcrowding
Overcrowding occurs when more people live in a dwelling than space allows, making movement restricted, privacy impossible, hygiene impractical, and rest difficult.
Health effects:
- Rapid spread of respiratory infections (TB, influenza, diphtheria)
- High morbidity and mortality
- Psychosocial harms: irritability, frustration, lack of sleep, anxiety, violence, mental disorders
Accepted standard: Expressed as persons per room (number of persons divided by number of rooms). WHO recommends no more than 1.5 persons per room as the threshold for overcrowding.
8. Environmental Sanitation
Environmental sanitation refers to the control of all environmental factors that may exercise a deleterious effect on physical, mental, or social well-being. Key components:
Excreta Disposal
Improper excreta disposal leads to:
- Soil pollution
- Water pollution
- Contamination of food
- Propagation of flies
- Resulting diseases: typhoid, paratyphoid fevers, cholera, dysentery, hepatitis, helminthiasis
Solid Waste Management
Poor solid waste management promotes:
- Rodent and insect breeding
- Soil and water pollution
- Aesthetic deterioration of the community
Noise Pollution
Noise is recognized as a physical environmental pollutant. Effects include:
- Hearing impairment (especially industrial workers)
- Sleep disturbance
- Cardiovascular stress
- Psychological effects (annoyance, anxiety)
Radiation Hazards
- Ionizing radiation (X-rays, nuclear): Cancers, genetic mutations
- Non-ionizing radiation (UV, microwave): Skin cancer, cataracts, thermal effects
9. Socioeconomic Environment and Health
Socioeconomic conditions are long-recognized influencers of health. Major factors:
-
Economic status: Per capita GNP determines purchasing power, standard of living, and disease patterns. Paradoxically, affluence contributes to coronary heart disease, diabetes, and obesity.
-
Education: Especially female education - closely linked to infant/child mortality reduction. Kerala (India) demonstrates that education compensates poverty's health effects.
-
Nutrition: Closely tied to environment - food production, contamination, and distribution are all environmentally determined.
-
Employment/Occupation: Occupational environment introduces specific health hazards (chemicals, dust, ergonomic stress).
10. Occupational Environment
The occupational environment introduces specific physical, chemical, biological, and ergonomic hazards. India's National Programme for Control and Treatment of Occupational Diseases addresses this. Key occupational hazards include:
- Dust: Pneumoconiosis (silicosis, coal worker's pneumoconiosis)
- Chemicals: Pesticide poisoning, heavy metal toxicity
- Noise: Noise-induced hearing loss
- Heat: Heat stroke, heat exhaustion
- Radiation: Radiation sickness, cancers
11. Control and Prevention Strategies
Air Quality
- Legislative controls (Clean Air Acts)
- Motor vehicle emission standards
- Industrial emission controls
- WHO Air Quality Guidelines
- Promotion of clean cooking fuels
Water Safety
- Water treatment (filtration, chlorination, UV)
- Source protection
- Legal frameworks (Water Pollution Act 1974)
Housing Improvement
- Building codes and standards
- Urban planning and slum improvement
- Provision of basic amenities (ventilation, sanitation)
Environmental Health Legislation (India)
- Environment Protection Act, 1986
- Air (Prevention and Control of Pollution) Act, 1981
- Water (Prevention and Control of Pollution) Act, 1974
- Solid Waste Management Rules
- Noise Pollution Control Rules
12. Summary: Key Concepts
| Concept | Detail |
|---|---|
| Internal environment | Organ systems; domain of internal medicine |
| External environment | Physical + Biological + Psychosocial |
| 3 components of external env. | Physical, Biological, Psychosocial |
| Air pollution immediate effect | Acute bronchitis, suffocation |
| Air pollution delayed effects | Chronic bronchitis, lung cancer, asthma, emphysema |
| PM2.5 | < 2.5 µm; most dangerous; reaches alveoli |
| WHO PM2.5 annual limit | 10 µg/m³ |
| Indoor pollution main cause | Solid fuel combustion |
| Water and fluoride | 1 mg/L = protective; excess = fluorosis |
| Nitrates in water | Methaemoglobinaemia in infants |
| Overcrowding main disease | Tuberculosis and respiratory infections |
| London smog | 1952 - extreme acute air pollution event |
Sources: Park's Textbook of Preventive and Social Medicine - Chapters on Concept of Health, Environment and Health, Air Pollution, Water Pollution, Housing and Health, Environmental Sanitation
causes of all pollution dispose mangemnt of community medicine
Searching sources...
Finding Sources
Finding Sources
Finding Sources
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Finding Sources
Finding Sources
Finding Sources
Finding Sources
Reading File
Reading File
I now have all the content needed for a comprehensive answer. Let me compile the full detailed response.
Causes of All Types of Pollution and Their Disposal/Management - Community Medicine
Based on Park's Textbook of Preventive and Social Medicine
OVERVIEW
The phenomenon called "pollution" is an inescapable consequence of the presence of man and his activities. Much of man's ill-health can be traced to adverse environmental factors such as air pollution, water pollution, soil pollution, noise pollution, and poor sanitation. The major types of pollution recognized in community medicine are:
- Air Pollution
- Water Pollution
- Soil Pollution (Excreta/Refuse)
- Noise Pollution
- Radiation Pollution
1. AIR POLLUTION
Definition
Air pollution signifies the presence in the ambient (surrounding) atmosphere of substances (gases, mixtures of gases, and particulate matter) generated by the activities of man in concentrations that interfere with human health, safety or comfort, or that are injurious to vegetation, animals, and other environmental media.
Types of Air Pollutants
A. Primary Air Pollutants - emitted directly into the atmosphere from a source such as a factory chimney or exhaust pipe (e.g., SO₂, CO, soot, lead particles).
B. Secondary Air Pollutants - formed within the atmosphere from chemical reactions of primary pollutants with oxygen and water. The most familiar example is ozone (O₃), which arises almost entirely from chemical reactions in the atmosphere.
C. Gaseous Air Pollutants - present as gases or vapours capable of passing through filters. If water-soluble, they deposit in the upper respiratory tract. If insoluble, they penetrate to the deep lung.
D. Particulate Air Pollutants - solid or liquid phase material suspended in the atmosphere, ranging from 1-100 µm in diameter.
Causes / Sources of Air Pollution
| Pollutant | Sources |
|---|---|
| Carbon monoxide (CO) | Incomplete combustion in automobiles, industrial processes, heating facilities, incinerators. Peaks during morning and evening rush hours. |
| Sulphur dioxide (SO₂) | Combustion of sulphur-containing fossil fuels, smelting of ores, power plants, oil refineries, kerosene heaters |
| Oxides of Nitrogen (NOₓ) | Automobile exhaust, gas stoves and heaters, wood-burning stoves, kerosene heaters |
| Lead | Automobile exhaust (leaded gasoline), smelting, recycling of lead, leaded paint stripping, leaded aviation fuel |
| Particulate Matter (PM2.5/PM10) | Power plants, industrial processes, vehicular traffic, domestic coal burning, incinerators, dust storms |
| Hydrocarbons/PAH | Automobile exhaust, cigarette smoke, combustion processes |
| Ozone (O₃) | Secondary pollutant from automobile exhaust photochemical reactions |
| Asbestos, beryllium, mercury | Industrial and mining operations |
| Hydrogen sulphide, ammonia | Industrial processes, sewage, agricultural activities |
| Radioactive compounds | Nuclear power plants, weapons testing |
| Indoor sources | Solid fuel combustion (wood, coal, dung), tobacco smoke, building materials (formaldehyde, asbestos), radon |
Health Effects
(a) Health Aspects:
- Immediate/Acute: Acute bronchitis, respiratory irritation; in extreme cases - death by suffocation (London Smog Disaster, 1952)
- Delayed/Chronic: Chronic bronchitis, lung cancer, bronchial asthma, emphysema, respiratory allergies
- SO₂ causes coughing, mucus secretion, aggravates asthma and COPD
- Lead causes impaired neuropsychological development in children (IQ loss, poor school performance, behavioural difficulties)
- NOₓ causes bronchiolitis obliterans, impaired lung defences
- PM2.5 increases cardiovascular and respiratory disease risk
- Epidemiological studies show sudden increases in air pollution are associated with immediate increases in morbidity and mortality
(b) Social and Economic Aspects:
- Destruction of plant and animal life
- Corrosion of metals, damage to buildings
- Reduced visibility in towns
- Acid rain causing deforestation (SO₂ + water = H₂SO₄)
Prevention and Control of Air Pollution (WHO Recommended)
- Containment - Prevent escape of toxic substances into ambient air through enclosure, ventilation, and air-cleaning "arresters"
- Replacement - Replace polluting technology with cleaner alternatives (electricity, solar power, natural gas, central heating instead of coal; unleaded petrol)
- Dilution - Valid within the self-cleaning capacity of the environment. Establish green belts between industrial and residential areas
- Legislation - Air (Prevention and Control of Pollution) Act, 1981 (India); WHO Air Quality Guidelines
- Vehicle emission standards - Catalytic converters, PUC certificates
- Use of clean fuels - LPG, CNG for domestic cooking and transport
- Air purification - HEPA filters, UV irradiation (operation theatres, infectious disease wards), chemical mists (triethylene glycol vapours)
2. WATER POLLUTION
Definition
Pure uncontaminated water does not occur in nature. Water pollution is the contamination of water beyond its natural self-purification capacity by human activities that makes it unsafe for use.
Causes / Sources of Water Pollution
A. Natural Sources (not essentially dangerous):
- Dissolved gases (CO₂, H₂S, N₂ from rainfall)
- Dissolved minerals (calcium, magnesium, sodium salts from soil)
- Suspended impurities (clay, silt, sand, mud)
- Microscopic organisms (derived from atmosphere, catchment area, soil)
B. Man-Made Sources (serious public health hazard):
| Source | Nature of Pollution |
|---|---|
| Sewage | Decomposable organic matter and pathogenic agents (bacteria, viruses, protozoa, helminths) |
| Industrial and trade wastes | Toxic agents - metal salts, complex synthetic organic chemicals, heavy metals (lead, mercury, arsenic, chromium) |
| Agricultural pollutants | Fertilizers (nitrates, phosphates) and pesticides |
| Thermal pollution (heat) | Cooling water from power plants raises water temperature, depletes dissolved oxygen |
| Radioactive substances | Nuclear power plant discharges, medical and industrial radioactive waste |
| Pipeline corrosion and leaky joints | Cross-connections between water supply and sewage pipes cause contamination even after treatment |
Indicators of water pollution: Total suspended solids, Biochemical Oxygen Demand (BOD) at 20°C, concentration of chlorides, nitrogen and phosphorus, absence of dissolved oxygen.
Water-Related Diseases
A. Biological (Waterborne diseases):
- Viral: Hepatitis A, Hepatitis E, poliomyelitis, rotavirus diarrhoea
- Bacterial: Typhoid, paratyphoid fever, bacillary dysentery, E. coli diarrhoea, cholera
- Protozoal: Amoebiasis, giardiasis
- Helminthic: Roundworm, threadworm, hydatid disease
- Leptospiral: Weil's disease
B. Water-Washed Diseases (insufficient water for hygiene):
- Shigellosis, trachoma, conjunctivitis, scabies, ascariasis
C. Water-Based Diseases (host lives in water):
- Schistosomiasis, Guinea worm (dracunculiasis)
D. Water-Related Insect Vector Diseases:
- Malaria, filariasis, arboviral diseases, onchocerciasis, African trypanosomiasis
E. Chemical Effects:
- High fluoride = dental/skeletal fluorosis
- High nitrates = methaemoglobinaemia in infants (cyanosis)
- Hard water = protective against cardiovascular diseases
Management / Control of Water Pollution
- Legislation: Water (Prevention and Control of Pollution) Act, 1974 - Central and State Water Boards with enforcement powers
- Treatment of water supply (large scale):
- Sedimentation (plain and with coagulants - alum)
- Filtration (slow sand filters, rapid sand filters)
- Disinfection - Chlorination (most practical), UV irradiation, ozonation, boiling
- Treatment of water (small scale):
- Boiling, chlorination with bleaching powder, solar disinfection
- Source protection: Safe well construction, sanitary surveying, sealing of well tops
- Sewage treatment before discharge into water bodies (primary, secondary, tertiary treatment)
- Industrial effluent treatment before release
- Surveillance at every point in distribution system
3. SOIL POLLUTION AND EXCRETA DISPOSAL
Public Health Importance of Excreta
Human excreta is a major source of environmental pollution. Health hazards of improper excreta disposal:
- Soil pollution
- Water pollution
- Contamination of foods
- Propagation of flies
Resulting diseases: Typhoid, paratyphoid fever, dysenteries, diarrhoeas, cholera, hookworm disease, ascariasis, viral hepatitis, and other intestinal infections.
Routes of transmission (the 5 Fs): Water, Fingers, Flies, Soil, Food.
4. SOLID WASTE POLLUTION
Definition
Solid wastes include garbage (food wastes), rubbish (paper, plastics, wood, metal, glass), demolition products (bricks, masonry, pipes), sewage sludge, dead animals, and manure.
Per capita daily solid waste produced ranges between 0.25 to 2.5 kg in different countries (varies with dietary habits, lifestyle, urbanization).
Sources of Refuse
| Type | Contents |
|---|---|
| Street refuse | Leaves, straw, paper, animal droppings, litter |
| Market refuse | Putrid vegetable and animal matter (highly infectious) |
| Stable litter | Animal droppings, leftover animal feeds |
| Industrial refuse | Wide variety - inert to highly toxic/explosive compounds |
| Domestic refuse | Ash (residue from cooking fires), rubbish (paper, cloth, metal, glass), garbage (waste food, vegetable peels) |
Health Hazards of Improper Solid Waste Disposal
- Decomposition favours fly breeding (disease vectors)
- Attracts rodents and vermin (plague, leptospirosis)
- Pathogens conveyed to food through flies and dust
- Water and soil pollution from drainage/leachate
- Unsightly appearance, nuisance from bad odours
- Correlation between improper disposal and incidence of vector-borne diseases
Methods of Solid Waste Disposal
(a) Dumping
Refuse dumped in low-lying areas for land reclamation. WHO condemned it as "a most insanitary method that creates public health hazards, nuisance and severe pollution". Drawbacks: exposed to flies and rodents, water and soil pollution, wind dispersal, odour.
(b) Controlled Tipping / Sanitary Landfill (Most satisfactory method)
Refuse is placed in a prepared trench, compacted, and covered with earth at the end of each working day. Three methods:
- Trench method - level ground; 2-3 m deep, 4-12 m wide trench
- Ramp method - sloping terrain
- Area method - filling land depressions, quarries, clay pits; each layer sealed with 30 cm mud cover
(c) Incineration
Burning of refuse at high temperatures. Advantages: complete destruction, reduces volume significantly, can generate energy. Used for hospital/infectious waste. Needs proper emission controls to prevent air pollution.
(d) Composting
Biological decomposition of organic matter into humus/manure.
- Bangalore method (NEERI method): Organic refuse is placed in trenches 2-3 m wide, 1 m deep; covered with earth; decomposed in 4-8 weeks to form compost.
- Mechanical composting: Industrial scale - refuse pulverized, mixed with sewage sludge/nightsoil in rotating machines. Controlled carbon-nitrogen ratio, temperature, moisture, pH, and aeration. Complete in 4-6 weeks. Used in Netherlands, Germany, Switzerland, Israel.
(e) Manure Pits (For rural India)
Individual householders dig pits and dump garbage, cattle dung, straw, and leaves. Covered with earth daily. Two pits used alternately. Converts to manure in 5-6 months for agricultural use. Effective and simple for rural communities.
(f) Burial (For small camps/disaster situations)
Trench 1.5 m wide, 2 m deep; refuse covered with 20-30 cm earth daily. Contents usable as field manure after 4-6 months.
5. EXCRETA DISPOSAL METHODS
In Unsewered Areas
A. Service Type (Conservancy System)
Nightsoil collected from bucket/pail latrines by human agency - now condemned as insanitary and inconsistent with human dignity. Nightsoil exposed to flies; risk of water and soil pollution.
B. Non-Service Type (Sanitary Latrines)
A sanitary latrine must ensure:
- Excreta does not contaminate ground or surface water
- Excreta does not pollute soil
- Not accessible to flies, rodents, animals
- Does not create nuisance from odour or unsightly appearance
Types of Sanitary Latrines:
| Type | Features | Suitable For |
|---|---|---|
| Bore hole latrine | 30-40 cm diameter hole, 4-8 m deep; concrete squatting plate | Family use; forerunner of non-service latrines |
| Pit privy (VIP latrine) | Ventilated Improved Pit - fly trap using light principle; most recommended for rural India | Rural communities |
| Pour flush latrine | Pan connected to pit via water seal trap; 2 cm water seal prevents flies and odour | Indian standard latrine |
| Aqua privy | Tank below the squatting slab filled with water; sewage treated in tank | Semi-urban areas |
| Septic tank | Underground watertight chamber; anaerobic digestion; liquid effluent to soak pit | Urban households |
In Sewered Areas
Municipal sewers carry waste to:
- Sewage treatment plants (primary → secondary → tertiary)
- Discharge of treated effluent to water bodies
6. NOISE POLLUTION
Definition
Noise is defined as "wrong sound, in the wrong place, at the wrong time." Noise pollution signifies the vast cacophony of sounds produced in modern life leading to health hazards. The 20th century has been described as the "Century of Noise."
Sources / Causes of Noise Pollution
- Automobiles, factories, industries, aircraft
- Railway junctions, traffic roundabouts, bus terminuses, airports
- Pressure horns, loudspeakers during festivities (especially at night)
- Domestic sources: radios, transistors, televisions
- Industrial machinery and equipment
Properties of Noise
- Loudness/Intensity: Measured in decibels (dB)
- Normal conversation = 60-65 dB
- Whispering = 20-30 dB
- Heavy street traffic = 60-80 dB
- Boiler factories = ~120 dB
- Safe daily exposure limit = 85 dB
- Frequency: Measured in Hertz (Hz)
Acceptable Noise Levels (dBA)
| Setting | Area | Level (dBA) |
|---|---|---|
| Residential | Bedroom | 25 |
| Residential | Living room | 40 |
| Commercial | Office | 35-45 |
| Commercial | Conference room | 40-45 |
| Industrial | Workshop | 40-60 |
| Industrial | Laboratory | 40-50 |
Health Effects of Noise
- Auditory effects: Noise-induced hearing loss (NIHL) - most common occupational disease; tinnitus
- Non-auditory physiological effects: Hypertension, cardiovascular stress, altered hormonal responses
- Psychological effects: Irritability, annoyance, anxiety, frustration, mental disorders
- Sleep disturbance and reduced work efficiency
- Communication interference causing accidents
Control of Noise Pollution
- Source control: Engineering controls - mufflers, enclosures, quieter machinery design
- Transmission control: Sound barriers, green belts, distance from sources
- Receptor protection: Personal Protective Equipment (PPE) - ear muffs, ear plugs (for occupational exposure)
- Legislation: Noise Pollution (Regulation and Control) Rules, 2000 (India); WHO guidelines
- Urban planning: Zoning - separation of industrial, commercial, and residential areas
- Traffic management: Speed limits, banning pressure horns in hospital/school zones
7. RADIATION POLLUTION
Causes / Sources
| Type | Sources |
|---|---|
| Ionizing radiation | Nuclear power plants, nuclear weapons testing, X-ray equipment (medical), radioactive waste |
| Non-ionizing radiation | UV radiation (sun), microwave radiation, radar, telecommunications towers, television transmitters, satellite systems |
Health Effects
- Ionizing: Radiation sickness, cancers (leukaemia, thyroid cancer), genetic mutations, teratogenesis
- UV: Skin cancer, cataracts
- Microwave/electromagnetic: Thermal effects on tissues (still being evaluated)
Control
- Radiation protection standards (distance, shielding, time limits)
- Radiation Protection Act
- International Commission on Radiological Protection (ICRP) guidelines
- Proper disposal of radioactive medical waste
SUMMARY TABLE: All Pollution Types at a Glance
| Pollution Type | Key Sources | Major Health Effects | Key Control Measures |
|---|---|---|---|
| Air | Vehicles, industry, coal burning, indoor fuels | Bronchitis, asthma, lung cancer, CVD, lead toxicity | Legislation, clean fuels, green belts, emission standards |
| Water | Sewage, industrial effluents, agriculture, pipeline leaks | Cholera, typhoid, dysentery, hepatitis, fluorosis | Water treatment, source protection, legislation (1974 Act) |
| Soil/Excreta | Open defecation, poor sanitation, industrial waste | Typhoid, dysentery, hookworm, cholera, ascariasis | Sanitary latrines, sewage treatment, septic tanks |
| Solid Waste | Domestic, market, street, industrial refuse | Fly/rodent breeding, soil & water pollution, vector-borne diseases | Sanitary landfill, composting, incineration, manure pits |
| Noise | Vehicles, industry, aircraft, domestic appliances | Hearing loss, hypertension, sleep disturbance, anxiety | Engineering controls, PPE, legislation, zoning |
| Radiation | Nuclear plants, X-rays, UV, telecom | Cancer, genetic mutations, skin disease, cataracts | Shielding, distance, time limits, ICRP guidelines |
Source: Park's Textbook of Preventive and Social Medicine - Chapters on Environmental Sanitation, Air Pollution, Water Pollution, Disposal of Wastes, Excreta Disposal, and Noise
Explain about dynamic disease transmission in detail
Searching sources...
Reading File
Finding Sources
Finding Sources
Found the exact section "DYNAMICS OF DISEASE TRANSMISSION" in block 2. Let me read it along with related sections:
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
Reading File
I now have extensive, rich content directly from Park's Textbook. Let me compile the complete detailed answer.
Dynamics of Disease Transmission - Community Medicine
Source: Park's Textbook of Preventive and Social Medicine
1. Introduction and Concept
Communicable diseases are transmitted from the reservoir/source of infection to a susceptible host. The study of how disease spreads dynamically through a population is called the dynamics of disease transmission.
There are three fundamental links in the chain of transmission:
- The Reservoir / Source of infection
- The Mode of Transmission
- The Susceptible Host
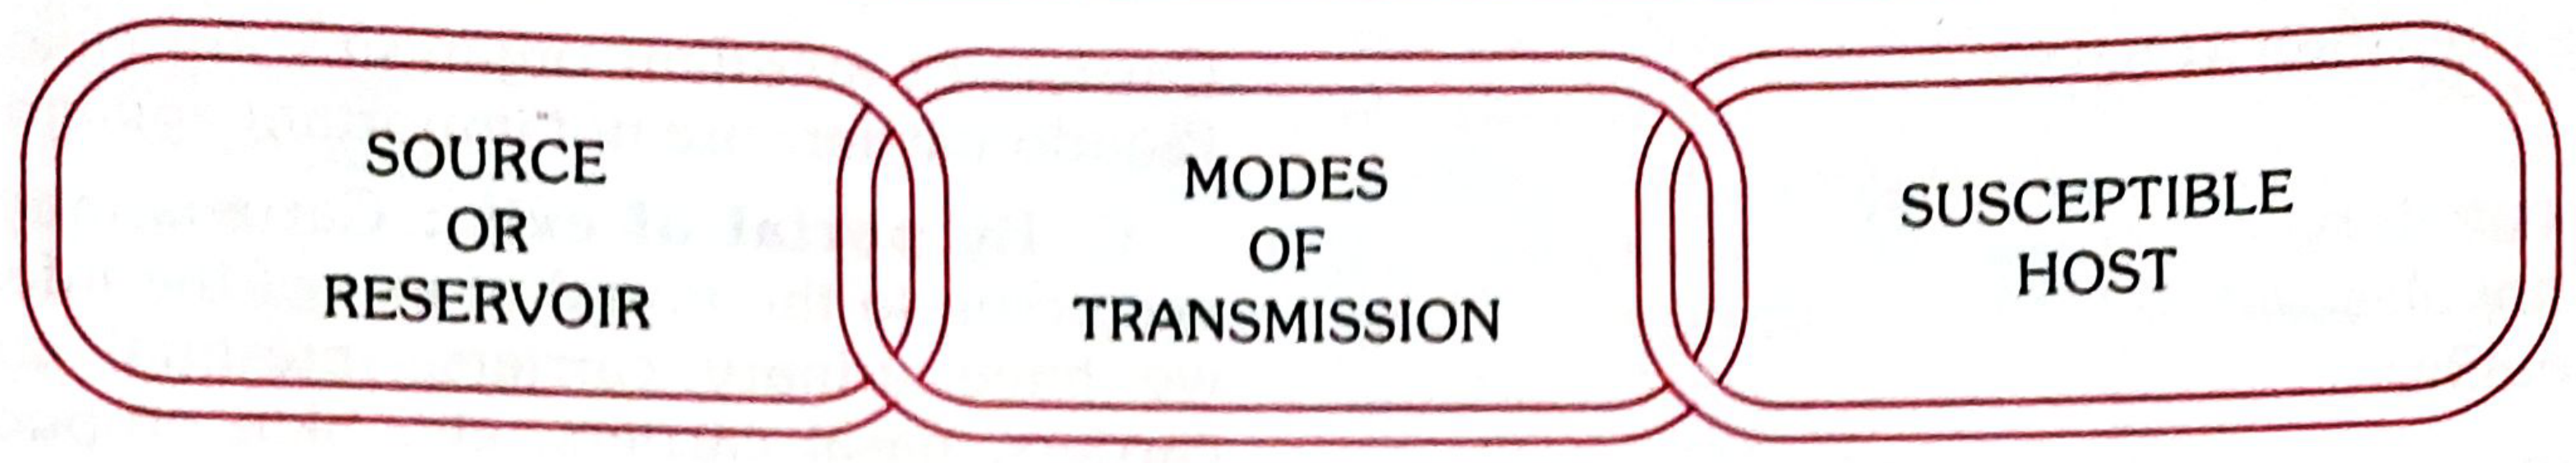
Breaking any single link in this chain interrupts the transmission of disease.
2. The Epidemiological Triad (Agent - Host - Environment)
The germ theory alone has many limitations. Not everyone exposed to tuberculosis develops tuberculosis. Not everyone exposed to beta-haemolytic streptococci develops acute rheumatic fever. This demanded a broader concept of disease causation - the Epidemiological Triad.
The triad synthesizes three basic factors:
- Agent - the cause of disease
- Host - the organism harbouring the disease
- Environment - the external surroundings that allow disease transmission
- Time - incubation periods, duration of illness, epidemic threshold
The traditional triangle of epidemiology (Fig. 5 of Park's) shows the interaction and interdependence of these four elements. The agent, host, and environment operating in combination determine:
- The onset of disease (single case to epidemic)
- The distribution of disease in the community
3. Natural History of Disease
Disease results from a complex interaction between man, agent, host, and environment. It unfolds in two phases:
Phase 1 - Prepathogenesis Phase
- The period preliminary to the onset of disease in man
- The disease agent has NOT yet entered man
- Factors favouring interaction between agent and host are already existing in the environment
- Also called "man in the midst of disease" or "man exposed to the risk of disease"
- We are all potentially in the prepathogenesis phase of many diseases at any given time
Phase 2 - Pathogenesis Phase
- Begins with the entry of the disease agent into the susceptible human host
- The disease agent multiplies and induces tissue and physiological changes
- Disease progresses through early pathogenesis → advanced disease → outcomes (recovery, disability, death, or carrier state)
4. Reservoir and Source of Infection
Key Definitions
- Source of infection: "The person, animal, object or substance from which an infectious agent passes or is disseminated to the host."
- Reservoir: "Any person, animal, arthropod, plant, soil or substance (or combination of these) in which an infectious agent lives and multiplies, on which it depends primarily for survival, and where it reproduces itself in such a manner that it can be transmitted to a susceptible host."
In short: the reservoir is the natural habitat where the organism metabolizes and replicates.
Note: Source and reservoir are NOT always synonymous.
- Hookworm: reservoir = man; source = soil contaminated with infective larvae
- Tetanus: reservoir = source = soil
- Typhoid: reservoir = case or carrier; source = faeces, urine, contaminated food/water
Homologous vs Heterologous Reservoir
- Homologous reservoir: Same species is victim (e.g., man is reservoir for Vibrio cholerae)
- Heterologous reservoir: Infection derived from a different species (e.g., animals infected with Salmonella)
Types of Reservoirs
| Type | Description | Examples |
|---|---|---|
| Human reservoir | Man is his own most important reservoir | Cases and carriers of typhoid, cholera, tuberculosis |
| Animal reservoir (Zoonoses) | Disease normally maintained in animals; transmitted to man | Rabies (dogs), brucellosis (cattle), plague (rodents), Japanese encephalitis (pigs/birds) |
| Non-living reservoir | Soil, water, organic matter | Tetanus (soil), botulism (soil), Legionella (water) |
5. Human Reservoir - Cases and Carriers
A. Cases
A case is defined as a person identified as having the particular disease or condition under investigation. Infection may manifest as:
(1) Clinical illness - Mild/moderate/severe/fatal; may be typical or atypical
- Epidemiologically, mild ambulant cases are more important sources than severe cases because they continue to spread infection while moving about
(2) Subclinical (inapparent/covert) cases
- Disease agent multiplies but causes NO signs or symptoms
- Agent is still eliminated from the body via stools, vomiting, secretions
- These persons contribute more to transmission than symptomatic patients because they are unrecognized
- Play a dominant role in maintaining chain of infection (endemicity) in the community
- Detectable only by laboratory tests (culture, antibody response, skin sensitivity tests)
- Examples: rubella, mumps, polio, hepatitis A & B, influenza, diphtheria
(3) Latent infection
- Host does not shed the infectious agent (lies dormant without symptoms)
- Example: herpes simplex (reactivates under stress), ancylostomiasis
Classification by onset position:
- Primary case: First case introduced into the population unit
- Index case: First case to come to the investigator's attention (not always the primary case)
- Secondary cases: Develop from contact with the primary case
- Suspect case: Has signs and symptoms but not yet definitively diagnosed
B. Carriers
A carrier is an infected person (or animal) that harbours a specific infectious agent without discernible clinical disease, but serves as a potential source of infection for others.
Key feature: The carrier is apparently healthy while being a source of infection - making carriers epidemiologically dangerous.
| Type of Carrier | Definition | Examples |
|---|---|---|
| Healthy carrier | Never had clinical disease; harbours agent | Meningococcal meningitis, cholera, polio |
| Incubatory carrier | In incubation period, shedding agent | Measles, influenza, hepatitis A |
| Convalescent carrier | Recovering but still shedding | Typhoid, cholera, dysentery |
| Temporary carrier | Short duration (weeks to months) | Many infections |
| Chronic carrier | Carriers for years | Typhoid (Salmonella typhi), hepatitis B |
6. Modes of Transmission
Transmission may be Direct or Indirect.
A. DIRECT TRANSMISSION
Direct transmission implies essentially immediate transfer of infectious agents from source to a susceptible individual, without an intermediate agency.
(1) Direct contact
- Skin-to-skin, mucosa-to-mucosa, or mucosa-to-skin transfer
- Includes: touching, kissing, sexual intercourse, or continued close contact
- Ensures a larger dose of infection and reduces survival time outside host
- Diseases: STDs, AIDS, leprosy, leptospirosis, skin and eye infections
(2) Droplet infection
- Direct projection of droplets of saliva and nasopharyngeal secretions during coughing, sneezing, speaking, or spitting
- Droplets impinge directly on conjunctiva, oro-respiratory mucosa, or skin of a close contact
- Particles ≥10 µm are filtered by the nose
- Particles ≤5 µm penetrate deeply and reach the alveoli
- Droplet spread limited to 30-60 cm between source and host
- Increased risk in close proximity, overcrowding, and poor ventilation
- Diseases: Common cold, diphtheria, whooping cough, tuberculosis, COVID-19, meningococcal meningitis, respiratory infections, eruptive fevers
(3) Contact with soil
- Direct exposure of susceptible tissue to the disease agent in soil, compost, or decaying vegetable matter
- Example: Hookworm (skin penetration by infective larvae in soil); tetanus (wound contamination)
(4) Inoculation into skin or mucosa
- Direct introduction of agent through skin breaks
- Examples: Animal bites (rabies), needlestick injuries (HIV, hepatitis B)
(5) Transplacental (Vertical) transmission
- Agent passes from infected mother to foetus through the placenta
- Examples: Rubella, syphilis, HIV, CMV, toxoplasmosis (TORCH infections)
B. INDIRECT TRANSMISSION
Indirect transmission requires the infectious agent to survive outside the human host in the external environment. An essential requirement is that the agent retains its pathogenicity and virulence until it finds a new host. This depends on:
- Characteristics of the agent
- Nature of the inanimate object
- Environmental factors (temperature, humidity)
- If the agent acquires drug resistance, it further facilitates spread
Traditionally summarized as the "5 Fs": Flies, Fingers, Fomites, Food, Fluid
1. Vehicle-Borne Transmission
Transmission through water, food (including raw vegetables, fruits, milk and milk products), ice, blood, serum, plasma, tissues, or organs.
The infectious agent may either:
- Multiply in the vehicle (e.g., S. aureus in food)
- Be passively carried in the vehicle (e.g., hepatitis A virus in water)
Diseases transmitted via water and food: Acute diarrhoeas, typhoid, cholera, polio, hepatitis A, food poisoning, intestinal parasites
Diseases transmitted via blood: Hepatitis B, malaria, syphilis, brucellosis, trypanosomes, HIV, CMV
Epidemiological features of vehicle transmission:
- (a) If contamination is heavy → explosive outbreak (e.g., cholera, hepatitis A epidemics)
- (b) Initial cases confined to those exposed to the contaminated vehicle
- (c) When secondary cases occur, primary case may be obscured
- (d) Distance travelled by infectious agent may be great
- (e) Not always possible to isolate the agent in the incriminated vehicle
- (f) When vehicle is controlled or withdrawn → epidemic subsides
- (g) Common source of infection is often traceable
2. Vector-Borne Transmission
A vector is an arthropod or any living carrier (e.g., snail) that transports an infectious agent to a susceptible individual.
Epidemiological classification of vector-borne diseases:
- Parasites, bacteria, rickettsia, viruses (arboviruses), spirochaetes
By method of transmission:
| Type | Mechanism | Examples |
|---|---|---|
| Mechanical transmission | Agent mechanically transported (soiling of feet/proboscis, GI passage) - NO development or multiplication in vector | Houseflies transmitting typhoid, dysentery |
| Biological - Propagative | Agent only multiplies in vector, no change in form | Plague bacilli in rat fleas |
| Biological - Cyclo-propagative | Agent changes in both form AND number in vector | Malaria parasites in mosquito (Anopheles) |
| Biological - Cyclo-developmental | Agent undergoes development but NOT multiplication | Microfilaria in mosquito |
Special forms of vector transmission:
- Transovarial transmission: Infectious agent transmitted vertically from infected female vector to her progeny (e.g., dengue in Aedes mosquito)
- Transstadial transmission: Agent transmitted from one stage of life cycle to another (e.g., nymph to adult)
Factors influencing vector ability to transmit disease:
- Host feeding preferences
- Infectivity (ability to transmit the agent)
- Susceptibility (ability to become infected)
- Survival rate of vectors in the environment
- Domesticity (degree of association with man)
- Suitable environmental factors (temperature, humidity, rainfall)
3. Airborne Transmission
(a) Droplet nuclei
- Tiny particles (1-10 microns) representing the dried residue of droplets
- Formed by evaporation of droplets coughed/sneezed into the air OR generated by atomizing devices (aerosols)
- Can remain airborne for long periods, disseminated by air currents
- Particles 1-5 µm are drawn into alveoli and may be retained there
- Diseases: Tuberculosis, influenza, chickenpox, measles, Q fever, COVID-19, many respiratory infections
(b) Dust
- Larger droplets settle on floors, carpets, furniture, clothing, bedding
- Become part of dust; infectious agents may remain viable for varying periods
- Diseases: Tuberculosis, Q fever (Coxiella burnetii), smallpox (historically)
4. Fomite-Borne Transmission
Transmission through contaminated inanimate objects (fomites) such as clothing, bedding, crockery, utensils, stethoscopes, etc.
5. Unclean Hands and Fingers
Faecal-oral transmission via unwashed hands carries bacteria, viruses, and parasites to mouth
- Diseases: Typhoid, dysentery, cholera, hepatitis A, polio
7. The Susceptible Host
A host is a person or living animal that affords subsistence or lodgement to an infectious agent under natural conditions.
Types of hosts:
- Obligate host: Only host for the agent (e.g., man in measles and typhoid)
- Primary/definitive host: Host in which parasite attains maturity or passes its sexual stage
- Secondary/intermediate host: Host in which parasite is in larval or asexual state
- Transport host (paratenic host): Organism in which parasite remains alive but does not undergo development
Host Susceptibility Factors
The probability of disease developing after exposure depends on:
- Immunity (specific antibodies, cellular immunity)
- Nutritional status (malnutrition increases susceptibility)
- Age (children and elderly are more vulnerable)
- Genetic makeup
- Level and duration of exposure
- Overall fitness and co-existing diseases
Immunity in Disease Dynamics
Active immunity: Developed by the host following infection or immunization; associated with antibodies or cells having specific action on the organism.
- Acquired following: (a) clinical infection (e.g., chickenpox, rubella), (b) subclinical/inapparent infection (e.g., polio, diphtheria), (c) immunization (killed vaccine, live attenuated vaccine, toxoid)
Passive immunity: Transfer of ready-made antibodies (normal human Ig, specific human Ig, animal antitoxins/antisera). Provides immediate but temporary protection.
Immune response:
- Primary response: First exposure → IgM appears first (days 3-10), peaks, then declines; IgG appears slightly later (peaks 7-10 days), then gradually falls over weeks/months
- Secondary (anamnestic) response: Re-exposure → rapid, large IgG response (memory cells activated)
8. Key Epidemiological Concepts in Disease Dynamics
Incubation Period
The time interval between invasion by an infectious agent and the appearance of the first sign or symptom of the disease. Different for each disease (hours to years).
Serial Interval
The gap in time between the onset of the primary case and the onset of secondary cases in a closed group (e.g., family). Used in practice when exact incubation period is unknown.
Generation Time
"The interval of time between receipt of infection by a host and maximal infectivity of that host." Generally roughly equal to incubation period, but not identical:
- Time of maximum communicability may precede or follow the incubation period
- Example: In mumps, communicability peaks ~48 hours before swelling of salivary glands
Communicable Period
"The time during which an infectious agent may be transferred directly or indirectly from an infected person to another person, from an infected animal to man, or from an infected person to an animal, including arthropods."
Communicability varies by disease:
- Some diseases are MORE communicable during the incubation period than during actual illness
- Early diagnosis and treatment can reduce communicability
Secondary Attack Rate (SAR)
A measure of communicability:
Formula:
SAR = (Number of exposed persons developing disease within incubation period range / Total number of exposed/susceptible contacts) × 100
- Primary case is excluded from both numerator and denominator
- High SAR = highly communicable disease; low SAR = less communicable
9. Herd Immunity
The resistance of a group to attack by a disease to which a large proportion of the members are immune. It protects the entire community - even non-immune individuals benefit from reduced transmission.
Key to propagated epidemics: "Transmission continues until the number of susceptibles is depleted or susceptible individuals are no longer exposed."
Propagated epidemics are more likely where:
- Large numbers of susceptibles are aggregated
- There is a regular supply of new susceptibles (births, immigrants) lowering herd immunity
10. Types of Epidemics (Dynamics at Population Level)
A. Common-Source Epidemics
(a) Point-Source (Single Exposure)
- Exposure is brief and essentially simultaneous
- All cases develop within one incubation period
- Epidemic curve: rises and falls rapidly with NO secondary waves, explosive clustering
- Example: Food poisoning outbreak at a banquet
- Key feature: Median incubation period = time for 50% of cases to occur after exposure
(b) Continuous/Multiple Exposure Epidemics
- Exposure is prolonged or repeated
- Epidemic curve shows a plateau rather than a sharp peak
- Example: Contaminated water supply over several weeks
B. Propagated Epidemics
- Usually of infectious origin, resulting from person-to-person transmission
- Epidemic shows a gradual rise and tails off over a longer period
- Each wave of cases infects the next group of susceptibles
- Transmission also via arthropod vectors or animal reservoirs
- Speed of spread depends on:
- Herd immunity
- Opportunities for contact
- Secondary attack rate
C. Slow (Modern) Epidemics
- Non-infectious diseases that spread slowly over decades
- Examples: Cardiovascular disease epidemic, obesity epidemic, tobacco-related cancers
- Detected by time-trend analysis, not by traditional epidemic curve
11. Temporal Patterns of Disease Occurrence
Secular (Long-Term) Trend
Changes in disease frequency over decades; reflects changes in herd immunity, agent virulence, living standards (e.g., declining tuberculosis mortality over the 20th century).
Periodic (Cyclic) Fluctuations
Recurrent peaks of disease at intervals. Related to accumulation of susceptibles and depletion of immune individuals (e.g., measles epidemic every 2-3 years before vaccination).
Seasonal Trend
- Many communicable diseases show seasonal variation
- Measles, varicella, cerebro-spinal meningitis, respiratory infections peak in spring/winter
- Bacterial gastrointestinal infections peak in summer (flies multiply, food spoilage faster)
- Vector-borne diseases (malaria, dengue) peak in monsoon/post-monsoon (mosquito breeding)
- Example: Dengue/DHF in India peaks in September-November (coinciding with late summer and rain)
Seasonal variation reflects: temperature, humidity, rainfall, overcrowding, life cycle of vectors.
12. Summary - Chain of Disease Dynamics
RESERVOIR/SOURCE
(Human case/carrier, animal, soil, water)
        ↓
EXIT MECHANISM
(Respiratory secretions, faeces, urine, blood, skin)
        ↓
MODE OF TRANSMISSION
Direct: Contact, Droplets, Soil, Inoculation, Transplacental
Indirect: Vehicle, Vector, Airborne, Fomites, Fingers
        ↓
PORTAL OF ENTRY
(Respiratory tract, GI tract, skin, mucosa, conjunctiva)
        ↓
SUSCEPTIBLE HOST
(Influenced by: immunity, nutrition, age, genetics, exposure dose)
        ↓
DISEASE (or subclinical infection, carrier state, immunity)
Breaking any link in this chain = interrupting transmission.
13. Key Definitions Summary Table
| Term | Definition |
|---|---|
| Reservoir | Natural habitat where agent metabolizes and replicates |
| Source of infection | Person/object from which agent is disseminated to host |
| Carrier | Infected person without clinical disease who can transmit |
| Incubation period | Time from exposure to first sign/symptom |
| Generation time | Time from receipt of infection to maximal infectivity of host |
| Serial interval | Time gap between onset of primary and secondary cases |
| Communicable period | Time during which agent may be transferred to a new host |
| Secondary attack rate | Measure of communicability in exposed contacts |
| Herd immunity | Group resistance due to high proportion of immune members |
| Epidemic | Cases in excess of normal expectancy in a region/period |
| Endemic | Constant presence of a disease in a given geographic area |
| Pandemic | Epidemic occurring over a very wide area, crossing international boundaries |
| Subclinical infection | Agent multiplies but no signs/symptoms; agent still shed |
| Latent infection | Agent dormant in host; NOT shed (e.g., herpes simplex) |
Source: Park's Textbook of Preventive and Social Medicine - Chapter on Dynamics of Disease Transmission, Epidemiological Triad, Natural History of Disease, and Types of Epidemics
This is a shared conversation. Sign in to Orris to start your own chat.