
I am a MD Dermatology Resident, studying for my final exams . Refer textbooks rooks, bolognia, Fitzpatrick, andrew’s, iadvl and compendium
Welcome! I'm ready to help you study for your MD Dermatology final exams using Rook's, Bolognia, Fitzpatrick, Andrews, IADVL, and the Compendium as your primary references.
What topic would you like to study? You can ask me about:
- Specific diseases - morphology, pathogenesis, diagnosis, treatment
- Drug mechanisms & side effects
- Histopathology
- Procedural dermatology
- Dermoscopy
- Exam-focused topics - high-yield facts, differentials, mnemonics
What's your first question?
Ehler danlos syndrome short note
Reading File
Now let me search the textbooks for Ehlers-Danlos Syndrome content across multiple books simultaneously.
Finding Sources
Finding Sources
I have the key file paths. Let me now read the Fitzpatrick and Andrews sections simultaneously - these are the most relevant dermatology textbooks.
Reading File
Reading File
Excellent content. Let me now read more of the Fitzpatrick content (subtypes, pathogenesis, treatment) and also the Robbins pathology section for a complete picture.
Reading File
Reading File
Let me now get the treatment section and vascular EDS section from Fitzpatrick, plus fetch the key clinical images.
Reading File
Loading Image
Loading Image
I now have comprehensive content from Fitzpatrick, Andrews, and Robbins. Let me compile the complete short note.
Ehlers-Danlos Syndromes (EDS) - Short Note
Definition
EDS is a clinically and genetically heterogeneous group of inherited connective tissue disorders characterized by:
- Skin hyperextensibility and fragility
- Joint hypermobility with frequent dislocations
- Abnormal wound healing with atrophic scarring
The 2017 International Classification recognizes 13 subtypes, all resulting from defects in collagen genes, enzymes that modify collagen, or other extracellular matrix proteins.
- Fitzpatrick's Dermatology, Vol. 1-2, p. 1247
- Andrews' Diseases of the Skin, p. 591
Epidemiology
| Parameter | Data |
|---|---|
| Combined prevalence | ~1 in 5,000 persons |
| Classical EDS | 1 in 10,000-20,000 newborns |
| Vascular EDS | 1 in 50,000-200,000 (most lethal) |
| Hypermobile EDS | Most common subtype overall |
Classification (2017 International Classification - 13 Subtypes)
| Type | Gene / Protein | Inheritance | Key Feature |
|---|---|---|---|
| Classical | COL5A1, COL1A1 | AD | Hyperextensible skin, atrophic "cigarette paper" scars |
| Classical-like | TNXB (tenascin-XB) | AR | No atrophic scars |
| Cardiac-valvular | COL1A2 | AR | Severe cardiac valve disease |
| Vascular | COL3A1, COL1A1 | AD | Arterial/organ rupture, thin translucent skin |
| Hypermobile | Unknown | AD | Most common; joint hypermobility, minimal skin changes |
| Arthrochalasia | COL1A1, COL1A2 | AD | Congenital hip dislocation |
| Dermatosparaxis | ADAMTS2 | AR | Severe skin fragility, sagging redundant skin |
| Kyphoscoliotic | PLOD1, FKBP14 | AR | Scoliosis, ocular fragility |
| Brittle Cornea Syndrome | ZNF469, PRDM5 | AR | Corneal fragility, keratoconus |
| Spondylodysplastic | B4GALT7, B3GALT6, SLC39A13 | AR | Short stature, skeletal dysplasia |
| Musculocontractural | CHST14, DSE | AR | Congenital contractures |
| Myopathic | COL12A1 | AD/AR | Muscle hypotonia, contractures |
| Periodontal | C1r, C1s | AD | Severe periodontitis, premature tooth loss |
Exam tip: Type IX EDS (former) is now reclassified as Occipital Horn Syndrome (= X-linked cutis laxa, mutation in ATP7A). - Andrews', p. 591
Pathogenesis
The fundamental defect lies in collagen biosynthesis:
- Collagen provides tensile strength to skin, joints, and vasculature
- Mutations in structural collagen genes or post-translational modifying enzymes disrupt fibrillogenesis
- Result: structurally weak collagen fibrils → skin fragility, joint laxity, vascular fragility
- Classical EDS: Type V collagen deficiency → abnormal fibril diameter regulation
- Vascular EDS: Type III collagen deficiency → affects mid-sized arteries, hollow organs
- Kyphoscoliotic EDS: lysyl hydroxylase deficiency (PLOD1) → defective cross-linking
Robbins & Cotran Pathologic Basis of Disease, p. 147
Clinical Features
Skin Features
| Feature | Description |
|---|---|
| Skin hyperextensibility | Skin stretches widely, recoils easily (unlike cutis laxa where it hangs) |
| Skin fragility | Minor trauma → disproportionate gaping tears, relatively painless |
| Atrophic "cigarette paper" scars | Wide, thin, wrinkled scars especially on knees, elbows, forehead, chin |
| Molluscoid pseudotumors | Calcified/fibrotic hematomas over pressure points (elbows, fingers, knees) |
| Spheroids | Small hard calcified nodules on forearms/shins; detectable on X-ray |
| Piezogenic pedal papules | Fat herniation at heels/wrists under pressure |
| Easy bruising | Especially on shins; persistent hyperpigmentation |
| Velvety, soft, doughy skin texture | Characteristic feel |
| Epicanthal folds | In childhood (may not persist) |
| Acrocyanosis / chilblains | Occasionally described |
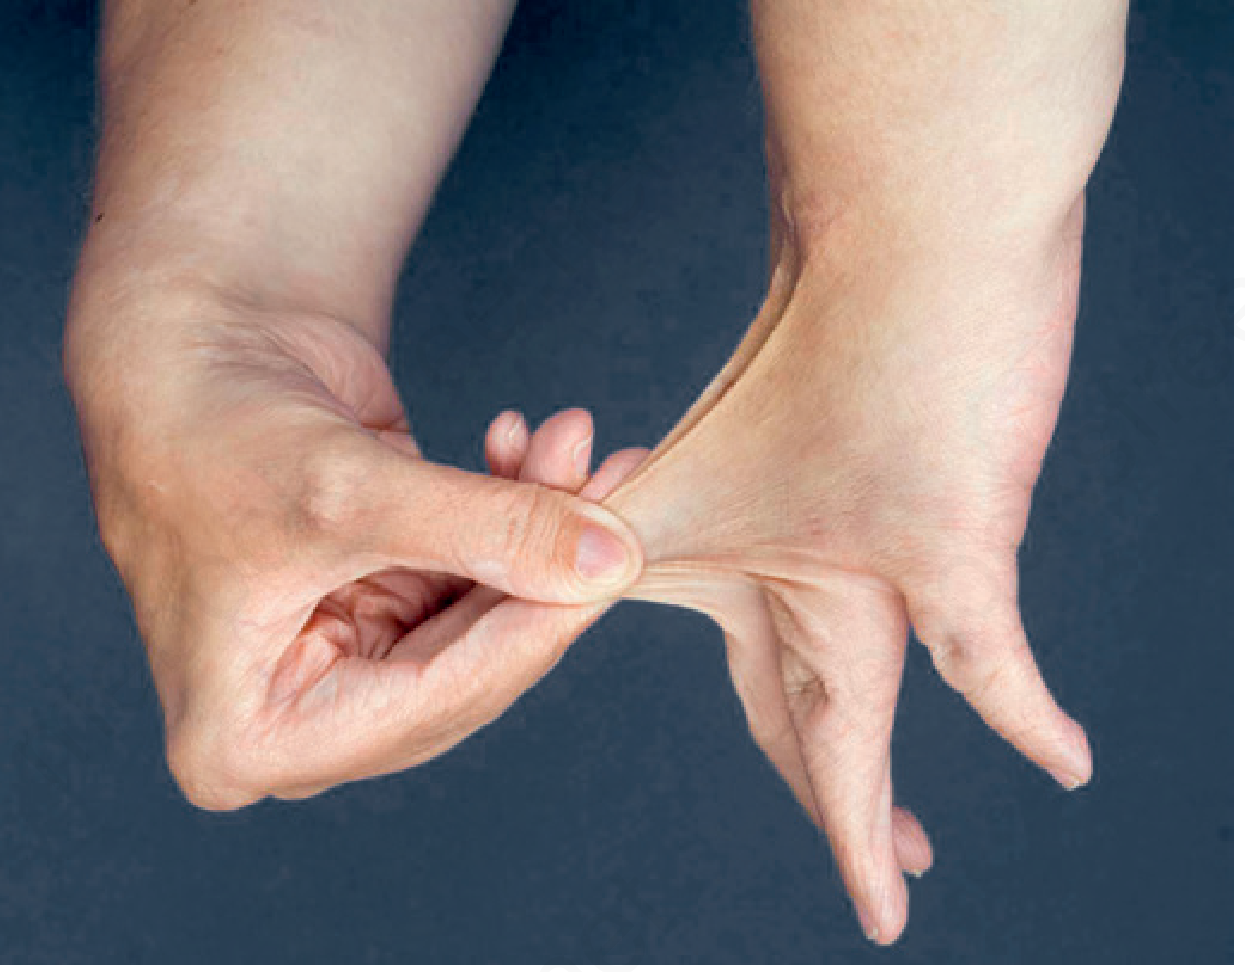
Fig. - EDS skin hyperextensibility. Note the skin recoils to normal shape on release (unlike cutis laxa). From Andrews' Diseases of the Skin.
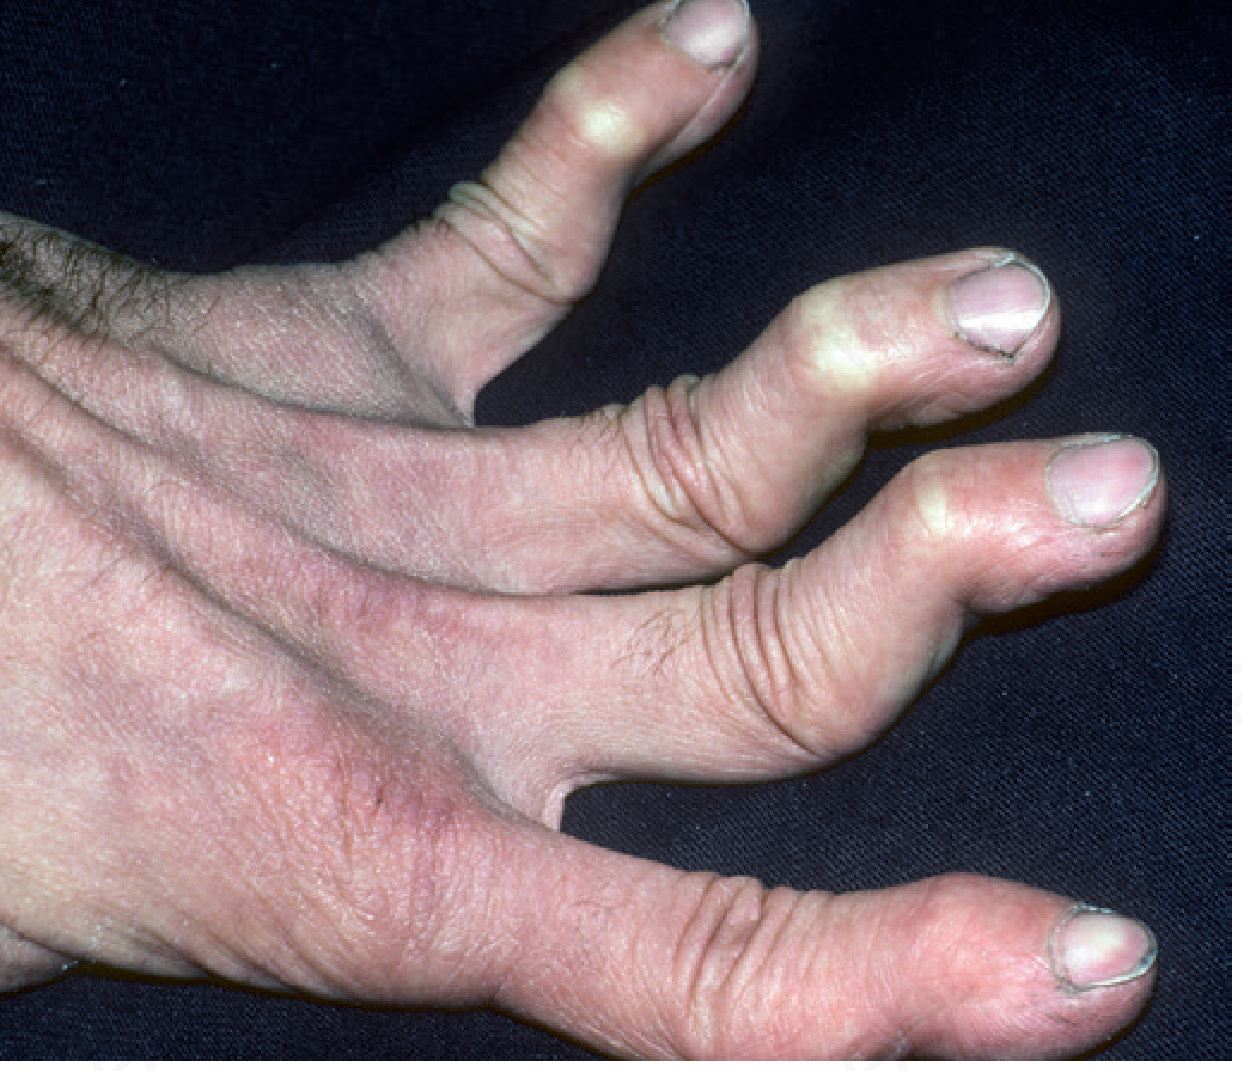
Fig. - Hyperextensible joints in EDS. From Andrews' Diseases of the Skin.
Joint Features
- Generalized joint hypermobility - greatest at fingers and wrists
- Assessed by the Beighton scale (score ≥5/9 confirms hypermobility)
- 5-point questionnaire for adults (Beighton criteria less reliable with age)
- Frequent sprains, subluxations, dislocations (shoulder, patella, TMJ most common in hEDS)
- Scoliosis, pes planus
- Chronic joint/limb pain - often misdiagnosed as fibromyalgia or chronic fatigue syndrome
- Early-onset osteoarthritis
Extracutaneous Features
| System | Manifestations |
|---|---|
| Cardiovascular | Aortic root dilation (cEDS); mitral valve prolapse; arterial rupture (vEDS - commonest cause of death) |
| GI | Sigmoid colon rupture ~25-30% of vEDS; rectal prolapse |
| Respiratory | Spontaneous pneumothorax ~12% vEDS |
| Ocular | Keratoconus, myopia, blue sclerae (kyphoscoliotic type); corneal fragility (brittle cornea syndrome) |
| Neuromuscular | Muscle hypotonia, delayed motor development, dysautonomia (hEDS) |
| Obstetric | Preterm delivery, uterine rupture in vEDS (12-25% maternal fatality rate) |
Important Subtype Details
Classical EDS (Most testable)
- Gene: COL5A1 (most common), rare COL1A1
- Inheritance: AD
- Hallmark: skin hyperextensibility + atrophic scars + joint hypermobility
- Skin assessment: pinch volar forearm, pull to resistance - Remvig criteria
- Wound healing: poor, frequent dehiscence, secondary intention often needed
Vascular EDS (Most dangerous)
- Gene: COL3A1 (Type III collagen)
- Inheritance: AD
- Median life span: ~51 years
- Thin, translucent skin with visible veins (especially face, arms, chest)
- Characteristic facial features: prominent eyes, small chin, thin lips, lobeless ears
- Spontaneous arterial rupture (3rd-4th decade peak) - mesenchymal, splenic, renal, descending aorta
- Aortic rupture typically NOT preceded by aortic dilation (unlike Marfan syndrome)
- Bowel (sigmoid) rupture in 25-30%
- Carotid-cavernous sinus fistula - medical emergency
- Varicose veins before age 20 = clinical red flag for vEDS
Dermatosparaxis EDS
- Gene: ADAMTS2 (procollagen I N-proteinase)
- Inheritance: AR
- Extremely fragile, sagging, redundant skin
- Premature rupture of membranes
- Was called "type VIIC" in old classification
Kyphoscoliotic EDS
- Gene: PLOD1 (lysyl hydroxylase-1) or FKBP14
- Inheritance: AR
- Congenital scoliosis, ocular fragility, muscle hypotonia
- Urine lysylpyridinoline:hydroxylysylpyridinoline ratio elevated - used for diagnosis
Histopathology
- Light microscopy: Often normal or subtle; collagen fibers may appear loose and irregular
- Electron microscopy: Abnormal collagen fibril morphology - irregular fibril diameters, "cauliflower" fibrils (classical EDS) - most diagnostic
- Elastin fibers are normal
- In vEDS: markedly reduced type III collagen on skin fibroblast culture
Key Differentials
| Condition | Key Distinction |
|---|---|
| Cutis Laxa | Skin hangs loosely, does not recoil after stretching (vs. EDS where skin recoils) |
| Marfan syndrome | Fibrillin-1 mutation; ectopia lentis; aortic dilation typically precedes rupture |
| Pseudoxanthoma Elasticum | Calcium deposits in elastic fibers; "plucked chicken skin"; angioid streaks |
| Osteogenesis Imperfecta | Collagen type I; bone fragility; blue sclerae; hearing loss |
Diagnosis
- Clinical - based on major and minor criteria per 2017 classification for each subtype
- Beighton scale for joint hypermobility (≥5/9)
- Molecular genetic testing - gene panel (confirmatory for most types)
- Skin fibroblast culture - type III collagen quantification (vEDS)
- Urine LNPK ratio - kyphoscoliotic EDS
- Skin biopsy + EM - fibril morphology
- Echocardiography, vascular imaging (CT/MRI) for vascular and cardiac subtypes
Treatment
No curative therapy exists. Management is supportive and multidisciplinary:
| Domain | Intervention |
|---|---|
| Wound care | Avoid tension, use Steri-strips, prolonged suture retention, avoid skin adhesives |
| Surgery | High risk - prolonged wound healing; use deep mattress sutures; anticipate dehiscence |
| Joints | Physiotherapy, bracing, avoid high-impact activities; surgical stabilization for recurrent dislocations |
| Vascular EDS | Celiprolol (beta-1 blocker) shown to reduce arterial events; avoid unnecessary arterial procedures |
| Pain | Multidisciplinary pain management |
| Genetic counseling | Essential for all patients and families |
| Screening | Echocardiography, ophthalmology referral as indicated |
| Obstetric | High-risk pregnancy management; caution in vEDS (12-25% maternal mortality) |
Celiprolol is the only drug with evidence specifically in vascular EDS (reduces arterial events).
Exam High-Yield Points
- 2017 classification = 13 subtypes (previously 6 in Villefranche 1997 classification)
- Classical EDS = Type V collagen defect (COL5A1), AD
- Vascular EDS = Type III collagen defect (COL3A1), AD - most lethal, median survival 51 years
- Dermatosparaxis = ADAMTS2 mutation - most severe skin fragility
- Kyphoscoliotic = PLOD1 (lysyl hydroxylase deficiency) - urine LNPK ratio diagnostic
- Former Type IX EDS = now Occipital Horn Syndrome = X-linked cutis laxa (ATP7A)
- EDS skin recoils after stretching; cutis laxa skin does not
- Beighton score ≥5/9 confirms generalized hypermobility
- "Cigarette paper" or "fish mouth" scars = pathognomonic description of classical EDS scarring
- Molluscoid pseudotumors + spheroids = classical EDS
- In vEDS, aortic rupture is NOT preceded by aortic dilation (unlike Marfan)
- Hypermobile EDS = most common type; gene unknown; diagnosis purely clinical
- Celiprolol = drug of choice in vascular EDS for reducing arterial events
- Most EDS types are AD except: classical-like, cardiac-valvular, dermatosparaxis, kyphoscoliotic, brittle cornea, spondylodysplastic, musculocontractural = AR
Sources: Fitzpatrick's Dermatology (8th ed.), p. 1247-1251; Andrews' Diseases of the Skin, p. 591; Robbins & Cotran Pathologic Basis of Disease, p. 147
Write in detail about collagen vascular diseases
Finding Sources
Finding Sources
Finding Sources
Now let me read the key dermatology sections - Andrews' SLE, Fitzpatrick's dermatomyositis, and also search for Fitzpatrick's SLE and scleroderma sections in parallel.
Reading File
Finding Sources
Finding Sources
Read rooks
Finding Sources
Finding Sources
The library has 4 dermatology textbooks available:
| # | Title | ISBN |
|---|---|---|
| 1 | Andrews' Diseases of the Skin - Clinical Dermatology | 9780323547536 |
| 2 | Andrews' Diseases of the Skin - Clinical Atlas, 2e | 9780323790130 |
| 3 | Fitzpatrick's Dermatology - Vol. 1 & 2 | 9780071837781 |
| 4 | Dermatology 2-Volume Set 5e (Bolognia) | 9780702082252 |
Unfortunately, Rook's Textbook of Dermatology is not available in the library. The "Dermatology 2-Volume Set 5e" (ISBN 9780702082252) is Bolognia's Dermatology, which is another premier reference.
The library also contains several other relevant texts that cover dermatological topics:
- IADVL and Compendium do not appear to be in the current library either.
For your collagen vascular disease question and all future study, I'll draw from:
- Fitzpatrick's (primary - most comprehensive)
- Andrews' (concise, exam-focused)
- Bolognia (clinical detail + images)
- Robbins & Cotran (pathogenesis)
Shall I proceed with the Collagen Vascular Diseases detailed note using these available textbooks?
Not robins , iadvl and compendium and Fitzpatrick and bolognia
Understood. The available dermatology textbooks in the library are:
- ✅ Fitzpatrick's Dermatology (Vol. 1 & 2) - available
- ✅ Bolognia's Dermatology (2-Volume Set 5e) - available
- ✅ Andrews' Diseases of the Skin - available
- ❌ Rook's Textbook of Dermatology - NOT in the library
- ❌ IADVL Textbook of Dermatology - NOT in the library
- ❌ Compendium of Dermatology - NOT in the library
For your exam preparation, I'll use Fitzpatrick + Bolognia + Andrews as the primary sources (these are the gold-standard references anyway), supplemented by Robbins for pathogenesis where helpful.
Shall I now proceed with the detailed write-up on Collagen Vascular Diseases using these three books?
Yes
Finding Sources
Finding Sources
Finding Sources
Excellent - I have all section locations. Now reading key content in parallel from all 4 major sections.
Reading File
Reading File
Reading File
Reading File
Good content flowing in. Now let me read the main SLE Fitzpatrick chapter, the DM detailed section, and MCTD/Sjogren sections.
Reading File
Reading File
Reading File
Good. Now let me read the Fitzpatrick SLE extracutaneous overview, the Andrews SLE cutaneous section, and the Sjogren chapter from Fitzpatrick.
Reading File
Reading File
Reading File
Excellent. Now let me get the Dermatomyositis and SSc treatment/antibody content from Fitzpatrick and Bolognia.
Reading File
Reading File
I now have comprehensive content from Fitzpatrick, Bolognia, and Andrews. Here is the complete detailed note:
Collagen Vascular Diseases (Connective Tissue Diseases) - Detailed Note
Collagen Vascular Diseases (CVDs) are a heterogeneous group of autoimmune disorders characterized by inflammation, immune dysregulation, and damage to connective tissue (skin, joints, muscles, blood vessels, and internal organs). The term is somewhat a misnomer - the primary abnormality is immune-mediated, not a primary collagen defect.
Group includes:
- Systemic Lupus Erythematosus (SLE)
- Systemic Sclerosis (Scleroderma)
- Dermatomyositis / Polymyositis
- Sjögren Syndrome
- Mixed Connective Tissue Disease (MCTD)
- Rheumatoid Arthritis (RA) - covered briefly
1. SYSTEMIC LUPUS ERYTHEMATOSUS (SLE)
Definition
A chronic, multisystem autoimmune disease characterized by formation of autoantibodies (especially anti-dsDNA and anti-Sm) causing widespread tissue damage via immune complex deposition.
Epidemiology
- F:M ratio = 9:1 (reproductive age women predominantly)
- Peak age: 15-40 years
- More severe in African-Americans and Asians
- Prevalence: ~1 in 2000 women
Pathogenesis
- Central defect: Failure to clear apoptotic cells → nuclear antigens exposed → loss of self-tolerance
- UV light, hormones (estrogen), infections, drugs trigger flares
- Type I interferon pathway is upregulated (IFN-α)
- Auto-antibodies + complement activation → immune complex deposition in skin (lupus band), kidneys, joints
- Key autoantibodies:
| Antibody | Specificity | Association |
|---|---|---|
| Anti-dsDNA | 95% specific | Disease activity, nephritis |
| Anti-Sm | 99% specific | Most specific for SLE |
| Anti-Ro/SS-A | 60-70% | Neonatal lupus, SCLE, photosensitivity |
| Anti-La/SS-B | 40% | Neonatal lupus, secondary Sjögren |
| Anti-histone | - | Drug-induced lupus |
| Anti-phospholipid | - | APS, thrombosis, recurrent miscarriages |
| ANA | 95% sensitive | Screening (not specific) |
- Fitzpatrick's Dermatology, Vol. 1-2, p. 1200
Classification of Cutaneous Lupus (Gilliam Classification)
A. LE-SPECIFIC LESIONS (show interface dermatitis on biopsy)
I. Acute Cutaneous LE (ACLE)
- Localized ACLE: Classic butterfly (malar) rash - fixed erythema over malar eminences + nose bridge, spares nasolabial folds (key distinction from dermatomyositis which does NOT spare NLF)
- Lasts days to weeks; heals without scarring
- Generalized ACLE: Widespread maculopapular photosensitive eruption; may resemble TEN (toxic epidermal necrolysis) in severe cases
II. Subacute Cutaneous LE (SCLE)
- Photodistributed eruption in 2 forms:
- Annular/polycyclic (most common, ~50%)
- Papulosquamous (psoriasiform)
- Favors V-neck area, upper back, shoulders
- Heals without scarring (unlike DLE)
- Strongly associated with anti-Ro/SS-A antibodies (>80%)
- HLA-B8, DR2, DR3 association
- Drug-induced SCLE: Hydrochlorothiazide, terbinafine, TNF-alpha inhibitors, PPIs, calcium channel blockers
III. Chronic Cutaneous LE (CCLE)
a) Discoid Lupus Erythematosus (DLE) - Most common CCLE
- Well-demarcated erythematous plaques → adherent hyperkeratotic scale (carpet tack sign - scale extends into follicular ostia) → atrophy → depigmentation centrally with hyperpigmentation at margins → scarring alopecia (irreversible)
- Favors face (especially malar, nose, ears), scalp, oral mucosa
- ~5% of DLE patients develop SLE; ~20% SLE patients have DLE
- Ear involvement ("DLE of the ears") is characteristic
- "Inverted ice cream cone" appearance on dermoscopy
b) LE Profundus / LE Panniculitis (Kaposi-Irrgang disease)
- Firm nodules (1-3 cm) in lower dermis/subcutis
- Overlying skin tethered → deep saucerized depressions
- Head, proximal arms, breasts, buttocks, thighs
- "Lupus mastitis" - breast nodules mimicking carcinoma
- ~50% have evidence of SLE; ~70% also have DLE lesions
c) Chilblain Lupus Erythematosus
- Purple-red patches/plaques on toes, fingers, face
- Precipitated by cold, damp climate
- Associated with anti-Ro/SS-A antibodies
- ~20% later develop SLE
d) Lupus Tumidus (LE Tumidus)
- Urticarial/succulent plaques with NO surface change (no scale, no atrophy)
- Highly photosensitive
- Most photosensitive variant; responds best to antimalarials
- Biopsy: dermal mucin deposition with perivascular/periadnexal lymphocytic infiltrate, minimal/no interface change
B. LE-NONSPECIFIC LESIONS (not diagnostic but common in SLE)
- Vasculitis, livedo reticularis
- Raynaud phenomenon (30%)
- Periungual telangiectasias (glomeruloid nail fold loops - differ from DM/SSc)
- Bullous LE (neutrophils at DEJ; anti-type VII collagen antibodies; responds to dapsone)
- Rowell syndrome (EM-like lesions + SLE)
- "Lupus hairs" - short hairs at frontal hairline (telogen effluvium + fragility)
- Diffuse non-scarring alopecia
- Oral ulcers (painless - criterion feature)
- Leg ulcers (punched out, deep)
Extracutaneous Manifestations of SLE
| System | Manifestations |
|---|---|
| Musculoskeletal | Arthralgia, non-erosive arthritis (Jaccoud arthropathy), myositis, AVN |
| Renal | Lupus nephritis (WHO class II-V); proteinuria, hematuria, RBC casts |
| Cardiac | Libman-Sacks endocarditis (verrucous, non-bacterial); pericarditis, myocarditis |
| Pulmonary | Pleuritis, shrinking lung syndrome, pulmonary hemorrhage |
| Neuropsychiatric | Seizures, psychosis, cognitive dysfunction, chorea, aseptic meningitis |
| Hematologic | AIHA (Coombs+), leukopenia, lymphopenia, thrombocytopenia |
| GI | Mesenteric vasculitis, hepatitis, pancreatitis |
| Ocular | Retinal vascular disease, "cytoid bodies" |
- Fitzpatrick's Dermatology, p. 1202-1203
Diagnostic Criteria for SLE
1982 ACR Criteria (need ≥4 of 11):
- Malar rash
- Discoid rash
- Photosensitivity
- Oral ulcers (painless)
- Arthritis (non-erosive, ≥2 joints)
- Serositis (pleuritis or pericarditis)
- Renal disorder (proteinuria >0.5g/day or casts)
- Neurologic disorder (seizures or psychosis)
- Hematologic disorder (AIHA/leukopenia/lymphopenia/thrombocytopenia)
- Immunologic disorder (anti-dsDNA, anti-Sm, APLAs)
- Positive ANA
SLICC Criteria (2012): More sensitive; need ≥4 criteria (at least 1 clinical + 1 immunologic), OR biopsy-proven lupus nephritis + ANA or anti-dsDNA.
Histopathology of LE
- Interface dermatitis - basal layer vacuolization + lymphocytic infiltrate
- Superficial and deep perivascular/periadnexal lymphocytic infiltrate
- Dermal mucin deposition (especially in lupus tumidus)
- Lupus Band Test (LBT): DIF shows granular IgG + C3 at DEJ (BMZ)
- Positive in lesional skin in all types of LE
- Positive in non-lesional sun-exposed skin in SLE (~75%)
- Positive in non-lesional non-sun-exposed skin in SLE (~50%) - most specific for SLE
Neonatal Lupus Erythematosus
- Passive transfer of maternal anti-Ro/SS-A (and anti-La/SS-B) across placenta
- Annular erythematous plaques on face/scalp (periorbital "raccoon eyes" pattern)
- Congenital complete heart block (CHB) - most serious; anti-Ro induced damage to AV node (permanent)
- Cytopenias, hepatic dysfunction - transient
- Skin resolves by 6-8 months as maternal antibodies cleared
Treatment of SLE
| Level | Treatment |
|---|---|
| Photoprotection | Sunscreen SPF ≥30 (UVA+UVB), protective clothing |
| Topical | Corticosteroids (Class I-III); tacrolimus/pimecrolimus for face |
| Antimalarials | Hydroxychloroquine (first-line for all SLE) 200-400 mg/day; chloroquine, quinacrine; reduces flares, prevents organ damage, reduces mortality |
| Systemic CS | Prednisone - for acute flares |
| Steroid-sparing | Methotrexate (skin, joints), azathioprine, mycophenolate mofetil (nephritis) |
| Biologics | Belimumab (anti-BLyS/BAFF; FDA approved for SLE); anifrolumab (anti-IFN-αR) |
| Nephritis | Cyclophosphamide (induction severe nephritis), MMF, rituximab |
Key point: Hydroxychloroquine is the backbone of SLE treatment. Regular ophthalmologic screening required (retinopathy risk, especially after 5 years or >5mg/kg/day).
2. SYSTEMIC SCLEROSIS (SSc / SCLERODERMA)
Definition
A multisystem autoimmune disease characterized by the triad of:
- Vasculopathy (Raynaud phenomenon, digital ulcers)
- Immune dysregulation (autoantibodies, inflammation)
- Fibrosis of skin and internal organs
- Fitzpatrick's Dermatology, p. 1115
Epidemiology
- F:M = 3:1 to 14:1; peak age 35-50 years
- Higher incidence in Black individuals (earlier onset, more diffuse disease)
- Prevalence: ~275 per million (US)
- Highest case-specific mortality of any autoimmune rheumatic disease
- 10-year survival ~70%
Classification
| Feature | Diffuse cutaneous SSc (dcSSc) | Limited cutaneous SSc (lcSSc) |
|---|---|---|
| Skin involvement | Proximal to elbows/knees; trunk, face | Distal to elbows/knees; face only |
| RP onset | Within 1 year of skin changes | Years before skin changes |
| Course | Rapid progression | Slow progression |
| Organ involvement | Lung fibrosis, SRC common | PAH, CREST syndrome |
| Antibodies | Anti-Scl-70 (anti-topoisomerase I), anti-RNA pol III | Anti-centromere (ACA) |
| Nailfold capillaries | Early dropout | Late dropout |
CREST Syndrome (a subset of lcSSc):
- C - Calcinosis cutis
- R - Raynaud phenomenon
- E - Esophageal dysmotility
- S - Sclerodactyly
- T - Telangiectasia (mat-like telangiectasias)
- Associated with anti-centromere antibodies (ACA)
- Risk of pulmonary arterial hypertension (PAH) without pulmonary fibrosis
Pathogenesis
Three core processes:
- Vascular injury - endothelial cell activation → intimal proliferation → obliterative vasculopathy → Raynaud, digital ulcers
- Immune activation - T-cell activation, B-cell hyperreactivity → autoantibodies
- Fibrosis - TGF-β drives fibroblast activation → excess collagen production
Clinical Features
Cutaneous Manifestations (in sequence)
| Stage | Features |
|---|---|
| Edematous phase | Puffy, non-pitting edema of hands ("sausage fingers") - often misdiagnosed as carpal tunnel |
| Indurative/sclerotic phase | Skin becomes smooth, tight, firm, yellowish, bound down ("hidebound") |
| Atrophic phase | Thin, atrophic skin |
Specific skin signs:
- Sclerodactyly - tightening of finger skin → "claw hand"
- Facial changes - expressionless face, radial furrowing around mouth (perioral rhagades), microstomia, pinched nose, "Mephistophelean" facies
- Raynaud phenomenon - triphasic color change: white (pallor) → blue (cyanosis) → red (hyperemia); often FIRST manifestation
- Digital ulcers - fingertip necrosis/pitting scars (ischemic)
- Calcinosis cutis - calcium deposits in skin and subcutaneous tissue (especially fingers)
- Telangiectasias - mat-like (dilated capillary mats), especially face, lips, hands
- "Salt and pepper" pigmentation - perifollicular hyperpigmentation with surrounding hypopigmentation (especially neck, trunk)
- Piezogenic papules, acral changes
- Mat telangiectasias on face, lips, oral mucosa
- Nailfold capillaroscopy: Dilated, tortuous loops with avascular areas ("scleroderma pattern") - also seen in DM
ACR Criteria for SSc (1980, 97% sensitive, 98% specific):
- Major criterion: Proximal scleroderma (skin changes proximal to MCP/MTP joints)
- Minor criteria (≥2 of 3):
- Sclerodactyly
- Digital pitting scars/fingertip loss of substance
- Bilateral basilar pulmonary fibrosis
Extracutaneous Manifestations
| System | Features |
|---|---|
| GI | Esophageal dysmotility (most common visceral; dysphagia, GERD), "watermelon stomach" (GAVE), small bowel → malabsorption, wide-mouthed diverticula in colon |
| Lung | Interstitial lung disease/pulmonary fibrosis (leading cause of death), PAH |
| Kidney | Scleroderma Renal Crisis (SRC) - sudden hypertension, oliguria, microangiopathy; associated with anti-RNA pol III; treat with ACE inhibitors |
| Heart | Pericarditis, myocardial fibrosis, arrhythmias |
| MSK | Arthralgias, "tendon friction rubs" (dcSSc) |
| ENT | Xerostomia, trigeminal neuropathy |
Autoantibodies in SSc
| Antibody | SSc subtype | Clinical association |
|---|---|---|
| Anti-Scl-70 (anti-topoisomerase I) | dcSSc | Pulmonary fibrosis, poor prognosis |
| Anti-centromere (ACA) | lcSSc/CREST | PAH, limited disease, calcinosis |
| Anti-RNA Polymerase III | dcSSc | Scleroderma Renal Crisis |
| Anti-U1-RNP | Overlap/MCTD | Myositis overlap |
| Anti-PM-Scl | SSc-myositis overlap | - |
| Anti-Th/To | lcSSc | PAH, ILD |
Histopathology of SSc
- Early: Dermal edema, perivascular lymphocytic infiltrate, dilated blood vessels
- Established: Dense, homogeneous collagen bundles filling dermis → collagen extends into subcutis; adnexal structures (eccrine glands) trapped in collagen; vessels show intimal thickening
Treatment of SSc
| Manifestation | Treatment |
|---|---|
| Raynaud | CCBs (nifedipine first-line); PDE5 inhibitors; prostanoids (iloprost IV) for digital ulcers |
| Digital ulcers | Bosentan (endothelin receptor antagonist), sildenafil |
| PAH | Bosentan, sildenafil, riociguat; prostacyclins |
| ILD/Pulmonary fibrosis | Nintedanib (first approved), cyclophosphamide, MMF |
| SRC | ACE inhibitors (captopril) - mainstay; avoid steroids (can precipitate SRC) |
| Skin fibrosis | Methotrexate (early dcSSc), autologous HSCT (severe dcSSc) |
| GERD/GI | PPIs, prokinetics |
3. DERMATOMYOSITIS (DM)
Definition
An idiopathic inflammatory myopathy with characteristic cutaneous and muscle involvement. Classified within the spectrum of inflammatory myopathies alongside polymyositis (PM) and inclusion body myositis (IBM).
Epidemiology
- Bimodal age distribution: juvenile (5-14 yrs) and adult (45-65 yrs)
- F:M = 2:1
- Adult DM carries 18-25% risk of malignancy (higher than PM)
- Juvenile DM: NO increased malignancy risk (key distinction)
Cutaneous Manifestations - PATHOGNOMONIC SIGNS
1. Gottron Papules
- Pathognomonic for DM
- Flat-topped violaceous papules/plaques over bony prominences of hands - especially DIP, PIP, MCP joints (dorsal surface)
- Extension onto extensor tendons also seen
- Key: Over INTERPHALANGEAL JOINTS (vs. psoriasis which involves skin between joints)
- May show overlying scale or central erosion (anti-MDA5 DM)
2. Gottron Sign
- Pathognomonic for DM
- Violaceous erythema (not raised papules) over bony prominences:
- Knuckles, elbows, knees, medial malleoli, dorsum of feet
- May show poikiloderma (atrophy + telangiectasia + pigmentation changes)
CHARACTERISTIC SIGNS (Highly specific, not pathognomonic):
| Sign | Description |
|---|---|
| Heliotrope rash | Violaceous/purple-red periorbital rash with edema; "heliotrope" (purple flower); involves eyelids (especially upper) |
| Shawl sign | Poikilodermatous erythema over posterior neck, shoulders, upper back (in a "shawl" distribution) |
| V-sign | Erythema over anterior chest and neck in V-shaped distribution |
| Holster sign | Erythema/poikiloderma on lateral thighs (where holster would be) |
| Mechanics hands | Hyperkeratotic, cracked, fissured skin on lateral and palmar fingers/hands resembling manual worker hands; associated with anti-synthetase syndrome (anti-Jo-1) |
| Nailfold changes | Periungual telangiectasias, dilated capillary loops with hemorrhage, ragged cuticles (cuticular hypertrophy) |
| Flagellate erythema | Linear "whip-like" streaks on trunk/back (also seen with bleomycin toxicity) |
| Calcinosis cutis | More common in juvenile DM; calcium deposits in skin/muscle |
Key distinction: Heliotrope rash + periorbital edema = DM. The nasolabial fold is NOT spared in DM (unlike SLE malar rash).
Muscle Manifestations
- Proximal, symmetric muscle weakness (hip > shoulder girdle)
- Difficulty climbing stairs, rising from chair, raising arms overhead
- Myalgia, tenderness
- Dysphagia (pharyngeal/esophageal muscle involvement)
- Dysphonia
- Amyopathic dermatomyositis (ADM): Cutaneous DM without clinical/biochemical myositis for ≥6 months (~10-20% of DM)
Extracutaneous Features
- ILD (Interstitial Lung Disease): ~30-40%; especially with anti-Jo-1 and anti-MDA5
- Raynaud phenomenon
- Cardiac: myocarditis, arrhythmias
- Calcinosis cutis (juvenile DM mainly)
- Constitutional: fever, weight loss, fatigue
Autoantibodies in DM
| Antibody | Association |
|---|---|
| Anti-Jo-1 (anti-histidyl-tRNA synthetase) | Anti-synthetase syndrome: ILD, mechanics hands, arthritis, fever, Raynaud |
| Anti-Mi-2 | Classical DM; shawl sign, V-sign; good prognosis |
| Anti-MDA5 | ADM + severe ILD (rapidly progressive), palmar papules, oral ulcers, ulcerations in Gottron papules; poor prognosis |
| Anti-TIF1-γ (anti-p155/140) | Malignancy-associated DM (adults); cancer marker |
| Anti-NXP-2 | Juvenile DM + calcinosis; adult DM + malignancy |
| Anti-SRP | Necrotizing myopathy; severe disease, cardiac involvement |
| Anti-SAE | Skin rash before myositis; dysphagia |
Malignancy in DM
- Risk is highest in the first year post-diagnosis, then declines
- Associated cancers: Lung, breast, ovarian, cervical, GI (gastric, colorectal), pancreatic, prostate
- Asian populations: Nasopharyngeal carcinoma more common
- Anti-TIF1-γ antibody = most important marker for malignancy
- All adult DM patients need cancer screening at diagnosis + long-term surveillance
Histopathology of DM
- Interface dermatitis with vacuolar degeneration of basal layer
- Perifascicular atrophy on muscle biopsy (diagnostic of DM)
- Perivascular + perimysial inflammation (CD4+ T cells, B cells, dendritic cells)
- Membrane attack complex (MAC) deposition on capillaries
Investigations
- Elevated muscle enzymes: CK (most sensitive), LDH, aldolase, AST, ALT
- EMG: myopathic pattern
- MRI muscle: edema, inflammation
- Muscle biopsy: perifascicular atrophy (DM); endomysial inflammation (PM)
- Skin biopsy: interface dermatitis (similar to LE)
- ANA positive in ~80%
Treatment of DM
| Line | Treatment |
|---|---|
| First-line | Systemic corticosteroids - prednisone 1-1.5mg/kg/day |
| Steroid-sparing | Methotrexate (skin + muscle), azathioprine |
| Skin-directed | Hydroxychloroquine, sunscreen, topical steroids |
| Refractory DM | IVIG (monthly), rituximab, cyclosporine (especially ILD in anti-MDA5), JAK inhibitors (ruxolitinib) |
| ILD | Tacrolimus + cyclosporine for rapidly progressive ILD (anti-MDA5) |
| Calcinosis | Diltiazem, probenecid, bisphosphonates (limited evidence) |
4. SJÖGREN SYNDROME
Definition
A chronic systemic autoimmune disorder characterized by lymphocytic infiltration and destruction of exocrine glands (mainly salivary and lacrimal) → dry mouth (xerostomia) and dry eyes (xerophthalmia/keratoconjunctivitis sicca).
- Primary Sjögren (pSS): Occurs alone
- Secondary Sjögren: Coexists with RA (most common), SLE, SSc, DM, PBC
Epidemiology
- F:M = 9:1 (most female-predominant rheumatic disease)
- Peak age: 4th-5th decade
- Prevalence: 0.2-2.7% (whites); one of the most common rheumatic diseases
Pathogenesis
- Type I interferon pathway upregulation (central role)
- Plasmacytoid dendritic cells + autoreactive lymphocytes
- CD4+ T cell infiltration of glands → acinar cell apoptosis → gland destruction
- B-cell hyperreactivity → autoantibody production
- Genetic factors: HLA-DR3, HLA-DQ2
Clinical Features
Glandular (Sicca Complex)
- Xerostomia: Dry mouth, difficulty chewing/swallowing, dental caries, parotid gland enlargement
- Xerophthalmia: Dry eyes, foreign body sensation, photophobia, corneal ulceration (keratoconjunctivitis sicca)
- Other: dry nose, dry vagina, dry trachea/bronchi
Extraglandular
| System | Features |
|---|---|
| Skin | Dry skin (xerosis), palpable purpura (vasculitis - most common cutaneous feature), annular erythema (pSS-specific), urticaria |
| MSK | Non-erosive arthritis, myalgia |
| Pulmonary | ILD, lymphocytic interstitial pneumonia (LIP) |
| Renal | Renal tubular acidosis (Type I, distal), interstitial nephritis |
| Neurologic | Peripheral neuropathy (especially sensory), CNS involvement, autonomic dysfunction |
| Lymphoma | 40-fold increased risk of B-cell NHL (mucosa-associated lymphoid tissue - MALT lymphoma); most important complication |
Autoantibodies
- Anti-Ro/SS-A: ~70% of pSS (most common)
- Anti-La/SS-B: ~40% of pSS (more specific)
- ANA: ~80%
- RF: ~75%
Diagnosis - Schirmer Test + Other
- Schirmer test: Filter paper in lower conjunctival fornix for 5 minutes; <5mm wetting = positive for dry eyes
- Rose Bengal stain / Lissamine Green stain: corneal epithelial damage
- Salivary flow rate: Unstimulated salivary flow <1.5 mL/15 min
- Lip/salivary gland biopsy: Focal lymphocytic sialadenitis (focus score ≥1 focus/4mm²)
- Parotid scintigraphy
Treatment
- Sicca symptoms: Artificial tears, saliva substitutes, pilocarpine (muscarinic agonist) for xerostomia/xerophthalmia
- Extraglandular: Hydroxychloroquine, corticosteroids, rituximab (for severe extraglandular)
- Lymphoma: Chemotherapy (RCHOP)
5. MIXED CONNECTIVE TISSUE DISEASE (MCTD)
Definition (Sharp Syndrome)
Overlapping clinical features of SLE + SSc + myositis + RA with defining serologic marker of high-titer anti-U1-RNP antibodies in the absence of anti-Sm antibodies.
Key Features
- Raynaud phenomenon
- Swollen "sausage fingers" (dactylitis)
- Esophageal dysfunction
- Inflammatory arthritis
- Muscle weakness
- Pulmonary hypertension
Diagnostic Antibody
- Anti-U1-RNP (anti-nRNP): High titer - essential for diagnosis
- ANA: Speckled pattern (particulate epidermal nuclear IgG on DIF - distinctive finding)
- Absence of anti-Sm excludes SLE
Prognosis
- Better than SSc (lower incidence of renal disease)
- Causes of death: Pulmonary fibrosis/PAH, cardiovascular events, infection
- Pulmonary hypertension + Raynaud + livedo reticularis = higher mortality
Treatment
- Inflammatory features (arthritis, myositis): Prednisone 1mg/kg/day
- Long-term: Steroid-sparing agents (MTX, azathioprine)
- Refractory: Rituximab (especially thrombocytopenia - 80% response rate)
- Scleroderma features: Least likely to improve
COMPARATIVE TABLE - Key Differentiators
| Feature | SLE | SSc | DM | Sjögren | MCTD |
|---|---|---|---|---|---|
| Key antibody | Anti-dsDNA, Anti-Sm | Anti-Scl-70, ACA | Anti-Jo-1, Anti-Mi-2, Anti-TIF1-γ | Anti-Ro, Anti-La | Anti-U1-RNP |
| ANA pattern | Peripheral/rim | Nucleolar | Speckled | Speckled | Speckled |
| Skin hallmark | Malar rash (spares NLF) | Tight/bound-down skin, Raynaud | Heliotrope + Gottron papules | Annular purpura | Sausage fingers |
| Scarring | DLE only | Yes (fibrosis) | No | No | No |
| Raynaud | Occasional | Almost always (first sign) | Occasional | Occasional | Always |
| Malignancy risk | Low | Low-moderate | High (adult DM 18-25%) | MALT lymphoma | Low |
| Renal | Nephritis (common) | SRC (rare, dcSSc) | Rare | RTA Type I | Rare |
| Lung | Pleuritis | ILD, PAH | ILD (anti-Jo-1, MDA5) | LIP | PAH |
| Key treatment | Hydroxychloroquine, belimumab | ACE-I (SRC), nintedanib (ILD) | Steroids + MTX/IVIG | Pilocarpine | Steroids |
NAILFOLD CAPILLAROSCOPY IN CVDs
| Pattern | Disease |
|---|---|
| Wandering/glomeruloid loops | SLE |
| Dilated loops + capillary dropout (scleroderma pattern) | SSc, DM |
| Ectasia of one half of capillary loop | Osler-Weber-Rendu syndrome |
| Ragged cuticles + dilated loops + hemorrhage | DM |
HISTOPATHOLOGY COMPARISON
| Disease | Key Histologic Finding |
|---|---|
| SLE/LE | Interface dermatitis + granular IgG/C3 at BMZ (LBT+) |
| SSc | Dense homogeneous collagen, trapped adnexa, intimal thickening |
| DM | Interface dermatitis + perifascicular atrophy (muscle) |
| Sjögren | Focal lymphocytic sialadenitis (lip biopsy) |
HIGH-YIELD EXAM POINTS
- Anti-Sm = most SPECIFIC for SLE; anti-dsDNA = correlates with disease activity
- LBT positive in non-lesional, non-sun-exposed skin = most specific for SLE (not just DLE)
- Malar rash spares nasolabial folds (SLE); Heliotrope rash does NOT spare NLF (DM)
- Gottron papules = over joints; psoriasis plaques = between joints on dorsal hand
- Anti-MDA5 = ADM + severe rapidly progressive ILD (often fatal without aggressive treatment)
- Anti-TIF1-γ = malignancy marker in adult DM
- Anti-Jo-1 = antisynthetase syndrome (ILD + mechanics hands + arthritis + fever + Raynaud)
- CREST = anti-centromere antibody; SSc renal crisis = anti-RNA Pol III
- PAH - most common cause of death in lcSSc/CREST; ILD - leading cause of death overall in SSc
- SRC treated with ACE inhibitors; steroids can precipitate SRC
- Sjögren = 40x risk of B-cell NHL (MALT lymphoma); lymphoma risk highest with parotid swelling, purpura, low C4
- Neonatal lupus = anti-Ro/SS-A → congenital complete heart block (permanent)
- Bullous LE responds to dapsone (anti-type VII collagen antibodies)
- MCTD = anti-U1-RNP (high titer) without anti-Sm; speckled ANA; better prognosis than SSc
- Juvenile DM - NO malignancy risk; calcinosis cutis common; excellent prognosis vs. adult DM
- Drug-induced lupus: anti-histone antibodies; caused by hydralazine, procainamide, isoniazid, minocycline
- Drug-induced SCLE: hydrochlorothiazide, terbinafine, TNF-alpha inhibitors, PPIs, CCBs
- Hydroxychloroquine - backbone of SLE treatment + reduces mortality + ophthalmologic monitoring required
- Perifascicular atrophy on muscle biopsy = DM (not PM - which shows endomysial inflammation)
- GAVE (watermelon stomach) = gastric antral vascular ectasia in SSc
Sources: Fitzpatrick's Dermatology 9th ed. (Vols. 1-2), pp. 1115-1120, 1200-1210, 1283-1295; Bolognia's Dermatology 5e, pp. 843-850, 4440-4455; Andrews' Diseases of the Skin, pp. 189-205, 201-210, 290-310This is a comprehensive, exam-focused note on all major Collagen Vascular Diseases. Here's a quick summary of what's covered:
5 Major Diseases covered:
- SLE - Gilliam classification of cutaneous LE, ACR/SLICC criteria, LBT, all autoantibodies, neonatal lupus, treatment including belimumab
- Systemic Sclerosis - dcSSc vs lcSSc, CREST syndrome, all autoantibodies (Scl-70, ACA, RNA Pol III), SRC, treatment with nintedanib/bosentan/ACE inhibitors
- Dermatomyositis - Pathognomonic signs (Gottron papules vs Gottron sign), all myositis-specific antibodies (Jo-1, Mi-2, MDA5, TIF1-γ), malignancy associations, treatment
- Sjögren Syndrome - Sicca complex, extraglandular manifestations, MALT lymphoma risk, Schirmer test, pilocarpine
- MCTD - Anti-U1-RNP, Sharp syndrome, overlap features, treatment
20 high-yield exam points are compiled at the end for last-minute revision. Ask if you need any section expanded further or want to test yourself with MCQs!
This is a shared conversation. Sign in to Orris to start your own chat.