
Brachial plexus
Reading File
Finding Sources
Finding Sources
Searching Images
brachial plexus roots trunks divisions cords branches anatomical diagram
Searching PubMed
"brachial plexus" AND anatomy
Searching the Web
brachial plexus anatomy roots trunks divisions cords branches NCBI Bookshelf
Reading File
Brachial plexus
The brachial plexus is a network of nerves formed by the anterior rami of C5-T1. It supplies motor and sensory innervation to most of the upper limb.
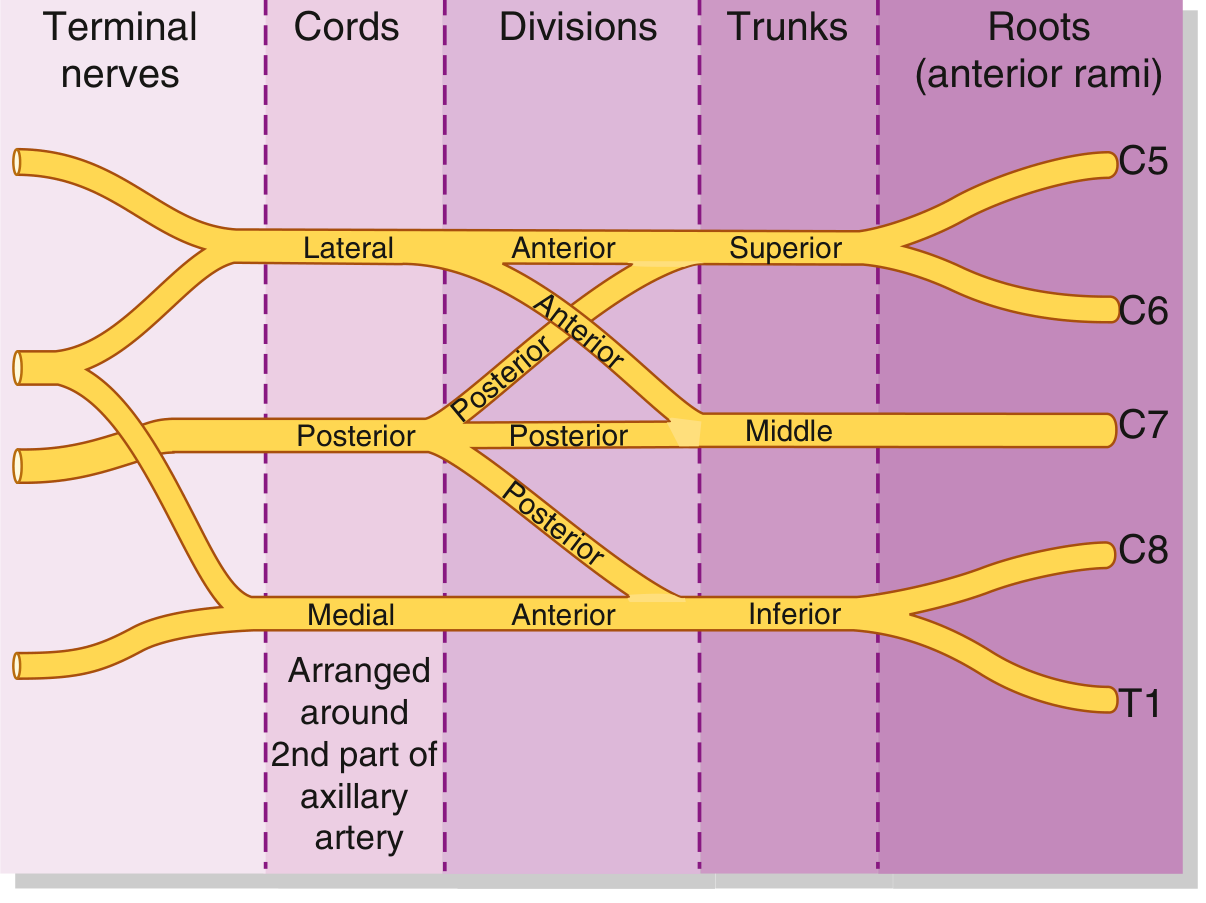
Order of components
Roots → Trunks → Divisions → Cords → Branches
Mnemonic: “Read That Damn Cadaver Book”
| Part | Arrangement |
|---|---|
| Roots | C5, C6, C7, C8, T1 |
| Trunks | Upper: C5-C6; Middle: C7; Lower: C8-T1 |
| Divisions | Each trunk splits into anterior and posterior divisions |
| Cords | Lateral, posterior, medial, named by relation to the axillary artery |
| Terminal branches | Musculocutaneous, Axillary, Radial, Median, Ulnar |
Formation of the cords
- Lateral cord: anterior divisions of upper and middle trunks
- Medial cord: anterior division of lower trunk
- Posterior cord: all three posterior divisions
Five terminal nerves
| Nerve | Main root values | Key function |
|---|---|---|
| Musculocutaneous | C5-C7 | Flexors of arm, especially biceps; sensation over lateral forearm |
| Axillary | C5-C6 | Deltoid and teres minor; sensation over lateral shoulder |
| Radial | C5-T1 | Extensors of arm and forearm; sensation over posterior limb and dorsolateral hand |
| Median | C6-T1 | Most forearm flexors, thenar muscles; sensation over lateral palm and lateral 3½ digits |
| Ulnar | C8-T1 | Most intrinsic hand muscles; sensation over medial 1½ digits |
Important collateral branches
- From roots: dorsal scapular nerve (C5), long thoracic nerve (C5-C7)
- From upper trunk: suprascapular nerve, nerve to subclavius
- From lateral cord: lateral pectoral nerve
- From medial cord: medial pectoral, medial cutaneous nerve of arm and forearm
- From posterior cord: upper and lower subscapular nerves, thoracodorsal nerve
Clinical correlations
- Upper trunk injury, C5-C6: Erb palsy, classically “waiter’s tip” posture.
- Lower trunk injury, C8-T1: Klumpke palsy, weakness of intrinsic hand muscles, possibly clawing.
- Long thoracic nerve injury: winged scapula due to serratus anterior paralysis.
- Posterior cord lesion: may affect axillary and radial nerve functions.
The plexus begins in the neck, passes between the anterior and middle scalene muscles, crosses over the first rib, and enters the axilla where its cords surround the axillary artery. Gray’s Anatomy for Students, p. 858. A concise NCBI anatomy review also summarizes the roots-to-terminal-branches sequence.
Explain brachial plexus lesions by clinical presentation
Reading File
Finding Sources
Finding Sources
Searching Images
diagram clinical patterns brachial plexus lesions Erb palsy Klumpke palsy root trunk cord
Searching PubMed
"brachial plexus injuries" AND clinical
Searching the Web
brachial plexus injury clinical presentation upper trunk lower trunk cord lesion Merck Manual
Reading File
Reading File
Reading File
Reading Web Page
https://merckmanuals.com/professional/neurologic-disorders/p…
Brachial plexus lesions cause patchy weakness, sensory loss, and reduced reflexes that do not fit one single root or peripheral nerve. The clinical pattern helps localize the lesion.
1. Upper plexus lesion: C5-C6, sometimes C7
Also called Erb palsy or upper-trunk palsy
Typical mechanism
- Traction separating the head and shoulder, such as a fall on the shoulder, motorcycle injury, or shoulder dystocia at birth.
Clinical presentation
- Weak shoulder abduction and external rotation: deltoid, supraspinatus, infraspinatus
- Weak elbow flexion and supination: biceps, brachialis
- In more extensive lesions, weak wrist and finger extension
- Reduced or absent biceps reflex and often brachioradialis reflex
- Sensory loss over the lateral shoulder and lateral arm/forearm, in a C5-C6 pattern
Typical posture in severe neonatal Erb palsy
- Arm adducted and internally rotated
- Elbow extended
- Forearm pronated
- Known as the “waiter’s tip” posture
Key clue: proximal arm weakness predominates, especially deltoid and biceps.
2. Lower plexus lesion: C8-T1
Also called Klumpke palsy or lower-trunk palsy
Typical mechanism
- Violent upward traction of an abducted arm, for example grasping something while falling
- Compression at the thoracic outlet
- Apical lung tumor, particularly a Pancoast tumor
Clinical presentation
- Marked weakness and wasting of intrinsic hand muscles
- Weak finger abduction/adduction and impaired fine finger movements
- Weak grip
- May also weaken finger and wrist flexion
- Sensory loss or pain along the medial forearm, medial hand, and little finger, roughly C8-T1/ulnar-sided distribution
- Reduced or absent grasp reflex in neonates
Associated Horner syndrome
- Ptosis, miosis, and facial anhidrosis suggest involvement of T1 sympathetic fibers, often indicating a lower-root avulsion or Pancoast tumor.
Key clue: hand weakness and medial-arm sensory symptoms predominate.
3. Total brachial plexus lesion: C5-T1
Typical mechanism
- Major traction injury, high-energy trauma, severe birth trauma, or extensive tumor/infiltrative disease.
Clinical presentation
- Flaccid, weak or completely paralysed upper limb
- Loss of shoulder, elbow, wrist, and hand movements
- Widespread sensory loss in the limb
- All relevant upper-limb reflexes may be absent
- Severe neuropathic pain may occur
- If lower roots are avulsed, Horner syndrome may coexist
Key clue: near-complete motor and sensory loss in one upper limb.
4. Posterior cord lesion
The posterior cord supplies the axillary and radial nerves.
Clinical presentation
- Weak shoulder abduction from deltoid weakness
- Weak elbow, wrist, and finger extension due to radial involvement
- Wrist drop
- Sensory loss over the lateral shoulder and posterior arm/forearm, extending to the dorsolateral hand
Key clue: combination of deltoid weakness plus wrist/finger extensor weakness.
5. Lateral cord lesion
The lateral cord contributes to the musculocutaneous nerve and lateral part of the median nerve.
Clinical presentation
- Weak elbow flexion and forearm supination from musculocutaneous involvement
- Reduced biceps reflex
- Sensory loss over lateral forearm
- May have variable median-nerve-pattern weakness in the forearm/hand
Key clue: biceps weakness with lateral forearm sensory loss, often broader than an isolated musculocutaneous neuropathy.
6. Medial cord lesion
The medial cord contributes to the ulnar nerve, medial median contribution, and medial cutaneous nerves.
Clinical presentation
- Weak intrinsic hand muscles
- Weakness in ulnar- and median-innervated hand muscles
- Sensory loss over medial arm, medial forearm, and ulnar side of hand
- May mimic ulnar neuropathy, but medial forearm sensory loss and median-intrinsic hand involvement indicate a more proximal lesion
Key clue: lower-plexus pattern with medial arm/forearm sensory involvement.
7. Root avulsion: preganglionic lesion
A root is torn from the spinal cord, usually in high-energy traction trauma.
Clinical clues
- Severe weakness, often profound
- Neuropathic or burning pain
- Horner syndrome, winged scapula, weak rhomboids, or elevated hemidiaphragm support a proximal/root-level lesion
- Sensation may be clinically impaired but sensory nerve action potentials can remain preserved on nerve-conduction testing because the dorsal root ganglion remains connected to the peripheral sensory nerve
- EMG may show denervation in paraspinal muscles
These lesions have a worse prognosis than postganglionic plexus injuries. Miller’s Review of Orthopaedics, pp. 697-698.
8. Nontraumatic brachial plexopathy patterns
| Cause | Characteristic presentation |
|---|---|
| Parsonage-Turner syndrome or neuralgic amyotrophy | Sudden, severe shoulder or supraclavicular pain followed days later by weakness and atrophy, often involving upper-trunk muscles or serratus anterior. Sensory loss is usually mild. |
| Neoplastic plexopathy | Severe, progressive pain followed by weakness, atrophy, and sensory loss. Lower trunk/medial cord involvement is common. Pancoast tumor may produce C8-T1 symptoms plus Horner syndrome. |
| Radiation-induced plexopathy | Usually delayed, progressive, often relatively painless weakness and sensory symptoms after radiotherapy. |
| Thoracic outlet syndrome | Lower-trunk pattern: hand intrinsic weakness with sensory symptoms mainly in the ulnar distribution; symptoms may be posture-related. |
| Hematoma or mass compression | Acute or subacute painful mixed motor-sensory deficit, especially after trauma, vascular procedures, bleeding disorder, or anticoagulation. |
A recent systematic review describes clinical assessment as requiring detailed mapping of weakness, reflexes, and sensory loss, with electrodiagnostic studies and imaging used to confirm localization when needed (2025 clinical assessment review).
Fast localization summary
- Deltoid + biceps weak → upper trunk, C5-C6, Erb pattern
- Intrinsic hand muscles weak → lower trunk, C8-T1, Klumpke pattern
- Deltoid weakness + wrist drop → posterior cord
- Whole limb flail → complete plexus lesion
- Medial hand pain/weakness + Horner syndrome → lower trunk/T1 lesion, consider root avulsion or Pancoast tumor
- Severe pain first, weakness later → Parsonage-Turner syndrome
New traumatic weakness, severe neuropathic pain, Horner syndrome, scapular winging, breathing difficulty, or suspected cervical root avulsion needs urgent specialist assessment.
Methyl alcohol posion and treatment
Reading File
Finding Sources
Finding Sources
Searching PubMed
methanol poisoning treatment
Searching the Web
methanol poisoning treatment fomepizole hemodialysis EXTRIP recommendations
Reading File
Reading File
Reading Web Page
https://www.extrip-workgroup.org/methanol
Methanol (methyl alcohol, wood alcohol) poisoning
Methanol poisoning is a medical emergency. If ingestion is suspected, seek emergency care immediately and contact the local poison center. Do not wait for visual symptoms or laboratory confirmation before seeking help.
Sources
Methanol occurs in industrial solvents, windshield-washer fluid, and some “canned heat” products. It is metabolized as:
Methanol → formaldehyde → formic acid
Formic acid causes high-anion-gap metabolic acidosis, optic nerve/retinal toxicity, and central nervous system injury. Fomepizole or ethanol prevents formation of these toxic metabolites by inhibiting alcohol dehydrogenase. Katzung’s Basic and Clinical Pharmacology, 16th ed., p. 632.
Clinical presentation
There may be a latent symptom-free period of about 6-24 hours, longer if ethanol was co-ingested.
| Stage | Features |
|---|---|
| Early | Inebriation, dizziness, headache, nausea, vomiting, abdominal pain |
| Progressive toxicity | Tachypnea from metabolic acidosis, confusion, drowsiness, hypotension |
| Characteristic toxicity | Blurred vision, photophobia, “snowfield” vision, reduced visual acuity, fixed/dilated pupils |
| Severe poisoning | Coma, seizures, respiratory failure, blindness, death |
Important late complications include optic neuropathy and basal ganglia, especially putaminal, injury that can cause a Parkinsonian syndrome. Comprehensive Clinical Nephrology, 7th ed., Box 13.6.
Diagnosis
Suspect methanol toxicity in a patient with unexplained acidosis, visual symptoms, altered consciousness, or a history of solvent/windshield-fluid ingestion.
Typical investigations
- Arterial or venous blood gas: metabolic acidosis, often severe
- Serum electrolytes and bicarbonate
- Anion gap: elevated
- Measured and calculated serum osmolality: early osmolar gap may be elevated
- Serum methanol concentration, if available
- Renal function, glucose, lactate, ethanol concentration
- ECG and continuous monitoring
- CT/MRI brain if neurological complications are suspected
A normal osmolar gap does not exclude late poisoning because methanol may already have been converted to formate.
Treatment
1. Immediate resuscitation
- Airway, breathing, circulation
- Oxygen and ventilatory support if required
- IV access, cardiac monitoring, serial neurologic and visual assessment
- Consult a medical toxicologist/poison center and nephrology early.
2. Block toxic metabolism: fomepizole
Fomepizole is the preferred antidote.
A commonly used regimen:
- 15 mg/kg IV loading dose
- Then 10 mg/kg IV every 12 hours for 48 hours
- Then 15 mg/kg IV every 12 hours thereafter because of autoinduction
- During intermittent hemodialysis, it must be given more frequently, often every 4 hours, according to the local protocol.
Do not delay antidotal treatment when suspicion is high, especially with acidosis, visual symptoms, elevated osmolar gap, or an available methanol level above the treatment threshold. Comprehensive Clinical Nephrology, 7th ed., Box 13.6.
3. If fomepizole is unavailable: ethanol
IV ethanol is an alternative because it competitively occupies alcohol dehydrogenase, reducing formate generation. It needs close monitoring because it can cause intoxication, hypoglycemia, and unstable blood ethanol concentrations. This should be administered only under a toxicology-directed hospital protocol.
4. Correct acidosis
- Give IV sodium bicarbonate for significant metabolic acidosis.
- This supports physiologic pH and reduces the proportion of undissociated formic acid that enters tissues.
5. Folate cofactor
- Folinic acid (leucovorin) or folic acid is usually administered to enhance formate metabolism.
- A common hospital regimen is folinic acid 50 mg IV every 4-6 hours, but follow local toxicology guidance.
6. Hemodialysis
Hemodialysis rapidly removes both methanol and formate and corrects acidosis. Intermittent hemodialysis is preferred when available.
The EXTRIP methanol recommendations recommend extracorporeal treatment when any of these are present:
- Coma
- Seizures
- New visual deficit
- pH ≤ 7.15
- Persistent metabolic acidosis despite antidote and supportive treatment
- Anion gap >24 mmol/L
- Impaired renal function
- High serum methanol concentration:
-
700 mg/L or 21.8 mmol/L while on fomepizole
-
600 mg/L or 18.7 mmol/L while on ethanol
-
500 mg/L or 15.6 mmol/L without an alcohol dehydrogenase blocker
-
Continue fomepizole or ethanol during dialysis, because dialysis also removes the antidote. Dialysis is generally stopped after clinical improvement and methanol falls below 200 mg/L (6.2 mmol/L), per EXTRIP.
Exam summary
Methanol poisoning
- Toxic metabolite: formic acid
- Main danger: high-anion-gap metabolic acidosis + visual loss
- Antidote of choice: fomepizole
- Additional treatment: sodium bicarbonate + folinic acid
- Severe poisoning: hemodialysis
- Classic visual symptom: “snowfield” vision
This is a shared conversation. Sign in to Orris to start your own chat.