
Advances in volume scanning in detail
volume scanning CT ultrasound advances
advances in volume scanning CT ultrasound 4D radiology 2024 2025
https://www.dirjournal.org/articles/doi/dir.2024.242926
"volume CT" OR "volumetric scanning" advances imaging
PMID: 40300917
Advances in Volume Scanning
1. Evolution from Single-Slice to Multidetector CT (MDCT)
- Shorter scan times, reducing motion artifact
- Sub-millimeter isotropic voxels enabling high-quality multiplanar reformats (axial, coronal, sagittal) and 3D volume rendering
- CT angiography (CTA) and CT perfusion by dynamic contrast acquisition
- Sections as thin as 0.5–1 mm with 0.4 mm in-plane resolution at 0.3 seconds per rotation; complete brain studies in 1–10 seconds
2. Wide-Area / 320-Detector Row CT: True Single-Rotation Volume Coverage
Clinical Applications
3. Four-Dimensional CT (4D-CT): Adding Time as a Dimension
Parathyroid Localization
- Non-contrast
- Arterial
- Venous
- Delayed/washout
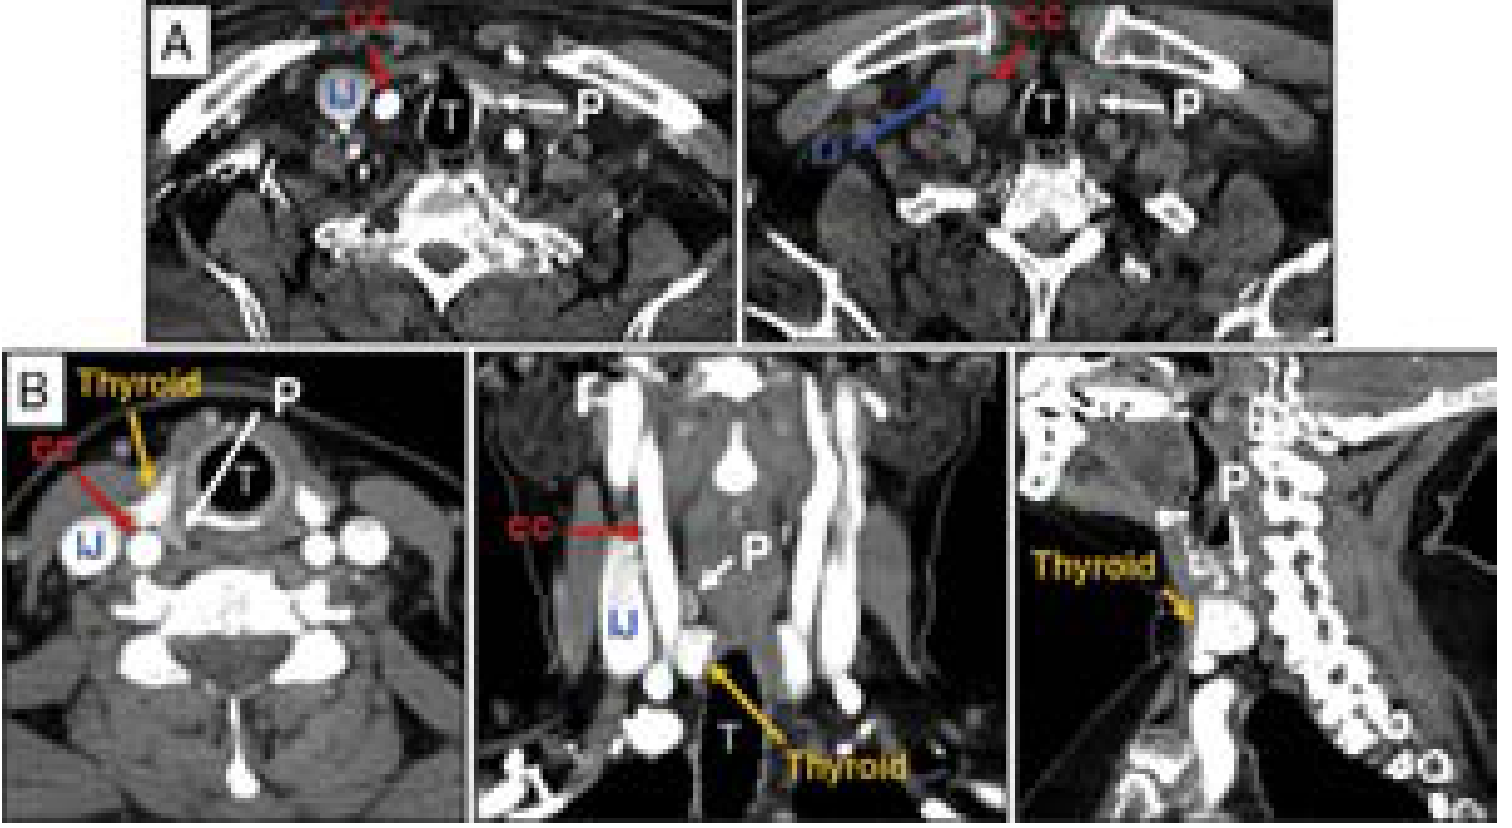
Musculoskeletal / Orthopaedic Applications
- Costoclavicular impingement
- Scapholunate instability
- Capitate subluxation
- Pisotriquetral instability
- Acromioclavicular dislocation
- Snapping scapula
Weight-Bearing CT (WBCT)
- Pre/postoperative evaluation of total ankle replacements
- Patellofemoral instability after MPFL reconstruction
- Diabetic foot architecture
- Flatfoot reconstruction
- Syndesmotic instability (a systematic review found WBCT measuring the syndesmotic area to be the most reliable parameter for this diagnosis) — Rockwood & Green's Fractures in Adults 10th ed 2025
4. Photon-Counting CT (PCD-CT): The Latest Detector Revolution
| Feature | Conventional MDCT | Photon-Counting CT |
|---|---|---|
| Resolution | ~0.4–0.5 mm in-plane | ~0.2 mm |
| Electronic noise | Inherent scintillator noise | Greatly reduced |
| Radiation dose | Standard | Often reduced |
| Spectral capability | Limited (dual-energy variants) | Multi-energy bins in each acquisition |
| Contrast dose | Standard iodine volume | Reduced contrast required |
| Metal/bone artifact | Beam hardening present | Improved calcium/bone artifact reduction |
5. 3D and 4D Ultrasound Volume Scanning
Mechanical Scanning
Free-Hand Scanning
2D Phased-Array Transducers (Matrix Arrays) — Real-Time 4D
- Wideband 2D sparse arrays with multiline receiving optimize active component count while maintaining accuracy and speed
- Obstetrics: Real-time 4D visualization of fetal face, movement, anomalies (midline cleft lip, anencephaly, Müllerian anomalies)
- Cardiology: Real-time 3D echocardiography for valve morphology, ventricular volumes, wall motion
- Oncology: Tumor margin delineation and volume measurements
- Urology: 3D TRUS for prostate volume calculation; cryo-probe placement confirmation
6. Dual-Energy CT and Spectral Imaging
- Material decomposition (iodine vs. calcium vs. uric acid maps)
- Virtual non-contrast reconstructions
- Reduced metal artifact via monoenergetic reconstructions
- Improved lesion characterization (e.g., renal stone composition, gout)
7. 3D Reconstruction and Post-Processing
- Multiplanar reformation (MPR): Axial, coronal, sagittal, oblique
- Maximum-intensity projection (MIP): Vascular and high-density structures
- 3D volume rendering: Surgical planning (fracture, tumor, vascular anatomy)
- "Ghosting" / bone removal for orthopaedic fracture visualization
- 3D printing: CT data used to generate physical models for maxillofacial reconstruction, complex fracture management, deformity correction, and tumor resection planning
- AI-assisted segmentation: Automated organ/lesion volumetry, plaque quantification (FFR-CT), myocardial mass estimation
Summary Table
| Technology | Key Advance | Clinical Gain |
|---|---|---|
| Helical CT | Continuous volumetric acquisition | Replaces sequential slices; CTA enabled |
| MDCT (64–256 row) | Faster, thinner, isotropic voxels | Sub-mm resolution; multiplanar reformat |
| 320-row wide-area CT | Single-rotation organ coverage | 4D cardiac, 4D-CTA, reduced dose |
| 4D-CT | Temporal dimension added | Parathyroid localization; joint kinematics |
| Weight-bearing CBCT | Physiologic loading during scan | Syndesmotic, ankle, flatfoot assessment |
| Photon-counting CT | Direct x-ray→electric conversion | 0.2 mm resolution; reduced dose/contrast |
| Dual-energy/Spectral CT | Multi-energy acquisition | Material decomposition; reduced artifact |
| 4D ultrasound (matrix array) | Real-time volumetric US | Fetal, cardiac, oncology applications |
| AI integration | Automated segmentation & analysis | FFR-CT, volumetry, prognostic biomarkers |
- Harrison's Principles of Internal Medicine 22E, p. 3427 (MDCT, photon-counting CT)
- Grainger & Allison's Diagnostic Radiology (MDCT evolution, 320-row cardiac CT)
- Bradley and Daroff's Neurology in Clinical Practice (4D-CTA, 320-row neurovascular)
- Current Surgical Therapy 14e (4D-CT parathyroid localization)
- Rockwood & Green's Fractures in Adults 10th ed 2025 (4D-CT joints, WBCT, 3D printing)
- Rubio PM et al. J Cardiovasc Comput Tomogr 2025 — Key advances in cardiac CT (PMID: 40300917)
- DIR Journal 2024 — New imaging techniques and trends in radiology
Advances in volume scanning in ct in detail , firstly define volume scanning and it principle , components and u want to add , and then advances
"computed tomography" volumetric scanning advances review
volume CT scanning definition principle components advances 2024 2025 radiology review
https://aditum.org/images/article/1769068116Advances_in_CT_I…
Volume Scanning in CT — Definition, Principles, Components, and Advances
PART 1 — DEFINITION OF VOLUME SCANNING IN CT
"From the same data set, both narrow sections (0.6–1.25 mm thickness) for high spatial resolution detail or 3D postprocessing and wide sections (2.5–5 mm) can be produced for better contrast resolution or quick review." — Grainger & Allison's Diagnostic Radiology
PART 2 — PHYSICAL PRINCIPLE OF VOLUME CT
2.1 X-Ray Attenuation and the Hounsfield Scale
Greater x-ray attenuation → higher density → whiter on scan. Poor attenuation (air, organs) → gray-black. — Harrison's Principles of Internal Medicine 22E, p. 3427
2.2 The Helical (Spiral) Acquisition — The Foundation of Volume Scanning
- The x-ray tube rotates continuously
- The patient table continuously translates through the rotating beam
- The combined motion traces a helix of data around the patient
- Computer algorithms interpolate this helical raw data into planar slice images at any desired interval
2.3 Pitch
- Pitch < 1: overlapping acquisitions → higher radiation dose, better Z-axis resolution
- Pitch > 1: faster coverage → lower dose but reduced Z-axis sampling
2.4 Cone Beam Geometry
PART 3 — COMPONENTS OF A VOLUME CT SCANNER
3.1 X-Ray Tube
- Generates a polychromatic (broad energy spectrum) x-ray beam
- Housed within the rotating gantry opposite the detector array
- Key parameters: kVp (peak voltage, determining photon energy) and mAs (tube current × time, determining photon flux and dose)
- Modern tubes rotate at 0.33 seconds per gantry rotation — down to as fast as 0.25 s in some systems
- Focal spot: The physical point where electrons strike the anode and x-rays are produced. Smaller focal spot = sharper image. The "flying focal spot" (see advances below) deflects the electron beam to alternate between two focal spot positions, doubling effective sampling
3.2 Gantry
- The rotating ring structure housing the x-ray tube and detector array
- Modern gantries achieve sub-0.35 second rotation times
- Slip-ring technology (introduced ~1987–1991) allows continuous rotation without cable wrap — a prerequisite for helical CT
- Some systems use dual-source design: two x-ray tube/detector pairs mounted 90° apart in the same gantry
3.3 Detector Array
- X-rays → converted to light photons by ceramic scintillators → converted to electrical signals by photodiodes
- Organized in rows (Z-axis) and channels (XY-plane)
- Modern scanners: 4 to 320 detector rows, each row ~0.5–0.625 mm thick
- More rows = wider anatomical coverage per rotation = faster volume scanning
- Dead space between detector elements (inter-detector septa)
- Electronic noise from the two-stage conversion (x-ray → light → electricity)
- Geometric dose inefficiencies (dose delivered to inter-row septa is wasted)
3.4 Patient Table (Couch)
- Motorized translation through the gantry bore during helical acquisition
- Precise table speed is coordinated with tube rotation and beam collimation to determine pitch
- Must be stable and vibration-free to avoid motion artifact in volumetric data
3.5 Collimators
- Pre-patient collimators (bow-tie filters): shape the x-ray beam to reduce peripheral dose and even out the attenuation profile across the patient's cross-section. Different bow-tie shapes for head vs. body
- Post-patient collimators: reject scattered radiation before it reaches detectors
- Z-axis collimation: defines the total width of the detector array illuminated, determining the number of slices per rotation
3.6 Reconstruction Computer
- Processes raw projection data into images
- Originally used Filtered Back Projection (FBP): computationally efficient but amplifies noise at low doses
- Modern systems use Iterative Reconstruction (IR) and Deep Learning Reconstruction (DLR)
- Must process large volumes of raw data rapidly — parallel GPU-based processing is now standard
3.7 Post-Processing Workstation
- Multiplanar Reformations (MPR): axial, coronal, sagittal, oblique planes
- Maximum Intensity Projections (MIP): highlights high-density structures (vessels, calcifications)
- Minimum Intensity Projections (MinIP): for airway visualization
- 3D Volume Rendering (VR): surface and opacity-rendered 3D anatomical displays
- Curved planar reformations (CPR): follows curved structures (coronary arteries, bile ducts)
- CT angiography (CTA) and CT perfusion maps
PART 4 — ADVANCES IN VOLUME CT SCANNING
Advance 1 — From Single-Slice to Multidetector CT (MDCT)
- 1971: First clinical CT scan (Hounsfield, Atkinson Morley Hospital) — single slice, ~4.5 minutes per image
- Early 1990s: Helical CT — continuous rotation + table movement → true volume acquisition
- 1998: Multiple manufacturers introduce multidetector CT (MDCT) — arrays of detector rows allowing multiple simultaneous slices per rotation
- 2000s–present: Rapid escalation from 4-row → 16 → 64 → 128 → 256 → 320-row systems
- Single breath-hold imaging of entire organ systems
- Reduced motion artifacts (less sedation needed in children)
- Improved spatial resolution — isotropic voxels (equal dimensions in X, Y, Z) enabling high-quality 3D reconstruction
- Faster acquisition → dynamic contrast-enhanced imaging → CTA + CT perfusion
"Three major benefits arise from these technological advances: single breath-hold imaging, reduction in motion artefacts, and improved spatial resolution." — Grainger & Allison's Diagnostic Radiology
Advance 2 — Wide-Area Detectors: 320-Row CT
- True 320-row arrays: wide-area detectors
- Dual-source CT: two x-ray tube/detector pairs → doubles temporal resolution without increasing rotation speed; particularly valuable in cardiac CT at high heart rates
- Flying focal spot: alternates the focal spot position between two positions per rotation, converting a 128-row array into a virtual 256-row array
- z-flying focal spot: applies focal spot deflection in the Z-axis, doubling z-axis sampling
- Cardiac CT: entire heart covered in one rotation → single-heartbeat coronary CT angiography → dramatically reduced radiation dose (no multi-beat stitching artifacts)
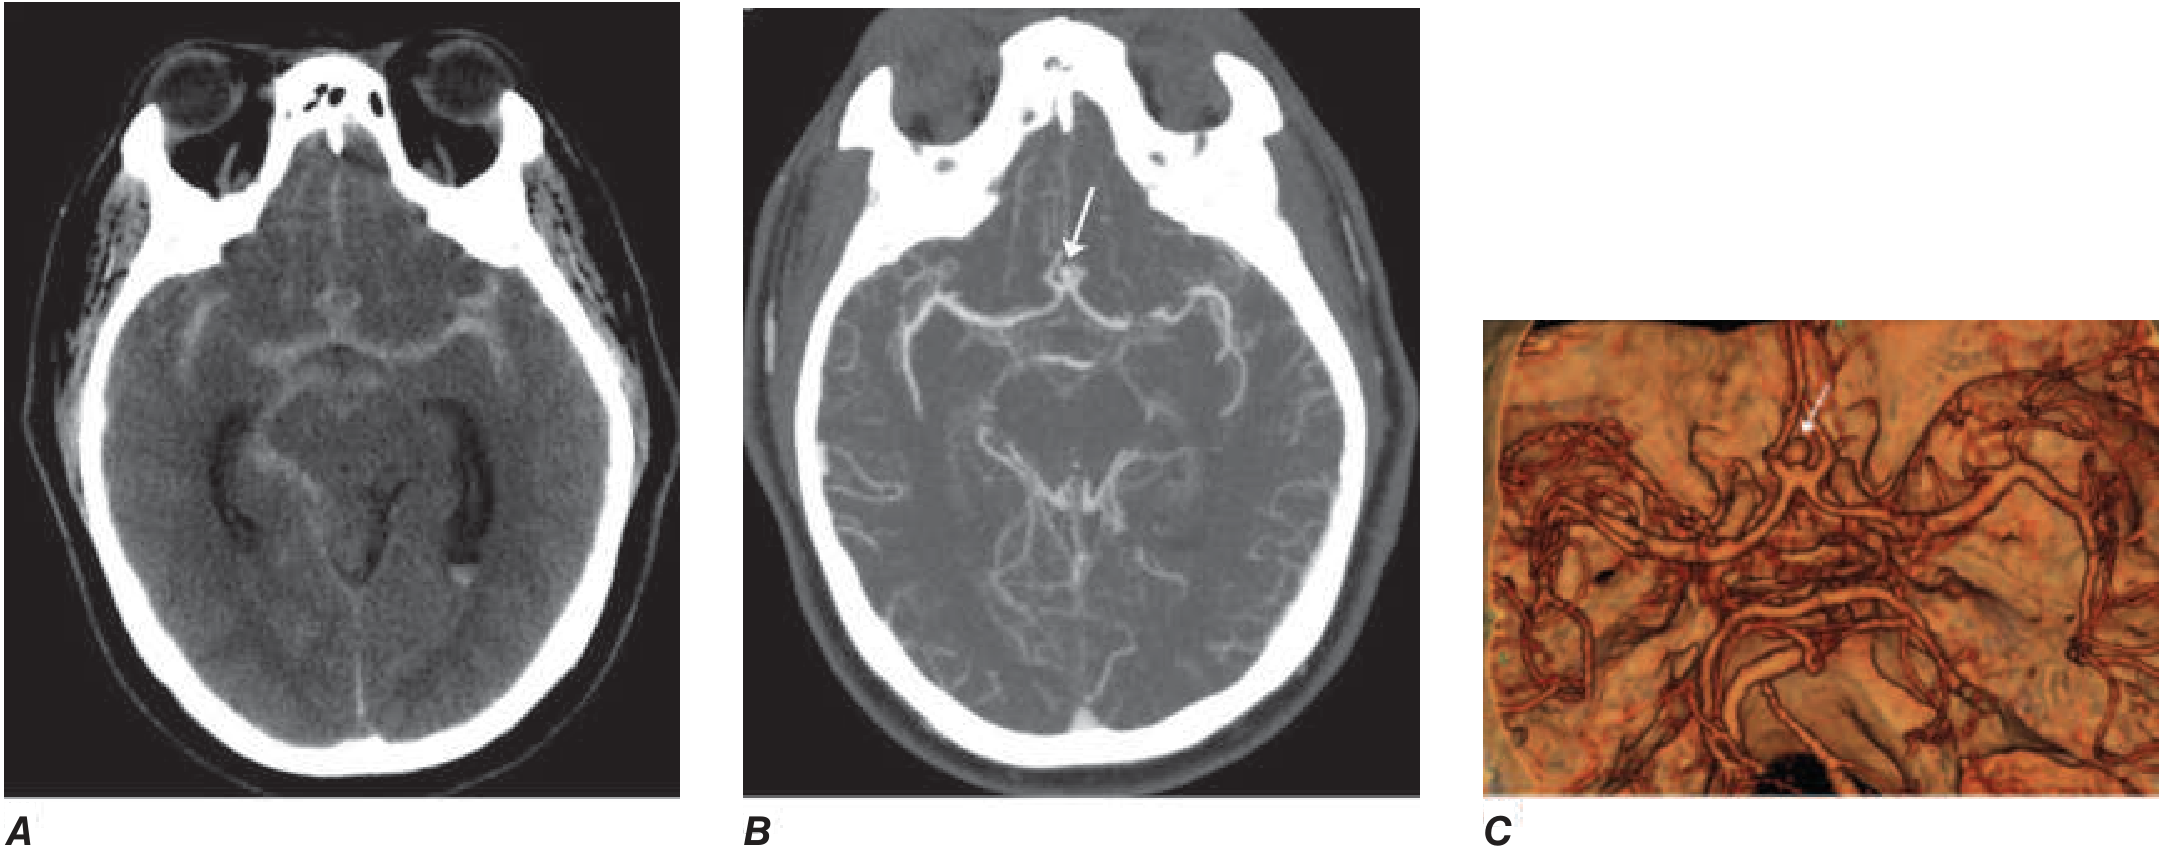
- 4D CT angiography (4D-CTA): dynamic scanning of the entire cerebrovasculature with both high spatial and temporal resolution — images contrast bolus passage through all cerebral vessels simultaneously; more accurate than single-phase CTA for defining intracranial thrombus burden and small aneurysms
- CT perfusion: simultaneous perfusion maps of an entire organ (brain, heart, liver) in one acquisition
- Pediatric imaging: ultra-fast acquisition minimizes need for sedation/general anesthesia
"More recent CT with 320 detector rows enables dynamic scanning, providing both high spatial and temporal resolution of the entire cerebrovasculature (four-dimensional [4D] CTA)." — Bradley and Daroff's Neurology in Clinical Practice
Advance 3 — Four-Dimensional CT (4D-CT): Adding Time
4D-CT for Parathyroid Localization
- Non-contrast
- Arterial phase
- Venous phase
- Delayed/washout phase
4D-CT for Joint Biomechanics
- Costoclavicular impingement
- Scapholunate instability
- Capitate subluxation
- Pisotriquetral instability
- Acromioclavicular dislocation
- Snapping scapula
- Lower extremity indications under active investigation
"Dynamic CT, otherwise known as 4D CT, is an emerging diagnostic tool to assess joint biomechanics... allowing the reconstructions to show dynamic cine-movies." — Rockwood & Green's Fractures in Adults, 10th ed. 2025
Advance 4 — Iterative Reconstruction (IR): Better Images, Lower Dose
| Type | Mechanism | Dose Reduction | Trade-off |
|---|---|---|---|
| Hybrid IR | Blends FBP + IR | ~30–50% | Mild "waxy" appearance in early generations |
| Pure/Model-Based IR (MBIR) | Physically models focal spot, beam, patient, detector | Up to 75–80% | Computationally very slow (3–4 reconstructions/hour initially) |
| Adaptive non-local means (ANLM) | Vendor-independent, post-FBP noise suppression | Comparable to IR | Less computational demand |
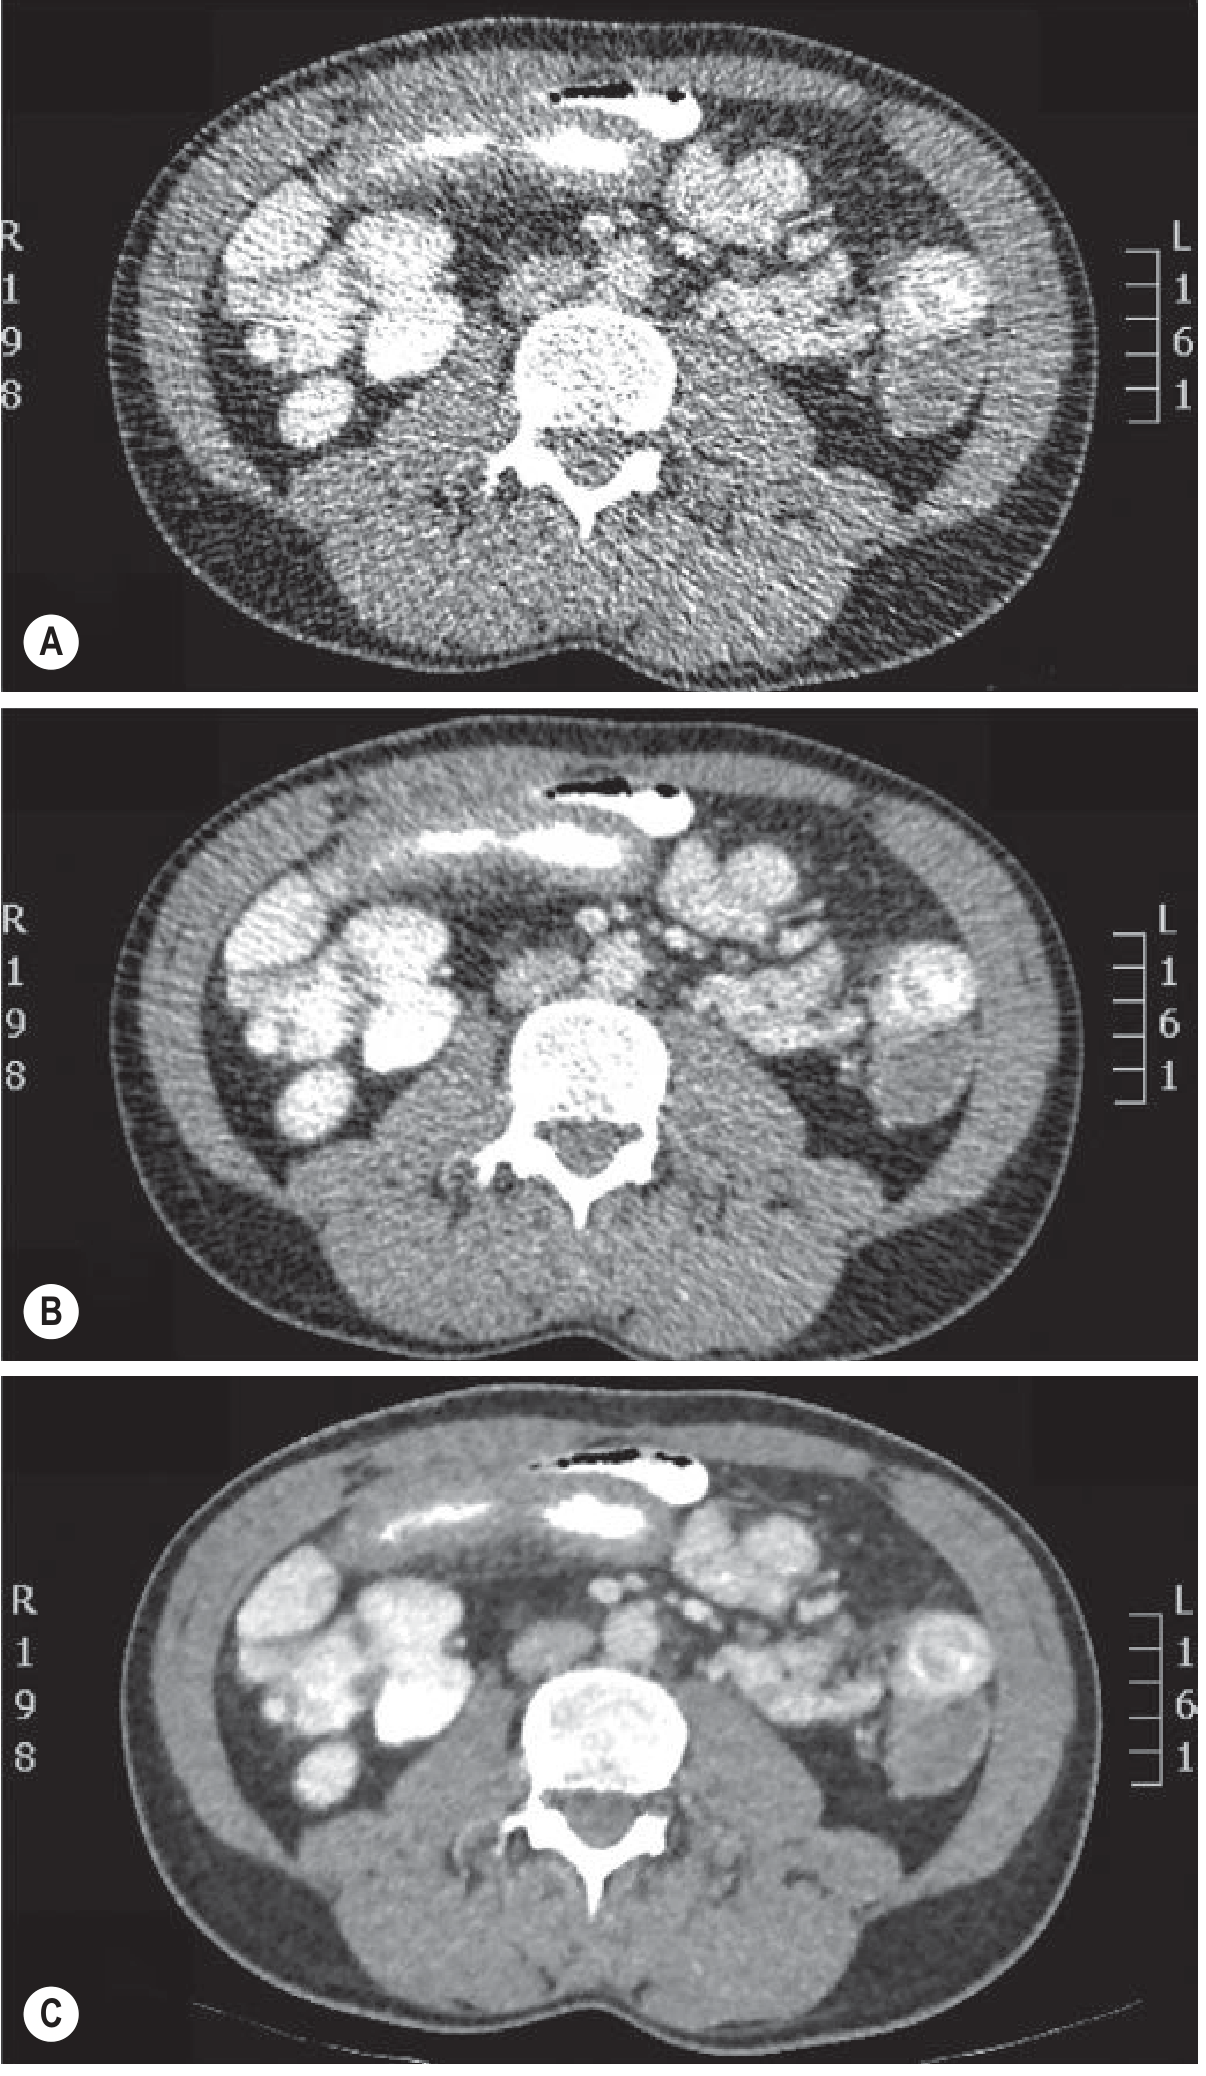
"The widespread dissemination of technologies such as iterative reconstruction is likely to result in CT dose reductions on the order of 75% and greater in future years." — Grainger & Allison's Diagnostic Radiology
Advance 5 — Photon-Counting Detector CT (PCD-CT): The Newest Detector Revolution
| Parameter | Conventional MDCT | Photon-Counting CT |
|---|---|---|
| In-plane resolution | ~0.4–0.5 mm | ~0.2 mm |
| Electronic noise | Inherent from 2-stage conversion | Near-zero (photons counted individually) |
| Radiation dose | Standard | Often reduced |
| Spectral capability | Requires special hardware (dual-source, fast kV switching) | Multi-energy bins built into every acquisition |
| Contrast dose | Standard | Reduced (improved CNR) |
| Calcium/bone artifact | Beam hardening present | Improved (spectral separation) |
| Detector element size | Limited by cross-talk | Smaller → higher resolution |
"New so-called photon-counting CT scanners... convert x-ray directly into an electric signal, rather than photon light, resulting in improved resolution, reduced electronic noise and thus dose reduction, improved spectral energy detection that reduces calcium and bone artifact, and improved contrast-to-noise ratio... Photon counting scanners are now able to produce CT images with 0.2 mm resolution often at reduced radiation dose." — Harrison's Principles of Internal Medicine 22E, p. 3427
Advance 6 — Dual-Energy CT (DECT) and Dual-Source CT
- Dual-source CT: Two x-ray tube/detector pairs at 90° in the same gantry, each running at a different kVp
- Fast kV switching: A single tube rapidly alternates between high and low kVp
- Dual-layer detectors: A single tube; detector rows are physically layered to capture different energy spectra simultaneously
- Virtual non-contrast (VNC) images: remove iodine mathematically → eliminate a non-contrast acquisition → reduces dose
- Iodine maps: quantify contrast uptake in lesions → organ perfusion assessment
- Uric acid vs. calcium stone differentiation: directly diagnose gout tophi and uric acid calculi
- Pulmonary embolism: dual-energy CT provides simultaneous morphological (clot) and functional (perfusion deficit) information in one acquisition
- Reduced beam-hardening and metal artifact: monoenergetic virtual reconstructions at high keV
- Bone subtraction: automated removal of bony structures for vascular imaging
Advances include: "Dual source geometry with ECG gating/triggering – less need for high dose retrospective cardiac CT even at high heart rates. Dual energy CT – roles in artefact reduction and potential for quantitative imaging." — Grainger & Allison's Diagnostic Radiology, Summary Box: Current Status of CT
Advance 7 — Deep Learning Reconstruction (DLR) and AI Integration
- IR uses physics-based mathematical models (slow, iterative loops)
- DLR uses a trained neural network that applies learned noise/artifact suppression patterns in a single forward pass → much faster than pure IR
- DLR models learn from millions of CT image pairs (noisy→clean) and can achieve image quality rivaling or surpassing pure IR at low doses
- Automated organ segmentation: lungs, liver, kidneys, heart, vasculature delineated automatically
- Pulmonary nodule detection and characterization: AI matches or exceeds radiologist performance for benign/malignant discrimination in screening CT
- FFR-CT (Fractional Flow Reserve from CT): AI analyzes coronary CT angiography volume to compute functional significance of stenoses without catheterization
- CT-ECV (extracellular volume): AI-derived myocardial biomarker from volume-scanned cardiac CT
- Bone mineral density (BMD) from opportunistic CT
"Some of the first medical applications of deep learning were in the field of dermatology, and more recently, this advanced form of pattern recognition has been reported to excel at the discrimination of benign and malignant lung nodules in thoracic CT scan. The breadth of application of these tools continues to expand to include image navigation and feature detection, biomarker development, and direct prediction of clinical outcomes." — Harrison's Principles of Internal Medicine 22E
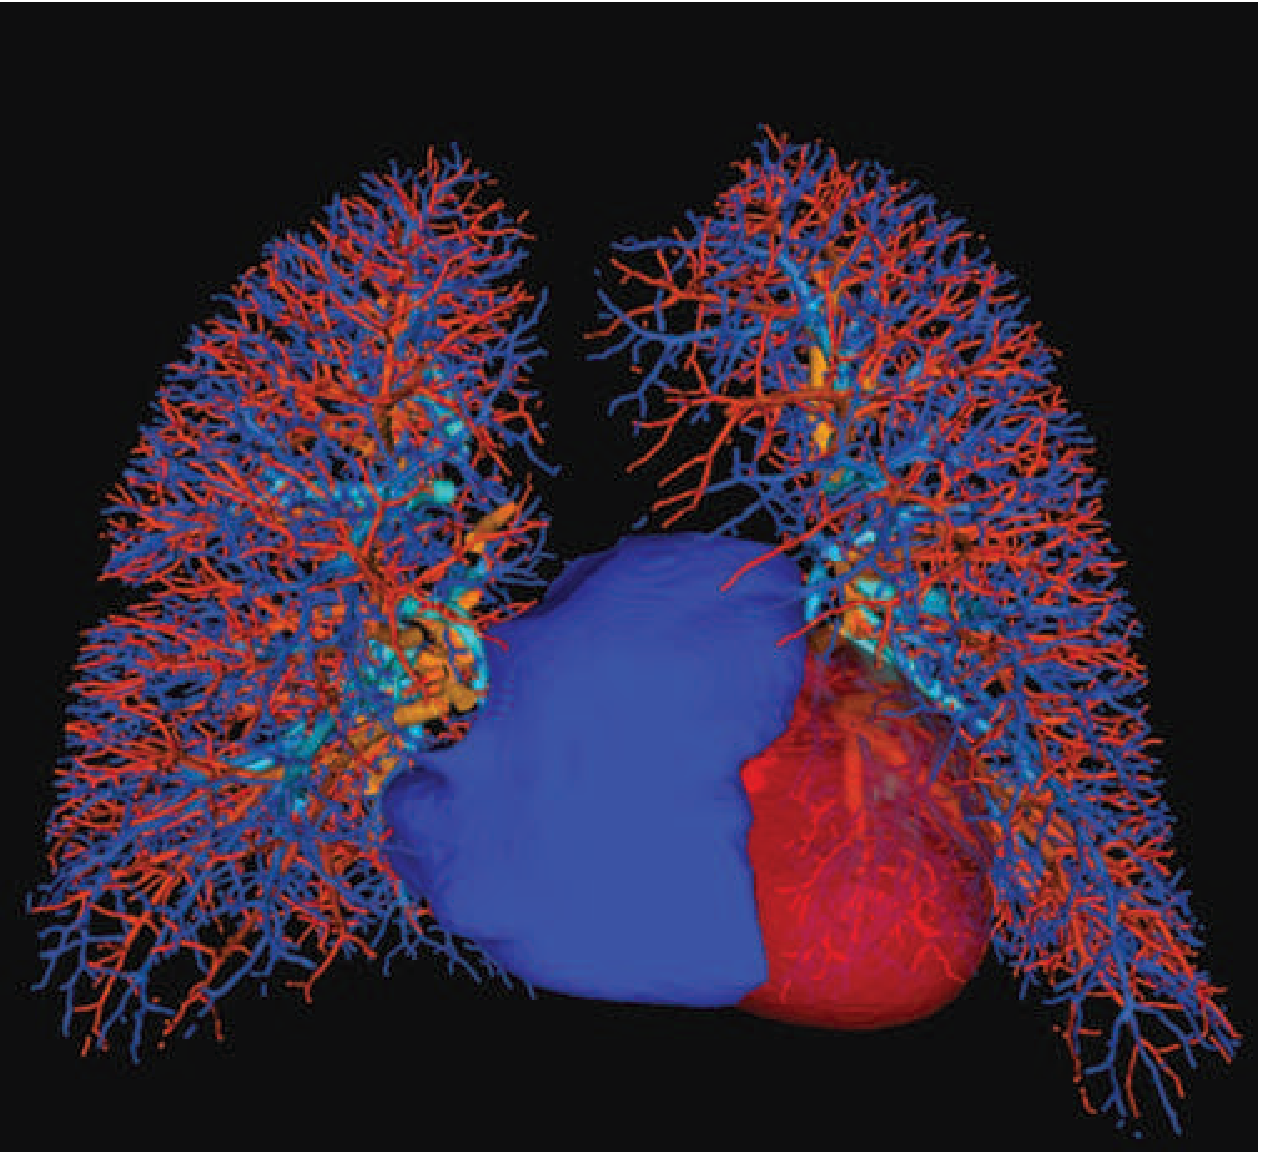
Advance 8 — High-Resolution Volume CT (HRCT) and Thin-Section Protocols
- Thin collimation (1–2 mm or sub-millimeter)
- High-spatial-frequency reconstruction algorithm ("lung" or "sharp" kernel)
- Single breath-hold acquisition to eliminate respiratory motion
- Volumetric assessment and characterization of pulmonary nodules
- Evaluation of interstitial lung disease (ILD) — thickened septa, ground-glass opacification, traction bronchiectasis
- Pulmonary embolism (PE) protocol
- Bronchiectasis and small airways disease
Advance 9 — Cone-Beam CT (CBCT) and Weight-Bearing CT
- Radiation dose considerably lower than conventional CT
- Weight-bearing CBCT: allows imaging of joints under physiological load (standing) — impossible with conventional supine CT
- Applications: syndesmotic instability, total ankle arthroplasty assessment, patellofemoral instability, flatfoot reconstruction, diabetic foot architecture
- Also widely used in dental/maxillofacial surgery for bony anatomy (jaw, skull base, implant planning)
- Limitation: poor soft-tissue contrast; beam-hardening artifact from dental restoration
Advance 10 — Portable CT and Point-of-Care Volume Scanning
- ICU and emergency department deployment without patient transport
- Intraoperative CT (surgical suites, hybrid ORs)
- Mobile cone-beam CT combined with bronchoscopy for real-time confirmation of peripheral lung biopsy position
- Canon Alphenix 4D CT + Aquilion One/Insight Edition: combined angiography/CT interventional system, FDA-cleared 2025, combining intraoperative 4D CT with DSA for complex endovascular procedures
Summary: The Arc of Volume CT Advances
1971 First clinical CT Single slice, 4.5 min/image
↓
1991 Helical CT True continuous volumetric acquisition
↓
1998 MDCT (4–16 rows) Multiple slices per rotation, isotropic voxels
↓
2000s 64-row MDCT Sub-mm isotropic CT angiography becomes routine
↓
2007 320-row wide-area CT Entire organ in one rotation; 4D perfusion/CTA
↓
2008– Iterative Reconstruction 30–80% dose reduction; better low-contrast detail
↓
2010s Dual-Energy CT Material decomposition; spectral imaging
↓
2017– Deep Learning Recon AI-based noise suppression; ultra-low dose possible
↓
2022– Photon-Counting CT (PCCT) 0.2 mm resolution; direct x-ray conversion; multi-energy bins
↓
2025+ AI integration Automated segmentation, FFR-CT, biomarker extraction
- Harrison's Principles of Internal Medicine 22E (McGraw-Hill, 2025), pp. 3427–3428
- Grainger & Allison's Diagnostic Radiology — CT Technology Chapters
- Bradley and Daroff's Neurology in Clinical Practice — CTA section
- Rockwood & Green's Fractures in Adults 10th ed. (2025) — 4D-CT and WBCT
- Current Surgical Therapy 14e — 4D-CT parathyroid
- DIR Journal 2024 — New imaging techniques and trends in radiology
- Rubio PM et al. J Cardiovasc Comput Tomogr 2025 — Cardiac CT key advances 2024This comprehensive guide covers everything you asked for. Here is a quick orientation to the structure:
- MDCT evolution (single-slice → 320 row)
- Wide-area detectors & 320-row CT (single-rotation organ coverage)
- Four-dimensional CT — parathyroid & joint biomechanics
- Iterative reconstruction (30–80% dose reduction)
- Photon-counting CT — 0.2 mm resolution, direct x-ray conversion, multi-energy spectral bins
- Dual-Energy / Dual-Source CT — material decomposition and spectral imaging
- Deep Learning Reconstruction + AI (FFR-CT, automated segmentation, biomarkers)
- High-Resolution thin-section protocols from volumetric data
- Cone-beam CT and weight-bearing CT
- Portable/point-of-care volume CT
Interventional guidance tools in CT what to write ?
What is this for? · How detailed should it be? · What aspect of interventional CT guidance do you want covered?
interventional guidance tools CT-guided procedures biopsy ablation drainage navigation 2024 2025 review
"CT-guided" interventional procedures needle guidance tools
CT-guided percutaneous interventional radiology biopsy ablation
CT guided interventional tools needle guidance systems robotic navigation augmented reality 2024 2025
Interventional Guidance Tools in CT — Complete Study Notes
1. DEFINITION AND OVERVIEW
- Is widely available across clinical settings
- Provides excellent anatomic delineation and spatial resolution regardless of overlying structures (bowel gas, fat, ribs)
- Visualizes deep structures inaccessible to ultrasound
- Allows precise multi-planar targeting of small or complex lesions
- Gives superior delineation of collection walls, adjacent organs, and safe access routes
"CT provides excellent anatomic delineation, irrespective of the overlying structures... The superior spatial resolution of CT over ultrasound often allows better localisation of the margins of a collection, the thickness of the wall, the adjacent organs and the access route." — Grainger & Allison's Diagnostic Radiology
2. WHY CT FOR INTERVENTIONAL GUIDANCE?
CT vs. Ultrasound vs. Fluoroscopy
| Feature | CT | Ultrasound | Fluoroscopy |
|---|---|---|---|
| Real-time guidance | Limited (except CT-fluoro) | Yes | Yes |
| Soft tissue resolution | Excellent | Good (superficial) | Poor |
| Deep lesions / retroperitoneum | Excellent | Limited | Limited |
| Gas-containing collections | Can visualize | Cannot penetrate | Variable |
| Radiation | Yes | None | Yes |
| Portability | No (except mobile CT) | Yes (bedside) | Some |
| Angulated approaches | Limited to axial plane | Freely angulated | Freely angulated |
| Cost | Higher | Lower | Moderate |
3. THE STANDARD CT GUIDANCE WORKFLOW
3.1 Pre-Procedure Planning
- Review cross-sectional imaging (CT/MRI) to identify:
- Target size, depth, and location
- Adjacent vulnerable structures: vessels, bowel, pleura, bile ducts, pericardium
- Optimal access window (skin-entry point)
- Planned needle/probe trajectory
- Assess coagulation status (INR, platelets) and anticoagulant use (stop clopidogrel 5 days prior for high-risk procedures)
- Broad-spectrum antibiotic prophylaxis within 1 hour of commencement (drainage procedures per Society of Interventional Radiology guidelines)
3.2 Patient Positioning and CT Localization
- Patient positioned prone, supine, or lateral depending on target
- Scout (topogram) to identify entry level
- Gantry laser guide used to mark the skin entry point precisely — essential when gantry is tilted craniocaudally for non-axial access windows
- Local anesthesia applied to the planned trajectory depth
3.3 Guidance Modes During Procedure
4. CT GUIDANCE MODES — THE CORE TOOLS
4.1 Conventional (Intermittent / "Quick-Check") CT Guidance
- Needle/catheter is manually advanced a small increment by the operator
- Operator steps away → CT scan acquired → image reviewed
- Needle position assessed → further manipulation as required
- Process repeated until target is reached
- Significantly lower radiation dose than real-time CT fluoroscopy
- Works on any standard CT scanner
- Sufficient for most percutaneous procedures
- Dependent on patient breath-holding consistency (each scan acquired at same respiratory phase)
- Slower than real-time methods
- Operator must step out of the room for each acquisition
"Quick-check CT guidance considerably reduces fluoroscopic time and radiation dose compared with real-time guidance." — Grainger & Allison's Diagnostic Radiology
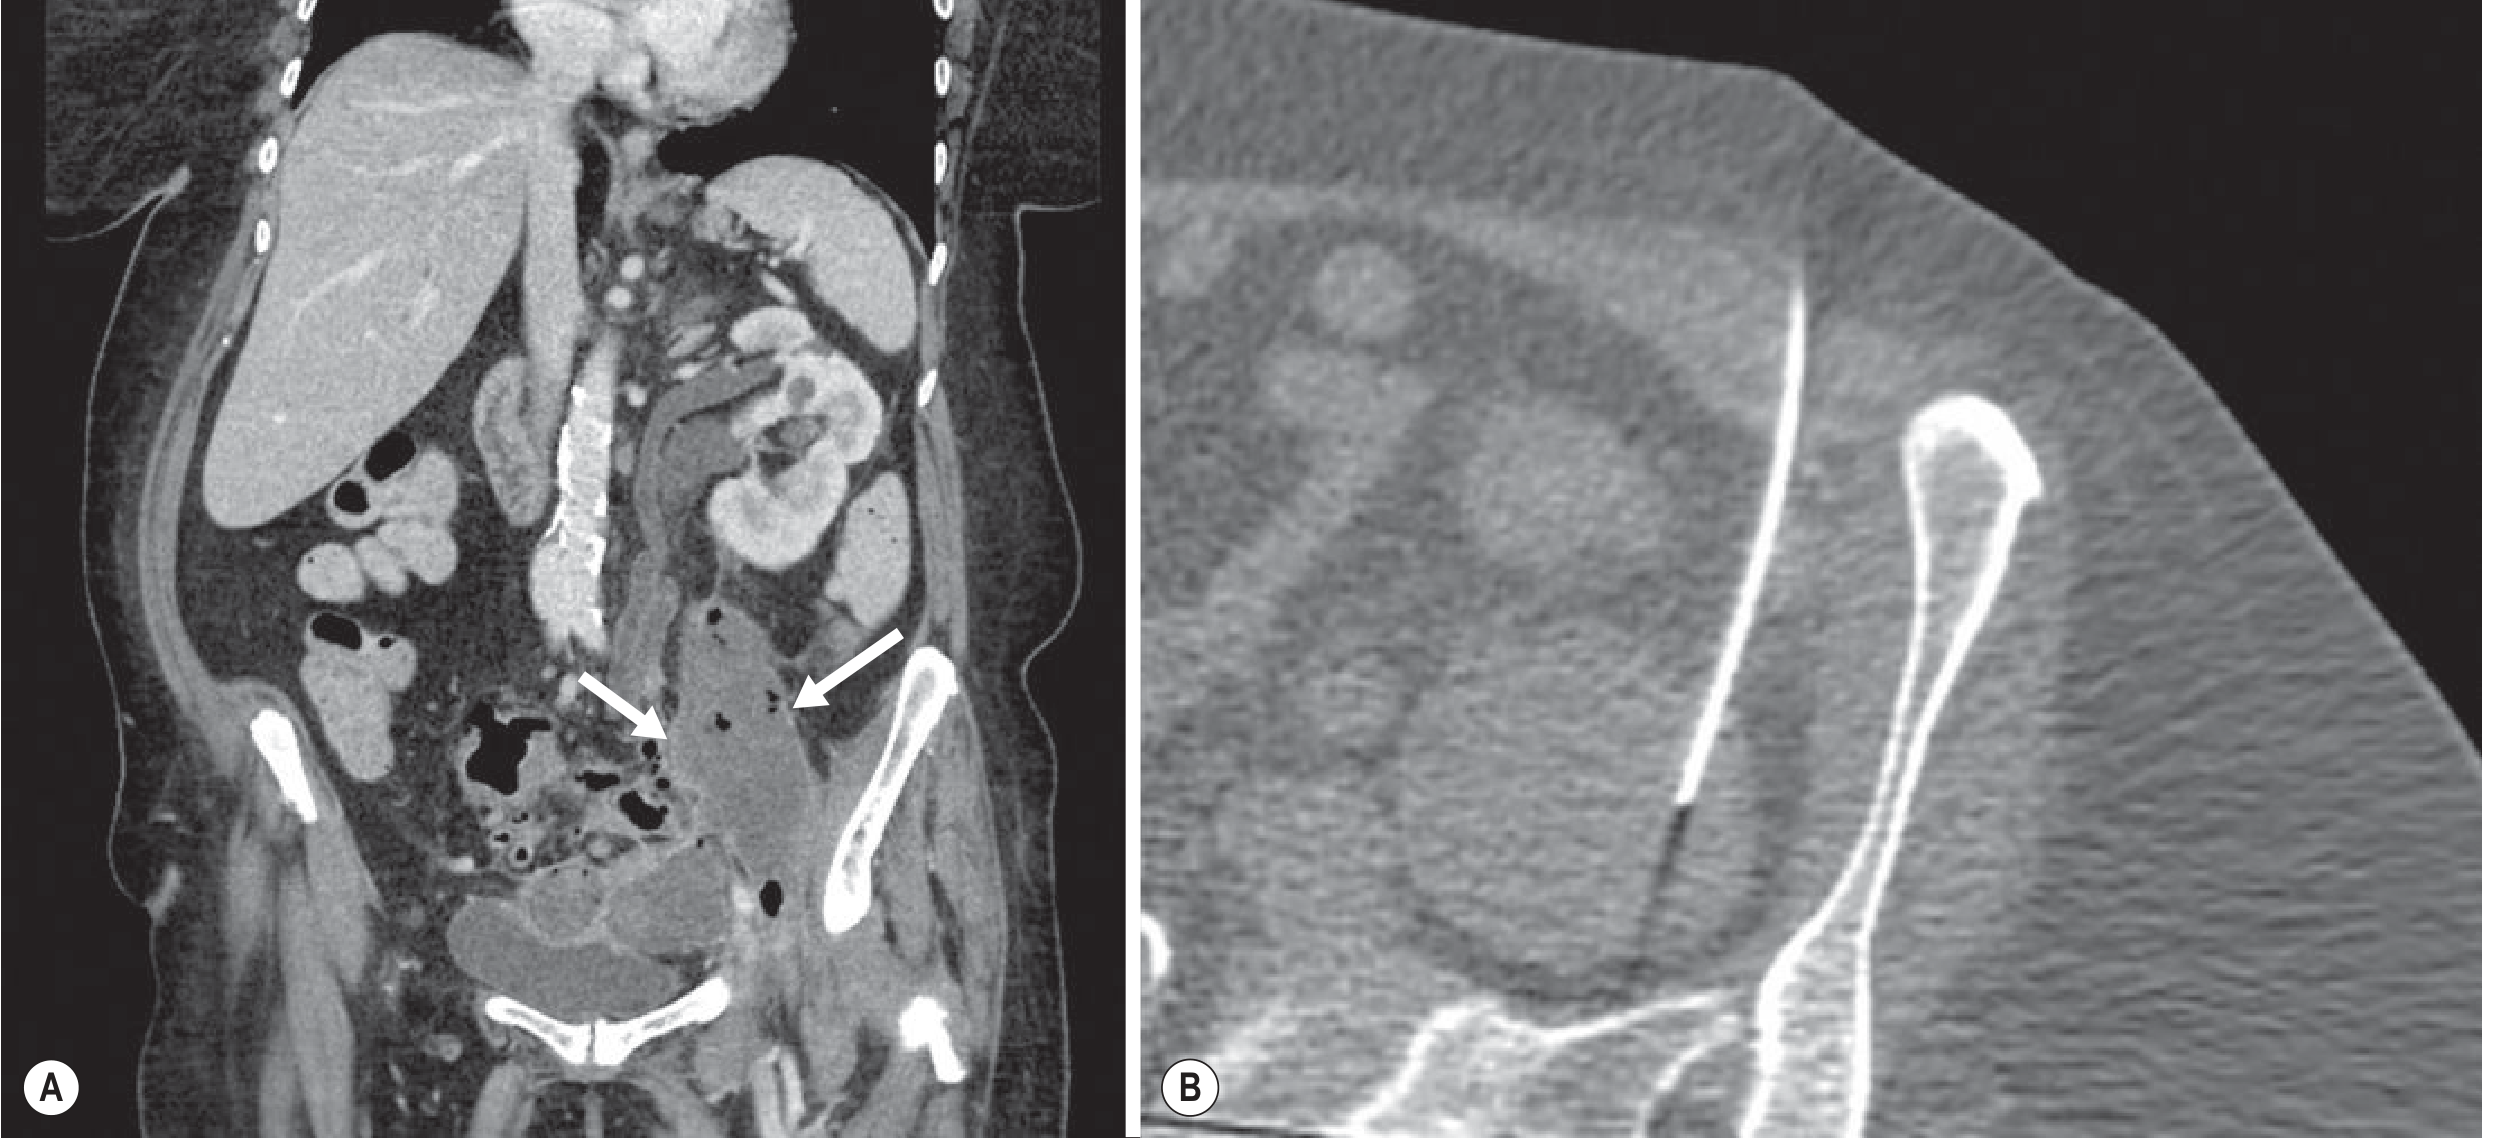
4.2 CT Fluoroscopy (Real-Time CT Guidance)
- Real-time mode: Needle held with a long clamp; operator keeps hands out of gantry while continuously imaging as needle is advanced
- Quick-check mode (more common): Intermittent rapid CT acquisitions timed to needle manipulation — shorter exposures than true real-time
- Typically uses reduced tube current (30–50 mA) to limit dose
- Images reconstructed and displayed at ~6 frames per second
- Scan length limited to a few cm around the target
- Overcomes the problem of respiratory motion — critical for kidney, liver, and lung lesions where the target moves with breathing
- Faster procedures: reduces needle manipulation steps
- Particularly valuable for: kidney biopsy, percutaneous cryoablation, RFA of renal tumors, fluid aspiration, drain placement, catheter placement
- Increased radiation dose to both patient and operator
- Operator hands may be in or near the gantry → radiation exposure risk
- Requires specific CT scanner capability
"Real-time CT fluoroscopy is available as an option on new CT imaging equipment. CT fluoroscopy gives a 3D CT image that is much more detailed and offers greater soft-tissue contrast and resolution than conventional CT. One significant disadvantage of CT fluoroscopy is the increased radiation exposure to the patient and radiologist or surgeon performing the procedure." — Campbell-Walsh Urology
4.3 Gantry Tilt
- The CT gantry can be tilted in the craniocaudal direction (typically ±30°)
- Creates an oblique imaging plane, allowing access to lesions where the axial plane alone does not provide a safe route (e.g., lesion near the dome of the liver covered by the lung, or access below a rib)
- The gantry laser guide projected onto the patient skin remains essential for orienting the operator when the gantry is tilted
- Limitation: adds complexity for the operator in maintaining the needle along the correct angulated trajectory
4.4 CT/Fluoroscopy Combined Method
- CT phase: Needle access to the target confirmed under CT guidance (superior soft-tissue detail)
- Fluoroscopy phase: Wire manipulation, catheter advancement, tract dilation, and final catheter positioning confirmed under fluoroscopy (real-time with contrast)
"The procedure can be performed under sole CT guidance or as a combined CT/fluoroscopy method. Needle access is gained under CT guidance, and a guidewire is inserted. Subsequent tract dilatation and catheter insertion is done under fluoroscopic control." — Grainger & Allison's Diagnostic Radiology
4.5 Cone-Beam CT (CBCT) in the Interventional Suite
- Available directly within the hybrid angiography/interventional suite — no separate CT room needed
- Produces 3D volumetric images equivalent to conventional CT for guidance purposes
- Software fusion packages overlay this 3D volume onto live fluoroscopic images (fluoroscopic overlay navigation)
- Shown to be equivalent to conventional CT guidance for drain placement with reduced procedure time
- Enables intraprocedural confirmation of device position in 3D (e.g., ablation probe, screw fixation, drain)
"Cone-beam CT, where available on modern angiography units, allows the acquisition of three-dimensional volumetric images in the interventional suite. Software fusion packages then allow this volumetric data to be superimposed on live fluoroscopic images. This technique has been shown to be equivalent to conventional CT guidance for drain placement with reduced procedure time." — Grainger & Allison's Diagnostic Radiology
- Percutaneous abdominal/pelvic abscess drain placement
- Complex vascular interventions
- Percutaneous screw fixation of pelvic bone metastases
- Intraprocedural verification in hepatic ablation and TACE (e.g., lipiodol deposition assessment)
5. INTERVENTIONAL PROCEDURES PERFORMED UNDER CT GUIDANCE
5.1 CT-Guided Biopsy
| Type | Gauge | Use | Yield |
|---|---|---|---|
| Fine Needle Aspiration (FNA) | 20–25G | Cytology; cystic lesions | Cells only |
| Core Needle Biopsy (CNB) | 14–18G | Histology with tissue architecture | Tissue cores |
| Coaxial technique | 17–19G introducer + inner needle | Multiple passes through single skin puncture | Reduced complications |
- Deep retroperitoneal or mediastinal lesions
- Lesions not visible / poorly visible on ultrasound
- Lesions requiring precise angulated approaches
- Pancreatic masses (EUS preferred if available; CT as alternative)
- Pleural and pericardial lesions
- Bone and spinal lesions
- Hemorrhage (most common)
- Pneumothorax (lung/pleural biopsy — ~15–25% incidence, majority managed conservatively)
- Biliary peritonitis, bowel perforation, gallbladder perforation
- Haemobilia, arterioportal shunt
- Mortality ~1:10,000 (cirrhosis and malignancy are risk factors)
- Route through intervening normal liver parenchyma probably reduces hemorrhage risk
- Avoid transgressing: hilum, gallbladder, hepatic flexure, stomach, duodenum, pleura, lung
- Contrast-Enhanced Ultrasound (CEUS): Used before biopsy to distinguish viable tumor from prior ablation zone — arterial enhancement of tumor recurrence around an ablation zone guides precise targeting
5.2 CT-Guided Fluid Aspiration and Percutaneous Drainage
- Abdominal/pelvic abscesses (post-surgical, diverticular, Crohn's, appendiceal)
- Pleural effusions (when ultrasound guidance inadequate or complex)
- Hepatic abscesses, renal cyst infection
- Psoas abscess
- Pancreatic pseudocysts and collections
- Empyema
- Gas within a collection (ultrasound cannot penetrate gas)
- Adjacent bowel loops obscure ultrasound window
- Deep retroperitoneal collections
- Complex multiloculated collections requiring precise access window planning
- Small-bore pigtail catheters (8–14F) with multiple side holes and locking mechanisms
- Placed using modified Seldinger technique (needle → guidewire → dilator → catheter)
5.3 CT-Guided Ablation Procedures — Thermal and Non-Thermal
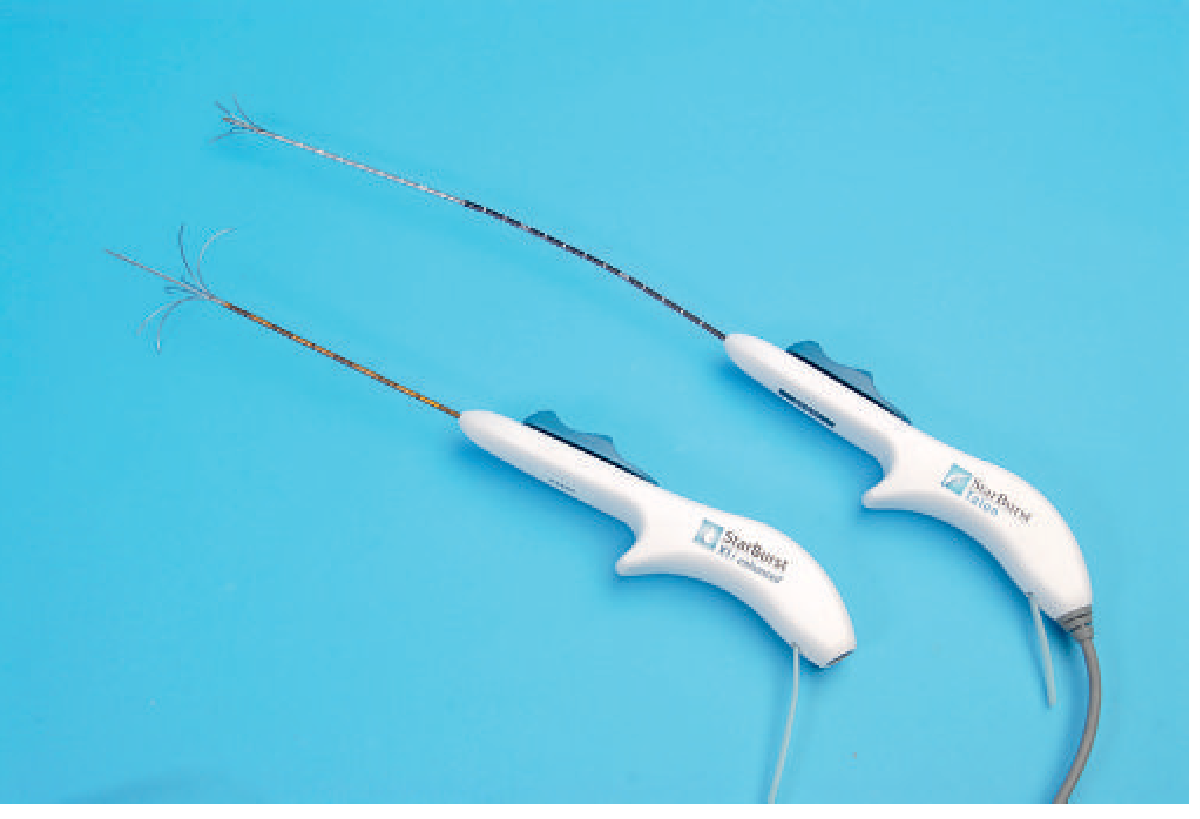
A. Radiofrequency Ablation (RFA)
- Single needle: 3–5 cm sphere of destruction in 15–20 minutes
- Expandable/clustered multi-tine arrays: overcome single-probe limitations by deploying multiple tines from one handle → larger, more reproducible ablation zones
- Cooled-tip electrodes: circulate saline internally to prevent charring at probe surface → allows higher power delivery
B. Microwave Ablation (MWA)
- Active heating zone extends ~10 mm around the active antenna tip
- Subsequent conductive heating less compromised by heat sink effect and tissue charring
- Faster ablation (single probe can be repositioned after ~5 minutes)
- Multiprobe interactive arrays available for larger volumes
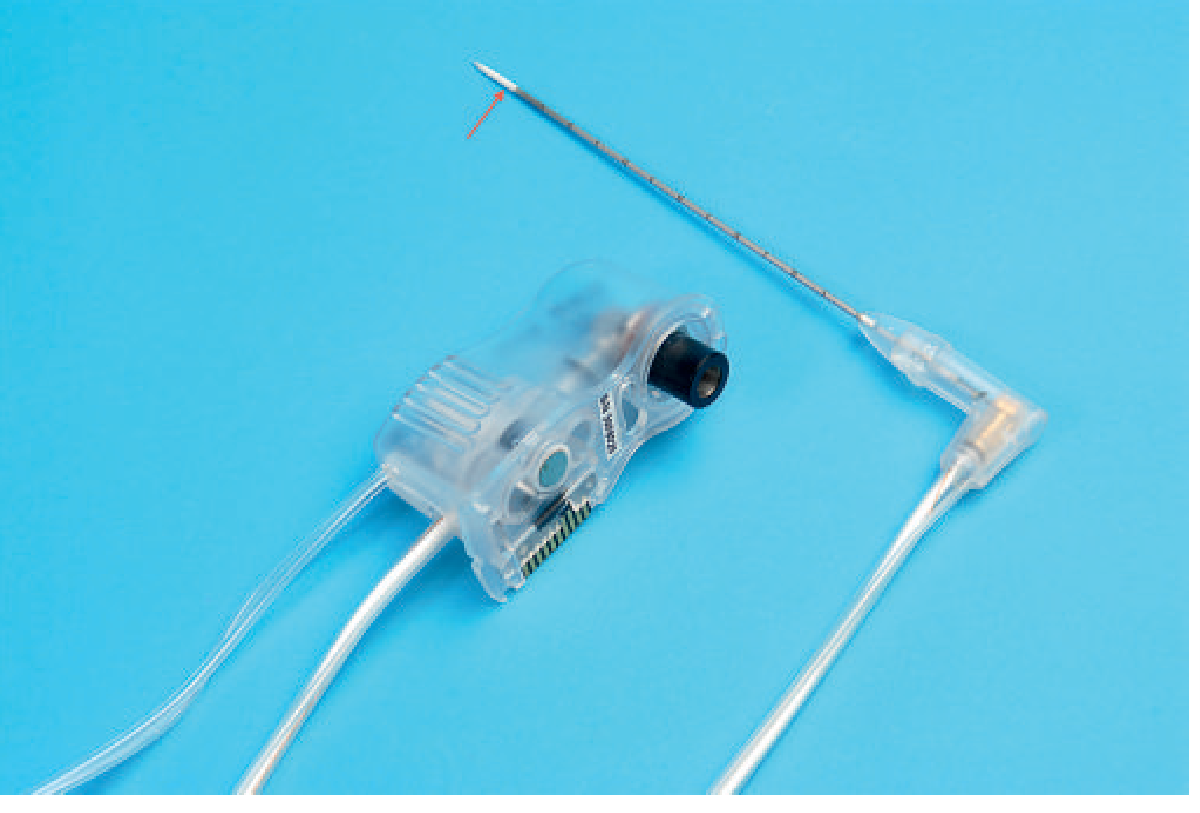
C. Cryoablation (CRA)
- Intracellular ice formation → disrupts organelles
- Extracellular ice formation + osmotic dehydration
- Microvascular endothelial injury
- Importantly: collagenous structures (pelvicalyceal system, bile ducts, vessels) are preserved → preferred near critical structures
"The outstanding feature of CRA is the physical iceball created through the tissues during the treatment cycle. The evolution of the iceball is more predictable and the phase change to ice is clearly visualised by current ultrasound, CT and MRI modalities." — Grainger & Allison's Diagnostic Radiology
D. Irreversible Electroporation (IRE)
- Severe muscle contractions from direct current → general anesthesia + muscle relaxants required
- Risk of cardiac dysrhythmias → ECG synchronization of current pulses required
- Limited clinical experience
E. Interstitial Laser Photocoagulation (ILP)
F. Focused Ultrasound (FUS/HIFU)
- Focuses 1 MHz acoustic energy onto a small focal zone (~12 × 3 mm per "sonication")
- Stacked sonications create larger ablation volumes
- Requires motion correction and respiratory gating for mobile organs
5.4 CT-Guided Drainage — Nephrostomy
- Sole CT guidance, or
- Combined CT/fluoroscopy method
5.5 CT-Guided Bone and Spinal Interventions
"Bone and spinal intervention is often performed under CT guidance." — Grainger & Allison's Diagnostic Radiology
- Vertebroplasty and kyphoplasty: CT confirms pedicle needle placement before cement injection
- Bone biopsy: Precise targeting of lytic/blastic lesions
- Percutaneous screw fixation of pelvic bone metastases (CBCT navigation)
- Nerve blocks and facet joint injections: CT provides precise anatomical localization when ultrasound/fluoroscopy are inadequate
- Epidural and paravertebral injections
6. ADVANCED AND EMERGING GUIDANCE TOOLS
6.1 Electromagnetic Navigation (EM Navigation)
- CT-guided lung biopsy: EM navigation used alongside CT fluoroscopy to improve targeting of peripheral pulmonary nodules in 60 consecutive patients (Grand et al.)
- Particularly useful for out-of-plane needle trajectories
- Reduces number of CT acquisitions needed → dose reduction
6.2 Optical Tracking Navigation Systems
- Imports pre-procedure CT → 3D reconstruction of target organ
- Plans optimal puncture path (safe, unobstructed trajectory)
- Registers patient coordinate system to world coordinate system via rigid registration of optical markers
- Guides the needle/robotic arm along the preplanned path in real time
6.3 Robotic Systems for CT-Guided Interventions
- Plan and mechanically align the needle guide toward the target
- Operator manually advances the needle along the preplanned axis
- Examples: Micromate (Interventional Systems), MAXIO, iSYS
- Autonomously advance the needle to the planned depth after alignment
- Fully motorized insertion along planned trajectory
- Higher accuracy but additional safety considerations
- Improved needle placement accuracy (±1–2 mm)
- Enables out-of-plane and double-angulated insertions not easily achieved manually
- Reduces radiation exposure to operator (hands away from gantry)
- Reduces number of CT check scans needed → lower total patient dose
- Reduces operator fatigue and variability
- First robotic needle system with FDA 510(k) clearance for CT optical navigation: Micromate (2023)
- CT-guided lung biopsy (comparison of robotic vs. CT fluoroscopy shows equivalent accuracy)
- CT-guided microwave ablation of abdominal tumors
- Liver, kidney, adrenal ablation
- Spine procedures
6.4 Augmented Reality (AR) and Extended Reality (XR) Navigation
- Pre-planning: 3D CT reconstructions reviewed in AR space before the procedure → optimized trajectory planning
- Intraprocedural: 2D/3D CT-fusion reference projected onto the procedural table, or viewed through HMD while scrubbed in → real-time guidance without needing to look at a remote monitor
- AR-enhanced percutaneous vertebroplasty: 100% clinical success rate in one study
- AR-guided percutaneous tumor procedures: live tracking accurate to ~5 mm in live patients
- Reduced procedure time
- Reduced radiation exposure to both patient and operator
- Pre-planning AR for CT-guided liver biopsies: less radiation, shorter indwelling needle time, fewer needle manipulations
- AR-HMD holographic guidance during percutaneous tumor ablation: difference between planned AR coordinates and physical anatomic markers = 3.3 mm
6.5 CT-US Fusion / Multi-Modality Fusion Guidance
- Ultrasound provides real-time guidance + no radiation
- CT provides better anatomical context, target localization, and lesion visibility (for lesions poorly visible on US)
- Particularly valuable for:
- Liver lesions visible on CT but not on B-mode US
- Post-ablation tumor recurrence (CEUS + CT fusion identifies viable tissue adjacent to ablation zone)
- Portal vein catheterization
6.6 AI-Assisted Needle Guidance (Software Integrated into CT Systems)
- myNeedle Companion (2D): Displays a fused coronal CT reconstruction alongside the current scan to visually guide in-plane procedures; automated needle trajectory planning
- myNeedle Guide 3D: Powerful 3D guidance for double-angulated procedures — plans and displays the needle path in 3D
- myNeedle Laser: Fully integrated laser guidance system; projects a laser cross onto the patient's skin aligning with the hub of the inserted needle to confirm the correct insertion angle along the preplanned path
6.7 Hybrid Interventional CT Suites (CT-Angiography Combined Systems)
- Combines a full-rotation angiography suite with a 320-detector row CT gantry on shared floor rails
- FDA-cleared 2025; commercially available 2026
- Allows the interventionalist to switch between fluoroscopic angiography and high-quality volumetric CT without moving the patient
- 4D CT capability: dynamic acquisition for perfusion, vascular mapping, and real-time ablation monitoring
- Applications: complex hepatic and endovascular interventions, TACE with CT confirmation, vertebral augmentation
7. CHOICE OF GUIDANCE MODALITY — DECISION FRAMEWORK
Target lesion
│
├─── Visible on ultrasound?
│ ├── Yes + superficial + simple → ULTRASOUND (real-time, no radiation)
│ └── No / gas / deep / complex → CT GUIDANCE
│
├─── CT guidance selected
│ ├── Simple axial approach, stable patient → CONVENTIONAL (quick-check) CT
│ ├── Respiratory motion significant (lung/kidney) → CT FLUOROSCOPY
│ ├── Non-axial trajectory required → GANTRY TILT + CT
│ ├── Complex drainage, needs catheter manipulation → CT + FLUOROSCOPY COMBINED
│ └── In interventional angio suite → CONE-BEAM CT ± FLUOROSCOPIC OVERLAY
│
└─── Advanced precision required / complex anatomy
├── EM navigation or optical tracking
├── Robotic assistance
└── AR/XR guidance or AI needle companion software
8. SUMMARY TABLE — Guidance Tools at a Glance
| Tool | Real-Time? | Radiation | Key Advantage | Key Limitation |
|---|---|---|---|---|
| Conventional CT (quick-check) | No | Moderate | Low dose, widely available | Breath-hold dependent |
| CT Fluoroscopy | Yes | High | Overcomes respiratory motion | High operator/patient dose |
| Gantry tilt | No | Moderate | Non-axial access window | Added complexity |
| CT + Fluoroscopy combined | Partial | Moderate | Best of both modalities | Two-room or two-system setup |
| Cone-Beam CT (CBCT) | Near real-time | Moderate | In-suite 3D; fluoroscopic overlay | Lower soft-tissue resolution than CT |
| EM Navigation | Yes (tracking) | Low | Out-of-plane trajectories; dose reduction | Registration drift with patient motion |
| Optical tracking + Robotics | Yes (tracking) | Low | Sub-2 mm accuracy; no operator radiation | Cost; setup time |
| Augmented Reality | Yes | Low | Hands-free; intuitive 3D visualization | Registration accuracy; organ deformation |
| CT-US Fusion | Yes (US) | Low | Real-time US + CT context | Lesion must be visible on US after fusion |
| AI Needle Software | Near real-time | Moderate | Automated trajectory planning | Dependent on vendor software |
| Hybrid CT-Angio Suite | Yes | Moderate-high | Full CT + angio in one room | Expensive; limited availability |
9. KEY EXAM POINTS — WHAT TO REMEMBER
- CT guidance = gold standard for deep/inaccessible lesions not seen on ultrasound
- Quick-check CT = most common method; lower dose; dependent on breath-holding
- CT fluoroscopy = real-time but highest radiation — operator must use long clamps and stand back
- Gantry tilt = allows access beyond axial plane; laser guide is essential
- Coaxial technique = one skin entry → multiple biopsy passes → fewer complications
- CBCT in hybrid suite = 3D volume + live fluoroscopic overlay → equivalent to CT for drainage with less procedure time
- Cryoablation iceball is directly visible on CT — only ablation modality with real-time CT-visible ablation zone
- RFA relies on conductive heating → vulnerable to heat-sink effect near vessels; MWA is more robust
- IRE = non-thermal → safe near major vessels and bile ducts; requires GA + ECG gating
- Robotics = ~1–2 mm accuracy, reduces operator radiation, enables double-angulated trajectories
- AR guidance = accurate to ~5 mm in live patients; reduces procedure time and radiation
- Combined CT-angio suites (Canon Alphenix 4D CT) = future of complex interventional guidance
- Grainger & Allison's Diagnostic Radiology — Chapters on abdominal drainage, hepatic intervention, ablation
- Campbell-Walsh Urology 3-Volume Set — CT fluoroscopy section
- Harrison's Principles of Internal Medicine 22E — CT technique
- Current Surgical Therapy 14e — Ablation techniques
- ScienceDirect 2025 — Robotic CT-guided MWA, Miami Cancer Institute
- PMC 2025 — Optical navigation robot-assisted puncture, liver/kidney
- PMC 2025 — Smart Goggles AR CT-US fusion
- ScienceDirect 2025 — Evaluation of navigation/robotic systems for percutaneous CT-guided interventions
- Siemens Healthineers — myNeedle guidance portfolioHere is a quick orientation to the full notes above:
- Definition — what CT interventional guidance is and why CT is chosen over US/fluoroscopy
- CT vs US vs Fluoroscopy comparison table
- Standard workflow — pre-planning, positioning, localization
- Core guidance modes (the main exam topic):
- Conventional / quick-check CT
- CT Fluoroscopy (real-time) — mechanism, advantages, radiation danger
- Gantry tilt
- Combined CT + Fluoroscopy
- Cone-Beam CT with fluoroscopic overlay
- Interventional procedures performed under CT guidance:
- Biopsy (FNA, core, coaxial technique, complications)
- Drainage (abscess, pleural, nephrostomy)
- Ablation — full detail on RFA, Microwave, Cryoablation, IRE, Laser, HIFU — mechanisms, advantages, CT monitoring role
- Bone/spine interventions
- Advanced guidance tools (emerging/advances section):
- Electromagnetic navigation
- Optical tracking + Robotics
- Augmented Reality (AR/XR)
- CT-US Fusion
- AI needle companion software
- Hybrid CT-angiography suites
- Decision framework — when to use which modality
- Summary table + 12 Key Exam Points