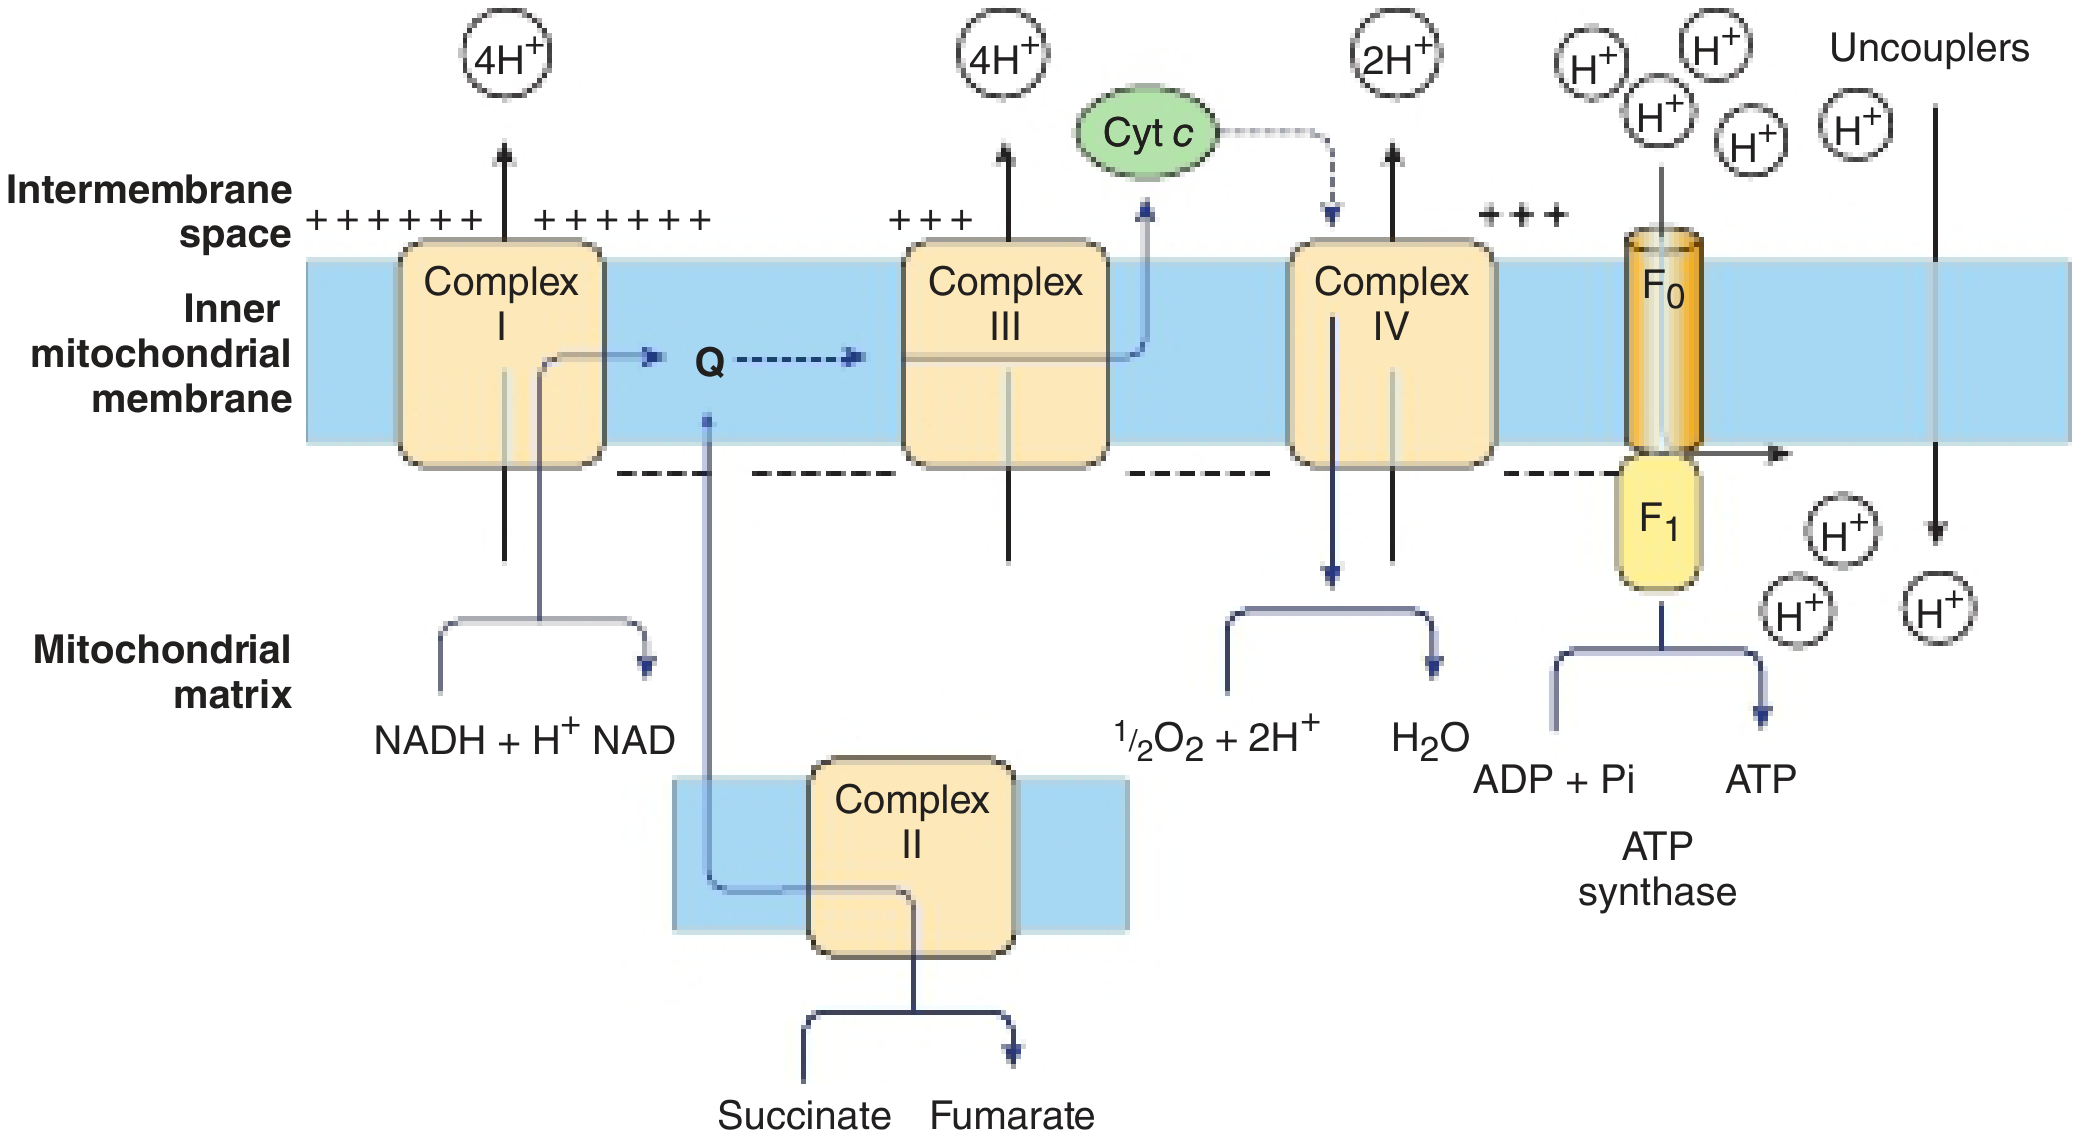
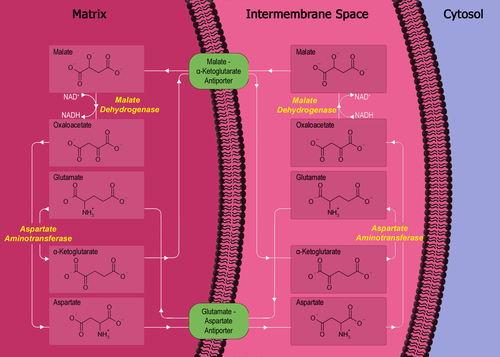
# THE ELECTRON TRANSPORT CHAIN (ETC) — A COMPREHENSIVE TREATISE
---
## TABLE OF CONTENTS
1. Introduction & Overview
2. Location and Structural Organization
3. Historical Background
4. Thermodynamic Basis
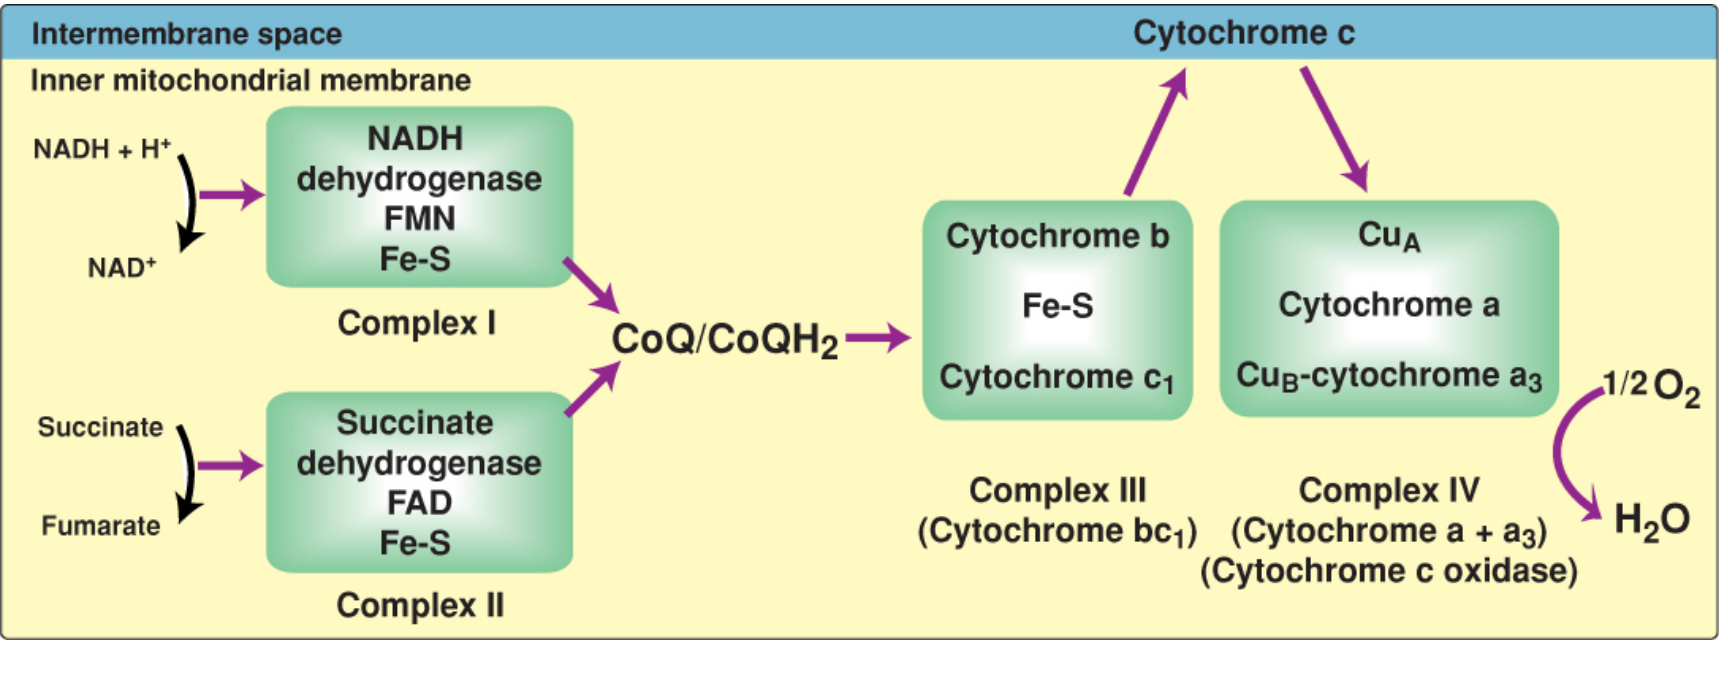
5. Components of the ETC
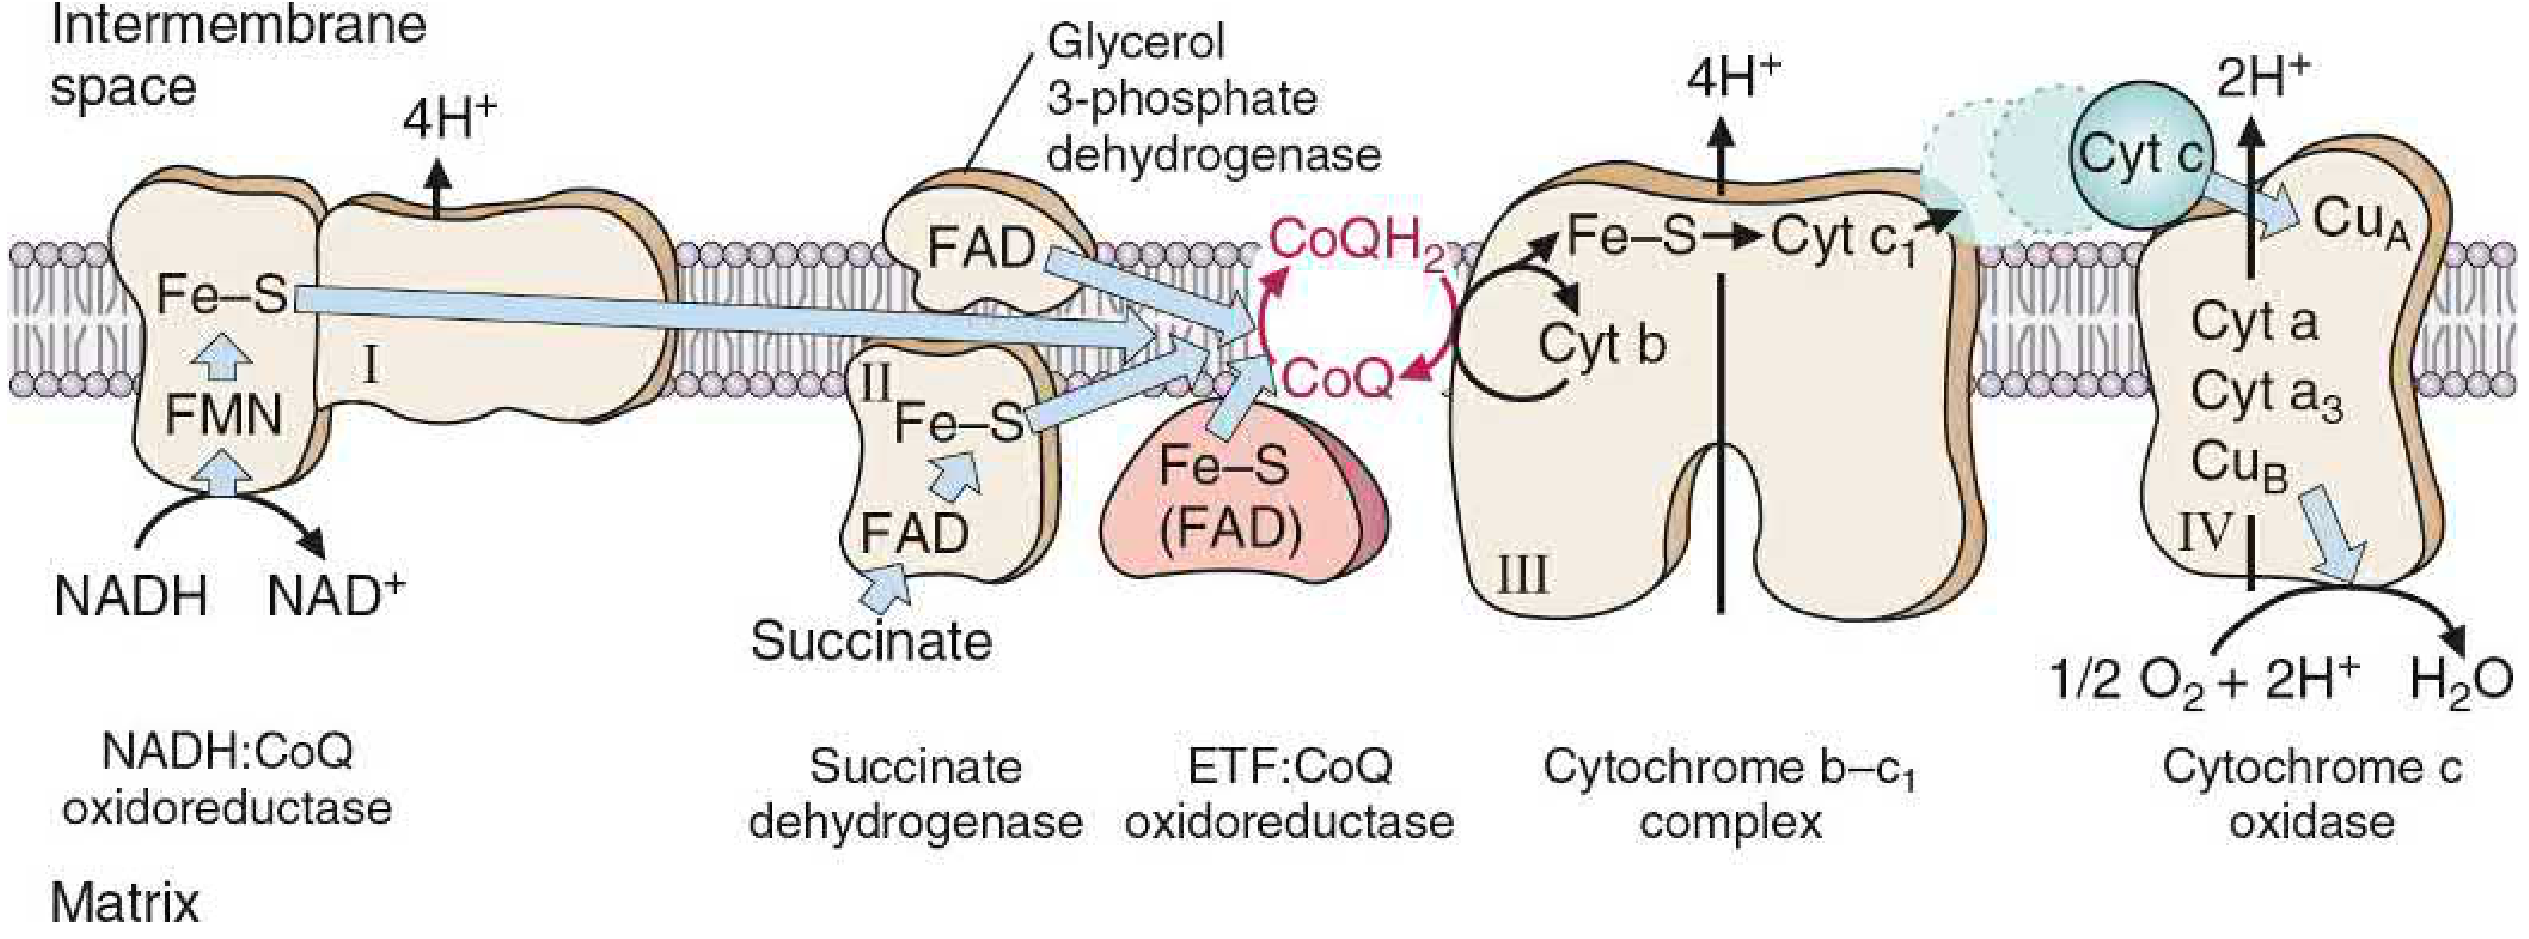
6. Complex I (NADH: Ubiquinone Oxidoreductase)
7. Complex II (Succinate: Ubiquinone Oxidoreductase)
8. Ubiquinone (Coenzyme Q)
9. Complex III (Ubiquinol: Cytochrome c Oxidoreductase)
10. Cytochrome c
11. Complex IV (Cytochrome c Oxidase)
12. Complex V (ATP Synthase) — Oxidative Phosphorylation
13. The Proton Motive Force
14. Chemiosmotic Hypothesis
15. P/O Ratios and ATP Yield
16. Shuttle Systems
17. Inhibitors of ETC
18. Uncouplers of ETC
19. Regulation of ETC
20. Reactive Oxygen Species (ROS)
21. Supercomplex Organization (Respirasomes)
22. Clinical Correlations (Comprehensive)
23. Summary Tables
---
## 1. INTRODUCTION & OVERVIEW
The **Electron Transport Chain** (also called the **respiratory chain** or **mitochondrial electron transport system**) is the final common pathway through which electrons derived from fuel molecules (carbohydrates, fats, amino acids) are transferred to molecular oxygen (O₂), the terminal electron acceptor. This process is coupled with the generation of a **proton gradient** across the inner mitochondrial membrane, which drives **ATP synthesis** via **oxidative phosphorylation**.
### Key Concepts:
- **Oxidation** = loss of electrons
- **Reduction** = gain of electrons
- Electrons flow from carriers with **more negative** (lower) reduction potential to carriers with **more positive** (higher) reduction potential
- The overall reaction:
> **NADH + H⁺ + ½O₂ → NAD⁺ + H₂O** (ΔG°' = −220 kJ/mol = −52.6 kcal/mol)
> **FADH₂ + ½O₂ → FAD + H₂O** (ΔG°' = −152 kJ/mol = −36.4 kcal/mol)
This large free energy change is released in a **stepwise manner** through the chain, preventing explosive release of energy and allowing efficient capture in the form of ATP.
---
## 2. LOCATION AND STRUCTURAL ORGANIZATION
### 2.1 Mitochondrial Anatomy
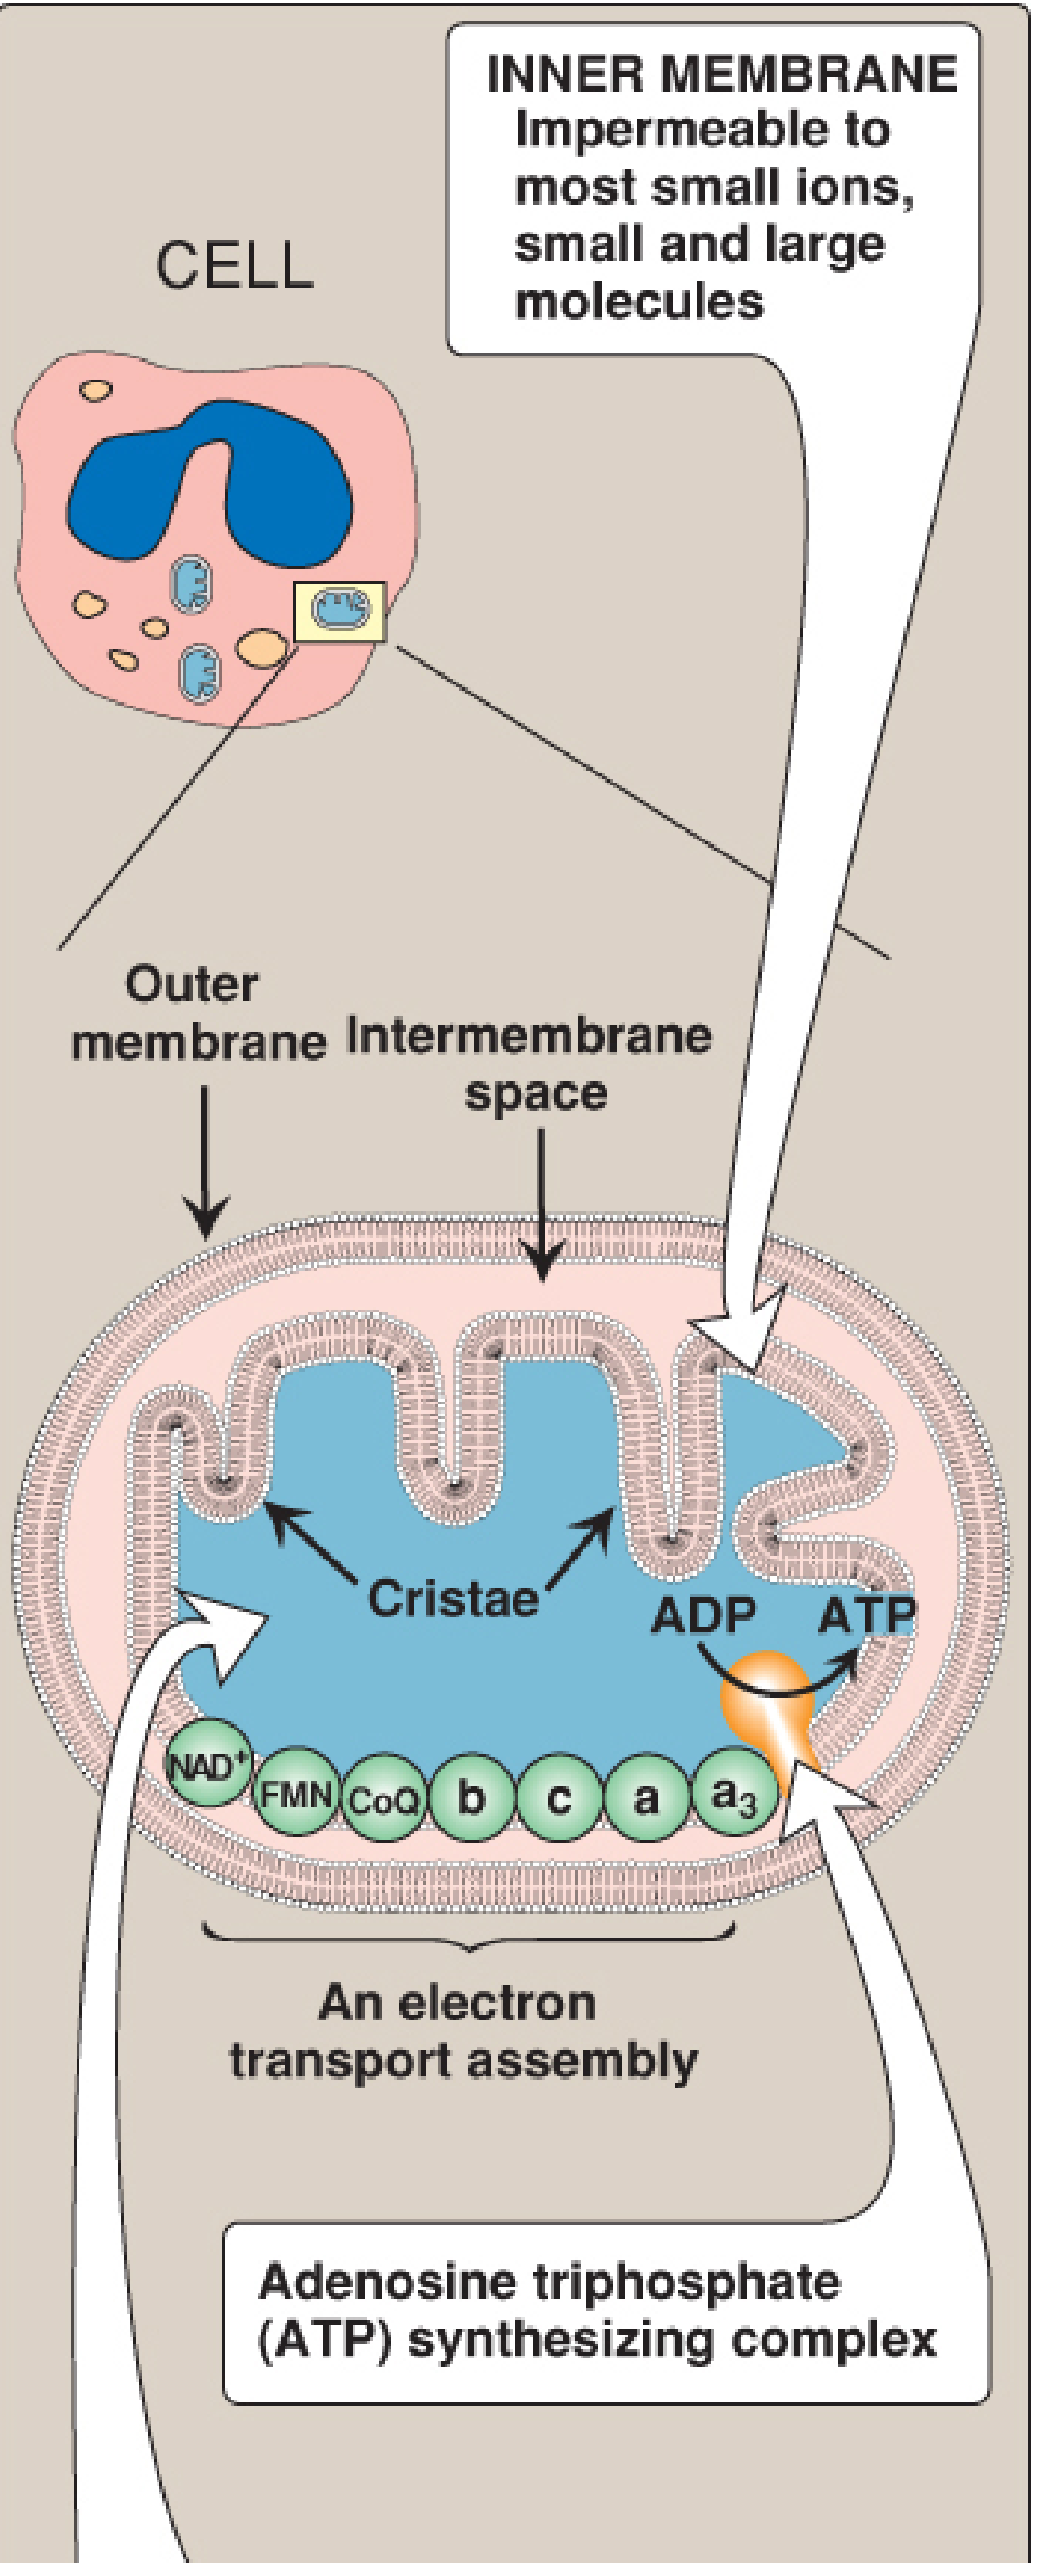
The ETC is located in the **inner mitochondrial membrane (IMM)**.
**Mitochondria** are **double-membrane** organelles:
| Structure | Features |
|-----------|----------|
| **Outer Mitochondrial Membrane (OMM)** | Permeable to molecules <5 kDa via porins (VDAC — Voltage-Dependent Anion Channel); contains monoamine oxidase (MAO) |
| **Intermembrane Space (IMS)** | ~pH 7.0 (slightly acidic relative to matrix); contains cytochrome c, adenylate kinase |
| **Inner Mitochondrial Membrane (IMM)** | Highly folded into **cristae**; IMPERMEABLE to most ions and molecules; contains ETC complexes, ATP synthase, cardiolipin; protein:lipid ratio ≈ 75:25 |
| **Mitochondrial Matrix** | ~pH 7.8 (slightly alkaline); contains TCA cycle enzymes, β-oxidation enzymes, mtDNA, mitoribosomes, PDH complex |
### 2.2 Cardiolipin
- **Diphosphatidylglycerol** — a unique phospholipid found almost exclusively in the IMM
- Contains **4 fatty acid chains** (usually linoleic acid)
- Essential for the function of Complex III, Complex IV, and ATP synthase
- Provides structural support and maintains the impermeability of the IMM to protons
> **🔴 CLINICAL: Barth Syndrome**
> - X-linked recessive disorder
> - Mutation in the **tafazzin gene (TAZ)** on Xq28
> - Tafazzin is a transacylase required for **cardiolipin remodeling**
> - Results in abnormal cardiolipin → impaired ETC function
> - Features: **dilated cardiomyopathy, skeletal myopathy, neutropenia, 3-methylglutaconic aciduria, growth retardation**
> - Predominantly affects males
### 2.3 Mitochondrial DNA (mtDNA)
- **Circular, double-stranded DNA** — 16,569 base pairs
- Encodes **37 genes**: 13 polypeptides (all ETC/ATP synthase subunits), 22 tRNAs, 2 rRNAs
- **Maternal inheritance** (mitochondria come from the ovum)
- No histones, limited repair mechanisms → high mutation rate (~10x nuclear DNA)
- **Heteroplasmy**: a cell can contain a mixture of normal and mutant mtDNA
- **Threshold effect**: disease manifests when the proportion of mutant mtDNA exceeds a critical threshold
**Subunits encoded by mtDNA:**
| Complex | mtDNA-encoded subunits |
|---------|----------------------|
| Complex I | ND1, ND2, ND3, ND4, ND4L, ND5, ND6 (7 subunits) |
| Complex II | **None** (all 4 subunits nuclear-encoded) |
| Complex III | Cytochrome b (1 subunit) |
| Complex IV | COX I, COX II, COX III (3 subunits) |
| Complex V | ATPase 6, ATPase 8 (2 subunits) |
| **Total** | **13 subunits** |
> **🔴 CLINICAL: Mitochondrial inheritance patterns**
> - All children of an affected mother may be affected (but variable expressivity due to heteroplasmy)
> - An affected father **CANNOT** transmit the disease
> - Tissues with high energy demands (brain, heart, skeletal muscle, retina, kidney) are most affected → explains the clinical phenotype of mitochondrial diseases
---
## 3. HISTORICAL BACKGROUND
| Year | Contribution |
|------|-------------|
| 1897 | **Buchner** — cell-free fermentation |
| 1900 | **Warburg** — identified "Atmungsferment" (respiratory enzyme), later identified as cytochrome oxidase |
| 1925 | **Keilin** — rediscovered cytochromes (a, b, c) using spectroscopy |
| 1937 | **Kalckar** — linked oxidation to phosphorylation |
| 1948 | **Kennedy & Lehninger** — localized oxidative phosphorylation to mitochondria |
| 1961 | **Peter Mitchell** — proposed the **Chemiosmotic Hypothesis** (Nobel Prize 1978) |
| 1964 | **Hatefi** — isolated the four respiratory complexes |
| 1979 | **Anderson** — sequenced human mtDNA |
| 1994 | **John Walker** — determined the crystal structure of ATP synthase (Nobel Prize 1997 with Paul Boyer) |
---
## 4. THERMODYNAMIC BASIS
### 4.1 Standard Reduction Potential (E°')
Electrons flow from a **more negative** E°' to a **more positive** E°'.
| Redox Pair | E°' (Volts) |
|------------|-------------|
| NAD⁺/NADH | −0.32 V |
| FAD/FADH₂ (free) | −0.22 V |
| FAD/FADH₂ (in Complex II) | +0.03 V |
| CoQ/CoQH₂ | +0.04 V |
| Cytochrome b (Fe³⁺/Fe²⁺) | +0.07 V |
| Cytochrome c₁ (Fe³⁺/Fe²⁺) | +0.22 V |
| Cytochrome c (Fe³⁺/Fe²⁺) | +0.25 V |
| Cytochrome a (Fe³⁺/Fe²⁺) | +0.29 V |
| Cytochrome a₃ (Fe³⁺/Fe²⁺) | +0.55 V |
| ½O₂/H₂O | +0.82 V |
### 4.2 Free Energy Relationship
$$\Delta G°' = -nF\Delta E°'$$
Where:
- n = number of electrons transferred
- F = Faraday constant (96,485 J/V·mol = 23.06 kcal/V·mol)
- ΔE°' = E°'(acceptor) − E°'(donor)
**For NADH oxidation:**
ΔE°' = +0.82 − (−0.32) = +1.14 V
ΔG°' = −2 × 96.485 × 1.14 = −220 kJ/mol
**For FADH₂ oxidation:**
ΔE°' = +0.82 − (−0.03 for bound FAD) = +0.79 V
ΔG°' ≈ −152 kJ/mol
### 4.3 Sites of Sufficient Free Energy for ATP Synthesis
The ΔG°' for ATP synthesis = +30.5 kJ/mol (minimum required)
Three sites have sufficient ΔG drop to drive proton pumping → ATP synthesis:
1. **Complex I**: NADH → CoQ (ΔE = 0.36 V → ΔG = −69.5 kJ/mol)
2. **Complex III**: CoQH₂ → Cytochrome c (ΔE = 0.21 V → ΔG = −40.5 kJ/mol)
3. **Complex IV**: Cytochrome c → O₂ (ΔE = 0.57 V → ΔG = −110 kJ/mol)
Complex II has **insufficient** free energy change to pump protons.
---
## 5. COMPONENTS OF THE ETC — ELECTRON CARRIERS
### 5.1 Types of Electron Carriers
| Carrier Type | Carries | Examples |
|-------------|---------|----------|
| **NAD⁺/NADH** | 2 electrons + 1 H⁺ (hydride ion) | Soluble in matrix |
| **FAD/FADH₂** | 2 electrons + 2 H⁺ | Prosthetic group (tightly bound) |
| **FMN/FMNH₂** | 2 electrons + 2 H⁺ | Prosthetic group in Complex I |
| **Coenzyme Q (Ubiquinone)** | 2 electrons + 2 H⁺ | Mobile carrier in lipid bilayer |
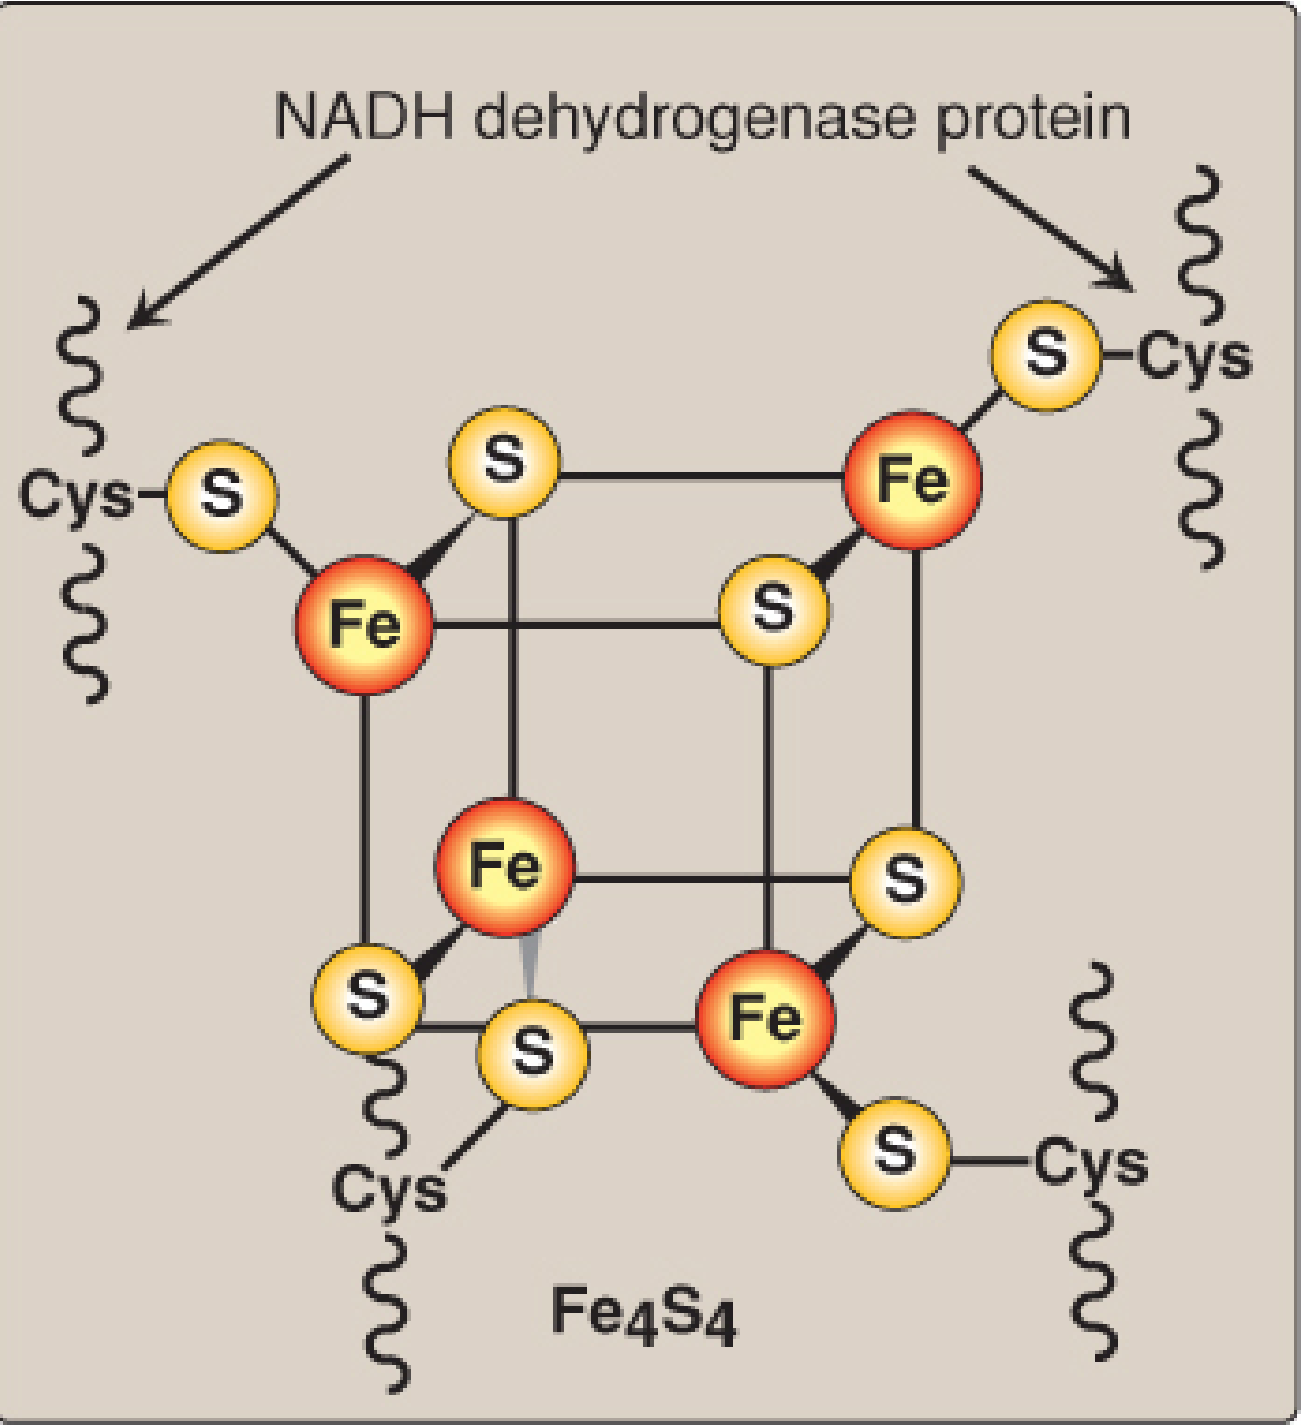
| **Iron-Sulfur Centers (Fe-S)** | 1 electron | Multiple types: [2Fe-2S], [3Fe-4S], [4Fe-4S] |
| **Cytochromes (heme iron)** | 1 electron (Fe²⁺ ↔ Fe³⁺) | Cyt b, c₁, c, a, a₃ |
| **Copper Centers** | 1 electron (Cu⁺ ↔ Cu²⁺) | CuA, CuB in Complex IV |
### 5.2 Flavin Nucleotides (FMN and FAD)
- Derived from **Riboflavin (Vitamin B₂)**
- Can accept **1 or 2 electrons** (can form a semiquinone radical intermediate)
- FMN is the **first electron acceptor** in Complex I
- FAD is the prosthetic group in Complex II (succinate dehydrogenase)
### 5.3 Iron-Sulfur Clusters
- Also called **non-heme iron** proteins
- Contain iron atoms coordinated with **inorganic sulfide (S²⁻)** and/or **cysteine sulfur** from the protein
- Types:
- **[2Fe-2S]** — Rieske center in Complex III (unique: one Fe coordinated by 2 histidines)
- **[4Fe-4S]** — most common, found in Complexes I, II, III
- **[3Fe-4S]** — found in Complex II
- Transfer **only 1 electron** at a time despite having multiple iron atoms
- The most complex arrangement is in **Complex I**: contains **8 Fe-S clusters** forming an electron "wire" ~95 Å long
### 5.4 Heme Groups and Cytochromes
Cytochromes are proteins with **heme prosthetic groups** containing iron that undergoes reversible Fe²⁺/Fe³⁺ transitions.
| Cytochrome | Heme Type | Location | Unique Features |
|-----------|-----------|----------|-----------------|
| Cyt b(bL and bH) | Heme B (protoporphyrin IX) | Complex III | Two b-type cytochromes in Q cycle |
| Cyt c₁ | Heme C (covalently attached) | Complex III | Part of the complex |
| Cyt c | Heme C | IMS (mobile carrier) | Small, water-soluble, peripheral protein; also involved in apoptosis |
| Cyt a | Heme A | Complex IV | Contains formyl group and hydroxyethylfarnesyl side chain |
| Cyt a₃ | Heme A | Complex IV | Contains the binuclear center (with CuB) where O₂ binds |
### 5.5 Copper Centers
- **CuA** in Complex IV: dinuclear copper center; first electron acceptor from cytochrome c
- **CuB** in Complex IV: paired with heme a₃ in the binuclear center; directly involved in O₂ binding and reduction
---
## 6. COMPLEX I — NADH:UBIQUINONE OXIDOREDUCTASE (EC 1.6.5.3)
### 6.1 Structure
- **Largest** respiratory complex
- **~1,000 kDa** (1 MDa) in mammals
- **45 subunits** in mammals (7 encoded by mtDNA: ND1–ND6, ND4L; 38 nuclear-encoded)
- Shaped like an **"L"** or a **boot**:
- **Hydrophilic arm** (peripheral arm): projects into the matrix; contains FMN and all Fe-S clusters
- **Hydrophobic arm** (membrane arm): embedded in the IMM; contains the proton-pumping machinery
- Contains:
- **1 FMN** (flavin mononucleotide)
- **8 iron-sulfur clusters**: N1a [2Fe-2S], N1b [2Fe-2S], N2 [4Fe-4S], N3 [4Fe-4S], N4 [4Fe-4S], N5 [4Fe-4S], N6a [4Fe-4S], N6b [4Fe-4S]
- The Fe-S clusters form a **~95 Å electron transfer wire**
### 6.2 Mechanism
1. **NADH** binds to the hydrophilic arm and donates **2 electrons as a hydride ion (H⁻)** to **FMN** → **FMNH₂**
2. FMNH₂ passes electrons **one at a time** through the chain of **8 Fe-S clusters**
3. The terminal Fe-S cluster **N2** (highest potential in the chain) donates electrons to **ubiquinone (CoQ)** bound at the ubiquinone-binding site at the junction of the two arms
4. CoQ is reduced: **Q → QH⁻ (semiquinone) → QH₂ (ubiquinol)**
5. The energy released drives **conformational changes** in the membrane arm that translocate **4 H⁺** from the matrix to the IMS
### 6.3 Proton Pumping Mechanism
- The membrane arm contains **three antiporter-like subunits** (ND2, ND4, ND5) each pumping **1 H⁺**
- A **fourth proton** is pumped at the junction/interface near the ubiquinone-binding site (ND1/ND6 region)
- Total: **4 H⁺ pumped per NADH** (per 2 electrons)
- The mechanism involves a **long-range conformational coupling** — a "piston-like" mechanism transmitted through a long amphipathic helix connecting the antiporter subunits
### 6.4 Overall Reaction
> **NADH + H⁺ + Q + 4H⁺(matrix) → NAD⁺ + QH₂ + 4H⁺(IMS)**
### 6.5 Inhibitors of Complex I
| Inhibitor | Source/Type | Mechanism |
|-----------|-----------|-----------|
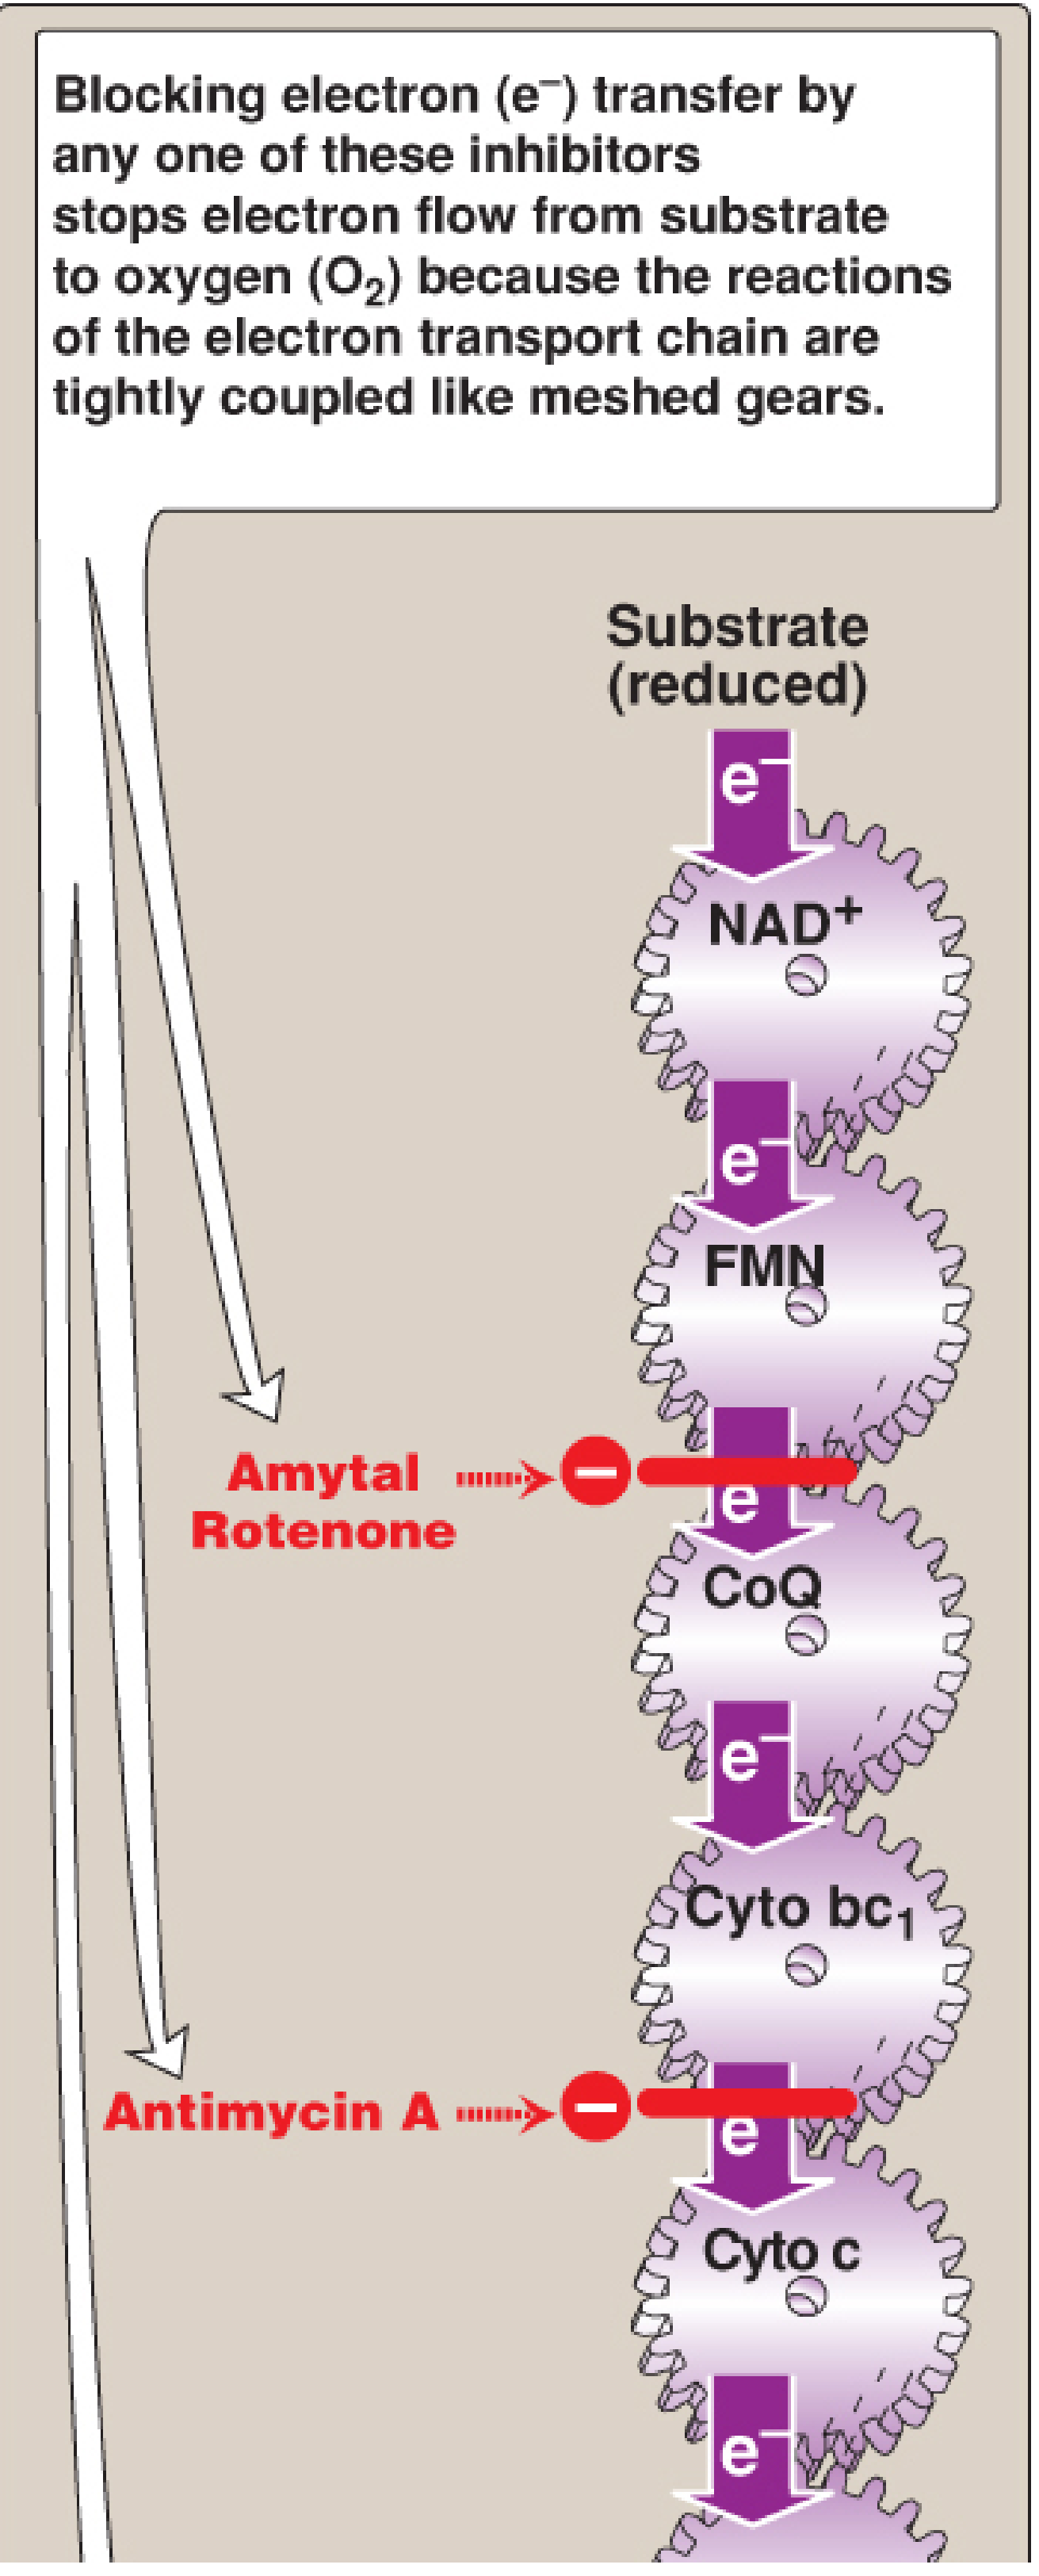
| **Rotenone** | Plant insecticide (from Derris plant roots) | Blocks electron transfer from Fe-S cluster N2 to ubiquinone |
| **Piericidin A** | Streptomyces antibiotic | CoQ analog; competes at Q-binding site |
| **Barbiturates (Amobarbital/Amytal)** | Pharmaceutical | Block at the same site as rotenone |
| **MPP⁺ (1-methyl-4-phenylpyridinium)** | Active metabolite of MPTP | Inhibits Complex I |
> **🔴 CLINICAL: Rotenone and Parkinson's Disease**
> - Chronic rotenone exposure in animal models produces **Parkinsonism** including selective dopaminergic neuron death and **Lewy body-like inclusions**
> - Dopaminergic neurons in the **substantia nigra pars compacta** are especially vulnerable due to high energy demands and high oxidative stress
> - Epidemiological studies link pesticide exposure (rotenone, paraquat) to increased Parkinson's disease risk
> **🔴 CLINICAL: MPTP Toxicity (Drug-induced Parkinsonism)**
> - **MPTP** (1-methyl-4-phenyl-1,2,3,6-tetrahydropyridine) is a contaminant of synthetic heroin ("designer drug")
> - MPTP crosses the blood-brain barrier → taken up by astrocytes → converted to **MPP⁺** by **MAO-B (monoamine oxidase B)**
> - MPP⁺ is selectively taken up by dopaminergic neurons via the **dopamine transporter (DAT)**
> - MPP⁺ inhibits **Complex I** → ATP depletion, ROS generation → selective death of dopaminergic neurons
> - Produces **acute, irreversible Parkinsonism**
> - This discovery was pivotal in understanding Parkinson's disease pathogenesis
> - Treatment: L-DOPA, dopamine agonists (same as idiopathic Parkinson's)
> - Prevention: MAO-B inhibitors (selegiline/rasagiline) can block MPTP → MPP⁺ conversion
> **🔴 CLINICAL: Leber's Hereditary Optic Neuropathy (LHON)**
> - **Mitochondrial inheritance** (maternal)
> - Caused by point mutations in mtDNA genes encoding **Complex I subunits**
> - Most common mutations: **m.11778G>A** (ND4, ~70% of cases), **m.3460G>A** (ND1), **m.14484T>C** (ND6)
> - Presents in **young adults (15-35 years)**, more commonly in **males** (male:female = 4:1, suggesting nuclear modifier genes like X-linked factors)
> - **Acute or subacute painless bilateral central vision loss** (sequential, one eye then the other within weeks to months)
> - Loss of **central vision** with **centrocecal scotoma** (central blind spot)
> - **Optic disc pseudoedema**, peripapillary telangiectatic microangiopathy (does NOT leak on fluorescein angiography)
> - Eventually → **optic atrophy**
> - Retinal ganglion cells (especially the papillomacular bundle) are selectively vulnerable
> - No consistently effective treatment; **idebenone** (CoQ analog) may have some benefit, especially in early stages
> - Variable penetrance due to **heteroplasmy**
> - Smoking and alcohol use may trigger/worsen the disease (environmental factors)
> **🔴 CLINICAL: Complex I Deficiency**
> - Most common cause of **mitochondrial disease** in children
> - Can be caused by mutations in any of the 45 structural genes (7 mtDNA, 38 nuclear) or assembly factor genes
> - Clinical spectrum:
> - **Leigh syndrome** (subacute necrotizing encephalomyelopathy) — most severe
> - **MELAS-like syndrome**
> - **Neonatal lactic acidosis**
> - **Hypertrophic cardiomyopathy**
> - **Leukodystrophy**
> - Lab findings: elevated **lactate**, elevated **lactate:pyruvate ratio** (>20:1), elevated **alanine**
---
## 7. COMPLEX II — SUCCINATE:UBIQUINONE OXIDOREDUCTASE (EC 1.3.5.1)
### 7.1 Structure
- **Smallest** respiratory complex: ~124 kDa
- **4 subunits** — **ALL nuclear-encoded** (the ONLY ETC complex entirely nuclear-encoded)
- **SDHA**: flavoprotein subunit; contains covalently bound **FAD** and the succinate-binding site
- **SDHB**: iron-sulfur protein; contains three Fe-S clusters: [2Fe-2S], [4Fe-4S], [3Fe-4S]
- **SDHC** and **SDHD**: membrane-anchor subunits; contain **heme b** (not involved in electron transfer — may serve in ROS protection) and the ubiquinone-binding site
- Part of **both** the TCA cycle (as succinate dehydrogenase, enzyme #6) **and** the ETC
### 7.2 Mechanism
1. **Succinate** is oxidized to **fumarate** (trans double bond) at the SDHA subunit
2. **FAD** is reduced to **FADH₂** (covalently bound, does NOT dissociate)
3. Electrons pass through the three Fe-S clusters in SDHB: [2Fe-2S] → [4Fe-4S] → [3Fe-4S]
4. Electrons are donated to **ubiquinone (CoQ)** at the Q-binding site in SDHC/SDHD → **ubiquinol (QH₂)**
### 7.3 Key Points
- **Does NOT pump protons** — insufficient free energy change (ΔG ≈ −6 kJ/mol for FAD → CoQ transfer)
- FADH₂ generated here enters the chain at the level of CoQ, bypassing Complex I
- Therefore, FADH₂ from Complex II generates **fewer ATP** than NADH (1.5 vs. 2.5 ATP)
### 7.4 Overall Reaction
> **Succinate + Q → Fumarate + QH₂**
> (No proton pumping)
### 7.5 Inhibitors of Complex II
| Inhibitor | Mechanism |
|-----------|-----------|
| **Malonate** | Competitive inhibitor of succinate (structural analog — dicarboxylic acid) |
| **Carboxin** | Blocks Q-binding site |
| **TTFA (thenoyltrifluoroacetone)** | Blocks Q-binding site |
| **3-Nitropropionic acid (3-NPA)** | Irreversible inhibitor; causes striatal necrosis |
> **🔴 CLINICAL: Hereditary Paraganglioma-Pheochromocytoma Syndrome**
> - Germline mutations in **SDHB, SDHC, SDHD** (and also **SDHA**, **SDHAF2**)
> - These are **tumor suppressor genes** (loss-of-function mutations)
> - SDH deficiency → accumulation of **succinate** → inhibits **prolyl hydroxylases (PHDs)** → stabilization of **HIF-1α (Hypoxia-Inducible Factor)** → **pseudohypoxic signaling** → angiogenesis, proliferation
> - This is an example of an **oncometabolite** mechanism
> - Clinical manifestations:
> - **Paragangliomas** (especially head and neck — carotid body tumors)
> - **Pheochromocytomas** (adrenal medulla)
> - **Gastrointestinal stromal tumors (GISTs)**
> - **Renal cell carcinoma**
> - **SDHB** mutations: highest malignancy risk (~30-40% metastatic)
> - **SDHD** mutations: predominantly **paternally inherited** expression (genomic imprinting)
> - Screening: plasma/urine **metanephrines and catecholamines**
> - Immunohistochemistry: loss of **SDHB** staining in tumor tissue is a marker
> **🔴 CLINICAL: Carney-Stratakis Syndrome**
> - Dyad of **paraganglioma** and **gastrointestinal stromal tumor (GIST)**
> - Due to germline **SDH subunit mutations**
> - Distinct from Carney triad (paraganglioma, GIST, pulmonary chondroma — usually sporadic)
> **🔴 CLINICAL: 3-Nitropropionic Acid (3-NPA) Toxicity**
> - Found in **moldy sugarcane** (Arthrinium saccharicola fungus)
> - Irreversibly inhibits Complex II (SDH)
> - Causes **acute encephalopathy** with selective **bilateral striatal (basal ganglia) necrosis**
> - Mimics **Huntington's disease** pathology
> - Used as an experimental model for Huntington's disease
### 7.6 Other FADH₂-Linked Dehydrogenases
Several other enzymes feed electrons to CoQ via FADH₂ without going through Complex I or Complex II:
| Enzyme | Pathway | Location |
|--------|---------|----------|
| **Electron-transferring flavoprotein (ETF) dehydrogenase** / ETF:QO | β-oxidation of fatty acids | IMM |
| **Glycerol-3-phosphate dehydrogenase (mitochondrial)** | Glycerol-3-phosphate shuttle | Outer surface of IMM |
| **Dihydroorotate dehydrogenase** | Pyrimidine biosynthesis | IMM |
| **Choline dehydrogenase** | Choline metabolism | IMM |
| **Proline dehydrogenase** | Proline metabolism | IMM |
These all reduce CoQ to CoQH₂, entering the ETC at the same point as Complex II (bypassing Complex I → therefore ~1.5 ATP per FADH₂).
> **🔴 CLINICAL: Multiple Acyl-CoA Dehydrogenase Deficiency (MADD) / Glutaric Aciduria Type II**
> - Deficiency of **ETF** or **ETF:ubiquinone oxidoreductase (ETF-QO)**
> - Impairs electron transfer from multiple FAD-linked dehydrogenases → impaired β-oxidation, branched-chain amino acid oxidation, and others
> - Biochemical: elevated multiple acylcarnitines, organic acids (glutaric, ethylmalonic, adipic, suberic acids)
> - Clinical: severe neonatal form (with or without congenital anomalies — renal cysts, facial dysmorphism) or milder late-onset form (lipid storage myopathy)
> - Treatment: **riboflavin** (B₂) — many cases are riboflavin-responsive (especially late-onset)
---
## 8. UBIQUINONE (COENZYME Q / CoQ₁₀)
### 8.1 Structure
- **2,3-dimethoxy-5-methyl-1,4-benzoquinone** with an **isoprenoid side chain**
- In humans: **10 isoprenoid units** (CoQ₁₀ or ubiquinone-50)
- The long hydrophobic tail allows it to dissolve freely in the **lipid bilayer** of the IMM
- **Small, lipid-soluble, mobile electron carrier** — NOT a protein
### 8.2 Redox States
CoQ can exist in **three redox states**:
1. **Ubiquinone (Q)** — fully oxidized
2. **Semiquinone radical (QH• or Q•⁻)** — partially reduced (one electron)
3. **Ubiquinol (QH₂)** — fully reduced (two electrons)
This ability to accept 1 or 2 electrons is crucial for the **Q cycle** in Complex III.
### 8.3 Function
- **Collects electrons** from Complexes I and II (and other FADH₂-linked dehydrogenases)
- **Shuttles electrons** to Complex III
- Acts as a **mobile electron carrier** in the membrane (unlike Fe-S clusters and cytochromes which are protein-bound)
- The **CoQ pool** contains ~10× more CoQ than Complex III → functions as a mobile electron buffer
### 8.4 Biosynthesis
- Synthesized endogenously via the **mevalonate pathway** (same pathway as cholesterol synthesis)
- The benzoquinone ring is derived from **tyrosine** (or phenylalanine)
- The isoprenoid tail is from the **mevalonate pathway** (farnesyl pyrophosphate → decaprenyl-PP)
> **🔴 CLINICAL: CoQ₁₀ Deficiency**
> - **Primary CoQ₁₀ deficiency**: autosomal recessive mutations in genes of CoQ₁₀ biosynthetic pathway (COQ2, COQ4, COQ6, COQ7, COQ8A, COQ8B, COQ9, PDSS1, PDSS2)
> - Clinical phenotypes:
> - **Cerebellar ataxia** (most common, often with cerebellar atrophy)
> - **Steroid-resistant nephrotic syndrome** (especially COQ2, COQ6, COQ8B mutations)
> - **Encephalomyopathy**
> - **Isolated myopathy** with ragged red fibers
> - **Multisystem infantile form** (severe)
> - **Secondary CoQ₁₀ deficiency**: seen in mitochondrial diseases, aging, statin therapy
> - Treatment: **oral CoQ₁₀ supplementation** (one of the few treatable mitochondrial disorders, especially the nephrotic and ataxic forms if treated early)
> **🔴 CLINICAL: Statins and CoQ₁₀**
> - Statins (HMG-CoA reductase inhibitors) inhibit the mevalonate pathway
> - This reduces not only **cholesterol** synthesis but also **CoQ₁₀** and **dolichol** synthesis
> - May contribute to **statin-associated myopathy/myalgia** (controversial but biologically plausible)
> - Some clinicians recommend **CoQ₁₀ supplementation** with statin therapy, though evidence is mixed
### 8.5 CoQ₁₀ as an Antioxidant
- Ubiquinol (QH₂) is a potent **lipid-soluble antioxidant**
- Protects membrane lipids from peroxidation
- Regenerates **vitamin E** (α-tocopherol) from its radical form
---
## 9. COMPLEX III — UBIQUINOL:CYTOCHROME c OXIDOREDUCTASE (EC 1.10.2.2)
Also called: **Cytochrome bc₁ complex**
### 9.1 Structure
- **~240 kDa** as a functional **homodimer** (each monomer ~11 subunits in mammals)
- **11 subunits** per monomer: **1 mtDNA-encoded** (cytochrome b) + **10 nuclear-encoded**
- Key catalytic subunits:
1. **Cytochrome b**: contains **two heme b groups** — heme bL (low potential, +0.07 V) and heme bH (high potential, +0.03 V → but higher in the context of electron flow)
2. **Rieske iron-sulfur protein**: contains [2Fe-2S] cluster — unique because one Fe is coordinated by **2 histidines** instead of cysteines (higher reduction potential: +0.28 V)
3. **Cytochrome c₁**: contains heme c₁
### 9.2 The Q Cycle (Mitchell's Q Cycle)
The Q cycle is an elegant mechanism that explains how Complex III:
- Transfers electrons from a **2-electron carrier** (QH₂) to a **1-electron carrier** (cytochrome c)
- Pumps **protons** across the membrane
- Effectively doubles the number of protons translocated per QH₂
**Two binding sites for CoQ:**
- **Qp site** (also called Qo site) — on the **P-side** (IMS side / positive side) — where QH₂ is **oxidized**
- **Qn site** (also called Qi site) — on the **N-side** (matrix side / negative side) — where Q is **reduced**
#### First Half of the Q Cycle:
1. **QH₂** binds at the **Qp site**
2. First electron → **Rieske [2Fe-2S]** → **Cytochrome c₁** → **Cytochrome c** (which departs as a reduced, mobile carrier)
3. 2 H⁺ are released into the **IMS** (from QH₂ oxidation)
4. The remaining electron goes to the **low-potential pathway**: QH• → **heme bL** → **heme bH** → reduces **Q** to **Q•⁻ (semiquinone)** at the **Qn site**
5. QH₂ at Qp is now fully oxidized → Q, which leaves
#### Second Half of the Q Cycle:
1. A **second QH₂** binds at the **Qp site**
2. Again: first electron → Rieske → cyt c₁ → **second cytochrome c** (reduced and departs)
3. 2 more H⁺ released into IMS
4. Second electron → heme bL → heme bH → reduces the **semiquinone (Q•⁻)** at Qn to **QH₂** (picking up **2 H⁺ from the matrix**)
5. This regenerated QH₂ can re-enter the cycle
#### Net Q Cycle (per pair of electrons reaching cytochrome c):
> **QH₂ + 2 cyt c (ox) + 2H⁺(matrix) → Q + 2 cyt c (red) + 4H⁺(IMS)**
**In one complete Q cycle** (processing 2 QH₂):
- 2 QH₂ oxidized at Qp
- 1 Q reduced to QH₂ at Qn (net consumption: 1 QH₂)
- **4 H⁺ released to IMS** (2 from each QH₂ oxidation at Qp)
- **2 H⁺ consumed from matrix** (for QH₂ formation at Qn)
- **Net proton translocation: ~4 H⁺ per 2 electrons** reaching O₂ via cyt c (but conventionally counted as **4 H⁺ per pair of electrons from QH₂ entering Complex III**, which equals 2 H⁺ per electron delivered to cyt c)
**Revised consensus: 4 H⁺ translocated per 2 electrons through Complex III** (per QH₂ oxidized net).
### 9.3 Inhibitors of Complex III
| Inhibitor | Site of Action | Mechanism |
|-----------|---------------|-----------|
| **Antimycin A** | **Qn (Qi) site** | Blocks electron transfer from heme bH to Q at the Qn site; prevents the second half of Q cycle |
| **Myxothiazol** | **Qp (Qo) site** | Blocks QH₂ oxidation at the Qp site |
| **Stigmatellin** | **Qp (Qo) site** | Blocks electron transfer to Rieske center |
> **🔴 CLINICAL: Antimycin A and ROS**
> - When Antimycin A blocks the Qn site, the **semiquinone radical (Q•⁻)** at the Qp site accumulates
> - This semiquinone can donate its electron directly to O₂ → forming **superoxide (O₂•⁻)**
> - Complex III (Qp site) is a major site of **mitochondrial ROS production**
> - Relevant to aging, ischemia-reperfusion injury, and neurodegenerative diseases
> **🔴 CLINICAL: Complex III Deficiency**
> - Rare; can be caused by mutations in:
> - **Cytochrome b** (mtDNA — MT-CYB)
> - **BCS1L** (assembly factor for Rieske protein)
> - **BCS1L mutations** cause:
> - **GRACILE syndrome** (Growth Retardation, Aminoaciduria, Cholestasis, Iron overload, Lactic acidosis, Early death) — Finnish heritage
> - **Björnstad syndrome** (sensorineural deafness + pili torti — twisted hair)
> - Isolated Complex III deficiency with encephalopathy
> - **MT-CYB mutations**: exercise intolerance, myopathy, cardiomyopathy
---
## 10. CYTOCHROME c
### 10.1 Structure and Function
- Small (~12.4 kDa), highly conserved, water-soluble protein
- Contains **one heme c** (covalently attached via thioether bonds to two cysteine residues — -CXXCH- motif)
- Located in the **intermembrane space**
- **Peripheral membrane protein** — loosely associated with the outer surface of the IMM (bound by electrostatic interactions with cardiolipin)
- Transfers **one electron** from Complex III (cyt c₁) → Complex IV (CuA)
### 10.2 Role in Apoptosis
> **🔴 CLINICAL: Cytochrome c and Apoptosis (Intrinsic Pathway)**
> - During **intrinsic (mitochondrial) apoptosis**:
> 1. Pro-apoptotic stimuli (DNA damage, oxidative stress, growth factor withdrawal) activate BH3-only proteins (BID, BIM, BAD, etc.)
> 2. These activate **BAX** and **BAK** (pro-apoptotic BCL-2 family members)
> 3. BAX/BAK oligomerize and form pores in the **outer mitochondrial membrane** → **MOMP (Mitochondrial Outer Membrane Permeabilization)**
> 4. **Cytochrome c is released** from the IMS into the cytoplasm
> 5. Cytochrome c binds **APAF-1** (Apoptotic Protease-Activating Factor 1) → forms the **apoptosome** (wheel-of-death)
> 6. The apoptosome activates **Caspase-9** (initiator caspase)
> 7. Caspase-9 activates **Caspase-3 and Caspase-7** (executioner caspases) → cell death
> - **Anti-apoptotic proteins** (BCL-2, BCL-XL, MCL-1) prevent BAX/BAK activation → prevent cytochrome c release
> - **Cancer cells** often overexpress BCL-2 → resistance to apoptosis
> - **Venetoclax**: BCL-2 inhibitor used in CLL and AML — restores apoptosis by allowing cytochrome c release
> - Other proteins released from mitochondria during apoptosis: **Smac/DIABLO** (inhibits IAPs), **AIF** (apoptosis-inducing factor — caspase-independent death), **endonuclease G**, **Omi/HtrA2**
### 10.3 Cytochrome c in Evolution
- One of the most conserved proteins in evolution
- Comparing cytochrome c amino acid sequences across species has been used to construct **phylogenetic trees**
- Human and chimpanzee cytochrome c are **identical** (100% homology)
- Human and yeast share ~60% identity
---
## 11. COMPLEX IV — CYTOCHROME c OXIDASE (EC 1.9.3.1)
### 11.1 Structure
- **~200 kDa** as a functional **dimer** (each monomer: 13 subunits in mammals)
- **3 mtDNA-encoded** subunits: **COX I, COX II, COX III** (catalytic core)
- **10 nuclear-encoded** subunits (regulatory/structural)
- Contains **4 redox-active metal centers**:
- **CuA center** (in COX II): dinuclear copper; first to accept electron from cytochrome c
- **Heme a** (in COX I): transfers electron to the binuclear center
- **Heme a₃** (in COX I): part of the binuclear center
- **CuB** (in COX I): part of the binuclear center; paired with heme a₃
- Also contains **Zn** and **Mg** ions (structural roles)
### 11.2 Mechanism
1. **Cytochrome c** (reduced) binds to the IMS face of Complex IV and donates **1 electron** to **CuA**
2. CuA → **heme a** → **binuclear center (heme a₃–CuB)**
3. At the binuclear center, **O₂ binds** (between Fe of heme a₃ and CuB)
4. **Four electrons** are required to fully reduce O₂:
> **O₂ + 4 e⁻ + 4 H⁺ (matrix) → 2 H₂O**
5. This occurs in a carefully controlled sequence to avoid release of partially reduced oxygen species (superoxide, peroxide)
### 11.3 Proton Pumping
Complex IV pumps **protons** across the IMM through **two proton channels** (D-channel and K-channel):
- **4 "chemical" protons**: consumed in the matrix to make H₂O (scalar protons)
- **4 "pumped" protons**: translocated from matrix to IMS (vectorial protons)
- Total: **8 H⁺ removed from the matrix** per O₂ (4 used for H₂O + 4 pumped)
- But per 2 electrons (from 1 NADH): **2 H⁺ pumped** + 2 H⁺ consumed for 1 H₂O
### 11.4 Overall Reaction
> **4 cyt c (red) + O₂ + 8H⁺(matrix) → 4 cyt c (ox) + 2H₂O + 4H⁺(IMS)**
(4 H⁺ consumed to make H₂O, 4 H⁺ pumped — from the matrix perspective, 8 H⁺ disappear)
**Per pair of electrons (per NADH):**
> 2 cyt c (red) + ½O₂ + 4H⁺(matrix) → 2 cyt c (ox) + H₂O + 2H⁺(IMS)
### 11.5 Inhibitors of Complex IV
| Inhibitor | Mechanism |
|-----------|-----------|
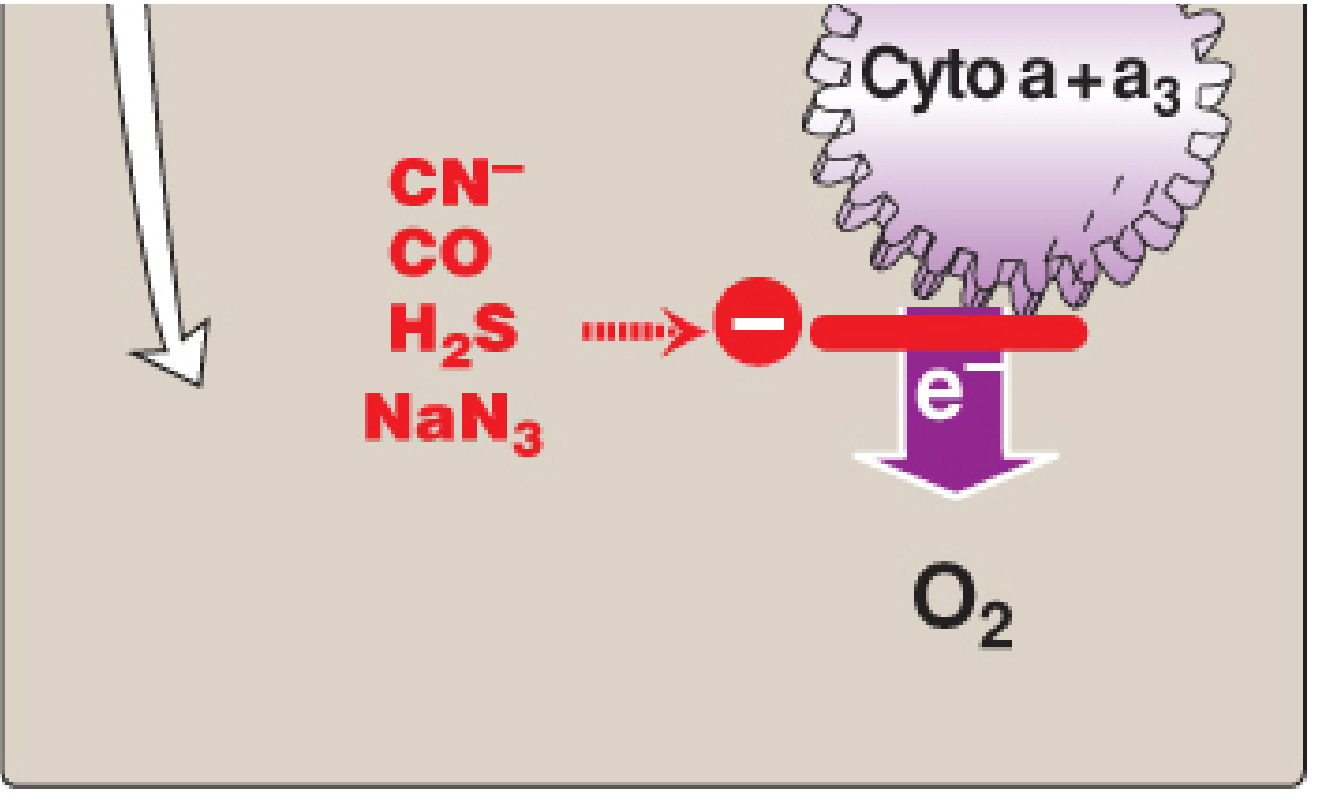
| **Cyanide (CN⁻)** | Binds to **Fe³⁺ of heme a₃** → blocks O₂ binding |
| **Carbon monoxide (CO)** | Binds to **Fe²⁺ of heme a₃** → blocks O₂ binding |
| **Hydrogen sulfide (H₂S)** | Binds to heme a₃ → blocks O₂ binding |
| **Azide (N₃⁻)** | Binds to Fe³⁺ of heme a₃ |
| **Nitric oxide (NO)** | Reversible inhibitor; binds to heme a₃ and CuB |
| **Phosphine (PH₃)** | Insecticide; inhibits Complex IV |
| **Formate** (from methanol metabolism) | Inhibits Complex IV |
> **🔴 CLINICAL: Cyanide Poisoning**
> - Sources: industrial chemicals (electroplating, mining), **smoke inhalation** (burning of plastics, wool, silk releases HCN), **cyanogenic glycosides** (bitter almonds, cassava, apple seeds, cherry pits — contain amygdalin), sodium nitroprusside (releases CN⁻ during prolonged infusion)
> - Mechanism: CN⁻ binds Fe³⁺ of cytochrome a₃ → **complete inhibition of Complex IV** → cells cannot use O₂ → **histotoxic/cytotoxic hypoxia**
> - Classic features:
> - **Bright cherry-red skin** (venous blood remains oxygenated because cells can't extract O₂)
> - **"Bitter almond" breath odor** (only 40% of people can detect this — genetically determined)
> - High **venous PO₂** (venous blood is almost as oxygenated as arterial → narrow **A-V O₂ difference**)
> - **Lactic acidosis** (severe, from anaerobic glycolysis)
> - Rapidly: headache, confusion, seizures, coma, death
> - PaO₂ and O₂ saturation may be **normal** (pulse oximetry and ABG can be misleadingly normal)
> - Lab: **elevated lactate**, **elevated venous O₂ saturation**, cyanide levels >0.5 mg/L are toxic, >3 mg/L lethal
> - Treatment:
> - **100% oxygen**
> - **Hydroxocobalamin (Cyanokit®)**: binds CN⁻ → cyanocobalamin (vitamin B₁₂) → renally excreted. **Preferred antidote**, especially in smoke inhalation (safe in combined CO/CN poisoning)
> - **Sodium thiosulfate**: provides sulfur donor for **rhodanese** (thiosulfate sulfurtransferase) → converts CN⁻ → **thiocyanate (SCN⁻)** → renally excreted. Slow onset.
> - **Sodium nitrite** (or amyl nitrite): induces **methemoglobinemia** → methemoglobin (Fe³⁺) binds CN⁻ → cyanomethemoglobin → draws CN away from cytochrome oxidase. **Caution in smoke inhalation** (may already have carboxyhemoglobin → further reduces O₂ carrying capacity)
> - **Dicobalt edetate (Kelocyanor)**: used in UK — cobalt directly chelates CN⁻
> - Traditional "Cyanide Antidote Kit": amyl nitrite + sodium nitrite + sodium thiosulfate
> **🔴 CLINICAL: Carbon Monoxide (CO) Poisoning**
> - CO binds to:
> 1. **Hemoglobin** (240× greater affinity than O₂) → **carboxyhemoglobin (COHb)** → leftward shift of O₂-Hb dissociation curve → impaired O₂ delivery
> 2. **Cytochrome c oxidase (Complex IV)** → Fe²⁺ of heme a₃ → histotoxic hypoxia
> 3. **Myoglobin** → impaired muscle O₂ utilization
> - Sources: incomplete combustion, house fires, car exhaust, charcoal grills, furnaces
> - Findings:
> - **Cherry-red skin** (due to COHb, but this is a LATE finding — often patients appear pale/cyanotic)
> - Headache (most common early symptom), nausea, confusion, syncope, seizures, coma
> - **PaO₂ is NORMAL** (dissolved O₂ is unaffected)
> - **O₂ saturation by pulse oximetry is FALSELY NORMAL** (pulse ox can't distinguish COHb from OxyHb)
> - **CO-oximetry** is the diagnostic test → directly measures COHb%
> - Normal COHb <3% (non-smokers), <10% (smokers); symptomatic >15-20%; lethal >50-60%
> - Treatment:
> - **100% O₂ via non-rebreather mask** (reduces COHb half-life from 5 hours → 90 minutes)
> - **Hyperbaric oxygen (HBO₂)**: reduces half-life to ~30 minutes; indicated for COHb >25%, loss of consciousness, neurological symptoms, cardiac ischemia, pregnancy
> - Delayed neuropsychiatric sequelae (DNS): cognitive impairment, personality changes weeks later → may be prevented by HBO₂
> **🔴 CLINICAL: Hydrogen Sulfide (H₂S) Poisoning**
> - "Knockdown gas" — toxic in sewer gas, volcanic emissions, petroleum industry
> - Mechanism: like cyanide, inhibits Complex IV
> - Can cause sudden collapse ("sewer gas asphyxia")
> - Rotten egg smell at low concentrations; at high concentrations → **olfactory nerve paralysis** (can no longer smell it — extremely dangerous)
> - Treatment: similar to cyanide → nitrites (to form sulfmethemoglobin), 100% O₂, supportive
> **🔴 CLINICAL: Nitric Oxide (NO) and Complex IV**
> - NO is a physiological signaling molecule (vasodilator, neurotransmitter)
> - At physiological concentrations: **reversibly inhibits Complex IV** → may regulate mitochondrial respiration and O₂ utilization
> - In excess (sepsis, inflammation → iNOS activation): excessive NO → mitochondrial dysfunction → contributes to **septic shock** pathophysiology
> - NO competes with O₂ at the binuclear center → when O₂ is low, NO inhibition is enhanced → may help redistribute O₂ in tissues (metabolic signaling)
> **🔴 CLINICAL: Methanol and Formate Toxicity**
> - Methanol → formaldehyde → **formic acid/formate** (via alcohol dehydrogenase and aldehyde dehydrogenase)
> - Formate inhibits **cytochrome c oxidase (Complex IV)**
> - Causes: **metabolic acidosis (high anion gap)**, **blindness** (retinal/optic nerve toxicity — retinal ganglion cells are especially vulnerable)
> - Treatment: **fomepizole** (4-methylpyrazole — ADH inhibitor) or ethanol (competitive substrate for ADH), dialysis, folate (enhances formate metabolism to CO₂ and H₂O)
---
## 12. COMPLEX V — ATP SYNTHASE (F₁F₀-ATP SYNTHASE) (EC 7.1.2.2)
### 12.1 Overview
- Also called: **F₁F₀-ATPase**, **Complex V**
- Not a component of the electron transport chain per se, but is the **site of oxidative phosphorylation**
- Uses the **proton motive force** (PMF) generated by Complexes I, III, IV to synthesize ATP from ADP + Pi
- **~600 kDa**
- **16 subunits** in mammals (2 mtDNA-encoded: ATPase 6 = subunit a, ATPase 8 = subunit A6L)
### 12.2 Structure
ATP synthase has two main components:
#### F₁ Component (Soluble, Matrix side — "Factor 1")
- **Knob-like structure** projecting into the matrix
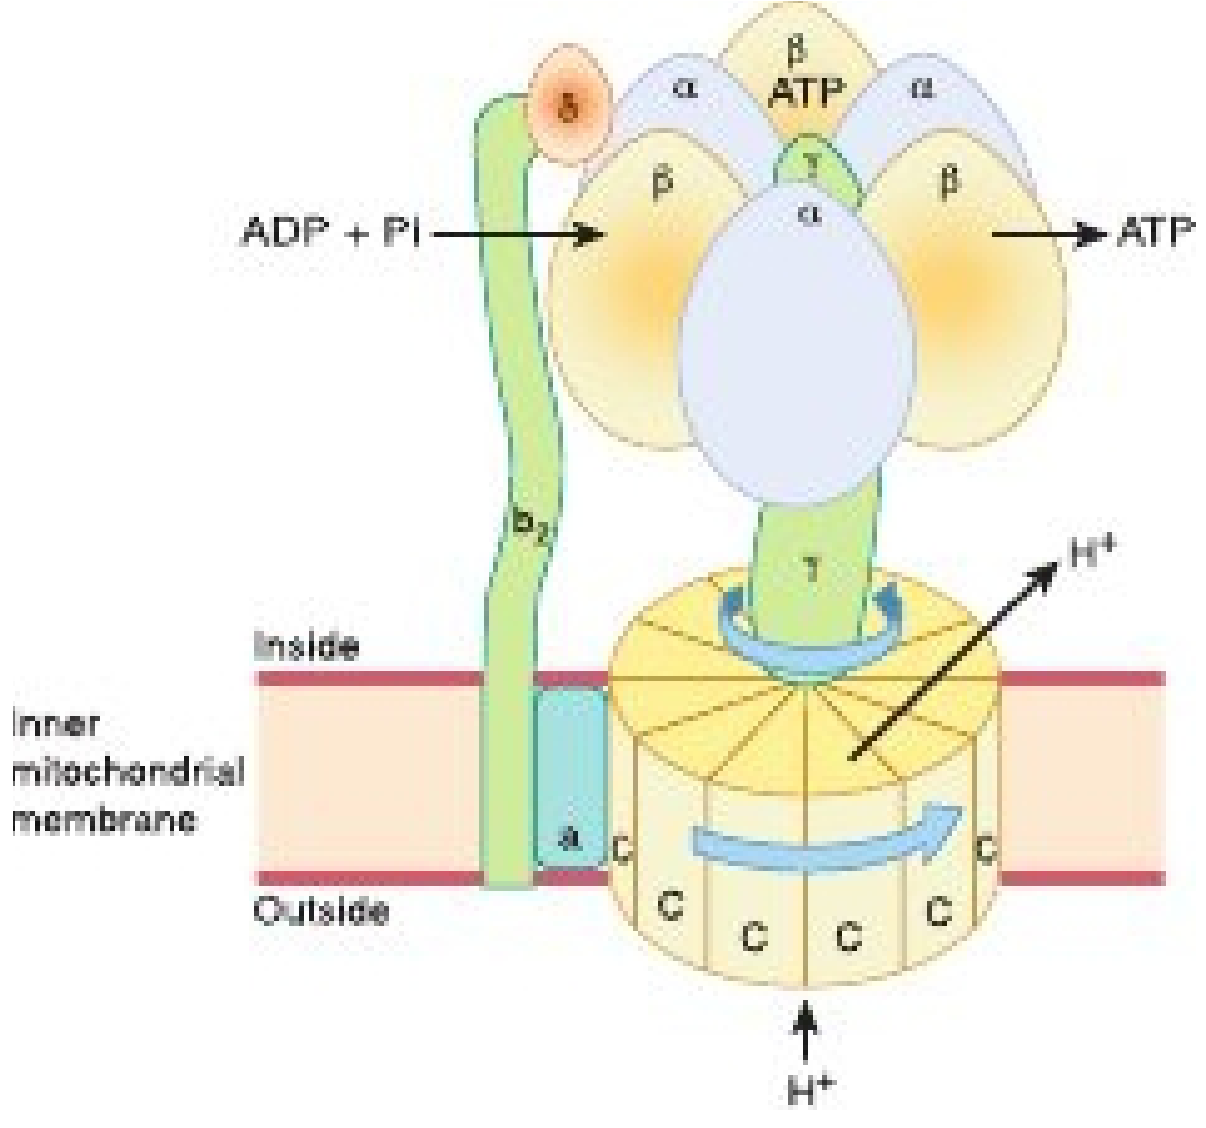
- Composition: **α₃β₃γδε**
- **3 α subunits** and **3 β subunits**: arranged alternately like segments of an orange
- Each **β subunit** contains a **catalytic site** for ATP synthesis
- The **3 β subunits** exist in 3 different conformations (see binding change mechanism)
- **γ subunit**: central stalk/axle; rotates within the α₃β₃ ring; asymmetric → drives conformational changes in β subunits
- **ε subunit**: attached to γ; part of the rotor
- **δ subunit**: part of the peripheral stalk (in bacterial nomenclature; in mitochondria, the OSCP — Oligomycin Sensitivity Conferring Protein)
#### F₀ Component (Membrane-embedded — "Factor 0" — "oligomycin-sensitive factor")
- **Proton channel**
- Composition (in mammals):
- **c-ring**: ring of **8-15 c subunits** (8 in mammals, 10 in yeast); each c subunit has a proton-binding carboxylate (aspartate or glutamate)
- **a subunit** (subunit 6): has two half-channels for proton translocation; stationary
- **b subunit**: part of the peripheral/lateral stalk connecting F₀ to F₁ (stator)
- **Additional subunits**: d, F6, A6L, e, f, g (structural and regulatory)
#### Peripheral Stalk (Stator)
- Connects F₁ to F₀ without rotating
- Composed of: **b, d, F6, OSCP** subunits
- Prevents co-rotation of α₃β₃ with γ → allows the conformational changes in β subunits
### 12.3 The Rotary Catalysis — Boyer's Binding Change Mechanism
(Paul Boyer — Nobel Prize 1997)
The γ subunit acts as a **rotating cam shaft**. As protons flow through F₀, the c-ring rotates, and the attached γ subunit rotates within the α₃β₃ hexamer, sequentially changing the conformation of each β subunit:
#### Three Conformations of β Subunits:
1. **O (Open)**: low affinity for substrates; releases ATP
2. **L (Loose)**: binds ADP + Pi loosely
3. **T (Tight)**: catalyzes ATP formation; binds ATP very tightly
#### Catalytic Cycle (per 120° rotation of γ):
- **Step 1**: ADP + Pi bind to the **L-site** (Loose)
- **Step 2**: γ rotates 120° → L-site converts to **T-site** (Tight) → ATP is synthesized (essentially a spontaneous condensation reaction when substrates are properly positioned)
- **Step 3**: The previous T-site converts to **O-site** (Open) → ATP is released
- **Step 4**: The previous O-site converts to L-site → ready for new ADP + Pi
**One full rotation (360°)** of γ = **3 ATP molecules** synthesized
### 12.4 Proton Translocation Through F₀
1. H⁺ from IMS enters the **half-channel** in the **a subunit** (inlet half-channel)
2. H⁺ binds to the **carboxylate** (Asp/Glu) on a **c subunit**
3. This neutralization allows the c subunit to move into the **hydrophobic lipid bilayer** environment
4. As the c-ring rotates (driven by the proton gradient), each c subunit eventually reaches the **outlet half-channel** on the matrix side
5. The H⁺ is released into the matrix
**Number of protons per ATP:**
- Depends on the number of **c subunits** in the ring
- In mammals (8 c subunits): 360°/3 = 120° per ATP; 8 H⁺ per 360° → **8/3 ≈ 2.67 H⁺ per ATP**
- Plus **1 H⁺** for the phosphate carrier (Pi/H⁺ symport) → **~3.67 H⁺ per ATP**
- Often approximated as **~4 H⁺ per ATP** (including phosphate transport)
### 12.5 ATP/ADP Translocase (Adenine Nucleotide Translocator — ANT)
- Located in IMM
- **Antiporter**: exchanges **ATP⁴⁻ (out to IMS)** for **ADP³⁻ (in to matrix)**
- This exchange is **electrogenic** — net export of 1 negative charge → driven by the membrane potential (Δψ)
- Consumes energy from the proton gradient
- Accounts for ~25% of the energy of the PMF
**Inhibitors of ANT:**
| Inhibitor | Effect |
|-----------|--------|
| **Atractyloside** (from thistle plant) | Binds to cytoplasmic face of ANT → blocks ADP import |
| **Bongkrekic acid** (from contaminated coconut/corn fermentation — Burkholderia gladioli) | Binds to matrix face → locks ANT in "m-state" |
> **🔴 CLINICAL: Bongkrekic Acid Poisoning**
> - From fermented coconut or corn products contaminated with **Burkholderia gladioli pathovar cocovenenans**
> - Outbreaks in Southeast Asia, China
> - Inhibits ANT → ATP depletion → multiorgan failure
> - Very high mortality rate (40-100%)
### 12.6 Phosphate Carrier (PiC)
- **Symporter**: transports **Pi (H₂PO₄⁻)** with **H⁺** into the matrix
- Driven by the ΔpH component of the PMF
- Total cost of ATP synthesis and transport:
- 3-4 H⁺ through ATP synthase
- 1 H⁺ for phosphate import
- Electrical potential used by ANT
### 12.7 Inhibitors of ATP Synthase (Complex V)
| Inhibitor | Mechanism |
|-----------|-----------|
| **Oligomycin** | Blocks the **proton channel** in F₀ (binds between a and c subunits) → prevents H⁺ flow → stops both ATP synthesis AND electron transport (because the PMF builds up and back-pressure stops proton pumping by Complexes I, III, IV) |
| **DCCD (Dicyclohexylcarbodiimide)** | Reacts with the carboxylate (Asp/Glu) on **c subunits** → blocks proton binding |
| **Aurovertin** | Binds to **β subunit** of F₁ → blocks catalytic activity |
| **Efrapeptin** | Blocks the F₁ catalytic site |
> **🔴 CLINICAL: Oligomycin Effect**
> - When oligomycin blocks ATP synthase → protons accumulate in IMS → PMF increases → proton pumping by Complexes I, III, IV stops → electron transport stops → O₂ consumption stops
> - This is called **"respiratory control"** — the tight coupling between electron transport and ATP synthesis
> - Shows that under normal conditions, ETC activity is directly coupled to ATP synthesis
> **🔴 CLINICAL: ATP Synthase Deficiency**
> - Mutations in **MT-ATP6** (subunit a):
> - **NARP syndrome** (Neuropathy, Ataxia, Retinitis Pigmentosa): when mutant mtDNA load is 70-90%
> - **Maternally Inherited Leigh Syndrome (MILS)**: when mutant load >90%
> - Most common mutation: **m.8993T>G** or **m.8993T>C** (both in MT-ATP6)
> - **MT-ATP8** mutations: rare; cardiomyopathy
> - Nuclear-encoded assembly factors: **TMEM70** mutations — most common cause of nuclear-encoded ATP synthase deficiency; 3-methylglutaconic aciduria, cardiomyopathy, lactic acidosis
---
## 13. THE PROTON MOTIVE FORCE (PMF)
### 13.1 Definition
The energy stored in the electrochemical proton gradient across the IMM.
**Two components:**
$$\Delta p = \Delta \psi - \frac{2.3RT}{F} \Delta pH$$
Where:
- **Δψ** = membrane potential (voltage gradient) — inside (matrix) is **negative**; ~150-180 mV in mammals
- **ΔpH** = pH gradient — matrix is more **alkaline** (~0.5-1.0 pH units)
- Under physiological conditions: ~80% from Δψ, ~20% from ΔpH
### 13.2 Total Protons Pumped per NADH
| Complex | H⁺ pumped (per 2 electrons from NADH) |
|---------|---------------------------------------|
| Complex I | 4 H⁺ |
| Complex III | 4 H⁺ (via Q cycle) |
| Complex IV | 2 H⁺ (pumped) + 2 H⁺ (consumed for H₂O) |
| **Total vectorial H⁺** | **10 H⁺** per NADH |
For FADH₂ (enters at CoQ, bypasses Complex I):
| Complex | H⁺ pumped (per 2 electrons from FADH₂) |
|---------|----------------------------------------|
| Complex III | 4 H⁺ |
| Complex IV | 2 H⁺ (pumped) + 2 H⁺ (consumed) |
| **Total vectorial H⁺** | **6 H⁺** per FADH₂ |
---
## 14. CHEMIOSMOTIC HYPOTHESIS
### Peter Mitchell (1961) — Nobel Prize in Chemistry (1978)
### 14.1 Key Postulates:
1. The ETC complexes are **vectorially arranged** in the IMM, pumping protons from matrix → IMS
2. The IMM is **impermeable to protons** (and most ions) — the proton gradient is maintained
3. The electrochemical proton gradient (**PMF**) stores energy
4. Protons flow back into the matrix **only through ATP synthase** → this drives ATP synthesis
5. The processes of electron transport and ATP synthesis are **coupled** through the PMF (not by chemical intermediates)
### 14.2 Evidence Supporting the Hypothesis:
1. **Intact IMM is required** for oxidative phosphorylation (disrupted membranes → no ATP synthesis)
2. **Uncouplers** (which dissipate the proton gradient) abolish ATP synthesis without stopping electron transport
3. Artificially created pH gradients across vesicles can drive ATP synthesis
4. ATP synthase reconstituted in artificial liposomes produces ATP when a pH gradient is applied
5. Ionophores that collapse the gradient inhibit ATP synthesis
---
## 15. P/O RATIOS AND ATP YIELD
### 15.1 Definition
**P/O ratio** = moles of ATP produced per atom of oxygen consumed (per pair of electrons reaching O₂)
### 15.2 Revised Values (Current Consensus)
Based on:
- ~4 H⁺ needed per ATP (including transport costs)
- 10 H⁺ pumped per NADH; 6 H⁺ pumped per FADH₂
| Substrate | H⁺ pumped | ATP per molecule (H⁺/~4) | P/O ratio |
|-----------|-----------|---------------------------|-----------|
| NADH | 10 | **~2.5** (10/4) | 2.5 |
| FADH₂ | 6 | **~1.5** (6/4) | 1.5 |
### 15.3 Total ATP Yield from Complete Oxidation of Glucose
| Reaction | NADH | FADH₂ | GTP/ATP | ATP equivalent |
|----------|------|-------|---------|----------------|
| Glycolysis: Glucose → 2 Pyruvate | 2 | — | 2 ATP (substrate level) | 2 |
| 2 Pyruvate → 2 Acetyl-CoA (PDH) | 2 | — | — | — |
| 2 turns TCA cycle | 6 | 2 | 2 GTP | 2 |
| **Totals** | **10 NADH** | **2 FADH₂** | **4 ATP/GTP** | |
**Calculation:**
- 10 NADH × 2.5 = 25 ATP
- 2 FADH₂ × 1.5 = 3 ATP
- 4 ATP/GTP (substrate level)
- **But**: glycolytic NADH (2) is in the cytoplasm and must be shuttled into mitochondria
**Shuttle systems affect the yield:**
- **Malate-Aspartate Shuttle**: delivers electrons as NADH → 2.5 ATP each → 5 ATP
- **Glycerol-3-Phosphate Shuttle**: delivers electrons as FADH₂ → 1.5 ATP each → 3 ATP
| Using Malate-Aspartate Shuttle | Using Glycerol-3-Phosphate Shuttle |
|-------------------------------|--------------------------------------|
| 25 + 3 + 4 + (2 × 2.5) = **30-32 ATP** | 25 + 3 + 4 + (2 × 1.5) = **30 ATP** |
**Most quoted: ~30-32 ATP per glucose**
(Older textbooks used 36-38 ATP based on P/O ratios of 3 and 2)
---
## 16. SHUTTLE SYSTEMS
The IMM is **impermeable to NADH**. Cytoplasmic NADH (from glycolysis) cannot directly enter mitochondria. Two shuttle systems transfer reducing equivalents:
### 16.1 Malate-Aspartate Shuttle
**Location**: primarily in **liver, heart, kidney**
**Mechanism**:
1. Cytoplasmic **oxaloacetate + NADH** → **malate + NAD⁺** (cytoplasmic malate dehydrogenase)
2. **Malate** crosses IMM via the **malate-α-ketoglutarate antiporter**
3. Matrix **malate** → **oxaloacetate + NADH** (mitochondrial malate dehydrogenase)
4. Matrix **oxaloacetate** cannot cross IMM → transaminated to **aspartate** (by aspartate aminotransferase, using glutamate → α-ketoglutarate)
5. **Aspartate** exits via the **glutamate-aspartate antiporter** (electrogenic — driven by Δψ)
6. Cytoplasmic aspartate → oxaloacetate (by cytoplasmic aspartate aminotransferase)
7. α-ketoglutarate returns to matrix via the malate-αKG antiporter
**Net result**: cytoplasmic NADH → mitochondrial NADH → **2.5 ATP** (most energetically efficient)
**Enzymes used**: malate dehydrogenase (both sides), aspartate aminotransferase (both sides)
### 16.2 Glycerol-3-Phosphate Shuttle
**Location**: primarily in **skeletal muscle, brain**
**Mechanism**:
1. Cytoplasmic **DHAP + NADH** → **glycerol-3-phosphate + NAD⁺** (cytoplasmic glycerol-3-phosphate dehydrogenase — NAD⁺-linked)
2. **Glycerol-3-phosphate** → **DHAP + FADH₂** (mitochondrial glycerol-3-phosphate dehydrogenase — FAD-linked, located on **outer surface of IMM**, has active site facing IMS)
3. FADH₂ directly reduces **CoQ** in the IMM
**Net result**: cytoplasmic NADH → mitochondrial FADH₂ → **1.5 ATP** (less efficient)
**Key difference**: this shuttle is **irreversible** (the mitochondrial enzyme is FAD-linked with a more positive E°') and **faster** than the malate-aspartate shuttle
> **🔴 CLINICAL: Malate-Aspartate Shuttle and Aralar1/AGC1 Deficiency**
> - **SLC25A12** mutations (encoding mitochondrial aspartate-glutamate carrier isoform 1 — AGC1/Aralar1)
> - Causes **global cerebral hypomyelination**, developmental delay, seizures
> - Impaired transfer of reducing equivalents into brain mitochondria
---
## 17. INHIBITORS OF THE ETC — COMPREHENSIVE SUMMARY
### 17.1 Classification by Site
| Complex | Inhibitors |
|---------|-----------|
| **Complex I** | Rotenone, Piericidin A, Barbiturates (amytal/amobarbital), MPP⁺ |
| **Complex II** | Malonate, Carboxin, TTFA, 3-Nitropropionic acid |
| **Complex III** | Antimycin A (Qi/Qn site), Myxothiazol (Qo/Qp site), Stigmatellin (Qo/Qp site) |
| **Complex IV** | Cyanide (CN⁻), Carbon monoxide (CO), Hydrogen sulfide (H₂S), Azide (N₃⁻), Nitric oxide (NO), Phosphine, Formate |
| **Complex V** | Oligomycin, DCCD, Aurovertin, Efrapeptin |
| **ANT** | Atractyloside, Bongkrekic acid |
### 17.2 Effects of ETC Inhibitors
When an inhibitor blocks at any site:
1. **Upstream** of the block: carriers become **more reduced** (can't pass electrons forward)
2. **Downstream** of the block: carriers become **more oxidized** (no electrons coming in)
3. **O₂ consumption decreases** (except with uncouplers)
4. **ATP synthesis decreases**
5. **NADH/NAD⁺ ratio increases** → inhibits TCA cycle and other NAD⁺-dependent reactions
6. **Lactate production increases** → **lactic acidosis**
---
## 18. UNCOUPLERS OF OXIDATIVE PHOSPHORYLATION
### 18.1 Definition
Uncouplers **dissipate the proton gradient** without generating ATP. They allow electron transport to continue (actually at an **accelerated rate**) but without ATP production. The energy is released as **heat**.
### 18.2 Mechanism
Uncouplers are **lipophilic weak acids** that:
1. Pick up H⁺ on the IMS side (protonated form is lipid-soluble)
2. Cross the IMM in their protonated form
3. Release H⁺ on the matrix side
4. Return across the membrane in their anionic form
5. This short-circuits the proton gradient → collapses Δp
### 18.3 Effects of Uncoupling
| Parameter | Effect |
|-----------|--------|
| Electron transport | ↑ (accelerated — no back-pressure from PMF) |
| O₂ consumption | ↑↑ |
| ATP synthesis | ↓↓ (abolished) |
| NADH/NAD⁺ ratio | ↓ (more NAD⁺ generated — TCA cycle accelerated) |
| Heat production | ↑↑ (**thermogenesis**) |
| Proton gradient | ↓↓ (dissipated) |
| Fuel oxidation | ↑↑ |
### 18.4 Examples of Uncouplers
| Uncoupler | Notes |
|-----------|-------|
| **2,4-dinitrophenol (DNP)** | Classical uncoupler; used as a weight-loss drug in 1930s (banned due to toxicity) |
| **FCCP (carbonyl cyanide-p-trifluoromethoxyphenylhydrazone)** | Research tool |
| **CCCP (carbonyl cyanide m-chlorophenylhydrazone)** | Research tool |
| **Thermogenin (UCP1)** | Natural uncoupling protein in brown adipose tissue |
| **Valinomycin** | K⁺ ionophore; dissipates Δψ component |
| **Nigericin** | K⁺/H⁺ antiporter ionophore; dissipates ΔpH |
| **Salicylates** (high dose aspirin) | Weak uncoupling activity |
| **Bilirubin** (high levels) | Mild uncoupler |
| **Calcium ions** (high levels) | Uncouple via mitochondrial permeability transition pore (mPTP) |
| **Long-chain fatty acids** | Can act as mild uncouplers |
> **🔴 CLINICAL: 2,4-Dinitrophenol (DNP) Toxicity**
> - Used in the 1930s as a **weight-loss agent** due to uncoupling → increased metabolic rate → fat burning
> - Banned by FDA in 1938 due to severe side effects
> - Still available illegally online → causes deaths in body-builders/dieters
> - Symptoms: **profuse sweating, tachycardia, tachypnea, hyperthermia** (potentially fatal **malignant hyperthermia-like syndrome**)
> - Cataracts (with chronic use)
> - **No specific antidote** — treatment is supportive: cooling, dantrolene may help
> - Narrow therapeutic index → small dose increase can be lethal
> **🔴 CLINICAL: Aspirin (Salicylate) Overdose**
> - High-dose salicylates are:
> 1. **Uncouplers of oxidative phosphorylation** (weak acid, lipid-soluble)
> 2. Direct stimulants of the respiratory center (medullary)
> - Clinical toxicity:
> - **Respiratory alkalosis** (early — direct stimulation of respiratory center)
> - Followed by **metabolic acidosis** (high anion gap — from uncoupling → lactate, ketoacids + salicylate itself)
> - **Mixed respiratory alkalosis and metabolic acidosis** is characteristic
> - Hyperthermia, tinnitus, diaphoresis, nausea/vomiting
> - Severe: pulmonary edema, cerebral edema, seizures, death
> - Treatment: sodium bicarbonate (alkalinize urine and blood → traps salicylate in ionized form in urine), hemodialysis for severe cases, cooling
### 18.5 Thermogenin (UCP1) and Brown Adipose Tissue (BAT)
> **🔴 CLINICAL: Non-Shivering Thermogenesis**
> - **Brown adipose tissue (BAT)** contains abundant mitochondria (brown color from cytochromes)
> - Contains **UCP1 (Uncoupling Protein 1 / Thermogenin)** — a natural proton channel in the IMM
> - UCP1 allows H⁺ to re-enter the matrix without passing through ATP synthase → energy released as **HEAT**
> - Important in:
> - **Neonates** (who cannot shiver) — major source of heat production
> - **Hibernating animals**
> - Adults (recently discovered to have metabolically active BAT, especially in supraclavicular, paravertebral, perirenal regions)
> - **Regulation of UCP1**:
> - Activated by: **free fatty acids**, **norepinephrine** (via β₃-adrenergic receptors → cAMP → PKA → hormone-sensitive lipase → FFA release → FFA activates UCP1)
> - Inhibited by: **purine nucleotides (GDP, GTP, ADP, ATP)** — bind and block the channel
> - **Cold exposure** → sympathetic nervous system → norepinephrine → β₃ receptors on BAT → thermogenesis
> - **Thyroid hormones** (T₃) upregulate UCP1 expression → explains heat intolerance in hyperthyroidism
> - **BAT and obesity**: less active BAT is associated with obesity; activating BAT is a potential anti-obesity strategy
### 18.6 Other Uncoupling Proteins
| UCP | Location | Proposed Function |
|-----|----------|-------------------|
| UCP1 | Brown adipose tissue | Thermogenesis |
| UCP2 | Widely expressed (pancreatic β-cells, brain, etc.) | ROS regulation, β-cell function |
| UCP3 | Skeletal muscle, heart | Fatty acid metabolism, ROS protection |
| UCP4 | Brain | Neuroprotection |
| UCP5 (BMCP1) | Brain | Neuroprotection |
> **🔴 CLINICAL: UCP2 and Type 2 Diabetes**
> - UCP2 in **pancreatic β-cells** may reduce ATP production → decreased ATP/ADP ratio → impaired glucose-stimulated insulin secretion
> - UCP2 polymorphisms have been associated with **type 2 diabetes** risk and **obesity** (though controversial)
> - UCP2 knockout mice show improved insulin secretion
---
## 19. TIGHT COUPLING, RESPIRATORY CONTROL, AND REGULATION
### 19.1 Respiratory Control
- Under normal conditions, electron transport is **tightly coupled** to ATP synthesis
- The rate of O₂ consumption (electron transport) is determined by the **availability of ADP**
- When ADP levels are low (cell has enough ATP) → no ATP synthesis needed → proton gradient builds up → back-pressure inhibits ETC → O₂ consumption decreases
- When ADP levels are high (ATP is being used) → ADP enters mitochondria → ATP synthase becomes active → proton gradient is consumed → ETC speeds up → O₂ consumption increases
### 19.2 Respiratory States (Chance & Williams)
| State | Substrate | ADP | O₂ | Rate of respiration |
|-------|-----------|-----|-----|---------------------|
| **State 1** | Low | Low | Adequate | Slow |
| **State 2** | Added | Low | Adequate | Slow |
| **State 3** (active) | Adequate | Added (high) | Adequate | **Fast** |
| **State 4** (resting/controlled) | Adequate | Depleted (low) | Adequate | **Slow** |
| **State 5** | Adequate | Adequate | **Absent** | **Zero** |
- **Respiratory Control Ratio (RCR)** = State 3 rate / State 4 rate
- Normal RCR = 5-10 (indicates tight coupling)
- Low RCR suggests **uncoupling** or **damaged mitochondria**
### 19.3 Regulation of ETC
| Regulatory Factor | Effect |
|------------------|--------|
| **[ADP]** | Primary regulator — high ADP → increased respiration |
| **[ATP]** | High ATP → inhibits Complex IV (allosteric) |
| **[NADH]/[NAD⁺] ratio** | Controls substrate supply to Complex I |
| **[O₂]** | Must be adequate (Km of Complex IV for O₂ is very low ~1 μM — efficient even at low O₂) |
| **Thyroid hormones** | Increase mitochondrial biogenesis, ETC expression, UCP expression → increase BMR |
| **Ca²⁺** | Activates PDH, isocitrate DH, α-KG DH → increases NADH supply; also stimulates Complex IV and ATP synthase |
| **NO** | Reversible inhibition of Complex IV — helps regulate O₂ distribution |
| **Allosteric regulation** | ATP inhibits cytochrome c oxidase; ADP relieves inhibition |
---
## 20. REACTIVE OXYGEN SPECIES (ROS)
### 20.1 Overview
The ETC is the **major source of intracellular ROS production** (~1-2% of O₂ consumed under normal conditions leads to superoxide formation instead of water).
### 20.2 Sites of ROS Production
| Site | ROS produced | Mechanism |
|------|-------------|-----------|
| **Complex I** (FMN site and N1a cluster) | **O₂•⁻** (superoxide) | Especially during **reverse electron transfer (RET)** from succinate when Δp is high |
| **Complex III** (Qp/Qo site) | **O₂•⁻** | Semiquinone radical at Qp site donates electron to O₂ |
| **Complex II** (flavin site) | O₂•⁻ | Minor source |
| **Other sources** | | Monoamine oxidase (OMM), p66^shc, xanthine oxidase, NADPH oxidase |
### 20.3 Types of ROS
| Species | Formula | Formation |
|---------|---------|-----------|
| **Superoxide** | O₂•⁻ | 1-electron reduction of O₂ |
| **Hydrogen peroxide** | H₂O₂ | By SOD from superoxide; or 2-electron reduction of O₂ |
| **Hydroxyl radical** | •OH | **Fenton reaction**: Fe²⁺ + H₂O₂ → Fe³⁺ + •OH + OH⁻ |
| **Peroxynitrite** | ONOO⁻ | O₂•⁻ + NO• → ONOO⁻ |
### 20.4 Antioxidant Defense Systems
| Defense | Mechanism |
|---------|-----------|
| **SOD (Superoxide Dismutase)** | O₂•⁻ → H₂O₂ + O₂; **MnSOD (SOD2)** in matrix, **Cu/ZnSOD (SOD1)** in cytoplasm and IMS |
| **Catalase** | 2 H₂O₂ → 2 H₂O + O₂ (in peroxisomes) |
| **Glutathione peroxidase (GPx)** | H₂O₂ + 2 GSH → 2 H₂O + GSSG (requires **selenium**) |
| **Glutathione reductase** | GSSG + NADPH → 2 GSH (requires NADPH from pentose phosphate pathway) |
| **Thioredoxin / Peroxiredoxin system** | Reduces H₂O₂ and organic peroxides |
| **Vitamin E (α-tocopherol)** | Lipid-soluble radical scavenger; breaks chain of lipid peroxidation |
| **Vitamin C (ascorbate)** | Water-soluble radical scavenger; regenerates vitamin E |
| **CoQ₁₀ (ubiquinol)** | Lipid-soluble antioxidant in membranes |
### 20.5 ROS-Mediated Damage
| Target | Damage |
|--------|--------|
| **DNA** | Oxidation of bases (8-oxo-guanine), strand breaks → mutations, cancer |
| **Proteins** | Carbonylation, disulfide bond formation, loss of function |
| **Lipids** | Lipid peroxidation → malondialdehyde (MDA), 4-hydroxynonenal (4-HNE) → membrane damage |
| **mtDNA** | Especially vulnerable (no histones, near ROS source, limited repair) → vicious cycle of mitochondrial dysfunction |
> **🔴 CLINICAL: ROS and Disease**
> - **Aging**: "Mitochondrial free radical theory of aging" — cumulative mtDNA damage → declining ETC function → more ROS → more damage (vicious cycle)
> - **Ischemia-Reperfusion Injury**: during reperfusion, sudden O₂ reintroduction → massive ROS burst from dysfunctional ETC → cell death (relevant in **MI, stroke, organ transplantation**)
> - **Neurodegenerative diseases**: Parkinson's (Complex I deficiency, ROS in substantia nigra), Alzheimer's, ALS (SOD1 mutations in familial ALS)
> - **Cancer**: ROS cause DNA mutations → oncogenic transformation; paradoxically, many cancer cells have increased ROS which promotes proliferation and genomic instability
> - **Diabetes**: Hyperglycemia → increased ETC substrate → ROS overproduction → diabetic complications (retinopathy, nephropathy, neuropathy)
> **🔴 CLINICAL: Superoxide Dismutase and ALS**
> - ~20% of familial ALS (amyotrophic lateral sclerosis) cases involve mutations in **SOD1 (Cu/ZnSOD)**
> - Not a loss-of-function → **gain of toxic function** (misfolded SOD1 aggregates → motor neuron death)
> - Autosomal dominant
> **🔴 CLINICAL: Friedreich's Ataxia and Iron-Sulfur Clusters**
> - Autosomal recessive; most common hereditary ataxia
> - GAA trinucleotide repeat expansion in **FXN gene** (frataxin)
> - **Frataxin**: mitochondrial protein involved in **iron-sulfur cluster assembly** and iron homeostasis
> - Frataxin deficiency → impaired Fe-S cluster synthesis → **dysfunctional Complexes I, II, III** and **aconitase**
> - Mitochondrial iron accumulation → **Fenton reaction** → ROS damage
> - Clinical: progressive **gait and limb ataxia** (cerebellar and spinocerebellar), **dysarthria**, **hypertrophic cardiomyopathy** (major cause of death), diabetes mellitus, **absent deep tendon reflexes** (peripheral neuropathy), **pes cavus**, **scoliosis**, upgoing plantars (corticospinal tract involvement)
> - Treatment: **idebenone** (CoQ analog, antioxidant — limited benefit), **omaveloxolone** (Nrf2 activator — FDA approved 2023)
---
## 21. SUPERCOMPLEXES (RESPIRASOMES)
### 21.1 Concept
Traditionally, ETC components were thought to diffuse freely in the IMM ("fluid model" or "random collision model"). Current evidence supports the **"solid-state" model** or **"plasticity model"** — complexes form **supramolecular assemblies**:
| Supercomplex | Composition | Name |
|-------------|-------------|------|
| **I + III₂** | Complex I + dimer of Complex III | Supercomplex |
| **I + III₂ + IV₁₋₄** | Complex I + Complex III dimer + 1-4 copies of Complex IV | **Respirasome** |
| **III₂ + IV** | Complex III dimer + Complex IV | Supercomplex |
### 21.2 Functional Significance
- **Substrate channeling**: CoQ and cytochrome c may be channeled between complexes → faster electron transfer → reduced ROS production
- **Enhanced efficiency**: reduces the distance electrons must travel
- **Reduced ROS**: shorter transit time → less chance of electron leak to O₂
- **Stabilization**: individual complexes are stabilized by supercomplex formation (Complex I is unstable without Complex III)
- **Cardiolipin** is essential for supercomplex assembly
> **🔴 CLINICAL: Supercomplex Dysfunction**
> - **Heart failure**: decreased supercomplex assembly → increased ROS, decreased ATP production
> - **Barth syndrome**: cardiolipin deficiency → impaired supercomplex formation
> - **Aging**: decreased supercomplex levels in aged tissues
---
## 22. COMPREHENSIVE CLINICAL CORRELATIONS
### 22.1 Mitochondrial Diseases — Overview
**General Features** (Mnemonic: mitochondrial diseases preferentially affect tissues with high ATP demand):
- **Brain**: encephalopathy, seizures, stroke-like episodes, cognitive decline, ataxia
- **Muscle**: myopathy, exercise intolerance, ophthalmoplegia
- **Heart**: cardiomyopathy, conduction defects
- **Eye**: optic neuropathy, retinitis pigmentosa, ptosis
- **Ear**: sensorineural hearing loss
- **Endocrine**: diabetes mellitus, growth hormone deficiency
- **GI**: pseudo-obstruction
- **Kidney**: tubular dysfunction, Fanconi syndrome
- **Liver**: hepatopathy
**Diagnostic clues**:
- **Elevated serum lactate** (most consistent finding)
- **Elevated lactate:pyruvate ratio** (>20:1, indicating NADH/NAD⁺ imbalance)
- **Elevated alanine** (transamination of pyruvate)
- **Ragged red fibers (RRF)** on **Gomori trichrome stain** of muscle biopsy (subsarcolemmal accumulation of abnormal mitochondria)
- **COX-negative fibers** (cytochrome c oxidase staining absent in affected fibers)
- **Strongly SDH-reactive fibers** ("ragged blue fibers")
- **MRI**: stroke-like lesions not conforming to vascular territories, bilateral basal ganglia lesions (Leigh syndrome), cerebellar atrophy
- **Genetic testing**: mtDNA sequencing, nuclear gene panels, whole exome/genome sequencing
- **Enzyme analysis**: measurement of individual complex activities in muscle tissue
### 22.2 Specific Mitochondrial Syndromes
#### MELAS (Mitochondrial Encephalomyopathy, Lactic Acidosis, Stroke-like episodes)
- **Mutation**: **m.3243A>G** in MT-TL1 (tRNA^Leu(UUR)) — ~80% of cases
- Also affects Complex I function predominantly
- **Onset**: usually childhood-young adulthood (onset before age 40)
- **Features**:
- **Stroke-like episodes** (NOT true strokes — do not follow vascular territories; often occipital/parietal)
- Lactic acidosis
- Seizures (often associated with stroke-like episodes)
- Myopathy, exercise intolerance
- Sensorineural hearing loss
- **Diabetes mellitus** (m.3243A>G is a common cause of **maternally inherited diabetes and deafness — MIDD**)
- Short stature
- Migraine headaches
- Cognitive decline
- **Ragged red fibers** on muscle biopsy
- Important: the same m.3243A>G mutation can cause **MELAS**, **MIDD**, or **progressive external ophthalmoplegia (PEO)** — variable phenotype due to heteroplasmy
#### MERRF (Myoclonic Epilepsy with Ragged Red Fibers)
- **Mutation**: **m.8344A>G** in MT-TK (tRNA^Lys) — ~80% of cases
- **Features**:
- **Myoclonus** (stimulus-sensitive, progressive)
- **Generalized epilepsy**
- Myopathy with **ragged red fibers**
- Cerebellar **ataxia**
- **Lipomas** (multiple, symmetric — especially cervical)
- **Sensorineural hearing loss**
- Short stature, optic atrophy, dementia
- Lactic acidosis
#### Leigh Syndrome (Subacute Necrotizing Encephalomyelopathy)
- Most common mitochondrial disease in infancy/childhood
- Can be caused by mutations in >75 different genes (both mtDNA and nuclear)
- Complex I (most common), Complex II, Complex III, Complex IV, Complex V, PDH, CoQ₁₀ biosynthesis
- Common mtDNA mutations: MT-ATP6 (m.8993T>G/C), MT-ND genes
- Common nuclear gene mutations: SURF1 (Complex IV assembly), NDUFS4 (Complex I), SDHA
- **Pathology**: bilateral, symmetric **necrotizing lesions** in basal ganglia (putamen, caudate), **brainstem**, thalamus, spinal cord
- **Features**:
- Developmental regression
- Hypotonia → spasticity
- Respiratory abnormalities (central hypoventilation — brainstem involvement)
- Eye movement abnormalities (nystagmus, ophthalmoplegia)
- Dysphagia
- Lactic acidosis
- Usually fatal in early childhood (but variable)
- **MRI**: bilateral symmetric T2-hyperintense lesions in basal ganglia and brainstem
> **🔴 CLINICAL: SURF1 Mutations and Leigh Syndrome**
> - **SURF1** is a **Complex IV assembly factor** (involved in heme a insertion)
> - Autosomal recessive
> - Most common nuclear gene cause of **COX-deficient Leigh syndrome**
> - Muscle biopsy: **COX-negative fibers** with **SDH-positive** fibers
#### Kearns-Sayre Syndrome (KSS)
- Caused by **large-scale mtDNA deletions** (typically 1.3-10 kb; most common: "common deletion" — 4,977 bp deletion removing genes from ATPase8 to ND5)
- Usually **sporadic** (not maternally inherited — deletions arise de novo in oocyte or early embryogenesis)
- **Diagnostic triad** (all required):
1. **Progressive External Ophthalmoplegia (PEO)** — ptosis + restricted eye movements
2. **Pigmentary retinopathy** ("salt and pepper" fundus)
3. **Onset before age 20**
- **Plus at least one of**: cardiac conduction defect, cerebellar ataxia, CSF protein >100 mg/dL
- Other features: short stature, hearing loss, endocrinopathies (diabetes, hypoparathyroidism, growth hormone deficiency), cognitive decline
- **Cardiac conduction defects** are life-threatening → may require pacemaker (heart block can cause sudden death)
- **Ragged red fibers** and **COX-negative fibers** on muscle biopsy
#### Pearson Syndrome
- Also caused by **large-scale mtDNA deletions** (same deletions as KSS)
- Presents in **infancy** (much earlier than KSS)
- **Sideroblastic anemia** + **pancreatic exocrine insufficiency**
- Bone marrow: **vacuolization of precursors**, **ringed sideroblasts**
- Many die in infancy; survivors may develop **KSS** in later years
- Same deletion → different phenotype due to tissue distribution of mutant mtDNA
#### Chronic Progressive External Ophthalmoplegia (CPEO)
- **PEO** without the full features of KSS
- Can be caused by:
- Single mtDNA deletions (sporadic)
- Nuclear gene mutations affecting mtDNA maintenance → multiple mtDNA deletions:
- **POLG** (mitochondrial DNA polymerase γ)
- **Twinkle/TWNK** (mitochondrial helicase)
- **ANT1/SLC25A4** (adenine nucleotide translocator)
- **RRM2B** (ribonucleotide reductase)
- Features: progressive ptosis, ophthalmoplegia, exercise intolerance
> **🔴 CLINICAL: POLG Mutations**
> - **POLG** encodes the catalytic subunit of **mitochondrial DNA polymerase γ** (responsible for mtDNA replication)
> - Autosomal recessive (or dominant)
> - Can cause a wide spectrum:
> - **Alpers-Huttenlocher syndrome**: childhood; progressive encephalopathy, intractable seizures, hepatopathy → **liver failure** (especially with valproate — **VALPROATE IS CONTRAINDICATED in POLG mutations** as it precipitates fatal hepatotoxicity)
> - **CPEO** (with multiple mtDNA deletions)
> - **Ataxia-neuropathy spectrum** (MIRAS — Mitochondrial Recessive Ataxia Syndrome, SANDO — Sensory Ataxic Neuropathy, Dysarthria, Ophthalmoparesis)
> - **Myocerebrohepatopathy spectrum**
#### NARP (Neuropathy, Ataxia, Retinitis Pigmentosa)
- **Mutation**: **m.8993T>G** (or T>C) in **MT-ATP6**
- When heteroplasmy level is **70-90%** → NARP
- When >90% → **Leigh syndrome** (maternally inherited Leigh syndrome — MILS)
- Features: peripheral neuropathy (sensorimotor), cerebellar ataxia, retinitis pigmentosa, proximal weakness, developmental delay
#### Aminoglycoside-Induced Ototoxicity
- **Mutation**: **m.1555A>G** in MT-RNR1 (12S rRNA)
- This mutation makes the mitochondrial ribosome more "bacterial-like" → **aminoglycosides** (which target bacterial ribosomes) also damage mitochondrial translation
- Individuals with this mutation: even a **single dose** of aminoglycosides can cause **permanent bilateral sensorineural hearing loss**
- Important genetic counseling point; some hospitals screen for this mutation before aminoglycoside use
### 22.3 Acquired Conditions Affecting the ETC
#### Ischemia-Reperfusion Injury
- During **ischemia**: O₂ deprived → ETC cannot function → NADH/FADH₂ accumulate → succinate accumulates (via reversal of Complex II) → ATP depleted → anaerobic glycolysis → acidosis → Ca²⁺ accumulation → cell damage
- During **reperfusion**: O₂ reintroduced → accumulated succinate is rapidly oxidized by Complex II → **reverse electron transport (RET)** through Complex I → massive superoxide production → oxidative damage, cell death, inflammation
- **Clinical relevance**: myocardial infarction reperfusion, stroke thrombolysis, organ transplantation
- **Therapeutic targets**: preventing succinate accumulation, inhibiting RET, antioxidants
#### Sepsis
- NO overproduction (iNOS) → Complex IV inhibition
- ROS-mediated ETC damage
- Mitochondrial dysfunction → bioenergetic failure → organ failure
#### Cancer (Warburg Effect)
- Many cancer cells rely on **aerobic glycolysis** ("Warburg effect") despite functional mitochondria
- Some cancers have **ETC mutations**:
- **SDH mutations** (paraganglioma, pheochromocytoma — discussed above)
- **Fumarate hydratase (FH)** mutations → hereditary leiomyomatosis and renal cell cancer (HLRCC)
- **Isocitrate dehydrogenase (IDH)** mutations → gliomas, AML (oncometabolite 2-hydroxyglutarate)
#### Drug-Induced Mitochondrial Toxicity
| Drug | Mechanism | Clinical Effect |
|------|-----------|-----------------|
| **NRTIs** (zidovudine, stavudine, didanosine) | Inhibit **mitochondrial DNA polymerase γ (POLG)** | Myopathy, lactic acidosis, lipodystrophy, neuropathy, hepatic steatosis |
| **Metformin** | Mild Complex I inhibition | Lactic acidosis (rare, mainly in renal failure) |
| **Doxorubicin** | ROS generation, Complex I inhibition, cardiolipin damage | Cardiomyopathy (dose-dependent, cumulative) |
| **Linezolid** | Inhibits mitochondrial protein synthesis (targets 16S rRNA — similar to bacterial ribosome) | Lactic acidosis, peripheral neuropathy (with prolonged use >2 weeks) |
| **Propofol** | Inhibits Complex I and Complex IV, impairs fatty acid oxidation | **Propofol infusion syndrome** (PRIS): cardiac failure, rhabdomyolysis, lactic acidosis, renal failure, lipemia; associated with high doses (>4 mg/kg/hr) for >48 hours, especially in critically ill children |
| **Valproate** | Depletes CoA, carnitine; inhibits β-oxidation; inhibits Complex IV; toxic in POLG mutations | Hepatotoxicity, hyperammonemia, Reye-like syndrome |
| **Chloramphenicol** | Inhibits mitochondrial ribosomes | Aplastic anemia |
| **Amiodarone** | Inhibits Complexes I and II | Phospholipidosis, liver damage, thyroid dysfunction |
| **Statins** | Decrease CoQ₁₀ synthesis | Myalgia/myopathy (mechanism debated) |
### 22.4 Malignant Hyperthermia
> **🔴 CLINICAL: Malignant Hyperthermia**
> - **Not a primary ETC disorder** but involves catastrophic thermogenesis
> - Autosomal dominant; mutations in **RYR1 (Ryanodine Receptor 1)** — ~70% of cases — or CACNA1S (dihydropyridine receptor)
> - Triggered by **volatile anesthetics** (halothane, sevoflurane, desflurane, isoflurane) and/or **succinylcholine**
> - Mechanism: uncontrolled Ca²⁺ release from sarcoplasmic reticulum → sustained muscle contraction → massively increased ATP consumption → accelerated ETC activity → excessive heat production, CO₂ production
> - Features: rapidly rising temperature, muscle rigidity (especially masseter/jaw rigidity), tachycardia, hypercarbia, metabolic acidosis, rhabdomyolysis, hyperkalemia
> - Treatment: **dantrolene** (blocks RyR1 Ca²⁺ release), active cooling, treat hyperkalemia and acidosis
> - Not the same mechanism as DNP uncoupling but shares the feature of excessive heat production
### 22.5 Thyroid Hormones and ETC
- **Hyperthyroidism**: increased expression of ETC components + increased UCP expression → increased O₂ consumption, heat production → heat intolerance, weight loss, sweating, tachycardia, increased BMR
- **Hypothyroidism**: decreased ETC activity → cold intolerance, weight gain, fatigue, decreased BMR
---
## 23. SUMMARY TABLES
### Table 1: Complete Summary of ETC Complexes
| Feature | Complex I | Complex II | Complex III | Complex IV | Complex V |
|---------|-----------|-----------|-------------|------------|-----------|
| **Name** | NADH:CoQ oxidoreductase | Succinate:CoQ oxidoreductase | CoQH₂:cyt c oxidoreductase | Cytochrome c oxidase | ATP synthase |
| **Subunits** | 45 | 4 | 11 (per monomer) | 13 | 16 |
| **mtDNA-encoded** | 7 (ND1-6, ND4L) | 0 | 1 (cyt b) | 3 (COX I-III) | 2 (ATP6, ATP8) |
| **Prosthetic groups** | FMN, 8 Fe-S clusters | FAD, 3 Fe-S clusters, heme b | Heme bL, heme bH, [2Fe-2S] Rieske, heme c₁ | Heme a, heme a₃, CuA, CuB | None (catalytic) |
| **Electron donor** | NADH | Succinate (FADH₂) | CoQH₂ | Cytochrome c | — |
| **Electron acceptor** | CoQ | CoQ | Cytochrome c | O₂ | — |
| **H⁺ pumped** | 4 | 0 | 4 (via Q cycle) | 2 (+ 2 for H₂O) | ~4 H⁺ consumed per ATP |
| **Inhibitors** | Rotenone, piericidin A, barbiturates, MPP⁺ | Malonate, carboxin, TTFA, 3-NPA | Antimycin A, myxothiazol, stigmatellin | CN⁻, CO, H₂S, N₃⁻, NO | Oligomycin, DCCD |
| **Key diseases** | LHON, Leigh syndrome, Complex I deficiency | Paraganglioma-pheochromocytoma | GRACILE, Björnstad | Leigh (SURF1) | NARP, MILS |
### Table 2: Proton Accounting
| Per NADH | Complex I | Complex III | Complex IV (pumped) | Total H⁺ pumped |
|----------|-----------|-------------|--------------------|--------------------|
| | 4 H⁺ | 4 H⁺ | 2 H⁺ | **10 H⁺** |
| Per FADH₂ | Complex I | Complex III | Complex IV (pumped) | Total H⁺ pumped |
|-----------|-----------|-------------|--------------------|--------------------|
| | 0 (bypassed) | 4 H⁺ | 2 H⁺ | **6 H⁺** |
### Table 3: ATP Yield
| | H⁺ per molecule | ATP per molecule |
|---|-----------------|------------------|
| NADH | 10 | **~2.5** |
| FADH₂ | 6 | **~1.5** |
### Table 4: Vitamins and Minerals in ETC
| Vitamin/Mineral | Role in ETC |
|----------------|-------------|
| **Riboflavin (B₂)** | Precursor of FMN (Complex I) and FAD (Complex II) |
| **Niacin (B₃)** | Precursor of NAD⁺ |
| **Pantothenic acid (B₅)** | Part of CoA (needed for acetyl-CoA — substrate for TCA) |
| **Iron** | Fe-S clusters (Complexes I-III), heme groups (cytochromes) |
| **Copper** | CuA and CuB in Complex IV |
| **Sulfur** | Fe-S clusters |
| **Coenzyme Q₁₀** | Mobile electron carrier (synthesized endogenously) |
| **Ubiquinone biosynthesis** | Requires tyrosine, mevalonate pathway intermediates |
### Table 5: Inhibitors vs. Uncouplers
| Parameter | Inhibitor | Uncoupler |
|-----------|-----------|-----------|
| Electron transport | ↓ Blocked | ↑ Accelerated |
| O₂ consumption | ↓ | ↑↑ |
| ATP synthesis | ↓ | ↓ |
| Heat production | ↓ | ↑↑ |
| Proton gradient | ↑ (builds up, if at Complex V) or normal | ↓↓ (dissipated) |
| NADH/NAD⁺ | ↑ (upstream of block) | ↓ |
---
## FINAL INTEGRATIVE SUMMARY
The Electron Transport Chain represents the culmination of aerobic metabolism. Through an elegant series of redox reactions catalyzed by four multi-subunit complexes embedded in the inner mitochondrial membrane, electrons derived from the oxidation of nutrients are passed in a thermodynamically favorable direction from NADH/FADH₂ to molecular oxygen. The free energy released is captured as a transmembrane electrochemical proton gradient (the proton motive force). ATP synthase, a remarkable molecular rotary motor, harnesses this gradient to synthesize ATP from ADP and Pi through Boyer's binding change mechanism.
The system is subject to:
- **Inhibition** (at any complex — leading to electron transport cessation, ATP depletion, and lactic acidosis)
- **Uncoupling** (dissipation of the proton gradient — electron transport continues but ATP is not made; energy is released as heat)
- **Genetic disorders** (mutations in either mtDNA or nuclear genes encoding ETC subunits, assembly factors, or mtDNA maintenance proteins — producing a vast spectrum of multisystem diseases preferentially affecting high-energy tissues)
Understanding the ETC is essential for comprehending:
- Normal energy metabolism
- The pathophysiology of mitochondrial diseases
- Mechanisms of toxicity (cyanide, CO, drug-induced mitochondrial toxicity)
- The basis of thermogenesis
- The role of ROS in aging, neurodegeneration, and ischemia-reperfusion injury
- Emerging therapeutic targets in cancer, obesity, and metabolic disease
---
*This document covers the essential biochemistry, molecular biology, physiology, pharmacology, and clinical medicine related to the Electron Transport Chain.*
Rewrite the whole content as it is plus add maximum number of high yield clear images along the content from your side