
Going to 1st clinicals for outside hospital just as 2nd year student without final for self experience but i knew nothing from any subject so help me to learn and main important things we also learn daily keep this and remaind me but main things alll I need to learn
What is your medical stream / program? · Which department/rotation are you starting with? · What kind of daily learning do you want?
2nd year MBBS clinical posting survival guide important topics ward skills
https://gmch.gov.in/sites/default/files/documents/Student_Le…
🏥 Your 2nd Year Clinical Survival Guide
"Starting from Zero" - Everything You Need for Your First Hospital Posting
PART 1 - THE MINDSET FIRST
- You show up every day
- You watch and ask questions
- You write things down and look them up that night
- You keep this guide updated as you learn new things
PART 2 - THE 5 THINGS YOU NEED ON DAY 1
| Item | Why |
|---|---|
| Small pocket notebook | Write every new thing you see or hear |
| Pen torch (penlight) | Pupil reflex, throat, ear |
| Stethoscope | Always around your neck |
| Your white coat | Clean, name badge on |
| This guide open on your phone | Reference everything here |
PART 3 - THE MOST IMPORTANT SKILL - HISTORY TAKING (SOCRATES + SYSTEM)
The Universal History Format (use this for EVERY patient)
- "What brought you to hospital today?" - in patient's own words
- Write it as: "Fever for 3 days" or "Chest pain since morning"
| Letter | Question to ask |
|---|---|
| S - Site | Where exactly is it? |
| O - Onset | When did it start? Sudden or gradual? |
| C - Character | What does it feel like? (sharp, dull, burning, crushing) |
| R - Radiation | Does it go anywhere else? |
| A - Associations | Any other symptoms along with this? |
| T - Timing | Constant or comes and goes? How long each time? |
| E - Exacerbating/Relieving | What makes it worse? What makes it better? |
| S - Severity | Score on 1-10? |
- Any previous hospital admissions?
- Hypertension / Diabetes / Asthma / TB / Heart disease?
- Any previous surgeries?
- Current medications? Dosage?
- Any allergies? (especially drug allergies - ask this EVERY time)
- Parents/siblings with similar illness?
- Diabetes, hypertension, cancer in family?
- Smoking (pack-years = packs/day x years smoked)
- Alcohol (units/week)
- Occupation
- Living conditions (for infectious diseases)
- Go through each system briefly: any cough? bowel issues? urinary symptoms? etc.
PART 4 - GENERAL EXAMINATION (What to check on EVERY patient)
The 4 Vitals - Check These First, Every Time
| Vital | Normal Range | How to check |
|---|---|---|
| Temperature | 36.5-37.5°C (oral) | Thermometer |
| Pulse | 60-100 bpm | Radial artery, 15 sec x 4 |
| Blood Pressure | 120/80 mmHg | Sphygmomanometer, right arm seated |
| Respiratory Rate | 12-20/min | Count chest rises for 30 sec x 2 |
| SpO2 | >95% | Pulse oximeter |
General Appearance - Look at the patient from the foot of the bed:
- Conscious? Alert? Confused?
- Comfortable or in distress?
- Pale, jaundiced, cyanosed?
- Well-nourished or malnourished?
Hands (examine first):
- Nails: clubbing, pallor (anemia), koilonychia, leukonychia
- Palms: palmar erythema, Dupuytren's contracture
- Pulse: rate, rhythm, character, volume
Eyes:
- Conjunctival pallor = anemia
- Scleral icterus = jaundice
- Xanthelasma = hyperlipidemia
Mouth:
- Central cyanosis (blue tongue) = hypoxia
- Tongue: smooth tongue = iron/B12 deficiency
Lymph nodes: always check neck, axilla, groin
Edema: press shin for 5 seconds - pitting or non-pitting?
PART 5 - SYSTEM-BY-SYSTEM QUICK GUIDES
🫀 CARDIOVASCULAR (Heart)
- Inspect: Visible pulsations, scars from surgery
- JVP (Jugular Venous Pressure): look at neck veins, raised in heart failure
- Palpate: Apex beat (normally 5th intercostal space, midclavicular line)
- Auscultate with stethoscope - 4 areas:
- Aortic: 2nd right intercostal space
- Pulmonary: 2nd left intercostal space
- Tricuspid: left lower sternal border
- Mitral: apex (5th ICS, MCL)
- Heart Failure: breathlessness, bilateral leg edema, raised JVP, basal crackles
- Hypertension: often found by chance, check BP both arms
- MI (Heart Attack): crushing central chest pain radiating to left arm/jaw, diaphoresis (sweating)
🫁 RESPIRATORY (Lungs)
- White/clear = viral, asthma
- Yellow/green = bacterial infection
- Rusty = pneumonia (lobar)
- Pink frothy = pulmonary edema
- Blood-stained = TB, cancer, PE
- Inspect: Rate, work of breathing, use of accessory muscles, shape of chest
- Tracheal position (normally midline - pushed away in effusion, pulled toward in collapse)
- Expansion: Hands on chest - equal movement?
- Percussion: Resonant (normal air), Dull (fluid/consolidation), Hyperresonant (pneumothorax)
- Auscultation: Vesicular (normal), Bronchial (consolidation), Added sounds:
- Crackles/crepitations = fluid (pneumonia, CCF)
- Wheeze = airway narrowing (asthma, COPD)
- Pleural rub = pleuritis
- Pneumonia: fever, cough, purulent sputum, dullness to percussion, bronchial breath sounds
- Asthma: wheeze, breathlessness, chest tightness, worse at night/with triggers
- TB: chronic cough >3 weeks, fever, night sweats, weight loss, hemoptysis
🫃 ABDOMEN (GI)
- Inspect: Distension, scars, visible veins (caput medusae = portal hypertension), pulsations
- Auscultate FIRST (before palpating, otherwise bowel sounds change): Normal = gurgling every 5-10 sec; Absent = ileus/peritonitis; Tinkling = obstruction
- Percuss: Liver dullness (right side), spleen dullness (left), shifting dullness = ascites
- Palpate: Light then deep, watch patient's face for pain
- Liver: start from right iliac fossa, move up
- Spleen: start from right iliac fossa toward left hypochondrium
- Renal angles: punch tenderness = kidney infection
- Special signs: Murphy's (cholecystitis), McBurney's (appendicitis), Rovsing's (appendicitis)
| Type | Cause | Clue |
|---|---|---|
| Pre-hepatic | Hemolysis | Dark urine, pale stools... wait no - NO bilirubin in urine |
| Hepatic | Liver disease | All abnormal |
| Post-hepatic (Obstructive) | Bile duct blockage | Dark urine + pale/clay stools + itch |
🧠 NEUROLOGY
| Component | Score |
|---|---|
| Eye opening: Spontaneous/To voice/To pain/None | 4/3/2/1 |
| Verbal: Oriented/Confused/Words/Sounds/None | 5/4/3/2/1 |
| Motor: Obeys/Localizes/Withdraws/Flexion/Extension/None | 6/5/4/3/2/1 |
| Maximum | 15 (normal) |
| Minimum | 3 |
| Coma | ≤8 |
- CN II: Visual acuity (read a chart)
- CN III/IV/VI: Eye movements ("follow my finger" - H pattern)
- CN V: Facial sensation
- CN VII: "Show your teeth, close your eyes tight, raise your eyebrows"
- CN IX/X: "Say ahh" - uvula midline?
- CN XII: Tongue out - midline?
- Tone: passive movement of limb - normal/hypertonia/hypotonia
- Power: grade 0-5 (0=no movement, 3=against gravity, 5=full normal)
- Reflexes: use tendon hammer - knee jerk (L3/4), ankle jerk (S1), biceps (C5/6)
- Sensation: light touch, pinprick
- Coordination: finger-nose test, heel-shin test
🍼 PEDIATRICS (Children)
| Age | Motor | Social/Language |
|---|---|---|
| 3 months | Holds head up | Social smile |
| 6 months | Sits with support | Babbles |
| 9 months | Stands with support | Says mama/dada |
| 12 months | Walks alone | 1-2 words with meaning |
| 18 months | Runs | 10+ words |
| 2 years | Climbs stairs | 2-word sentences |
| Age | Normal HR | Normal RR |
|---|---|---|
| Newborn | 100-160 | 40-60 |
| 1-5 years | 80-120 | 20-30 |
| 6-12 years | 70-110 | 15-20 |
- BCG: at birth (against TB)
- OPV + IPV: at birth, 6, 10, 14 weeks (polio)
- DTP (Penta): 6, 10, 14 weeks (diphtheria, tetanus, pertussis)
- MMR: 9-12 months (measles, mumps, rubella)
👶 OBSTETRICS & GYNECOLOGY (OBG)
- G_P_A_ : Gravida (total pregnancies), Para (deliveries >28 wks), Abortion (<28 wks)
- LMP (Last Menstrual Period) - to calculate gestational age and EDD
- EDD (Expected Date of Delivery) = LMP + 9 months + 7 days (Naegele's rule)
- Blood pressure every visit (watch for preeclampsia - BP >140/90 after 20 weeks)
- Fundal height = gestational age in weeks (roughly)
- Fetal heart sounds: normal 110-160 bpm
- Eclampsia: seizures in pregnancy - give MgSO4
- PPH (Postpartum Hemorrhage): >500mL blood loss after delivery
- Cord prolapse: cord visible at vagina - emergency C-section
PART 6 - IMPORTANT INVESTIGATIONS (Lab Values to Know)
CBC (Complete Blood Count)
| Test | Normal Range | Abnormal means |
|---|---|---|
| Hemoglobin (Hb) | Men: 13-17 g/dL, Women: 12-15 g/dL | Low = anemia |
| WBC (White cells) | 4,000-11,000 /μL | High = infection/leukemia |
| Neutrophils | 40-70% | High = bacterial infection |
| Lymphocytes | 20-40% | High = viral infection |
| Platelets | 1,50,000-4,00,000 /μL | Low = dengue, ITP |
LFT (Liver Function Tests)
| Test | Normal |
|---|---|
| Total Bilirubin | 0.3-1.2 mg/dL |
| AST/ALT (transaminases) | <40 U/L |
| ALP | 44-147 U/L |
| Albumin | 3.5-5.0 g/dL |
| PT/INR | 0.9-1.1 |
KFT (Kidney Function Tests)
| Test | Normal |
|---|---|
| Serum Creatinine | 0.6-1.2 mg/dL |
| Blood Urea Nitrogen | 7-20 mg/dL |
| Serum Sodium | 136-145 mEq/L |
| Serum Potassium | 3.5-5.0 mEq/L |
RBS/FBS (Blood Sugar)
| Test | Normal | Diabetes |
|---|---|---|
| Fasting | <100 mg/dL | >126 mg/dL |
| Random (RBS) | <140 mg/dL | >200 mg/dL |
| HbA1c | <5.7% | >6.5% |
PART 7 - COMMON DRUGS YOU'LL SEE ON PRESCRIPTIONS
| Drug | For | Route | Remember |
|---|---|---|---|
| Paracetamol | Fever/pain | Oral/IV | Max 4g/day, safe in pregnancy |
| Ibuprofen (NSAIDs) | Pain/inflammation | Oral | Avoid in renal failure, gastric ulcer |
| Amoxicillin | Bacterial infections | Oral | Check penicillin allergy |
| Metformin | Type 2 Diabetes | Oral | Hold before contrast dye |
| Amlodipine | Hypertension | Oral | Ankle edema is side effect |
| Atorvastatin | High cholesterol | Oral | Give at night |
| Furosemide | Edema/fluid overload | Oral/IV | Loops lose potassium |
| Metronidazole | Anaerobic infections | Oral/IV | No alcohol! |
| Ondansetron | Nausea/vomiting | Oral/IV | QT prolongation concern |
| Omeprazole | Stomach protection/ulcers | Oral | Give before meals |
PART 8 - WARD PRACTICAL SKILLS (Watch First, Then Practice)
- IV cannulation - insert IV line into vein
- Blood sample collection (venipuncture)
- ABG (Arterial Blood Gas) - for respiratory patients
- Urine catheter insertion (Foley's)
- NG (Nasogastric) tube insertion
- Measuring blood pressure manually
- Reading ECG (electrocardiogram) - see below
ECG Reading - 5-Step Approach
- Rate: Count big squares between two R waves, divide 300 by that number. Normal 60-100 bpm.
- Rhythm: Regular or irregular? P wave before every QRS?
- Axis: Normal = -30° to +90°
- P waves: Present? Normal shape?
- QRS + ST changes: Look for ST elevation (STEMI), ST depression (ischemia), Q waves (old MI), widened QRS (bundle branch block)
- PR interval: 0.12-0.20 sec (one big square)
- QRS: <0.12 sec (3 small squares)
- QT: <0.44 sec (adjusted for rate)
PART 9 - HOW TO PRESENT A CASE (On Ward Rounds)
"This is [Mr/Mrs X], a [age]-year-old [male/female] who presented with [chief complaint] for [duration]. On history, [relevant positives and negatives]. On examination, vitals are [state vitals]. General examination revealed [findings]. Systemic examination of [relevant system] showed [findings]. Investigations showed [key results]. My impression is [diagnosis/differential]. The patient is currently on [treatment]."
PART 10 - YOUR DAILY LEARNING ROUTINE (Do This Every Day)
Morning (Before Ward Rounds)
- Review the patients you are following from yesterday
- Look up ONE topic from yesterday that you didn't understand
- Know your patients' vitals from the nursing chart before rounds
During Ward Rounds
- Stand where you can see and hear clearly
- Write every unfamiliar term in your notebook
- Note what questions the senior doctor asks the patient
- Ask "What does that finding mean?" when you have a moment
Evening (After Posting)
- Pick ONE new topic you encountered today
- Read about it for 20-30 minutes from your textbook or notes
- Write a 5-line summary of what you learned
- Ask me (Orris) to explain anything you still don't understand
PART 11 - DAILY TOPIC SCHEDULE (2-Week Rotation Starter)
| Day | Topic | Department |
|---|---|---|
| Day 1 | History taking + SOCRATES | Any |
| Day 2 | Vitals + General examination | Any |
| Day 3 | CVS examination + Heart failure | Medicine |
| Day 4 | ECG basics | Medicine/Cardiology |
| Day 5 | Respiratory examination + Pneumonia | Medicine |
| Day 6 | Abdominal examination + Jaundice | Medicine/Surgery |
| Day 7 | Blood investigations (CBC, LFT, KFT, RBS) | Any |
| Day 8 | Surgical ward - wound care, drains, IV fluids | Surgery |
| Day 9 | Pediatric history + Developmental milestones | Pediatrics |
| Day 10 | Immunization + Pediatric emergencies | Pediatrics |
| Day 11 | Obstetric history + ANC | OBG |
| Day 12 | Common drugs + prescription reading | Pharmacology/Any |
| Day 13 | Neurology exam + GCS | Medicine/Neurology |
| Day 14 | Case presentation practice | Any |
PART 12 - EMERGENCY SIGNS - CALL FOR HELP IMMEDIATELY
- Airway: patient unable to speak/gurgling sounds
- Breathing: RR >30 or <8, SpO2 <90%, severe labored breathing
- Circulation: BP <90/60, HR >130 or <40, cold clammy skin
- Disability: GCS dropping, new-onset seizure, unequal pupils
- Exposure: high fever >40°C, massive bleeding
HOW TO USE THIS GUIDE GOING FORWARD
- What department you're in
- One condition or case you saw
- One question you couldn't answer
- A focused explanation of that condition
- What to look for on examination
- What questions might be asked about it
- A 3-5 line summary to add to your notes
Cardiac
❤️ CARDIAC MODULE - Complete Clinical Guide
For 2nd Year Students on Cardiology/Medicine Posting
SECTION 1 - CARDIAC HISTORY TAKING
5 Key Cardiac Symptoms
| Symptom | Ask This |
|---|---|
| Chest pain | Where? Left/central? Radiation to arm/jaw? Crushing or sharp? Worse on exertion? |
| Dyspnea | On exertion or at rest? How many pillows to sleep? (orthopnea) Woken up at night gasping? (PND) |
| Palpitations | Fast or slow? Regular or irregular? How long? Associated dizziness? |
| Syncope | Any warning? During exertion or at rest? Full loss of consciousness? |
| Edema | Ankle swelling? Both legs? How long? Getting worse? |
- Rheumatic fever as a child? (causes valvular disease)
- Family history of sudden cardiac death or early heart disease?
- Smoking, diabetes, hypertension, high cholesterol? (risk factors)
- Previous heart attack or stents?
SECTION 2 - CARDIOVASCULAR EXAMINATION (Step-by-Step)
THE SEQUENCE: Inspect → Palpate → Percuss → Auscultate
STEP 1 - HANDS (Start here always)
| Finding | What it means |
|---|---|
| Clubbing | Cyanotic congenital heart disease, infective endocarditis |
| Splinter hemorrhages (nails) | Infective endocarditis |
| Osler's nodes (painful lumps on fingers) | Infective endocarditis |
| Janeway lesions (painless on palms) | Infective endocarditis |
| Peripheral cyanosis (blue fingers) | Low cardiac output |
| Xanthomas (fatty deposits on tendons) | High cholesterol |
- Rate - count for 15 sec x 4 (normal 60-100 bpm)
- Rhythm - regular or irregular? (irregular = AF - atrial fibrillation)
- Character - normal / bounding (aortic regurgitation) / weak/thready (shock) / collapsing (AR)
- Volume - normal / increased / decreased
- Radio-radial delay - feel both wrists together (delay = aortic dissection, coarctation)
- Radio-femoral delay - feel wrist + groin simultaneously (delay = coarctation of aorta)
STEP 2 - BLOOD PRESSURE
- Measure both arms (difference >15 mmHg = subclavian stenosis or aortic dissection)
- Normal: <120/80 mmHg
- Hypertension: ≥140/90 mmHg
- Pulse pressure = Systolic - Diastolic (normal ~40 mmHg)
- Wide pulse pressure (>60) = aortic regurgitation, thyrotoxicosis
- Narrow pulse pressure (<25) = aortic stenosis, cardiac tamponade
STEP 3 - FACE & EYES
| Finding | Condition |
|---|---|
| Malar flush (red cheeks) | Mitral stenosis |
| Central cyanosis (blue tongue/lips) | Right-to-left shunt, severe heart failure |
| Xanthelasma (yellow deposits around eyes) | Hypercholesterolemia |
| High-arched palate + tall build | Marfan syndrome (aortic root disease) |
STEP 4 - JVP (Jugular Venous Pressure)
- Patient at 45 degrees, head turned slightly left
- Look at the right side of the neck - find the internal jugular vein (not the carotid - JVP has 2 waves, is non-pulsatile, and goes away when you press on it)
- Normal = top of pulsation <4 cm above sternal angle
- Right heart failure
- Cardiac tamponade (with pulsus paradoxus)
- Superior vena cava obstruction
- Fluid overload
STEP 5 - PRAECORDIUM (Chest)
- Scars: midline sternotomy scar = bypass surgery; left lateral = mitral valve surgery
- Visible pulsations: apex beat visible? Heaves?
- Apex beat: Normally at 5th intercostal space, midclavicular line
- Displaced outward/downward = cardiomegaly (heart failure, dilated cardiomyopathy)
- Tapping quality = mitral stenosis
- Heaving/thrusting = left ventricular hypertrophy (hypertension, aortic stenosis)
- Parasternal heave: Place palm on left sternal border - heave felt = right ventricular enlargement
- Thrills: Palpable vibration = severe murmur present (like feeling a cat purr)
STEP 6 - AUSCULTATION (The most important step)
         2nd Right ICS = AORTIC area (A)
         2nd Left ICS  = PULMONARY area (P)
Left sternal border    = TRICUSPID area (T)
      5th ICS, MCL     = MITRAL/Apex area (M)
- S1 (lub) = mitral + tricuspid valves CLOSING at start of systole
- S2 (dub) = aortic + pulmonary valves CLOSING at end of systole
- Listen: lub-DUB ... lub-DUB (S2 louder at base)
- S3 (lub-dub-ta): heard after S2, at apex - sign of heart FAILURE (volume overload)
- S4 (ta-lub-dub): heard before S1, at apex - sign of STIFF ventricle (hypertension, LVH)
| Grade | Description |
|---|---|
| 1 | Very faint, only with concentration |
| 2 | Faint but heard immediately |
| 3 | Moderate, no thrill |
| 4 | Loud with thrill |
| 5 | Very loud, heard with stethoscope partly off chest |
| 6 | Heard without stethoscope |
COMMON MURMURS TO KNOW
| Murmur | Type | Area | Radiation | Pitch | Mnemonic |
|---|---|---|---|---|---|
| Aortic Stenosis | Systolic (ejection) | Aortic area | To neck/carotids | Harsh, crescendo-decrescendo | "AS radiates to neck" |
| Aortic Regurgitation | Diastolic | Aortic area | Left sternal border | Soft, blowing, early diastolic | "AR = diastolic at left sternal border" |
| Mitral Stenosis | Diastolic | Apex | None | Rumbling, low-pitched, mid-diastolic | "MS = rumble at apex" |
| Mitral Regurgitation | Systolic (pansystolic) | Apex | To axilla | Blowing, pansystolic | "MR blows to armpit" |
STEP 7 - LUNGS (always do this after cardiac exam)
- Basal crackles (crepitations) at both lung bases = pulmonary edema from left heart failure
- Pleural effusion (stony dullness, absent breath sounds) = can be from heart failure
STEP 8 - ABDOMEN & LEGS
- Hepatomegaly (enlarged liver): right heart failure causes liver congestion - tender liver
- Ascites: right heart failure (shifting dullness)
- Pitting edema: press shin/ankle for 5 seconds - indentation = pitting edema from heart failure, hypoalbuminemia
SECTION 3 - MOST COMMON CONDITIONS YOU'LL SEE
1. HEART FAILURE
| HFrEF (Reduced EF) | HFpEF (Preserved EF) | |
|---|---|---|
| EF | <40% | >50% |
| Problem | Weak pump | Stiff pump |
| Common cause | MI, dilated cardiomyopathy | Hypertension, diabetes, obesity |
| Left Heart Failure | Right Heart Failure |
|---|---|
| Dyspnea on exertion | Ankle/leg edema |
| Orthopnea (can't lie flat) | Raised JVP |
| PND (woken at night gasping) | Tender hepatomegaly |
| Basal lung crackles | Ascites |
| Frothy pink sputum (severe) |
- ECG: may show LVH, old MI, arrhythmia
- Chest X-Ray (CXR): look for ABCDE:
- A - Alveolar edema (bat-wing shadowing)
- B - Kerley B lines (horizontal lines at bases)
- C - Cardiomegaly (CTR >0.5)
- D - Dilated upper lobe veins
- E - Effusion (pleural)
- BNP/NT-proBNP: elevated in heart failure (best marker)
- Echo (TTE): measures ejection fraction - the GOLD STANDARD test
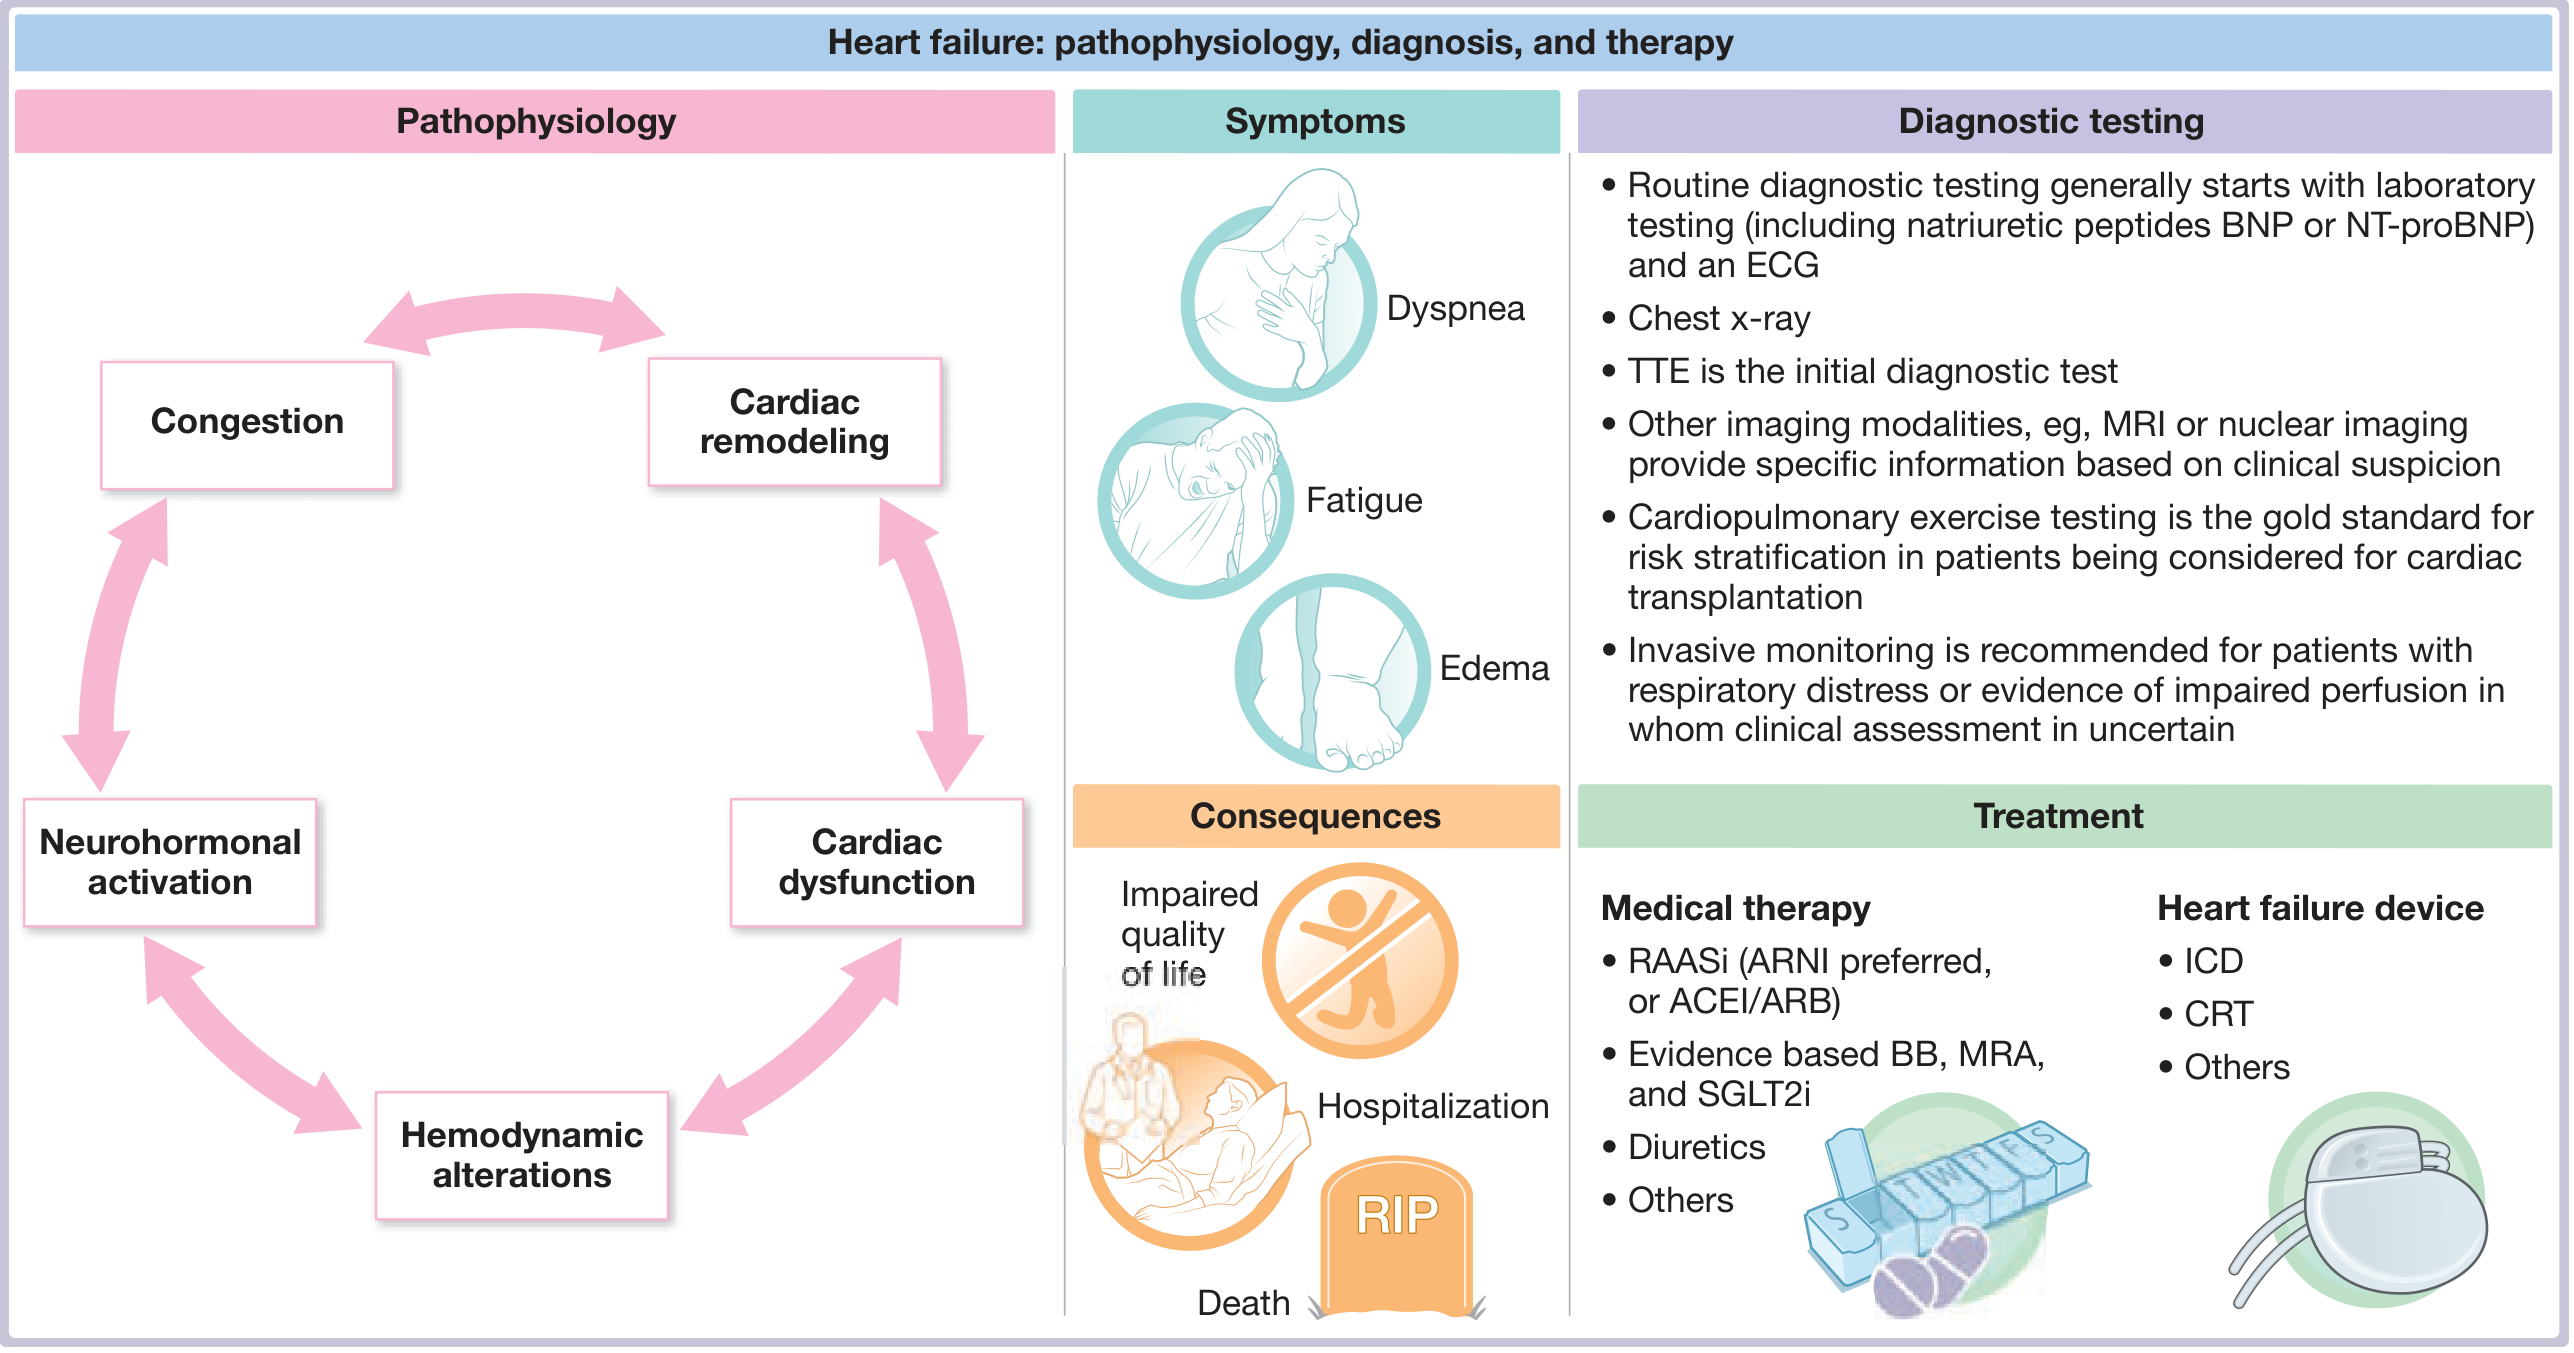
| Drug class | Example | Why given |
|---|---|---|
| Beta-blocker | Carvedilol, Metoprolol | Reduces mortality, slows heart |
| ACEi / ARB / ARNI | Ramipril / Sacubitril-Valsartan | Reduces remodeling, mortality |
| Diuretic | Furosemide | Relieves congestion/edema |
| SGLT2 inhibitor | Dapagliflozin, Empagliflozin | New - reduces hospitalization |
| Spironolactone (MRA) | Spironolactone | Reduces mortality |
2. HYPERTENSION
| Category | Systolic | Diastolic |
|---|---|---|
| Normal | <120 | <80 |
| Elevated | 120-129 | <80 |
| Stage 1 HTN | 130-139 | 80-89 |
| Stage 2 HTN | ≥140 | ≥90 |
| Hypertensive Crisis | >180 | >120 |
- Renal artery stenosis
- Pheochromocytoma (episodic headache, sweating, palpitations)
- Hyperaldosteronism (low potassium + high BP)
- Coarctation of aorta
- Heart: LVH, heart failure, IHD
- Eyes: hypertensive retinopathy (papilledema, AV nipping, flame hemorrhages)
- Aorta: dissection
- Deep kidneys: proteinuria, CKD
- Stroke/brain: hemorrhagic stroke, hypertensive encephalopathy
- Young patient: ACE inhibitor (Ramipril 2.5-10mg OD)
- Elderly/African: Calcium channel blocker (Amlodipine 5-10mg OD)
- With fluid overload: Thiazide diuretic (Hydrochlorothiazide 12.5-25mg OD)
3. ISCHEMIC HEART DISEASE (IHD) / ANGINA / MI
Stable Angina → Unstable Angina → NSTEMI → STEMI
(chronic)           (ACS - Acute Coronary Syndrome)
- Sudden severe crushing/squeezing central chest pain
- Radiation to left arm, jaw, neck, back
- Sweating (diaphoresis), nausea, vomiting
- Breathlessness
- Sense of doom
- Note: Diabetics and elderly can have SILENT MI (no pain - just breathlessness, fatigue)
| Stage | ECG Finding |
|---|---|
| Hyperacute (minutes) | Tall peaked T waves |
| Acute (hours) | ST elevation (STEMI) |
| Evolving (hours-days) | T wave inversion |
| Old (days-weeks) | Pathological Q waves (>0.04 sec, >25% of R) |
| Leads with changes | Territory | Artery |
|---|---|---|
| II, III, aVF | Inferior | RCA |
| V1-V4 | Anterior | LAD |
| I, aVL, V5-V6 | Lateral | LCx |
- MONA (old mnemonic, still useful to know):
- Morphine (for pain)
- Oxygen (if SpO2 <94%)
- Nitrates (GTN) - sublingual
- Aspirin 300mg (chewed, not swallowed)
- Dual antiplatelet: Aspirin + Clopidogrel (or Ticagrelor)
- Reperfusion within 90 min: Primary PCI (angioplasty + stent) is GOLD STANDARD. If not available: thrombolysis (streptokinase or tPA)
- Anticoagulation: Heparin
- Long-term: Beta-blocker + ACEi + Statin + Dual antiplatelets
4. ATRIAL FIBRILLATION (AF)
- No visible P waves (replaced by fibrillatory baseline - wavy line)
- Irregularly irregular QRS complexes
- Ventricular rate usually fast (100-180 bpm) if uncontrolled
- Pulmonary (PE, pneumonia)
- Ischaemia (MI)
- Rheumatic heart disease
- Alcohol / thyrotoxicosis
- Thyroid (hyperthyroidism - very common cause)
- Electrolytes (low K/Mg)
- Sepsis / surgery
- Rate control: Beta-blocker (metoprolol) or Digoxin
- Rhythm control: Cardioversion (electrical or chemical with amiodarone)
- Anticoagulation to prevent stroke: Warfarin or DOACs (apixaban, rivaroxaban) - based on CHA₂DS₂-VASc score
SECTION 4 - ECG INTERPRETATION (Step-by-Step System)
Step 1 - Check the basics
- Patient name, date, speed (25 mm/sec standard), calibration (1mV = 10mm)
Step 2 - Rate
- Regular rhythm: 300 ÷ number of large squares between R waves
- Irregular: count QRS complexes in 10-second strip × 6
Step 3 - Rhythm
- Is it regular or irregular?
- Is there a P wave before every QRS?
- Regular + P before every QRS = sinus rhythm ✓
Step 4 - Axis
| Leads I & aVF | Axis |
|---|---|
| Both positive | Normal (-30° to +90°) |
| I positive, aVF negative | Left axis deviation (LAD) |
| I negative, aVF positive | Right axis deviation (RAD) |
Step 5 - P wave
- Present? Normal shape? Duration <0.12 sec? Positive in I and II?
- Absent = AF or junctional rhythm
Step 6 - PR interval
- Normal: 0.12-0.20 sec (3-5 small squares)
- Short (<0.12): WPW syndrome
- Prolonged (>0.20): 1st degree AV block
- Progressive lengthening then dropped beat: 2nd degree (Wenckebach)
- No relationship between P and QRS: 3rd degree (complete) heart block
Step 7 - QRS, ST, T waves
| Finding | Meaning |
|---|---|
| Wide QRS (>0.12 sec) | Bundle branch block or ventricular rhythm |
| LBBB pattern (broad notched R in V5/V6) | Left bundle branch block |
| RBBB pattern (RSR' in V1, broad S in V6) | Right bundle branch block |
| ST elevation | STEMI, pericarditis |
| ST depression | NSTEMI/unstable angina, ischemia, digoxin |
| T wave inversion | Ischemia, PE, LVH |
| Pathological Q wave | Old MI (>0.04 sec or >25% of R wave height) |
SECTION 5 - IMPORTANT CARDIAC INVESTIGATIONS AT A GLANCE
| Test | What it tells you | When to order |
|---|---|---|
| ECG | Rate, rhythm, ischemia, blocks | First test for all cardiac complaints |
| CXR | Cardiomegaly, pulmonary edema, effusion | Dyspnea, suspected heart failure |
| Echo (TTE) | EF, valve function, wall motion | Heart failure, murmur, suspected structural disease |
| BNP/NT-proBNP | Heart failure marker | Dyspnea - is it cardiac or respiratory? |
| Troponin I or T | Myocardial necrosis | Chest pain - rule in/rule out MI (serial: 0, 3, 6 hours) |
| Lipid profile | Cardiovascular risk | All cardiac patients |
| HbA1c | Diabetes control | All cardiac patients (diabetes = major risk factor) |
| TSH | Thyroid function | AF, heart failure |
SECTION 6 - CARDIAC DRUGS SUMMARY (You'll See These Daily)
| Drug | Class | Use | Key Side Effect |
|---|---|---|---|
| Aspirin | Antiplatelet | MI prevention, ACS | GI bleeding |
| Clopidogrel | Antiplatelet | After stent, ACS | Bleeding |
| Atorvastatin | Statin | Cholesterol, CAD prevention | Myopathy, ↑LFTs |
| Ramipril | ACE inhibitor | HTN, heart failure, post-MI | Dry cough, hyperkalemia |
| Metoprolol/Carvedilol | Beta-blocker | HTN, HF, angina, AF | Bradycardia, bronchospasm (avoid in asthma) |
| Amlodipine | Calcium channel blocker | HTN, angina | Ankle edema, flushing |
| Furosemide | Loop diuretic | Heart failure, edema | Hypokalemia, dehydration |
| Spironolactone | MRA | Heart failure, HTN | Hyperkalemia, gynecomastia |
| Digoxin | Cardiac glycoside | AF rate control, HF | Narrow therapeutic window - toxicity: nausea, xanthopsia (yellow vision), bradycardia |
| GTN (Nitroglycerin) | Nitrate | Angina relief | Headache, hypotension |
| Warfarin | Anticoagulant | AF, DVT, valve disease | Bleeding - monitor INR (target 2-3) |
| Heparin | Anticoagulant | ACS, DVT (acute) | Bleeding, HIT |
| Amiodarone | Antiarrhythmic | AF, VT | Thyroid, lung, liver, photosensitivity |
SECTION 7 - QUICK REFERENCE CARD (Memorize These)
NORMAL CARDIAC VALUES:
HR: 60-100 bpm
BP: <120/80 mmHg
Apex beat: 5th ICS, MCL
PR interval: 0.12-0.20 sec
QRS: <0.12 sec
EF (ejection fraction): 55-70% normal; <40% = HFrEF

KEY NUMBERS:
JVP normal: <4 cm above sternal angle (at 45°)
BNP: >100 pg/mL = likely heart failure
NT-proBNP: >125 pg/mL = heart failure
Troponin: ANY elevation = myocardial injury
TODAY'S SUMMARY (5 Lines)
- Cardiac exam follows: Hands → Pulse → BP → Face → JVP → Praecordium (IPPPA) → Lungs → Legs
- S3 = heart failure; S4 = stiff ventricle (HTN/LVH)
- STEMI = ST elevation on ECG → call senior immediately → aspirin + reperfusion
- AF = irregularly irregular pulse, no P waves, risk of stroke → anticoagulate
- Heart failure = dyspnea + edema + raised JVP + basal crackles → treat with BADS drugs
Tests in cardiac like ecg echo angio and other all how to learn and red it
🔬 CARDIAC INVESTIGATIONS - How to Learn & Read All of Them
Complete Guide for Clinical Students
THE BIG PICTURE - What Test Gets Ordered When?
Patient comes with cardiac complaint
            ↓
STEP 1: ECG (first, always, within 10 minutes)
            ↓
STEP 2: Blood tests (Troponin, BNP, CBC, LFT, KFT, lipids)
            ↓
STEP 3: Chest X-Ray
            ↓
STEP 4: Echocardiogram (Echo/TTE) - structure & function
            ↓
STEP 5: Stress Test / Holter (if needed)
            ↓
STEP 6: CT Angio / MRI (specialized)
            ↓
STEP 7: Coronary Angiography (invasive - gold standard for arteries)
TEST 1 - ECG (Electrocardiogram)
What is an ECG?
The 12 Leads - What Each One "Looks At"
Limb leads (on arms and legs):
| Lead | Looks at |
|---|---|
| I | Lateral wall of heart |
| II | Inferior + conduction (used for rhythm strip) |
| III | Inferior wall |
| aVR | Right side (looks "into" the cavity - normally negative) |
| aVL | High lateral wall |
| aVF | Inferior wall |
Chest/Precordial leads (V1-V6):
| Lead | Looks at |
|---|---|
| V1-V2 | Septal wall |
| V3-V4 | Anterior wall |
| V5-V6 | Lateral wall |
The ECG Waveform - What Each Part Means
         R
        / \
       /   \
P    T/     \
 \  / \     S
  \/   \   /
  Q     \_/

P wave → QRS complex → T wave
| Wave/Interval | What it represents | Normal Duration |
|---|---|---|
| P wave | Atrial depolarization (atria contract) | <0.12 sec (3 small squares) |
| PR interval | Time from atrial to ventricular activation (AV node delay) | 0.12-0.20 sec (3-5 small squares) |
| QRS complex | Ventricular depolarization (ventricles contract) | <0.12 sec (<3 small squares) |
| ST segment | Ventricles fully depolarized (should be at baseline) | Flat = normal |
| T wave | Ventricular repolarization (ventricles recover) | Same direction as QRS |
| QT interval | Total ventricular activity | <0.44 sec (corrected for rate) |
- Small square = 0.04 sec (40 ms) horizontally
- Large square = 0.20 sec (200 ms) = 5 small squares
- Vertically: 1 small square = 0.1 mV
How to READ an ECG - The 7-Step System (Never Skip Steps)
Step 1 - Check Calibration & Speed
- Standard speed: 25 mm/sec
- Standard calibration: 10 mm = 1 mV (look for calibration box at start)
Step 2 - Heart Rate
Rate = 300 ÷ (number of large squares between two R peaks)
| Large squares between R-R | Heart rate |
|---|---|
| 1 | 300 bpm |
| 2 | 150 bpm |
| 3 | 100 bpm |
| 4 | 75 bpm |
| 5 | 60 bpm |
| 6 | 50 bpm |
Step 3 - Rhythm
- Is it regular? (Are R-R intervals equal?)
- Is there a P wave before every QRS? (= sinus rhythm)
- Is the QRS narrow (<3 small squares) or wide?
| Pattern | Rhythm |
|---|---|
| Regular, P before every QRS, narrow QRS | Normal sinus rhythm ✓ |
| Regular, no P waves, narrow QRS | Junctional rhythm |
| Irregularly irregular, no P waves | Atrial Fibrillation |
| Regular saw-tooth waves, 2:1 or 4:1 QRS | Atrial Flutter |
| No organized activity, chaotic | Ventricular Fibrillation (emergency!) |
Step 4 - Axis
| Lead I | aVF | Axis |
|---|---|---|
| Positive (upright) | Positive (upright) | Normal ✓ |
| Positive | Negative | Left axis deviation (LAD) |
| Negative | Positive | Right axis deviation (RAD) |
| Both negative | Extreme axis |
- LAD: LBBB, left anterior fascicular block, inferior MI
- RAD: RBBB, right ventricular hypertrophy, lateral MI, PE
Step 5 - P Waves
- Present and upright in leads I and II = sinus rhythm
- Absent = AF, junctional rhythm, or complete heart block
- Peaked P in II (>2.5mm) = right atrial enlargement (P pulmonale)
- Broad notched P in II = left atrial enlargement (P mitrale)
Step 6 - PR Interval (0.12-0.20 sec)
| PR interval | Condition |
|---|---|
| Short (<0.12 sec) | WPW syndrome (delta wave), junctional |
| Normal (0.12-0.20) | Normal ✓ |
| Long >0.20 (1 big square) | 1st degree AV block |
| Progressive lengthening then dropped beat | 2nd degree Mobitz I (Wenckebach) |
| Fixed PR, some beats dropped | 2nd degree Mobitz II |
| P and QRS completely unrelated | 3rd degree (Complete) heart block - emergency! |
Step 7 - QRS, ST segment, T waves
| Finding | Meaning |
|---|---|
| Wide QRS (>3 small squares / 0.12 sec) | BBB or ventricular origin |
| RBBB pattern (RSR' in V1, wide S in V6) | Right bundle branch block |
| LBBB pattern (broad M-shaped in V5/V6, W in V1) | Left bundle branch block |
| Pathological Q wave (>1 small square wide OR >25% of R height) | Old MI |
| ST change | Meaning |
|---|---|
| Elevation ≥1mm in ≥2 contiguous limb leads | STEMI (call senior now!) |
| Elevation ≥2mm in ≥2 contiguous chest leads | STEMI |
| Saddle-shaped elevation in all leads | Pericarditis |
| Depression ≥1mm | Ischemia, NSTEMI, digoxin effect |
| Horizontal/downsloping depression | More specific for ischemia |
- Inverted T in V1-V4 = anterior ischemia, PE, right heart strain
- Tall peaked T = hyperkalemia (early), hyperacute STEMI
- Flattened T = hypokalemia, ischemia
ECG Patterns to Recognize Immediately
STEMI (Emergency - shout for help):
- ST elevation in at least 2 leads in the same territory
- New LBBB can also = STEMI equivalent
AF (Atrial Fibrillation):
- No P waves
- Irregularly irregular QRS
- Wavy/fibrillatory baseline
Complete Heart Block (3rd degree):
- P waves march at their own rate (~30-60 bpm)
- QRS complex marches at its own slower rate
- They have NO relationship to each other
- Wide QRS (escape rhythm from ventricles)
Ventricular Tachycardia (VT):
- Wide QRS tachycardia (rate >100, QRS >0.12)
- Monomorphic (all QRS same shape) = regular VT
- If pulseless = VF → Defibrillate immediately
WPW (Wolff-Parkinson-White):
- Short PR (<0.12 sec)
- Delta wave (slurred upstroke of QRS)
- Wide QRS
- Accessory pathway bypasses AV node
TEST 2 - ECHOCARDIOGRAM (Echo / TTE)
What is it?
Types of Echo
| Type | How | What it shows |
|---|---|---|
| TTE (Transthoracic Echo) | Probe on chest wall | Standard views - structure, EF, valves |
| TOE/TEE (Transoesophageal) | Probe swallowed - sits behind heart | Better images - used for valves, thrombus, endocarditis |
| Stress Echo | Echo during exercise or dobutamine | Wall motion abnormalities during ischemia |
| 3D Echo | Volumetric imaging | Detailed valve anatomy, EF |
The Most Important Echo Numbers to Know
| Measurement | Normal Value | Abnormal means |
|---|---|---|
| Ejection Fraction (EF) | 55-70% | <40% = HFrEF (systolic failure) |
| LV end-diastolic diameter | <5.5 cm | >5.5 = dilated LV |
| LV wall thickness | 0.6-1.1 cm | >1.1 = LVH (hypertrophy) |
| Aortic root | <3.7 cm | >4.0 = aortic root dilation (Marfan risk) |
| IVC diameter | <2.1 cm, collapses >50% | Non-collapsing IVC = raised RA pressure |
What the Echo Report Will Tell You
- EF% - the most important single number
- Wall motion abnormality (WMA) = area of heart not moving = previous MI
- TAPSE >17mm = normal RV function
- <17mm = RV dysfunction (cor pulmonale, PE, right heart failure)
- Each valve graded as: Normal / Mild / Moderate / Severe regurgitation or stenosis
- Aortic valve area (AVA): Normal >2 cm², Severe AS <1 cm²
- Pericardial effusion = fluid around heart
- Large effusion + hemodynamic compromise = cardiac tamponade (emergency)
- E/A ratio for diastolic function
- Pressure gradients across valves (e.g., mean gradient >40 mmHg = severe AS)
How to understand Echo views (what the probe shows):
| View | How to get it | What you see |
|---|---|---|
| Parasternal long axis (PLAX) | Probe left of sternum, 3-4th ICS | LV, aortic valve, mitral valve side-on |
| Parasternal short axis (PSAX) | Same position rotated 90° | Cross-section of LV - like looking down a barrel |
| Apical 4-chamber | Probe at apex (where you felt apex beat) | All 4 chambers at once - great for EF |
| Subcostal | Probe below xiphisternum | IVC, pericardial effusion |
TEST 3 - CORONARY ANGIOGRAPHY (Cardiac Cath / Angio)
What is it?
When is it done? (Indications)
| Situation | Why angio |
|---|---|
| STEMI | Immediate PCI (open the blocked artery) |
| ACS (NSTEMI/unstable angina) | Risk stratification + possible stenting |
| Stable angina not controlled by drugs | Check severity of blockages |
| Positive stress test | Confirm ischemia, plan treatment |
| Before valve surgery | Rule out coexisting coronary disease |
| New-onset heart failure | Check if ischemic cause |
| Cardiogenic shock | Urgent revascularization |
What you see on angiogram:
- Normal artery: Smooth, well-defined lumen with good dye flow
- Stenosis: Narrowing of the artery - described as % blockage (e.g., 70% stenosis)
- Occlusion: Complete block, no dye flow beyond the point
- TIMI flow grade:
- Grade 0 = no flow (complete occlusion)
- Grade 1 = trickle
- Grade 2 = partial flow
- Grade 3 = normal flow ✓
What happens after angio?
| Finding | Action |
|---|---|
| <50% stenosis | Medical management only |
| 50-70% stenosis | Depends on symptoms and FFR measurement |
| >70% stenosis | PCI (stenting) or CABG (bypass surgery) |
| Left main disease or triple vessel disease | CABG preferred |
PCI (Angioplasty + Stent):
- Balloon inflated to open stenosis
- Stent (metal mesh tube) placed to keep artery open
- Drug-eluting stent (DES) = coated with drug to prevent re-narrowing
- Post-stent: dual antiplatelet for at least 12 months (Aspirin + Clopidogrel)
TEST 4 - BLOOD TESTS IN CARDIAC PATIENTS
Cardiac Enzymes / Biomarkers
Troponin (the most important)
- Released when heart muscle cells die
- Types: Troponin I (TnI) and Troponin T (TnT) - high sensitivity versions used now
- Any elevation = myocardial injury (must interpret with clinical context)
| Time from MI | Troponin level |
|---|---|
| 0-2 hours | Starting to rise |
| 3-6 hours | Detectably elevated |
| 12-24 hours | Peak |
| 7-10 days | Returns to normal |
- PE (pulmonary embolism)
- Myocarditis
- Sepsis
- Renal failure
- Tachyarrhythmia
- Stroke/subarachnoid hemorrhage
BNP / NT-proBNP (Heart Failure Marker)
- Released by ventricles when they are stretched (volume/pressure overload)
- Best test for: "Is this dyspnea cardiac or respiratory?"
| BNP Level | Interpretation |
|---|---|
| <100 pg/mL | Heart failure unlikely |
| 100-400 | Indeterminate - assess clinically |
| >400 pg/mL | Heart failure very likely |
| NT-proBNP | Interpretation |
|---|---|
| <125 pg/mL (age <75) | Heart failure unlikely |
| >900 pg/mL (age <75) | Heart failure likely |
CK-MB (Creatine Kinase - MB fraction)
- Older marker, less specific than troponin
- Still used in some centers to detect re-infarction (rises faster than troponin after repeat MI)
Other Blood Tests Ordered in Cardiac Patients
| Test | Why ordered | What to look for |
|---|---|---|
| CBC | Anemia worsens cardiac disease | Low Hb = anemia |
| Lipid profile | Cardiovascular risk | LDL >100 mg/dL = treat if CAD |
| HbA1c | Diabetes control | >6.5% = diabetic |
| KFT (creatinine) | Renal function before ACEi, contrast dye | Check before angio |
| Potassium | Before diuretics, ACEi | <3.5 = hypokalemia (arrhythmia risk) |
| TSH | Thyroid disease causes AF, HF | High TSH = hypothyroidism, low = hyperthyroidism |
| Serum ferritin + iron | Iron deficiency worsens heart failure | Low ferritin = give IV iron |
| Coagulation (PT/INR) | Warfarin monitoring | Target INR 2-3 for AF |
| D-dimer | Suspected PE or DVT | <500 = PE unlikely if low pre-test probability |
TEST 5 - CHEST X-RAY (CXR) IN CARDIAC DISEASE
How to Read a CXR Systematically (ABCDE)
A - Airway
- Trachea midline? (pushed = tension pneumothorax, mediastinal mass)
B - Bones & Borders
- Look at ribs, clavicles for rib notching (coarctation of aorta)
- Heart borders sharp? (blurred = consolidation next to heart)
C - Cardiac size
- CTR (Cardiothoracic Ratio): Widest heart diameter ÷ widest chest diameter
- Normal < 0.5 (heart occupies less than half the chest)
-
0.5 on PA film = cardiomegaly
D - Diaphragm
- Right higher than left (liver below)
- Loss of costophrenic angle = pleural effusion
- Air under diaphragm = perforated viscus (surgery emergency)
E - Everything Else (pulmonary vasculature)
| X-ray Sign | Meaning |
|---|---|
| Upper lobe venous diversion | Early left heart failure (veins in upper zones become more prominent) |
| Kerley B lines (horizontal lines at bases) | Interstitial edema |
| Bat-wing / Butterfly shadowing | Alveolar pulmonary edema - severe |
| Bilateral pleural effusions | Heart failure, hypoalbuminemia |
| Large globular heart shadow | Pericardial effusion ("flask-shaped heart") |
TEST 6 - STRESS TEST (Exercise ECG / TMT)
What is it?
Why done?
- Diagnose angina / ischemia
- Risk-stratify after MI
- Assess exercise-induced arrhythmias
Positive stress test (= ischemia) - stop the test if any of these:
- ST depression >1mm (horizontal or downsloping) during exercise
- ST elevation during exercise
- Chest pain reproduced
- BP drops during exercise (hypotension = severe disease)
- Serious arrhythmia (VT, VF)
Contraindications (don't do stress test in these patients):
- STEMI within 2 days
- Unstable angina (ongoing chest pain)
- Uncontrolled heart failure
- Severe aortic stenosis
- Uncontrolled arrhythmia
TEST 7 - HOLTER MONITOR & AMBULATORY ECG
What is it?
Why used?
- Patient reports palpitations, dizziness, blackouts - but ECG in clinic is normal
- Monitor for paroxysmal AF (comes and goes)
- Assess heart rate response to antiarrhythmic drugs
Types:
| Device | Duration | Used for |
|---|---|---|
| Holter monitor | 24-48 hours | Frequent palpitations |
| Event recorder (loop) | Weeks to months | Infrequent symptoms |
| Implantable loop recorder (ILR) | Up to 3 years | Very rare syncope, cryptogenic stroke |
| Telemetry (inpatient) | Continuous | Hospitalized cardiac patients |
What to look for in a Holter report:
- Maximum and minimum heart rate over 24 hours
- Any pauses (>3 seconds = significant)
- PACs (premature atrial contractions) or PVCs (ventricular)
- Paroxysmal AF episodes
- Does the patient's diary symptoms match any arrhythmia on the recording?
TEST 8 - CT CORONARY ANGIOGRAPHY (CTCA) & CARDIAC MRI
CTCA (CT Coronary Angiogram)
- Non-invasive way to look at coronary arteries using a CT scanner + contrast dye
- Used for: Intermediate-risk chest pain, ruling out significant CAD
- Gives calcium score (higher = more plaque = higher CV risk)
- Cannot treat (unlike invasive angiography) - only diagnoses
Cardiac MRI (CMR)
- Best test for: Myocarditis, cardiomyopathy, cardiac masses, pericardial disease, viability assessment
- No radiation
- Late gadolinium enhancement (LGE): Shows areas of scar tissue (fibrosis) - crucial for cardiomyopathy diagnosis
- Not available everywhere - done in specialized centers
SUMMARY TABLE - Which Test Answers Which Question?
| Clinical Question | Best Test |
|---|---|
| Is there an arrhythmia right now? | ECG |
| Did this patient have an MI? | Serial Troponin (0, 3, 6h) |
| Does the patient have heart failure? | BNP + Echo |
| How strong is the heart pumping? | Echo (EF%) |
| Are the heart valves working? | Echo (Doppler) |
| Is there significant coronary blockage? | Coronary Angiography (gold standard) |
| Screening for CAD non-invasively? | CTCA |
| Intermittent palpitations at home? | Holter monitor |
| Is there cardiac scar/myocarditis? | Cardiac MRI |
| Is there pulmonary edema? | Chest X-Ray |
| Exercise-induced chest pain? | Stress test (TMT) |
| Before giving contrast/ACEi? | Serum creatinine |
| Before giving diuretics? | Serum potassium |
DAILY CARD - Stick This on Your Notebook
ECG READING ORDER (Never skip):
1. Rate  2. Rhythm  3. Axis  4. P waves
5. PR interval  6. QRS  7. ST & T waves

NORMAL VALUES:
HR: 60-100  |  PR: 3-5 small squares
QRS: <3 squares  |  QT: <11 squares
ST: flat/isoelectric  |  T: same direction as QRS

STEMI = ST elevation in 2+ contiguous leads → EMERGENCY
AF = No P waves + irregular QRS
3rd degree block = P and QRS unrelated → EMERGENCY

ECHO: EF <40% = systolic failure (HFrEF)
TROPONIN: Any rise = myocardial injury
BNP >400 = heart failure likely
In patient ward possible of any departments what need to learn all explain fast
medical student inpatient ward skills checklist all departments general medicine surgery OBG pediatrics
🏥 INPATIENT WARD - Everything You Need to Know
All Departments | Fast & Practical
THE GOLDEN RULE IN ANY WARD
Every patient in every department needs the same 3 things from you:
- A proper history
- A proper examination
- A plan (investigations + treatment)
The rest is just department-specific details layered on top.
PART 1 - WHAT HAPPENS IN THE WARD (Daily Routine)
The Typical Ward Day
| Time | Activity | What you do |
|---|---|---|
| 7:00-8:00 AM | Pre-round | Check vitals chart, review overnight events, read new results |
| 8:00-10:00 AM | Ward rounds | Walk with team, present your patients, take notes |
| 10:00 AM-1:00 PM | Post-round work | Collect samples, write notes, assist procedures |
| 2:00-4:00 PM | Afternoon rounds/procedures | Follow up results, IV fluids, dressings |
| 4:00-5:00 PM | Handover | Pass information to night team |
The Hierarchy - Know Who is Who
Consultant (Attending) → Head of team
        ↓
Senior Resident (PG 2-3) → Runs the ward
        ↓
Junior Resident (PG 1) → Day-to-day orders
        ↓
Intern → Direct ward work
        ↓
YOU (Student) → Learn, observe, assist
PART 2 - UNIVERSAL WARD SKILLS (Every Department)
SKILL 1 - Reading the Bedside Chart
TEMPERATURE CHART (TPR chart):
- Temperature: plotted as dots - look for fever spikes (>38°C) or hypothermia (<36°C)
- Pulse: plotted as line
- Respiration rate: noted
- Blood pressure: recorded each shift
- SpO2: oxygen saturation
- Input/Output chart: IV fluids in + oral in / urine out + drain out
- Max temp in last 24 hours - fever? improving?
- Pulse rate trend
- Blood pressure - high/low?
- Urine output - minimum acceptable = 0.5 mL/kg/hour (e.g., 70kg person = 35 mL/hour minimum)
- Any overnight events written in nursing notes?
SKILL 2 - IV Lines & IV Fluids
Types of IV Access:
| Type | Where | Used for |
|---|---|---|
| Peripheral IV (cannula) | Vein on hand/forearm | Fluids, drugs (most patients) |
| Central line (CVP) | Neck/chest/groin | ICU patients, caustic drugs, CVP monitoring |
| Arterial line | Radial artery | Continuous BP monitoring, ABG |
IV Fluid Types - Know These 5:
| Fluid | Contents | When used | Watch out for |
|---|---|---|---|
| Normal Saline (NS) 0.9% | NaCl 154 mEq/L | Hypovolemia, hyponatremia | Hyperchloremic acidosis if large volumes |
| Dextrose 5% (D5W) | 50g glucose/L | Hypoglycemia, maintenance, drug diluent | NOT for hyponatremia |
| Ringer's Lactate (RL) | Na, K, Ca, lactate | Surgical patients, trauma, burns | Most physiological |
| DNS (Dextrose Normal Saline) | D5 + half NS | Maintenance fluids, pediatrics | Common in wards |
| Dextrose 10% (D10W) | 100g glucose/L | Severe hypoglycemia, neonates | Hyperglycemia |
How to read an IV order:
"1 pint NS over 6 hours" = 500 mL normal saline → drip rate = 500/6 = ~83 mL/hour
Drops/min = (Volume in mL × 20) ÷ (Time in minutes)
Signs that IV site needs to be changed:
- Redness, swelling, pain at cannula site = phlebitis → change site immediately
- Fluid not draining = blocked → flush gently or re-site
- Cannula sites should be changed every 72 hours routinely
SKILL 3 - Oxygen Therapy
Oxygen Delivery Devices:
| Device | Flow Rate | FiO2 delivered | Used when |
|---|---|---|---|
| Nasal cannula (prongs) | 1-6 L/min | 24-44% | Mild hypoxia, comfortable for patient |
| Simple face mask | 5-10 L/min | 35-55% | Moderate hypoxia |
| Non-rebreather mask (NRM) | 10-15 L/min | 60-90% | Severe hypoxia, emergency |
| Venturi mask | Fixed rates | Precise % (24%, 28%, 35%, 40%, 60%) | COPD patients (controlled O2) |
- Most patients: 94-98%
- COPD patients: 88-92% (too much O2 can suppress their drive to breathe)
SKILL 4 - Reading Drug Charts & Prescriptions
Parts of a Drug Chart:
Regular medications: given every day at set times
PRN (as needed): given only when patient asks or when certain condition met
One-time (STAT) dose: given immediately once
IV medications: separate section, with rate
Common Abbreviations on Drug Charts:
| Abbreviation | Meaning |
|---|---|
| OD / QD | Once daily |
| BD / BID | Twice daily |
| TDS / TID | Three times daily |
| QID | Four times daily |
| HS / ON | At night (hora somni) |
| AC | Before meals |
| PC | After meals |
| PRN / SOS | As needed |
| STAT | Immediately |
| SC | Subcutaneous |
| IM | Intramuscular |
| IV | Intravenous |
| PO | By mouth (oral) |
| SL | Sublingual (under tongue) |
| NGT | Through nasogastric tube |
SKILL 5 - Writing a Progress Note (SOAP Format)
Date: 24/06/2026    Time: 08:30    Day 3 of admission

S - Subjective (what the patient says):
"Patient reports reduced chest pain today. Still some breathlessness on exertion.
Slept well. Appetite improving."

O - Objective (what you find):
Vitals: T 37.2°C, P 88 bpm regular, BP 128/82, RR 18, SpO2 97% on room air
General: Alert, comfortable at rest
CVS: S1 S2 heard, no murmurs. JVP not raised.
RS: Clear air entry bilaterally, no crackles.
Abdomen: Soft, non-tender
Investigations: Today's Troponin 0.04 (down from 1.2 on admission). ECG: sinus rhythm, no new changes.

A - Assessment (your impression):
NSTEMI - clinically improving. Troponin trending down. Haemodynamically stable.

P - Plan:
Continue aspirin 75mg + clopidogrel 75mg + atorvastatin 40mg + ramipril 2.5mg
Urology review not needed
Echo ordered - pending
Plan for stress test before discharge
Discussed with Dr. [Senior name]
SKILL 6 - Recognizing a Sick Patient (ABCDE Emergency Approach)
| Step | Check | Action if abnormal |
|---|---|---|
| A - Airway | Can they speak? Gurgling/stridor? | Head tilt, jaw thrust, suction, call senior |
| B - Breathing | RR, SpO2, chest movement | High-flow O2, examine chest |
| C - Circulation | Pulse, BP, cap refill, cold limbs | IV access, fluid bolus, ECG |
| D - Disability | GCS, pupils, blood glucose | Check BGL (hypoglycemia is common!) |
| E - Exposure | Fever, rash, bleeding, drain output | Full exposure, check drug chart |
- SpO2 <90% despite O2
- BP <90/60 or falling
- HR <40 or >150
- GCS drop of >2 points
- Unresponsive patient
- New seizure
PART 3 - DEPARTMENT-SPECIFIC WARD KNOWLEDGE
🏥 GENERAL MEDICINE WARD
What you see here:
Most Common Admissions & What to Know:
1. Diabetic Patient in Ward
| Problem | BGL | Symptoms | Treatment |
|---|---|---|---|
| Hypoglycemia | <70 mg/dL | Sweating, trembling, confusion, palpitations | 15g sugar (juice/glucose) + recheck in 15 min |
| Hyperglycemia | >250 mg/dL | Polyuria, thirst, weakness | Insulin sliding scale or correction dose |
| DKA | Usually >300, with ketones | Fruity breath, deep breathing (Kussmaul), vomiting | IV fluids + insulin infusion (emergency!) |
| HHS | >600, NO ketones | Extreme dehydration, confusion, elderly | IV fluids slowly |
| Insulin | Onset | Duration | Given when |
|---|---|---|---|
| Regular/Actrapid (short-acting) | 30 min | 6-8 hours | Before meals or sliding scale |
| NPH (intermediate) | 1-2 hr | 12-18 hours | BD dosing |
| Glargine/Lantus (long-acting) | 1-2 hr | 24 hours | Once daily, basal |
2. Hypertensive Patient
- Target BP in ward: <140/90 (general), <130/80 (diabetic/CKD)
- Hypertensive emergency: BP >180/120 + end organ damage (headache, visual changes, confusion, chest pain) → IV labetalol or nitroprusside - call senior immediately
- Hypertensive urgency: BP >180/120, NO end organ damage → oral antihypertensives, reduce slowly over 24-48 hours
3. Fever in a Ward Patient
- Blood culture (2 sets from different sites, before antibiotics)
- Urine culture and sensitivity (C&S) + urine routine
- CXR
- CBC with differential (neutrophils up = bacterial, lymphocytes up = viral)
- Examine: IV sites, wound sites, chest, abdomen, legs (for DVT)
- Low grade: 37.5-38°C
- Moderate: 38-39°C
- High grade: >39°C
- Hyperpyrexia: >41°C (emergency - brain damage risk)
4. Stroke Patient in Medicine Ward
| Ischemic Stroke | Hemorrhagic Stroke | |
|---|---|---|
| Cause | Clot blocking artery | Blood vessel bursting |
| CT scan | Normal initially / later infarct | Bright white (blood) immediately |
| Treatment | tPA (thrombolysis) within 4.5 hours OR thrombectomy | BP control, neurosurgery review |
| Anticoagulation | YES (prevent recurrence) | NO (makes bleeding worse) |
- Neuro obs every 4-8 hours: GCS, pupils, limb power
- BP (target varies - don't over-lower in first 24 hours)
- Blood glucose (hyperglycemia worsens stroke)
- Swallow assessment before giving oral food/drugs (aspiration risk)
- DVT prophylaxis (compression stockings, heparin)
🔪 SURGERY WARD
What you see here:
Pre-Operative Patient (Before Surgery):
- Patient fasted? (6 hours for food, 2 hours for clear fluids)
- Consent signed?
- Blood group and cross-match done?
- Investigations: CBC, KFT, LFT, coagulation, ECG, CXR
- Allergies documented?
- Regular medications reviewed (hold metformin, warfarin, aspirin as instructed)
- IV access secured?
- Anaesthesia review done?
- Mark the site of surgery?
Post-Operative Patient (After Surgery):
| Time post-op | Cause | W |
|---|---|---|
| Day 1-2 | Wind - atelectasis (collapsed alveoli), pneumonia | Pulmonary |
| Day 3-5 | Water - UTI | Urinary |
| Day 5-7 | Wound infection | Wound |
| Day 5+ | Walking - DVT/PE | Venous |
| Anytime | Wonder drugs - drug fever | Drug/IV line |
- Vitals trend
- Pain score (0-10) - is analgesia adequate?
- Wound: dry and intact? Any ooze, redness, dehiscence?
- Drains: type, color, amount of output
- Urine output (catheter bag)
- Bowel sounds returned? Passing gas? (before allowing oral feeds)
- IV site clean?
- DVT prophylaxis ordered?
Surgical Drains - What You'll See:
| Drain type | Looks like | Used for | What to check |
|---|---|---|---|
| Corrugated (passive) | Flat rubber sheet | Wound dead space | Amount, color of fluid |
| Redivac/suction | Plastic bulb with vacuum | Enclosed spaces (breast, neck) | Collapse of bulb = working |
| Intercostal drain (ICD) | Tube in chest → water seal | Pneumothorax, hemothorax, effusion | Bubbling, swinging, amount |
| T-tube | T-shaped in bile duct | After cholecystectomy | Bile output |
| Ryle's tube (NG tube) | Tube through nose to stomach | Decompression, aspiration | Aspirate color, amount |
- Serous (clear/straw yellow) = normal wound fluid
- Serosanguinous (pink) = normal after surgery
- Sanguinous (frank blood) = active bleeding - call senior
- Purulent (cloudy/thick) = infection
- Bilious (green) = bile leak
- Chylous (milky white) = lymphatic leak
Wound Dressings - How to Assist:
- Wash hands, gloves on (sterile for clean wounds)
- Remove old dressing - note: wet? soiled? adherent?
- Clean wound with saline or antiseptic (per surgeon's instruction)
- Inspect wound: is it healing? Any dehiscence (opening), infection, necrosis?
- Apply new dressing
- Document wound appearance in notes
- Primary intention: edges closed (sutured) - clean surgical wounds
- Secondary intention: left open to heal from base - infected/large wounds
- Tertiary (delayed primary): cleaned first, then closed later
👶 PEDIATRICS WARD
The key difference: everything depends on AGE and WEIGHT
Calculating Drug Doses in Children:
- Age 1-10 years: Weight (kg) = (Age + 4) × 2
- e.g., 6-year-old: (6+4) × 2 = 20 kg
Common Pediatric Ward Problems:
Fever in a Child
- Simple: <15 min, one episode, no focal features → benign, good prognosis
- Complex: >15 min, focal, repeated → investigate for meningitis
- Immediate management: ABC, position (lateral), diazepam if >5 min (0.5 mg/kg PR or IV 0.2-0.3 mg/kg)
Dehydration in Children
| Degree | % body weight lost | Signs |
|---|---|---|
| Mild | <5% | Slightly dry mouth, normal eyes, normal skin turgor |
| Moderate | 5-10% | Sunken eyes, reduced skin turgor, tachycardia |
| Severe | >10% | Sunken fontanelle, very dry, no tears, weak/absent pulse |
- Deficit = % dehydration × weight × 10 mL/kg
- Plus maintenance fluids per day (Holliday-Segar rule):
- 0-10 kg: 100 mL/kg/day
- 10-20 kg: 1000 mL + 50 mL/kg for each kg above 10
-
20 kg: 1500 mL + 20 mL/kg for each kg above 20
Jaundice in Newborn (Neonatal Jaundice)
- Physiological: Appears day 2-3, gone by day 14 in term, day 21 in preterm - normal
- Pathological: Appears <24 hours OR persists >14 days OR bilirubin very high → treat
- Treatment: Phototherapy (blue light breaks down bilirubin through skin)
- Severe: Exchange transfusion (double-volume blood exchange)
Common Pediatric Presentations Table:
| Condition | Age | Key signs | First thing to do |
|---|---|---|---|
| Bronchiolitis | <2 years | Wheeze, tachypnea, feeding difficulty | O2, hydration, supportive care |
| Croup | 6 months-3 years | Barking cough, stridor (inspiratory) | Dexamethasone 0.6 mg/kg oral/IM |
| Epiglottitis | 2-7 years | Drooling, tripod position, high fever, muffled voice | DON'T examine throat - secure airway first |
| Intussusception | 3 months-6 years | Colicky pain, current jelly stool, sausage-shaped mass | USS abdomen - air enema reduction |
| Meningitis | Any | Neck stiffness, photophobia, petechial rash, bulging fontanelle | LP + antibiotics ASAP |
🤰 OBG WARD (Obstetrics & Gynecology)
Obstetrics Section:
| Measurement | How often | Normal | Alarm |
|---|---|---|---|
| BP | Every visit | <140/90 | >140/90 after 20 weeks = preeclampsia |
| Urine dipstick | Every visit | No protein, no glucose | Proteinuria = preeclampsia risk |
| Fundal height | Every visit | = weeks of pregnancy (cm) | Too small = IUGR, too big = twins/polyhydramnios |
| Fetal heart rate (FHR) | Every visit | 110-160 bpm | <110 or >160 = fetal distress |
| Edema | Every visit | Mild ankle ok | Facial/generalized = preeclampsia |
- G = Gravida (total pregnancies including current)
- P = Para (deliveries >28 weeks)
- A/L = Abortions/Live births
- Example: G3P2A1 = 3 pregnancies, 2 deliveries, 1 abortion
- 1st: 0-13 weeks (organogenesis - MOST drug-sensitive)
- 2nd: 14-26 weeks (growth phase)
- 3rd: 27-40 weeks (preparation for birth)
| Emergency | Signs | Immediate action |
|---|---|---|
| Eclampsia | Seizure in pregnant/postpartum woman | MgSO4 4g IV loading dose, airway, O2 |
| PPH | >500mL blood loss after vaginal delivery | Fundal massage, oxytocin 10 IU IM, IV access |
| Cord prolapse | Cord visible/felt at cervix | Head down position, push presenting part up, emergency C-section |
| Placenta previa | Painless bright red bleeding | No vaginal exam! IV access, crossmatch, emergency C-section |
| Placental abruption | Painful dark bleeding, rigid uterus | IV access, fetal monitoring, possible C-section |
Gynecology Section:
- Ectopic pregnancy (always check pregnancy test in female of reproductive age with pelvic pain)
- PID (pelvic inflammatory disease)
- Ovarian cyst - torsion or rupture
- Uterine fibroid with bleeding
- Post-operative hysterectomy/myomectomy
🦴 ORTHOPEDICS WARD
- 5 P's: Pain (out of proportion = compartment syndrome!) | Pallor | Paresthesia | Paralysis | Pulselessness
- Any of these = emergency - compartment syndrome or vascular injury
- Classic: Pain out of proportion to injury, pain on passive stretch, tense swollen limb
- Check weights are hanging freely
- Limb in correct position
- Skin under traction device - pressure sores?
- All hip/knee replacement patients → low molecular weight heparin (enoxaparin) + compression stockings
- Early mobilization encouraged
👁️ ENT WARD
- Bleeding (primary = within 24 hours, secondary = days 5-10) → emergency return to OR
- Pain score, able to swallow
- No hot drinks/spicy food for 2 weeks
- Tie/flange secure (2-finger gap)
- Inner tube cleaned every 4-8 hours
- Suction PRN
- Always have same-size spare tube at bedside
- Emergency: tube blocked → remove inner tube → if still blocked → deflate cuff → if still blocked → remove tube → ventilate via stoma
- Sit forward, breathe through mouth
- Pinch soft part of nose for 10 minutes continuous
- If not stopped: anterior nasal packing (Merocel/BIPP)
- Posterior bleed: posterior packing, ENT review
🧠 NEUROLOGY / NEUROSURGERY WARD
Neuro Obs (Neurological Observations):
- GCS (E+V+M, max 15)
- Pupils: Size (mm), equality, reaction to light (PEARL = Pupils Equal And Reactive to Light)
- Limb power: Grade 0-5 each limb
- Temperature, BP, pulse
- Hypertension (high BP)
- Bradycardia (slow heart rate)
- Irregular breathing (Cheyne-Stokes) → This is a pre-terminal sign - call senior immediately
- Patient in lateral decubitus (fetal position) or seated leaning forward
- Level: L3-L4 or L4-L5 (below spinal cord ending at L1-L2)
- Normal CSF: Clear, opening pressure 6-20 cmH2O
| CSF finding | Bacterial meningitis | Viral meningitis | TB meningitis |
|---|---|---|---|
| Appearance | Turbid/cloudy | Clear | Slightly turbid |
| Cells | PMNs (thousands) | Lymphocytes (hundreds) | Lymphocytes |
| Protein | Very high (>1g/L) | Mildly elevated | High |
| Glucose | Very low (<1/2 blood) | Normal | Low |
| Gram stain | Positive | Negative | AFB (sometimes) |
PART 4 - PRACTICAL PROCEDURES (Watch Then Assist)
| Procedure | What it is | What to prepare |
|---|---|---|
| IV cannulation | Insert IV line | Gloves, tourniquet, IV cannula (18-20G usually), flush, dressing |
| Venipuncture | Blood sample | Gloves, tourniquet, needle, correct colored tubes |
| NG tube insertion | Tube through nose to stomach | NGT (10-16 Fr), lubricant, stethoscope, 20mL syringe |
| Urinary catheterization | Foley catheter into bladder | Sterile kit, appropriate size catheter (14-16 Fr for adults) |
| Pleural tap (thoracocentesis) | Drain fluid from chest | Large syringe, wide-bore needle, USS guidance ideally |
| Ascitic tap | Drain fluid from abdomen | Like pleural tap but abdomen, USS guidance |
| Blood transfusion | Give packed red cells | Crossmatch done, blood group checked, consent, pre-transfusion vitals |
Blood Transfusion - Safety Steps (MUST follow every time):
- Two nurses check at bedside: patient name, hospital number, blood group, expiry date
- Check for patient identity band - matches blood product label
- Take pre-transfusion baseline vitals
- Each unit runs over 4 hours (unless emergency)
- Check vitals 15 min after starting (most reactions happen early)
| Reaction | When | Signs | Action |
|---|---|---|---|
| Febrile non-hemolytic | During/after | Fever, chills | Stop transfusion briefly, paracetamol, restart slowly |
| Allergic/urticarial | During | Rash, itch | Stop, chlorphenamine (antihistamine) |
| Anaphylaxis | Immediately | Hypotension, wheeze, rash | Stop immediately, adrenaline 0.5mg IM, call senior |
| ABO incompatibility (hemolytic) | First 15 min | Fever, loin pain, hemoglobinuria (red urine), shock | Stop immediately - life-threatening |
PART 5 - DISCHARGE PLANNING (Happens in All Wards)
| Task | Who does it | You can help with |
|---|---|---|
| Discharge summary written | Doctor | Draft on paper for review |
| Medications prescribed for home | Doctor | Check drug names and doses |
| Follow-up appointment booked | Ward clerk / you | Know which OPD to refer to |
| Patient educated | Nurse + Doctor | Explain what to expect at home |
| Red flags explained | Doctor | When to come back to ER |
| Referrals made | Doctor | Physio, OT, social worker if needed |
THE MASTER CHECKLIST - For Every Patient, Every Day
BEFORE ROUNDS:
□ Check vitals chart (last 24 hours)
□ Check urine output
□ Check input/output balance
□ Read nursing notes for overnight events
□ Know today's investigation results

ON ROUNDS:
□ Present patient in SOAP format
□ Know what's being planned for today
□ Write down any new orders or changes

AFTER ROUNDS:
□ Note down 1 new thing you learned
□ Ask "what does this finding/result mean?"
□ Look up any term you didn't understand

END OF DAY:
□ Update your progress note
□ Check evening vitals
□ Confirm handover done
QUICK EMERGENCY REFERENCE - Stick This on Your Pocket Card
PATIENT SUDDENLY DETERIORATES:
→ ABCDE approach
→ Call senior immediately
→ High-flow O2 via non-rebreather mask
→ IV access × 2, blood tests
→ ECG, CXR, ABG

HYPOGLYCEMIA (<70 mg/dL):
→ 15g glucose (3 glucose tablets / 150mL juice)
→ Recheck in 15 min
→ If unconscious: 25mL of 50% dextrose IV

ANAPHYLAXIS:
→ Stop trigger, call help
→ Adrenaline 0.5mg IM (lateral thigh)
→ O2 high flow, IV access, fluids

SEIZURE:
→ Position safely, lateral
→ Time it
→ Diazepam if >5 minutes
→ Check glucose

CARDIAC ARREST:
→ Shout for help + call crash team
→ Start CPR: 30 compressions : 2 breaths
→ Get defibrillator
→ Do not stop until team arrives
General medicine
🏥 GENERAL MEDICINE - Complete Ward Guide
Everything You Need to Know | Condition by Condition
WHO YOU WILL SEE IN GENERAL MEDICINE
| System | Common Conditions |
|---|---|
| Metabolic | Diabetes (DKA, HHS, hypoglycemia), thyroid disease |
| Cardiovascular | Hypertension, heart failure, MI (see Cardiac module) |
| Respiratory | Pneumonia, TB, COPD, asthma, pleural effusion |
| Infectious | Dengue, typhoid, malaria, UTI, cellulitis, sepsis |
| GI/Liver | Jaundice, hepatitis, cirrhosis, GI bleed |
| Renal | Acute kidney injury, UTI, nephrotic syndrome |
| Blood | Anemia (all types), thrombocytopenia |
| Neuro | Stroke, meningitis, seizures |
| Electrolytes | Hyponatremia, hyperkalemia |
CONDITION 1 - DIABETES MELLITUS
Two Main Types:
| Type 1 | Type 2 | |
|---|---|---|
| Cause | Autoimmune - no insulin production | Insulin resistance + relative deficiency |
| Age | Usually <30 years | Usually >40 years (but rising in young) |
| Build | Thin | Often overweight/obese |
| Onset | Acute (days) | Gradual (years) |
| Needs insulin | Yes, always | Initially no, later may need |
| Ketones | Yes (prone to DKA) | Rarely |
Diagnosis (WHO Criteria):
| Test | Normal | Pre-diabetes | Diabetes |
|---|---|---|---|
| Fasting glucose | <100 mg/dL | 100-125 | ≥126 mg/dL |
| Random glucose | <140 | 140-199 | ≥200 mg/dL |
| 2h post 75g glucose (OGTT) | <140 | 140-199 | ≥200 |
| HbA1c | <5.7% | 5.7-6.4% | ≥6.5% |
Symptoms of Diabetes ("PUPIL"):
- Polyuria (passing lot of urine)
- Unaccountable weight loss
- Polydipsia (excessive thirst)
- Infections - recurrent (skin, urine, fungal)
- Lethargy / fatigue
Monitoring in Ward:
- 4-point BGL: fasting, pre-lunch, pre-dinner, bedtime
- Target in hospital: 140-180 mg/dL (less strict than outpatient targets)
- HbA1c every 3 months outpatient
Diabetes Emergencies - The Big 3:
1. Hypoglycemia (BGL <70 mg/dL)
- Mild: Sweating, trembling, palpitations, hunger, anxiety
- Moderate: Confusion, slurred speech, headache
- Severe: Seizure, loss of consciousness
- If conscious: 15g fast-acting carbs (150 mL juice / 3-4 glucose tablets / 1 tbsp sugar)
- Wait 15 minutes, recheck
- If still <70: repeat
- If unconscious/unable to swallow: 25-50 mL 50% dextrose IV (D50W) OR glucagon 1mg IM
- Once recovered: give snack with complex carbs to prevent recurrence
- Find and fix the CAUSE
2. DKA - Diabetic Ketoacidosis (Type 1 mainly)
- BGL usually >250 mg/dL (but can be lower in "euglycemic DKA")
- Nausea, vomiting, abdominal pain
- Kussmaul breathing (deep, labored - blowing off CO2)
- Fruity/acetone smell on breath
- Dehydration, confusion, drowsiness
| Pillar | What to give | Watch for |
|---|---|---|
| 1. Fluids | Normal saline 1L in first hour, then 250-500 mL/hr | Fluid overload in elderly |
| 2. Insulin | Insulin infusion 0.1 unit/kg/hour | Don't drop glucose too fast |
| 3. Potassium | Add KCl to fluids when K+ <5.5 (insulin drives K into cells → hypokalemia) | NEVER give insulin if K+ <3.5 first |
| 4. Treat cause | Antibiotics if infection, etc. |
3. HHS - Hyperosmolar Hyperglycemic State (Type 2 mainly)
Diabetic Complications - Know These:
| Complication | What it is | How to detect |
|---|---|---|
| Retinopathy | Damaged retinal blood vessels | Annual fundoscopy |
| Nephropathy | Kidney damage | Urine microalbumin, creatinine |
| Neuropathy | Nerve damage - numbness/pain in feet | Monofilament test, vibration sense |
| Macrovascular | Heart attack, stroke, peripheral artery disease | ECG, ankle-brachial index |
| Diabetic foot | Infection + ischemia + neuropathy | Foot inspection every visit |
CONDITION 2 - HYPERTENSION
Definition: BP ≥140/90 mmHg on 2+ separate readings
Classification:
| Category | Systolic | Diastolic | Action |
|---|---|---|---|
| Normal | <120 | <80 | Lifestyle |
| Elevated | 120-129 | <80 | Lifestyle |
| Stage 1 | 130-139 | 80-89 | Lifestyle ± drug |
| Stage 2 | ≥140 | ≥90 | Drug + lifestyle |
| Hypertensive urgency | >180 | >120 | Oral drugs, hours |
| Hypertensive emergency | >180 | >120 + end organ damage | IV drugs, ICU |
Asking About Secondary Hypertension (5% of cases):
- Headache, sweating, palpitations in episodes? → Pheochromocytoma
- Weakness, low potassium? → Hyperaldosteronism (Conn's syndrome)
- Snoring, daytime sleepiness? → Obstructive sleep apnea
- Young female, flank bruit? → Renal artery stenosis
- Coarctation: radio-femoral delay, leg claudication
Target Organ Damage - "BRAIN-HEART-KIDNEY-EYE":
| Organ | Damage |
|---|---|
| Brain | Stroke, hypertensive encephalopathy (headache + confusion + papilledema) |
| Heart | LVH (ECG shows tall R in aVL + deep S in V3 sum >28mm), IHD, heart failure |
| Kidney | Proteinuria → CKD |
| Eye | Hypertensive retinopathy (grades 1-4: AV nipping → flame hemorrhages → papilledema) |
Treatment - Drug Choice:
| Patient type | First choice drug | Reason |
|---|---|---|
| Young, white | ACEi (Ramipril) | RAAS dominant |
| Elderly/black | CCB (Amlodipine) | Volume/Ca channel dominant |
| With diabetes/CKD | ACEi or ARB | Renoprotective |
| With heart failure | ACEi + beta-blocker | Proven mortality benefit |
| With angina | Beta-blocker + CCB | |
| With fluid overload | Thiazide or loop diuretic | |
| Pregnant | Methyldopa, Labetalol, Nifedipine | ACEi/ARB contraindicated |
Hypertensive Emergency vs Urgency:
| Emergency | Urgency | |
|---|---|---|
| BP | >180/120 | >180/120 |
| End organ damage | YES (brain/heart/kidney/eye) | NO |
| Treatment | IV drugs in ICU (labetalol, nitroprusside) | Oral drugs, reduce over 24-48h |
| Target | Reduce MAP by 25% in first hour | Reduce slowly over 24-48h |
CONDITION 3 - PNEUMONIA
Community-Acquired Pneumonia (CAP) - Most Common Type
- Fever, rigors (uncontrollable shaking)
- Productive cough - rusty/yellow/green sputum
- Pleuritic chest pain (sharp, worse on breathing)
- Breathlessness
- Reduced breath sounds + dullness + bronchial breathing on the affected side
| Organism | Clue |
|---|---|
| Streptococcus pneumoniae | Most common, rusty sputum, lobar consolidation |
| Haemophilus influenzae | COPD patients |
| Atypical (Mycoplasma, Legionella, Chlamydia) | Young adults, dry cough, headache, diarrhea, confusion, CXR worse than exam suggests |
| Staphylococcus aureus | Post-influenza, IV drug users, cavitating pneumonia |
| Klebsiella | Alcoholics, currant jelly sputum |
- CXR: consolidation (white area in lung)
- CBC: raised WBC (neutrophilia = bacterial)
- Blood cultures: 2 sets before antibiotics
- Sputum for C&S
- ABG if SpO2 <94% or unwell
- Urine Legionella antigen (if atypical suspected)
- Confusion (new)
- Urea >7 mmol/L (BUN >20 mg/dL)
- Respiratory rate ≥30/min
- Blood pressure <90 systolic or <60 diastolic
- Age ≥65
| Score | Severity | Management |
|---|---|---|
| 0-1 | Low risk | Outpatient oral antibiotics |
| 2 | Moderate | Consider hospital admission |
| 3-5 | Severe | ICU consideration |
- Non-severe: Amoxicillin 500mg TDS oral (or Amoxicillin-clavulanate)
- Add azithromycin/doxycycline if atypical suspected
- Severe: IV co-amoxiclav + IV azithromycin
- Follow local antibiogram for your hospital
CONDITION 4 - TUBERCULOSIS (TB)
Extremely Common in South Asia, Africa, Southeast Asia
- Fever - low-grade, worse in evenings
- Night sweats
- Weight loss (significant, unintentional)
- Swelling - lymph nodes (cervical mainly)
- Weakness, anorexia
- Cough >3 weeks, hemoptysis
| Type | Site | Notes |
|---|---|---|
| Pulmonary TB | Lung | Most common, infectious, CXR: upper lobe cavities + consolidation |
| TB Lymphadenitis | Lymph nodes | Most common extrapulmonary |
| TB Meningitis | Brain/meninges | Most dangerous, CSF lymphocytes + very low glucose |
| TB Peritonitis | Abdomen | Ascites + constitutional symptoms |
| Miliary TB | Throughout body (blood spread) | Millet-seed shadows on CXR, very ill patient |
- Sputum AFB smear (3 samples - early morning preferred)
- GeneXpert MTB/RIF (rapid PCR - gold standard for quick diagnosis, also detects rifampicin resistance)
- Sputum culture (takes 6-8 weeks but gold standard)
- CXR: upper lobe infiltrates, cavities, hilar lymphadenopathy
- Mantoux/TST: positive = ≥10mm induration in 48-72 hrs (≥5mm in immunocompromised)
| Phase | Duration | Drugs | Mnemonic |
|---|---|---|---|
| Intensive phase | 2 months | HINH + Rifampicin + Pyrazinamide + Ethambutol | "2HRZE" |
| Continuation phase | 4 months | HINH + Rifampicin | "4HR" |
- Rifampicin: Orange-red urine/tears (warn patient - NORMAL), hepatotoxicity
- INH: Peripheral neuropathy (give pyridoxine/B6 with it), hepatotoxicity
- Pyrazinamide: Gout (raises uric acid), hepatotoxicity
- Ethambutol: Color blindness (red-green), vision changes
CONDITION 5 - DENGUE FEVER
Very Common in Tropical Countries
| Phase | When | Features |
|---|---|---|
| Febrile | Day 1-3 | High fever (up to 40°C), severe headache, retro-orbital (behind eye) pain, bone/joint pain ("breakbone fever"), rash |
| Critical | Day 4-6 | Fever may drop - THIS IS DANGEROUS - plasma leakage → shock, bleeding |
| Recovery | Day 7-10 | Fever resolves, platelet count recovers, bradycardia common |
| Type | Features |
|---|---|
| Dengue Fever | Fever + severe headache + myalgia + arthralgia + rash - self-limited |
| Dengue Hemorrhagic Fever (DHF) | + Plasma leakage (pleural effusion, ascites) + thrombocytopenia + hemorrhagic tendency |
| Dengue Shock Syndrome (DSS) | DHF + circulatory shock - emergency! |
- NS1 antigen: positive day 1-5 (early)
- IgM antibody: positive after day 5
- CBC: leukopenia (low WBC), thrombocytopenia (platelet <100,000 = concern, <20,000 = risk of major bleed)
- Rising hematocrit (Hct) = hemoconcentration = plasma leakage happening
- Abdominal pain or tenderness
- Persistent vomiting
- Clinical fluid accumulation (ascites, pleural effusion)
- Mucosal bleeding (gums, epistaxis, melena)
- Lethargy or restlessness
- Liver enlargement >2 cm
- Rapid increase in Hematocrit + rapid fall in platelet
- NO specific antiviral
- Supportive: IV fluids (Ringer's Lactate preferred), strict fluid balance
- NO aspirin, NO NSAIDs (both increase bleeding risk)
- Paracetamol for fever only
- Monitor platelet and Hct every 6-12 hours
- Platelet transfusion only if <10,000 OR <20,000 with bleeding
CONDITION 6 - ANEMIA
Definition: Hb <13 g/dL (men) / <12 g/dL (women) / <11 g/dL (pregnancy)
Classify First - By MCV (Mean Corpuscular Volume):
Microcytic (MCV <80 fL) - Small red cells:
| Cause | Clue | Treatment |
|---|---|---|
| Iron deficiency | Most common worldwide; koilonychia, glossitis, pallor, pica | Ferrous sulfate 200mg TDS for 3 months (continue 3 months after Hb normalizes) |
| Thalassemia | Mediterranean/South Asian origin, family history, splenomegaly | No iron! (it accumulates); transfusion-dependent |
| Anemia of chronic disease | Rheumatoid arthritis, TB, malignancy, CKD | Treat underlying cause |
| Sideroblastic | Rare; ring sideroblasts on bone marrow | Pyridoxine |
Normocytic (MCV 80-100 fL) - Normal sized cells:
| Cause | Clue |
|---|---|
| Anemia of chronic disease | As above |
| Acute blood loss | Recent bleed, low BP, tachycardia |
| Hypothyroidism | Weight gain, cold intolerance, bradycardia |
| Hemolytic anemia | Jaundice + anemia + splenomegaly; raised LDH, reduced haptoglobin |
| CKD | Creatinine elevated; lack of EPO production |
Macrocytic (MCV >100 fL) - Large red cells:
| Cause | Clue | Treatment |
|---|---|---|
| Vitamin B12 deficiency | Vegan diet, elderly, gastrectomy, pernicious anemia; peripheral neuropathy (subacute combined degeneration) | B12 IM injections (1000 mcg alternate days × 2 weeks, then monthly) |
| Folate deficiency | Poor diet, pregnancy, malabsorption, alcoholism, methotrexate | Folic acid 5mg OD daily |
| Alcohol | Large cells without anemia even | Abstinence |
| Hypothyroidism | Same as normocytic cause | Thyroxine |
| Liver disease | Treat underlying |
Blood Film - What to Look For:
| Finding | Condition |
|---|---|
| Hypochromic microcytes | Iron deficiency |
| Target cells | Thalassemia, liver disease |
| Hypersegmented neutrophils (>5 lobes) | B12/folate deficiency |
| Sickle cells | Sickle cell disease |
| Schistocytes (fragmented cells) | TTP, HUS, DIC, prosthetic valve |
| Spherocytes | Hereditary spherocytosis, autoimmune hemolysis |
| Malaria parasites (ring forms) | Malaria! |
CONDITION 7 - ACUTE KIDNEY INJURY (AKI)
Definition (KDIGO Criteria): Any ONE of:
- Rise in creatinine ≥0.3 mg/dL within 48 hours
- Rise in creatinine ≥1.5× baseline within 7 days
- Urine output <0.5 mL/kg/hour for ≥6 hours
Classify by Cause:
| Type | Cause | Clue | Urine Na |
|---|---|---|---|
| Pre-renal | Dehydration, blood loss, low BP, heart failure | Thirsty, dry, no urine, raised urea:creatinine ratio >20:1 | Low (<20 mEq/L) |
| Intrinsic renal | Glomerulonephritis, ATN (drugs, contrast, sepsis), interstitial nephritis | Muddy brown casts in urine (ATN) | High (>40 mEq/L) |
| Post-renal | Obstruction - BPH, stone, pelvic cancer | Palpable bladder, bilateral hydronephrosis on USS | Variable |
Investigations in AKI:
- Serum creatinine, urea, electrolytes
- Urine output monitoring (strict hourly in severe AKI)
- Urinalysis + microscopy (casts, protein, blood)
- Renal ultrasound (rule out obstruction)
- ABG (look for metabolic acidosis)
- Urine Na, urine osmolality (pre vs intrinsic)
Life-Threatening Complications of AKI ("AEIOU"):
- Acidosis - treat with bicarbonate if severe
- Electrolytes - hyperkalemia (most dangerous!)
- Ingestion (toxins/drugs that worsen renal function - stop nephrotoxics)
- Overload (fluid overload → pulmonary edema)
- Uremia symptoms (encephalopathy, pericarditis, platelet dysfunction)
Hyperkalemia in AKI - Treatment Sequence:
- Peaked/tall T waves (first sign)
- Widened QRS
- Sine-wave pattern → cardiac arrest
| Step | Drug | Action | How fast |
|---|---|---|---|
| Calcium | 10 mL 10% calcium gluconate IV | Stabilizes cardiac membrane | Immediate, 2-3 min |
| Bicarbonate | NaHCO3 IV | Shifts K into cells | 15-30 min |
| Dextrose + Insulin | 25mL 50% dextrose + 10 units actrapid IV | Shifts K into cells | 30-60 min |
| Inhaled salbutamol | 10-20mg nebulised | Shifts K into cells | 30 min |
| Gut: Resonium | Calcium resonium oral/PR | Removes K from body | Hours |
| Dialysis | If refractory or renal failure | Removes K | Definitive |
Pre-renal AKI Management:
- IV fluid challenge: 500mL NS/RL over 30 min, reassess
- Monitor urine output hourly
- Stop nephrotoxic drugs (NSAIDs, aminoglycosides, contrast, ACEi temporarily)
- Treat underlying cause (sepsis, heart failure)
CONDITION 8 - LIVER DISEASE / JAUNDICE
Classify Jaundice:
| Type | Site of problem | Bilirubin | Urine | Stool | LFTs |
|---|---|---|---|---|---|
| Pre-hepatic | Excess hemolysis | Unconjugated (indirect) ↑ | Normal (no bilirubin in urine) | Normal | ALP, ALT normal |
| Hepatic | Liver cell damage | Both ↑ | Dark (bilirubin present) | Pale | ALT/AST very high |
| Post-hepatic (obstructive) | Bile duct blockage | Conjugated (direct) ↑ | Dark + frothy | Clay/pale | ALP very high, ALT mildly |
Causes to Know:
| Pre-hepatic | Hepatic | Post-hepatic |
|---|---|---|
| Malaria | Viral hepatitis (A,B,C,E) | Gallstones (choledocholithiasis) |
| Sickle cell | Alcoholic hepatitis | Pancreatic cancer |
| Hereditary spherocytosis | Drug-induced (paracetamol, TB drugs, statins) | Cholangiocarcinoma |
| Cirrhosis | Strictures | |
| Leptospirosis |
Cirrhosis - Complications to Recognize in Ward:
| Complication | Signs | Management |
|---|---|---|
| Ascites | Distended abdomen, shifting dullness, fluid thrill | Low salt diet, spironolactone 100mg OD, furosemide 40mg OD; large volume: therapeutic tap |
| Spontaneous Bacterial Peritonitis (SBP) | Fever + abdominal pain + new ascites in cirrhotic | Diagnostic tap (PMN >250/mm³) → IV cefotaxime 2g TDS |
| Hepatic encephalopathy | Confusion, asterixis (flapping tremor), fetor hepaticus (musty smell) | Lactulose (3 times daily, aim 2-3 soft stools/day), rifaximin; find precipitant (infection, GI bleed, constipation, drugs) |
| Variceal bleeding | Hematemesis in cirrhotic, signs of portal HTN | IV terlipressin, endoscopy for banding, beta-blocker prophylaxis |
| Hepatorenal syndrome | AKI in cirrhotic with no other cause, no response to fluids | Terlipressin + albumin, dialysis if needed |
Hepatitis:
| Type | Route | Acute/Chronic | Vaccine |
|---|---|---|---|
| Hepatitis A | Fecal-oral (contaminated food/water) | Acute only (no chronic) | YES |
| Hepatitis B | Blood, sexual, vertical (mother-child) | Acute + can become chronic | YES |
| Hepatitis C | Blood (transfusion, needles) | Often chronic → cirrhosis → cancer | NO (but DAAs can cure it) |
| Hepatitis D | Only with Hep B (needs HBsAg) | Chronic | Hep B vaccine covers |
| Hepatitis E | Fecal-oral | Usually acute, dangerous in pregnancy | Available in some countries |
CONDITION 9 - ASTHMA & COPD
Asthma:
- RR >25/min
- HR >110 bpm
- Unable to complete sentences
- SpO2 <92%
- PEFR 33-50% of best
- Silent chest (no wheeze - air entry very poor - extreme danger)
- SpO2 <92%
- Exhaustion
- PaCO2 normal or raised (patient too tired to hyperventilate)
- O2 to target SpO2 94-98%
- Nebulized salbutamol 5mg + ipratropium 0.5mg back-to-back
- Systemic steroids: prednisolone 40mg oral or hydrocortisone 100mg IV
- Magnesium sulfate 2g IV (if severe/life-threatening)
- IV salbutamol or aminophylline (ICU if needed)
COPD (Chronic Obstructive Pulmonary Disease):
| Asthma | COPD | |
|---|---|---|
| Age | Any | Usually >40 |
| Cause | Allergy/atopy | Smoking |
| Reversibility | Full reversal | Incomplete |
| Symptoms | Variable | Progressive, persistent |
| Sputum | Clear/white | Often purulent during exacerbation |
- Increased breathlessness + increased sputum + change in sputum color
- O2 target: 88-92% (not >94% - hypercapnic drive)
- Controlled O2 via Venturi mask (24% or 28%)
- Nebulized salbutamol + ipratropium
- Prednisolone 30mg × 5 days
- Antibiotics if infective exacerbation (amoxicillin or doxycycline)
- ABG to check CO2 (rising CO2 + acidosis = BiPAP needed)
CONDITION 10 - SEPSIS
Definition: Life-threatening organ dysfunction caused by dysregulated host response to infection
- RR ≥22/min
- Altered mental status (GCS <15)
- Systolic BP ≤100 mmHg
Septic Shock:
- Sepsis + need for vasopressors to maintain MAP ≥65 mmHg + serum lactate >2 mmol/L
Sepsis Six (Do ALL within 1 hour):
| Action | |
|---|---|
| 1 | Give O2 (target SpO2 >94%) |
| 2 | Take blood cultures (2 sets) |
| 3 | Give IV antibiotics (broad-spectrum, within 1 hour of diagnosis) |
| 4 | Give IV fluid bolus (30 mL/kg crystalloid if hypotensive/high lactate) |
| 5 | Monitor urine output (catheterize if needed) |
| 6 | Check lactate (>4 = very severe) |
- Piperacillin-tazobactam (Tazocin) 4.5g TDS IV
- Or ceftriaxone 2g OD IV
- Add metronidazole if abdominal source suspected
CONDITION 11 - ELECTROLYTE DISTURBANCES
Hyponatremia (Na+ <135 mEq/L)
| Type | Volume status | Cause |
|---|---|---|
| Hypovolemic hyponatremia | Dry patient | Vomiting, diarrhea, diuretics |
| Euvolemic hyponatremia | Normal volume | SIADH (low Na, low urine Na, high urine osmolality) |
| Hypervolemic hyponatremia | Oedematous patient | Heart failure, cirrhosis, nephrotic syndrome |
- Hypovolemic: Normal saline fluids
- SIADH: Fluid restriction (1000 mL/day), treat cause
- NEVER correct Na faster than 8-10 mEq/L per 24 hours - risk of osmotic demyelination syndrome (brain damage)
Hyperkalemia (K+ >5.5 mEq/L)
Hypokalemia (K+ <3.5 mEq/L)
- Oral: KCl (Slow-K) 600mg TDS if mild and patient eating
- IV: Add KCl 40 mEq to 1L NS/RL over 4 hours - NEVER push IV potassium (causes cardiac arrest)
- Max IV rate: 20 mEq/hour via peripheral line (40 mEq/hour only in ICU with monitoring)
DAILY CLINICAL APPROACH IN GENERAL MEDICINE WARD
The Morning Pre-Round Checklist (Do For Each Patient):
PATIENT: _______________  Day ___ of admission
Diagnosis: _______________

VITALS (last 24h):
□ Max Temp: ___  (fever still present?)
□ Pulse: ___  (tachycardia / bradycardia?)
□ BP: ___  (controlled? high? low?)
□ RR: ___  (tachypneic?)
□ SpO2: ___  (on how much O2?)
□ BGL: ___ (if diabetic)

INPUT/OUTPUT:
□ IV fluids in: ___
□ Urine out: ___  (adequate? >0.5 mL/kg/hr?)

RESULTS:
□ Today's blood tests: ___
□ Imaging: ___
□ Cultures pending? Yes / No

MEDICATIONS:
□ IV antibiotics – correct dose and timing?
□ Any drug reviews needed?

PLAN TODAY:
□ Change IV to oral antibiotics?
□ New investigation needed?
□ Consultation needed?
□ Discharge planning?
IMPORTANT INVESTIGATIONS QUICK REFERENCE
What Each Lab Test Tells You:
| Test | Normal | What to think when abnormal |
|---|---|---|
| WBC | 4-11 × 10³ | High + neutrophilia → bacterial; High + lymphocytes → viral; Very high → leukemia |
| Hb | M: 13-17, F: 12-15 g/dL | Low → anemia; check MCV, retics |
| Platelet | 1.5-4 lakh/μL | Low → dengue, ITP, sepsis, DIC; Very low (<20,000) → bleeding risk |
| ESR | <20 (M), <30 (F) | Raised → infection, inflammation, malignancy |
| CRP | <5 mg/L | Raised → acute inflammation, bacterial > viral |
| Serum creatinine | 0.6-1.2 mg/dL | High → AKI or CKD |
| Serum Na | 136-145 mEq/L | Low → SIADH, dehydration, heart failure |
| Serum K | 3.5-5.0 mEq/L | High → AKI, ACEi; Low → diuretics, vomiting |
| ALT/AST | <40 U/L | High (>3×) → hepatitis, liver injury |
| ALP | 44-147 U/L | High → cholestasis, bone disease |
| Total bilirubin | <1.2 mg/dL | High → jaundice; direct vs indirect |
| Albumin | 3.5-5.0 g/dL | Low → malnutrition, liver disease, nephrotic |
| CK/CPK | <200 U/L | Very high → rhabdomyolysis, MI, myositis |
| Lactate | <2 mmol/L | High → sepsis, ischemia, poor perfusion |
| D-dimer | <500 ng/mL | Elevated in DVT/PE but also infection/malignancy |
GENERAL MEDICINE WARD - TOP DRUGS YOU'LL SEE EVERY DAY
| Drug | Used for | Key point |
|---|---|---|
| Paracetamol 500mg-1g | Fever, pain | Safe in pregnancy, max 4g/day, avoid in liver disease |
| Amoxicillin/co-amoxiclav | Pneumonia, UTI | Check penicillin allergy |
| Ceftriaxone 1-2g IV | Pneumonia, meningitis, sepsis | Once daily dosing |
| Metronidazole | Anaerobic infections, H. pylori | No alcohol - causes severe reaction |
| Furosemide 40mg | Fluid overload, hypertension | Hypokalemia, ototoxic in high doses |
| Omeprazole 20-40mg | Gastric protection, ulcers | Give before meals |
| Ondansetron 4-8mg | Nausea/vomiting | QT prolongation - check ECG |
| Metformin 500-2g | Type 2 diabetes | HOLD before contrast dye and surgery |
| Insulin (various) | Diabetes | Check BGL before every dose |
| Prednisolone | Asthma, autoimmune, allergic | Hyperglycemia, infection risk, peptic ulcer with NSAIDs |
| LMWH (Enoxaparin) | DVT prophylaxis, ACS | Hold in AKI, bleeding |
| ORS | Dehydration, diarrhea | First-line for mild-moderate dehydration |
| Lactulose | Hepatic encephalopathy, constipation | Aim 2-3 soft stools/day |
| Iron (ferrous sulfate) | Iron deficiency anemia | Take between meals for better absorption, black stools normal |
| Vitamin B12 (cyanocobalamin) | B12 deficiency | IM injections if GI absorption impaired |
POCKET CHEAT SHEET - EMERGENCY VALUES IN GENERAL MEDICINE
CALL SENIOR IMMEDIATELY IF:
→ SpO2 <90% despite O2
→ BP <90/60 or falling fast
→ HR >140 or <40
→ RR >30
→ GCS drop ≥2 points
→ Na+ <120 or >155 mEq/L
→ K+ >6.5 or ECG changes of hyperK
→ Glucose <50 or >500 mg/dL
→ Lactate >4 mmol/L
→ Active massive bleeding
→ Unresponsive patient
→ Severe uncontrolled pain not responding to analgesia

5 MOST COMMON CAUSES OF FEVER IN A MEDICINE WARD:
1. Pneumonia / chest infection
2. UTI
3. IV line infection (phlebitis / septic thrombophlebitis)
4. DVT
5. Drug fever (usually appears 7-10 days after starting new drug)
- Diabetes - Types, diagnosis, DKA, HHS, hypoglycemia, complications
- Hypertension - Classification, target organ damage, drug choices, emergencies
- Pneumonia - CURB-65, organisms, antibiotics
- Tuberculosis - Symptoms, diagnosis, HRZE treatment, DOTS
- Dengue - Phases, warning signs, NS1/IgM, fluid management
- Anemia - Micro/Normo/Macrocytic classification, blood film
- Acute Kidney Injury - Pre/intra/post-renal, hyperkalemia treatment
- Liver disease - Jaundice types, cirrhosis complications (ascites, SBP, encephalopathy)
- Asthma & COPD - Exacerbation management, O2 targets
- Sepsis - qSOFA, Sepsis Six
- Electrolytes - Hyponatremia, hypo/hyperkalemia
Continue the above one
🏥 GENERAL MEDICINE - CONTINUED
Part 2 | Conditions 12 to 20
CONDITION 12 - THYROID DISEASE
Quick Anatomy of Thyroid Hormone Axis:
Hypothalamus → TRH
      ↓
Pituitary → TSH
      ↓
Thyroid gland → T3 + T4
- TSH HIGH → Thyroid not making enough → Hypothyroidism
- TSH LOW → Thyroid making too much → Hyperthyroidism
- TSH is always the FIRST test to order
HYPOTHYROIDISM
Causes:
| Cause | Notes |
|---|---|
| Hashimoto's thyroiditis | Most common in developed countries; autoimmune, anti-TPO antibodies |
| Iodine deficiency | Most common worldwide (endemic goiter) |
| Post-radioactive iodine treatment | Iatrogenic |
| Post-thyroidectomy | Surgical removal |
| Drugs | Amiodarone, lithium, interferon |
Symptoms - "SLOW":
- S - Slow metabolism: weight gain, constipation, bradycardia, slow reflexes
- L - Low temperature tolerance: cold intolerance, feeling always cold
- O - Other: dry skin, hair loss, puffy face/eyes (myxedema), hoarse voice
- W - Weakness: fatigue, lethargy, muscle cramps, depression, poor memory
Signs on examination:
- Bradycardia
- Dry, coarse skin
- Non-pitting periorbital edema (myxedema)
- Slow-relaxing (hung-up) tendon reflexes
- Goiter (enlarged thyroid) if due to iodine deficiency or Hashimoto's
- Macroglossia (large tongue)
Investigations:
- TSH: HIGH (most sensitive test)
- Free T4: LOW
- Anti-TPO antibodies: positive in Hashimoto's
- CBC: may show macrocytic anemia
- Lipids: often elevated (hypothyroidism raises LDL)
- ECG: bradycardia, low voltage, flattened T waves
Treatment:
- Levothyroxine (T4) - synthetic thyroid hormone
- Starting dose: 25-50 mcg OD (start low especially in elderly/cardiac patients - can precipitate angina)
- Take on empty stomach, 30-60 minutes before food
- Increase by 25 mcg every 6-8 weeks
- Monitor TSH 6-8 weeks after any dose change
- Target TSH: 0.5-2.5 mIU/L
Myxedema Coma (Extreme Hypothyroidism - Emergency):
- Severely ill, unconscious, hypothermic, bradycardic
- Precipitated by: cold exposure, infection, sedative drugs
- Treatment: IV T4 + IV hydrocortisone + warming + ICU
HYPERTHYROIDISM
Causes:
| Cause | Notes |
|---|---|
| Graves' disease | Most common; autoimmune, TSH receptor antibodies (TRAb); exophthalmos |
| Toxic multinodular goiter | Older patients, nodular thyroid |
| Toxic adenoma | Single hot nodule |
| Subacute thyroiditis | Painful thyroid, transient hyperthyroidism then hypothyroidism |
| Excess iodine (Jod-Basedow) | After contrast dye, amiodarone |
Symptoms - "FAST":
- F - Fast heart: palpitations, tachycardia, AF
- A - Anxious, agitated, tremor of hands, heat intolerance, sweating
- S - Slim down: weight loss despite good appetite, diarrhea
- T - Tired yet hyperactive: insomnia, weakness, menstrual irregularity
Graves' Disease Specific Signs:
- Exophthalmos (proptosis - bulging eyes) - pathognomonic
- Pretibial myxedema (thickened skin over shins)
- Diffuse smooth goiter with bruit
- Thyroid acropachy (clubbing - rare)
Investigations:
- TSH: LOW (suppressed, often undetectable)
- Free T3/T4: HIGH
- TRAb: positive in Graves'
- Thyroid scan (Tc-99m): Graves' = diffuse uptake; toxic adenoma = focal hot nodule
Treatment:
| Option | Drug/Procedure | Notes |
|---|---|---|
| Antithyroid drugs | Methimazole (carbimazole) or PTU | Euthyroid in 3-8 weeks; agranulocytosis is rare but serious side effect |
| Beta-blocker | Propranolol / atenolol | Controls symptoms FAST (tremor, palpitations) while waiting for antithyroid effect |
| Radioactive iodine (RAI) | I-131 | Destroys thyroid tissue; often leads to hypothyroidism eventually |
| Surgery | Thyroidectomy | For large goiter, compressive symptoms, failed drugs |
Thyroid Storm (Thyrotoxic Crisis) - Emergency:
- Extreme hyperthyroidism: very high temp, extreme tachycardia/AF, confusion, vomiting, heart failure
- Precipitated by: surgery, infection, trauma, contrast dye
- Treatment: High-dose methimazole + Lugol's iodine (blocks hormone release) + propranolol + steroids + treat precipitant + ICU
CONDITION 13 - PEPTIC ULCER DISEASE (PUD) & UPPER GI BLEED
Peptic Ulcer Disease
| Gastric Ulcer | Duodenal Ulcer | |
|---|---|---|
| More common in | Older age, NSAIDs use | Younger patients, H. pylori |
| Pain timing | Worse 30-60 min AFTER food | Worse 2-3 hrs after food, relieved by eating ("hunger pain") |
| Weight | May lose weight (pain on eating) | Normal |
| H. pylori | 70% | 90% |
Causes:
- H. pylori (Helicobacter pylori) - most common cause worldwide
- NSAIDs (aspirin, ibuprofen, diclofenac) - inhibit prostaglandins that protect stomach
- Stress ulcers - critically ill patients in ICU
- Zollinger-Ellison syndrome - rare; gastrinoma causing massive acid production
Symptoms:
- Epigastric pain (burning/gnawing)
- Nausea, bloating
- Heartburn
- Complications: bleeding (hematemesis, melena), perforation (sudden severe pain), obstruction (persistent vomiting)
H. pylori Testing:
| Test | Notes |
|---|---|
| Urea breath test (UBT) | Best non-invasive; patient drinks labeled urea, bacteria break it down |
| Stool antigen test | Good non-invasive option |
| Biopsy (via endoscopy) | Gold standard; also gives histology |
| Serology (IgG) | Positive = past or present infection, not useful for test-of-cure |
H. pylori Eradication (Triple Therapy × 14 days):
- PPI (omeprazole 20mg BD) + Amoxicillin 1g BD + Clarithromycin 500mg BD
- If penicillin allergy: Replace amoxicillin with metronidazole
- Confirm eradication 4 weeks after completing antibiotics with UBT or stool antigen
Acid Suppression Drugs:
| Drug class | Example | How it works |
|---|---|---|
| PPI (proton pump inhibitor) | Omeprazole, pantoprazole, esomeprazole | Irreversibly blocks H+/K+ ATPase pump - most effective |
| H2 blocker | Ranitidine, famotidine | Blocks H2 receptor on parietal cell |
| Antacids | Magnesium hydroxide, aluminum hydroxide | Neutralizes acid (fast but short acting) |
| Sucralfate | Sucralfate | Coats ulcer base |
| Misoprostol | Misoprostol | Prostaglandin analog - protects mucosa (used with NSAIDs) |
Upper GI Bleed (UGIB)
Presentation:
- Hematemesis = vomiting blood (bright red = active; coffee-ground = older blood)
- Melena = black, tarry, offensive-smelling stools (blood digested in upper GI)
- Hematochezia (bright red rectal bleeding) only if very massive UGIB
Causes:
| Cause | Clue |
|---|---|
| Peptic ulcer (most common - 50%) | History of NSAIDs, H. pylori, epigastric pain |
| Esophageal varices | Cirrhotic patient, portal hypertension, large UGIB |
| Mallory-Weiss tear | Retching/vomiting before blood |
| Gastritis/erosions | NSAID use, alcohol, stress |
| Esophagitis | GERD, dysphagia |
Glasgow-Blatchford Score (Pre-endoscopy risk score):
- Score 0 = low risk → outpatient management possible
- Score ≥7 → needs urgent endoscopy and likely intervention
Immediate Management of UGIB:
ABCDE FIRST - assess stability
         ↓
IV access × 2 (large bore, 16G+)
         ↓
Blood tests: CBC, LFT, KFT, coagulation, GROUP & CROSSMATCH
         ↓
IV fluids - Ringer's Lactate / Normal saline
         ↓
Blood transfusion if Hb <8 g/dL (or <10 if cardiac patient)
         ↓
IV PPI: Pantoprazole 80mg bolus, then 8mg/hr infusion
         ↓
Urgent endoscopy (within 24h, within 12h if high risk)
         ↓
If varices: IV terlipressin + antibiotics (ceftriaxone - SBP prophylaxis)
- Score >5 = high rebleed/mortality risk
CONDITION 14 - URINARY TRACT INFECTION (UTI)
Types:
| Type | Site | Symptoms | Severity |
|---|---|---|---|
| Cystitis | Bladder | Dysuria, frequency, urgency, suprapubic pain | Lower UTI - mild |
| Pyelonephritis | Kidney + pelvis | Above + fever, loin/flank pain, rigors, nausea | Upper UTI - serious |
| Prostatitis | Prostate (men) | Perineal pain, difficulty urinating, tender prostate | Can be severe |
| Asymptomatic bacteriuria | Any | No symptoms, bacteria in urine | Treat only in pregnancy |
Risk Factors:
- Female sex (short urethra)
- Sexual activity ("honeymoon cystitis")
- Pregnancy (always treat even if asymptomatic)
- Urinary catheter (most common hospital infection)
- Obstruction (BPH, stones)
- Diabetes
- Immunocompromised
Diagnosis:
- Urine dipstick: Nitrites (bacteria convert nitrates) + Leucocyte esterase (WBCs) = likely UTI
- Urine microscopy: WBCs >5/HPF (pyuria), bacteria, RBCs
- Urine culture & sensitivity (C&S): Gold standard - identifies organism + antibiotic sensitivity (results take 24-48 hours)
- Send urine before starting antibiotics
Common Organisms:
- E. coli - 80% of uncomplicated UTI
- Klebsiella, Proteus, Pseudomonas (especially in hospital/catheter-associated)
- Staphylococcus saprophyticus - young sexually active women
- Enterococcus - in complicated/hospital UTI
Treatment:
| Type | Drug | Duration |
|---|---|---|
| Uncomplicated cystitis (women) | Nitrofurantoin 100mg BD or Trimethoprim 200mg BD | 3-5 days |
| Pyelonephritis (oral) | Ciprofloxacin 500mg BD or Co-amoxiclav 625mg TDS | 7-14 days |
| Pyelonephritis (IV - admitted) | Ceftriaxone 1-2g OD IV or Gentamicin | Until afebrile 24-48h, then switch oral |
| Catheter-associated UTI | Treat only if symptomatic; change catheter first | 5-7 days |
| Pregnancy (any bacteriuria) | Cephalexin or Nitrofurantoin (avoid in 3rd trimester) | 7 days |
CONDITION 15 - MALARIA
Plasmodium Species:
| Species | Clinical severity | Special features |
|---|---|---|
| P. falciparum | Most dangerous - can be fatal | Cerebral malaria, severe anemia, respiratory distress |
| P. vivax | Relapses (liver dormant form - hypnozoite) | Treat with primaquine to prevent relapse |
| P. ovale | Like vivax, relapses | Primaquine needed |
| P. malariae | Mild, can persist for years | Quartan fever (48h cycle) |
Classic Presentation:
- Periodicity of fever: P. falciparum = irregular; P. vivax/ovale = every 48h (tertian); P. malariae = every 72h (quartan)
- Rigors (shaking chills) → high fever → profuse sweating → resolution (cold-hot-sweat cycle)
- Headache, myalgia, nausea
- Splenomegaly (chronic malaria)
- Jaundice, anemia (destruction of RBCs)
Complications of Severe Falciparum Malaria:
- Cerebral malaria: Seizures, altered consciousness, coma
- Blackwater fever: Massive hemolysis → hemoglobinuria (dark/black urine)
- Severe anemia (Hb <7)
- Hypoglycemia (especially in children, pregnant women)
- Acute lung injury / Pulmonary edema
- AKI
Diagnosis:
- Peripheral blood smear (thick + thin smear): Gold standard; identifies species and parasite density
- Thick film: better for detecting parasites (screening)
- Thin film: identifies species (diagnosis)
- Rapid diagnostic test (RDT/ICT): Quick, good for P. falciparum (HRP2 antigen)
- Quantitative buffy coat (QBC)
Treatment:
| Type | Treatment |
|---|---|
| Uncomplicated P. falciparum | Artemisinin-based combination therapy (ACT): Artemether-lumefantrine (Coartem) or AS+AQ |
| Severe/complicated falciparum | IV Artesunate (preferred) or IV quinine + doxycycline |
| P. vivax/ovale (blood stage) | Chloroquine (where sensitive) or ACT |
| P. vivax/ovale (liver - prevent relapse) | Primaquine 15mg OD × 14 days (check G6PD first - primaquine causes hemolysis in G6PD deficiency) |
CONDITION 16 - DEEP VEIN THROMBOSIS (DVT) & PULMONARY EMBOLISM (PE)
DVT - Blood Clot in Deep Vein (usually leg)
Risk Factors - Virchow's Triad:
| Component | Risk factors |
|---|---|
| Stasis | Bed rest, long flight, immobilization, heart failure |
| Hypercoagulability | Malignancy, pregnancy, OCP, thrombophilia, post-surgery |
| Vessel injury | Trauma, surgery, IV catheter |
Symptoms of DVT:
- Unilateral leg swelling (one leg much bigger than other)
- Warmth, redness, tenderness along vein
- Homan's sign (calf pain on dorsiflexion) - not reliable
- Calf circumference >3 cm difference between legs = significant
Wells DVT Score:
- Score ≥2 = DVT likely → do USS
- Score <2 = DVT unlikely → D-dimer first
Diagnosis:
- Compression USS (duplex): First line - non-compressibility of vein = DVT
- D-dimer: Sensitive but not specific - negative D-dimer rules out DVT if low pre-test probability
PE - Pulmonary Embolism (Clot in Lung Artery)
Symptoms:
- Sudden breathlessness (most common)
- Pleuritic chest pain (sharp, worse on breathing)
- Hemoptysis (blood-stained sputum)
- Tachycardia
- Tachypnea
- Syncope (massive PE)
Wells PE Score (simplified):
- Clinical signs of DVT (+3)
- PE is #1 diagnosis (+3)
- HR >100 (+1.5)
- Immobilization >3 days / surgery in past 4 weeks (+1.5)
- Previous DVT/PE (+1.5)
- Hemoptysis (+1)
- Malignancy (+1)
ECG in PE:
- Sinus tachycardia (most common finding)
- S1Q3T3 pattern (S wave in lead I, Q wave + inverted T in lead III) - classic but not common
- Right heart strain: right axis deviation, RBBB, T-wave inversion V1-V4
CTPA (CT Pulmonary Angiogram): Gold standard for PE diagnosis
Treatment:
| Severity | Treatment |
|---|---|
| Low-moderate PE, stable | LMWH (enoxaparin) → transition to DOAC (rivaroxaban or apixaban) |
| High-risk/massive PE + hemodynamic instability | IV thrombolysis (alteplase 100mg over 2h) - systemic; surgical/catheter embolectomy |
| All PE patients | Anticoagulation for minimum 3 months (6+ months if unprovoked or cancer-related) |
- Enoxaparin 40mg SC once daily
-
- Ted stockings / intermittent pneumatic compression
- Early mobilization
CONDITION 17 - CELLULITIS & SKIN INFECTIONS
Presentation:
- Spreading redness, warmth, swelling, tenderness
- Fever, raised WBC
- Typically lower limbs
- Entry point: minor wound, tinea pedis (athlete's foot), insect bite
Organisms:
- Streptococcus pyogenes (Group A Strep): Most common
- Staphylococcus aureus: Especially MRSA (methicillin-resistant)
- Diabetic foot: often polymicrobial
Grading Severity:
| Grade | Features | Treatment |
|---|---|---|
| 1 (mild) | No systemic illness, no comorbidities | Oral flucloxacillin or cefalexin |
| 2 (moderate) | Systemic signs (fever, raised WBC) | IV antibiotics, consider admission |
| 3 (severe) | Severe systemic illness, spreading rapidly | IV antibiotics, surgical review |
| 4 (life-threatening) | Sepsis + necrotizing fasciitis | Emergency surgical debridement + broad spectrum IV ABx |
Mark the Borders:
- Use a skin marker to draw the edge of redness when patient admitted
- Reassess in 6-12 hours: redness spreading beyond line = treatment not working
- Redness staying within line / reducing = improving
Necrotizing Fasciitis (Flesh-eating infection - Emergency):
- Rapidly spreading infection along fascial planes
- Disproportionate pain (pain much worse than appearance)
- Crepitus (gas under skin - feel crackling)
- Skin discoloration → black necrosis
- Treatment: Emergency surgical debridement + broad-spectrum IV ABx (meropenem + clindamycin + vancomycin) + ICU
CONDITION 18 - EPILEPSY & SEIZURES
Types of Seizures (ILAE Classification):
Focal (Partial) Seizures - Start in one area of brain:
- Simple focal: Conscious throughout - twitching of one limb, abnormal smell/taste
- Complex focal: Impaired consciousness - blank staring, automatisms (lip smacking, picking)
- Focal to bilateral tonic-clonic: Starts focal, spreads to whole brain
Generalized Seizures - Involve whole brain from start:
| Type | Features |
|---|---|
| Tonic-clonic ("grand mal") | Rigid (tonic) → jerking (clonic) → post-ictal phase (confused, sleepy) |
| Absence ("petit mal") | Brief blank stare, no post-ictal; children, responsive to ethosuximide |
| Myoclonic | Brief muscle jerks, often in morning |
| Tonic | Sudden rigidity, falls |
| Atonic (drop attacks) | Sudden loss of muscle tone → falls |
Status Epilepticus - Medical Emergency:
| Time | Action |
|---|---|
| 0-5 min | ABCDE, O2, position lateral (recovery), IV access, check BGL |
| 5 min | First-line: Lorazepam 0.1 mg/kg IV (or diazepam 10mg IV/PR) |
| 10 min | If no response: repeat benzodiazepine |
| 20-30 min | Second-line: Levetiracetam 60 mg/kg IV OR phenytoin 20 mg/kg IV OR valproate 40 mg/kg IV |
| 40+ min | Third-line: Anaesthesia (midazolam/propofol infusion) - ICU, ventilation |
Investigations after first seizure:
- BGL (hypoglycemia causes seizures)
- Na, Ca, Mg (electrolyte seizures)
- Toxicology (drug/alcohol related)
- CT brain (rule out structural cause)
- MRI brain (better for hippocampal sclerosis, cortical dysplasia)
- EEG (electroencephalogram) - identifies epileptiform activity
Common Antiepileptic Drugs (AEDs):
| Drug | Best for | Side effects to know |
|---|---|---|
| Sodium valproate | All seizure types, first line generalized | Weight gain, hair loss, tremor, teratogenic (spina bifida) - AVOID in women of childbearing age |
| Carbamazepine | Focal seizures | Diplopia, ataxia, hyponatremia, induces liver enzymes |
| Lamotrigine | Focal + generalized | Rash (Stevens-Johnson syndrome if started too fast) |
| Levetiracetam | All types (widely used now) | Mood changes, depression - safe in pregnancy |
| Phenytoin | Status epilepticus, focal | Zero-order kinetics (small dose changes → big level changes), gum hyperplasia, hirsutism, nystagmus |
| Ethosuximide | Absence seizures only | GI upset |
CONDITION 19 - NEPHROTIC & NEPHRITIC SYNDROME
Two Key Glomerular Syndromes - Know the Difference:
| Feature | NEPHROTIC | NEPHRITIC |
|---|---|---|
| Proteinuria | Massive (>3.5g/day) | Mild to moderate |
| Haematuria | No (or minimal) | YES - characteristic |
| Oedema | Massive (face, legs, ascites) | Mild-moderate |
| Blood pressure | Normal or low | HIGH (hypertension) |
| Albumin | LOW (lost in urine) | Normal |
| Cholesterol | HIGH (compensatory) | Normal/mildly raised |
Nephrotic Syndrome:
| Primary (kidney disease) | Secondary (systemic disease) |
|---|---|
| Minimal change disease (children) | Diabetes (most common secondary cause) |
| Membranous nephropathy (adults) | Lupus (SLE) |
| FSGS (focal segmental glomerulosclerosis) | Amyloidosis |
- Thrombosis (loss of antithrombin III in urine) → DVT, renal vein thrombosis
- Infections (loss of immunoglobulins) → pneumococcal, gram-negative
- Hyperlipidemia → cardiovascular risk
- Steroids (prednisolone 1mg/kg/day) - especially minimal change disease (remits well)
- ACEi/ARB (reduces proteinuria)
- Diuretics for edema
- Statins for hyperlipidemia
- Treat underlying cause
Nephritic Syndrome:
| Cause | Clue |
|---|---|
| Post-streptococcal GN | Child, 1-3 weeks after throat/skin Strep infection, low C3 |
| IgA nephropathy (Berger's) | Haematuria during/after URTI (synpharyngitic) |
| Lupus nephritis | Young woman + rash + joints + renal involvement |
| Goodpasture's (anti-GBM) | Haemoptysis + haematuria (lung-kidney syndrome) |
| ANCA vasculitis (GPA, MPA) | Multi-system, ANCA positive |
CONDITION 20 - CHRONIC KIDNEY DISEASE (CKD)
GFR Staging:
| Stage | GFR | Kidney function |
|---|---|---|
| G1 | >90 | Normal/high - but kidney damage present |
| G2 | 60-89 | Mildly reduced |
| G3a | 45-59 | Mildly-moderately reduced |
| G3b | 30-44 | Moderately-severely reduced |
| G4 | 15-29 | Severely reduced |
| G5 | <15 | Kidney failure (need dialysis/transplant) |
Causes:
- Diabetic nephropathy (most common worldwide)
- Hypertensive nephropathy
- Glomerulonephritis
- Obstructive uropathy (stones, BPH)
- Polycystic kidney disease (PKD)
- Recurrent infections
CKD Complications - Know All:
| Complication | Mechanism | Treatment |
|---|---|---|
| Anemia | Low erythropoietin (EPO) | EPO injections (darbepoetin), IV iron |
| Hypertension | Fluid retention + RAAS activation | ACEi/ARB (also slows progression), diuretics |
| Hyperkalemia | Reduced K+ excretion | Low K diet, stop ACEi if K>6, resonium, dialysis |
| Metabolic acidosis | Can't excrete H+ | Sodium bicarbonate tablets |
| Hyperphosphatemia | Reduced phosphate excretion | Phosphate binders (calcium carbonate/sevelamer) |
| Secondary hyperparathyroidism | Low Ca + high PO4 → PTH rises → bone disease | Active vitamin D (calcitriol), cinacalcet |
| Fluid overload | Can't excrete water | Fluid restriction, diuretics, dialysis |
| Uremia (end-stage symptoms) | Toxin accumulation | Dialysis |
Uremia Symptoms (End-Stage CKD):
- Nausea, anorexia, vomiting
- Pruritus (itch all over - urea deposits in skin)
- Encephalopathy (confusion, asterixis)
- Pericarditis (uremic pericarditis)
- Platelet dysfunction → bleeding tendency
- Metallic taste in mouth
Dialysis - Types:
| Hemodialysis (HD) | Peritoneal Dialysis (PD) | |
|---|---|---|
| How | Blood filtered through machine | Fluid put into abdomen, uses peritoneum as membrane |
| Frequency | 3× per week, 4h sessions | Daily (CAPD) or nightly (APD) |
| Access | AV fistula (surgically created) | PD catheter in abdomen |
| Where | Hospital or satellite unit | At home |
GENERAL MEDICINE MASTER DRUG CHART (Complete)
| Drug | Class | Use | Important Points |
|---|---|---|---|
| Levothyroxine | Thyroid hormone | Hypothyroidism | Empty stomach, check TSH 6-8 wks |
| Methimazole / Carbimazole | Antithyroid | Hyperthyroidism | Check WBC (agranulocytosis) |
| Propranolol | Beta-blocker | Symptom control in hyperthyroidism | Also used in portal HTN (varices) |
| Omeprazole / Pantoprazole | PPI | Ulcers, GERD, upper GI bleed | Before meals for best effect |
| Amoxicillin+Clarithromycin+PPI | Triple therapy | H. pylori eradication | 14 days |
| Terlipressin | Vasoconstrictor | Variceal bleed, hepatorenal syndrome | Monitor for ischaemia |
| Artemether-lumefantrine | ACT | Malaria (P. falciparum) | With food for better absorption |
| Primaquine | Antimalarial | P. vivax relapse prevention | Check G6PD first |
| Enoxaparin (LMWH) | Anticoagulant | DVT/PE treatment and prophylaxis | Reduce dose in CKD |
| Rivaroxaban/Apixaban | DOAC | DVT/PE, AF | No monitoring needed (unlike warfarin) |
| Alteplase (tPA) | Thrombolytic | Massive PE, STEMI | Risk of major bleeding |
| Flucloxacillin / Cefalexin | Antibiotic | Cellulitis (Strep/Staph) | Standard first-line |
| Vancomycin | Antibiotic | MRSA infections | Monitor levels, nephrotoxic |
| Lorazepam / Diazepam | Benzodiazepine | Seizures / status epilepticus | Respiratory depression |
| Sodium valproate | AED | Epilepsy (all types) | Teratogenic - avoid in young women |
| Levetiracetam | AED | Epilepsy | Good safety profile, IV available |
| Prednisolone | Steroid | Nephrotic syndrome, asthma, autoimmune | Hyperglycemia, infection, osteoporosis |
| Erythropoietin (EPO) | Growth factor | CKD anaemia | Monitor Hb, risk of hypertension |
| Calcium carbonate | Phosphate binder | CKD hyperphosphatemia | Give WITH meals |
| Calcitriol | Active Vit D | CKD bone disease | Monitor Ca levels |
| Sodium bicarbonate | Alkali | CKD metabolic acidosis | Oral tablets daily |
| Nitrofurantoin | Antibiotic | Uncomplicated UTI | Avoid in CKD, pyelonephritis |
| Ciprofloxacin | Antibiotic | Pyelonephritis, complicated UTI | Avoid in children, tendon rupture |
DAILY CHECKLIST FOR GENERAL MEDICINE - FULL VERSION
Questions to ask yourself about EVERY PATIENT, every day:
SYSTEM-BY-SYSTEM REVIEW:

METABOLIC:
□ If diabetic: BGL checked? Insulin given? Any hypo episodes overnight?
□ Thyroid patient: On levothyroxine? TSH pending?

CARDIOVASCULAR:
□ BP controlled? Which antihypertensive? Any chest pain?
□ If heart failure: weight? Fluid balance? Diuretic response?

RESPIRATORY:
□ SpO2? On O2? How many liters? Can we wean?
□ Fever + cough + consolidation on CXR? Start antibiotics?

RENAL:
□ Urine output >0.5 mL/kg/hr?
□ Creatinine trend? Rising or falling?
□ Any nephrotoxic drugs to stop?

INFECTIONS:
□ Are cultures back? Sensitivities match current antibiotic?
□ IV to oral switch possible? (afebrile 24-48h + tolerating oral)
□ Line sites clean? IV changed in last 72h?

HAEMATOLOGICAL:
□ Anaemia: Hb? Transfusion needed?
□ Thrombocytopenia: Dengue? DIC? TTP?
□ DVT prophylaxis ordered?

GI/LIVER:
□ Bowels moving? If liver disease: any encephalopathy signs (asterixis)?
□ On lactulose? How many stools/day?

MEDICATIONS:
□ Any drug interactions? Any to stop?
□ Renal dosing adjustments needed?
□ Anticoagulation (dose, monitoring)?

SOCIAL/DISCHARGE:
□ Improving enough for discharge?
□ Follow-up appointment needed?
□ Patient knows their diagnosis and medications?
THINGS SENIORS WILL ASK YOU ON ROUNDS (Be Ready)
| Question | Answer they expect |
|---|---|
| "What are the causes of jaundice?" | Pre-hepatic / Hepatic / Post-hepatic |
| "What is this patient's CURB-65 score?" | Calculate from RR, BP, BUN, confusion, age |
| "Why is this patient hyponatremic?" | Assess volume status → SIADH vs dehydration vs fluid overload |
| "What does this ECG show?" | Rate, rhythm, axis, P waves, PR, QRS, ST/T |
| "What is your differential for this fever?" | Think by system: chest? urine? line? wound? drugs? DVT? |
| "What next investigation would you order?" | Based on history - always explain WHY you're ordering it |
| "What is the treatment for DKA?" | Fluids + Insulin + Potassium + Treat cause |
| "How would you manage this GI bleed?" | ABCDE + IV access × 2 + Crossmatch + IV PPI + Endoscopy |
- Diabetes (DKA, HHS, Hypoglycemia) | 2. Hypertension | 3. Pneumonia | 4. TB | 5. Dengue | 6. Anemia | 7. AKI | 8. Liver / Jaundice | 9. Asthma & COPD | 10. Sepsis | 11. Electrolytes | 12. Thyroid disease | 13. PUD & GI Bleed | 14. UTI | 15. Malaria | 16. DVT & PE | 17. Cellulitis | 18. Epilepsy | 19. Nephrotic & Nephritic | 20. CKD
Condition 11 not completed the info give that
CONDITION 11 - ELECTROLYTE DISTURBANCES (COMPLETE)
Full Guide | All 7 Electrolytes
OVERVIEW - WHY ELECTROLYTES MATTER
- Cardiac arrest (K+, Ca2+, Mg2+)
- Seizures (Na+, Ca2+, Mg2+)
- Muscle paralysis (K+, Mg2+)
- Coma (Na+)
ELECTROLYTE 1 - SODIUM (Na+) | Normal: 136-145 mEq/L
HYPONATREMIA (Na+ <135 mEq/L)
Symptoms (depend on speed of fall, not just level):
| Na+ Level | Symptoms |
|---|---|
| 130-135 | Usually asymptomatic |
| 125-130 | Nausea, headache, malaise |
| 120-125 | Confusion, disorientation |
| <120 | Seizures, coma, death |
Step 1: Assess the patient's VOLUME STATUS (the most important step)
Look at the patient:
- Dry mouth, low BP, tachycardia, reduced skin turgor → HYPOVOLEMIC
- Normal examination → EUVOLEMIC
- Oedema, ascites, raised JVP → HYPERVOLEMIC
Causes by Volume Status:
| Volume Status | Condition | Key Clue |
|---|---|---|
| Hypovolemic (dry, losing fluid) | Vomiting/diarrhea, diuretics (especially thiazides), Addison's disease | Urine Na >20 if kidneys losing it (diuretics, Addison); Urine Na <20 if extra-renal loss (diarrhea) |
| Euvolemic (normal volume) | SIADH (most common euvolemic cause), hypothyroidism, psychogenic polydipsia | High urine sodium (>40), high urine osmolality (>100 mOsm/kg) |
| Hypervolemic (oedematous) | Heart failure, cirrhosis, nephrotic syndrome | Dilutional hyponatremia - too much water, Na diluted out |
SIADH (Syndrome of Inappropriate ADH Secretion):
- CNS: meningitis, stroke, subarachnoid hemorrhage, head injury
- Chest: pneumonia, TB, lung cancer (small cell - most common malignancy cause)
- Malignancy: small cell lung cancer (secretes ADH ectopically)
- Drugs: carbamazepine, SSRIs (fluoxetine), morphine, cyclophosphamide, vincristine
- Idiopathic / Post-surgery
- Serum Na <135 mEq/L (low serum osmolality <280)
- Urine osmolality >100 mOsm/kg (inappropriately concentrated)
- Urine Na >40 mEq/L (kidneys still losing Na)
- Normal thyroid and adrenal function (exclude hypothyroidism, Addison's)
- No diuretics, no volume depletion, no oedema
Treatment of Hyponatremia:
- Myelin sheath around brainstem neurons is destroyed
- Results in: dysarthria (slurred speech), dysphagia, flaccid paralysis, coma
- Irreversible, devastating - especially in malnourished, alcoholics, elderly
| Severity | Na level & Symptoms | Treatment |
|---|---|---|
| Mild/Chronic asymptomatic | Na 125-134, no symptoms | Treat underlying cause + fluid restriction 1000 mL/day (for SIADH) |
| Moderate | Na 115-124, nausea, confusion | Fluid restriction + cautious sodium correction |
| Severe/Symptomatic | Na <120 OR seizures/coma | 3% Hypertonic saline 100 mL IV over 10 min (can repeat × 2); raise Na by 4-6 mEq in first 6 hours |
- Patient seizing OR
- GCS dropping OR
- Na <115 mEq/L
- In chronic hyponatremia (>48h): max correction 8 mEq/L in 24 hours
- In acute hyponatremia (<48h): can correct up to 1-2 mEq/L per hour
- Recheck Na every 2-4 hours when giving hypertonic saline
| Cause | Specific treatment |
|---|---|
| Hypovolemic hyponatremia | Normal saline (replace volume) |
| SIADH | Fluid restriction 800-1000 mL/day; treat cause |
| Heart failure | Diuretics + treat heart failure |
| Cirrhosis | Albumin, treat underlying liver disease |
| Hypothyroidism | Levothyroxine (Na corrects as thyroid corrects) |
| Addison's disease | Hydrocortisone (emergency if in crisis) |
HYPERNATREMIA (Na+ >145 mEq/L)
Causes:
- Water loss: Fever, sweating, burns, diabetes insipidus (DI), osmotic diuresis (DKA), diarrhea
- Inadequate water intake: Elderly, unconscious, infants who can't ask for water
- Salt excess (rare): IV hypertonic saline, excess sodium bicarbonate, sea water ingestion
Symptoms:
- Thirst (if conscious)
- Confusion, lethargy, irritability
- Weakness, tremors
- Seizures, coma (severe Na >155-160)
Treatment of Hypernatremia:
Free water deficit = [(Na actual - 140) ÷ 140] × Total Body Water (TBW) TBW = 0.6 × body weight in kg
- TBW = 0.6 × 70 = 42 L
- Free water deficit = [(165-140) ÷ 140] × 42 = 7.5 L
- Mild: Encourage oral water/feeds
- If IV needed: 5% Dextrose (D5W) or 0.45% NaCl (half-normal saline)
- Never give pure water IV - causes hemolysis
ELECTROLYTE 2 - POTASSIUM (K+) | Normal: 3.5-5.0 mEq/L
HYPERKALEMIA (K+ >5.5 mEq/L)
Causes ("DREAD"):
- Drugs: ACEi, ARBs, spironolactone, NSAIDs, heparin, beta-blockers, digoxin toxicity
- Renal failure (AKI/CKD) - can't excrete K+
- Endocrine: Addison's disease (no aldosterone → K+ retained)
- Acidosis: H+ goes into cells, K+ comes out
- Destruction: rhabdomyolysis, tumor lysis syndrome, massive hemolysis, burns
ECG Changes (in order as K rises):
| K+ level | ECG Change |
|---|---|
| 5.5-6.0 | Tall, peaked, narrow, tented T waves |
| 6.0-6.5 | PR interval prolongation, P waves flatten |
| 6.5-7.0 | Wide QRS (>0.12 sec) |
| >7.0 | P waves disappear, sine-wave pattern |
| >8.0-9.0 | VF or asystole → cardiac arrest |
Treatment - Three Goals (from Fischer's Mastery of Surgery):
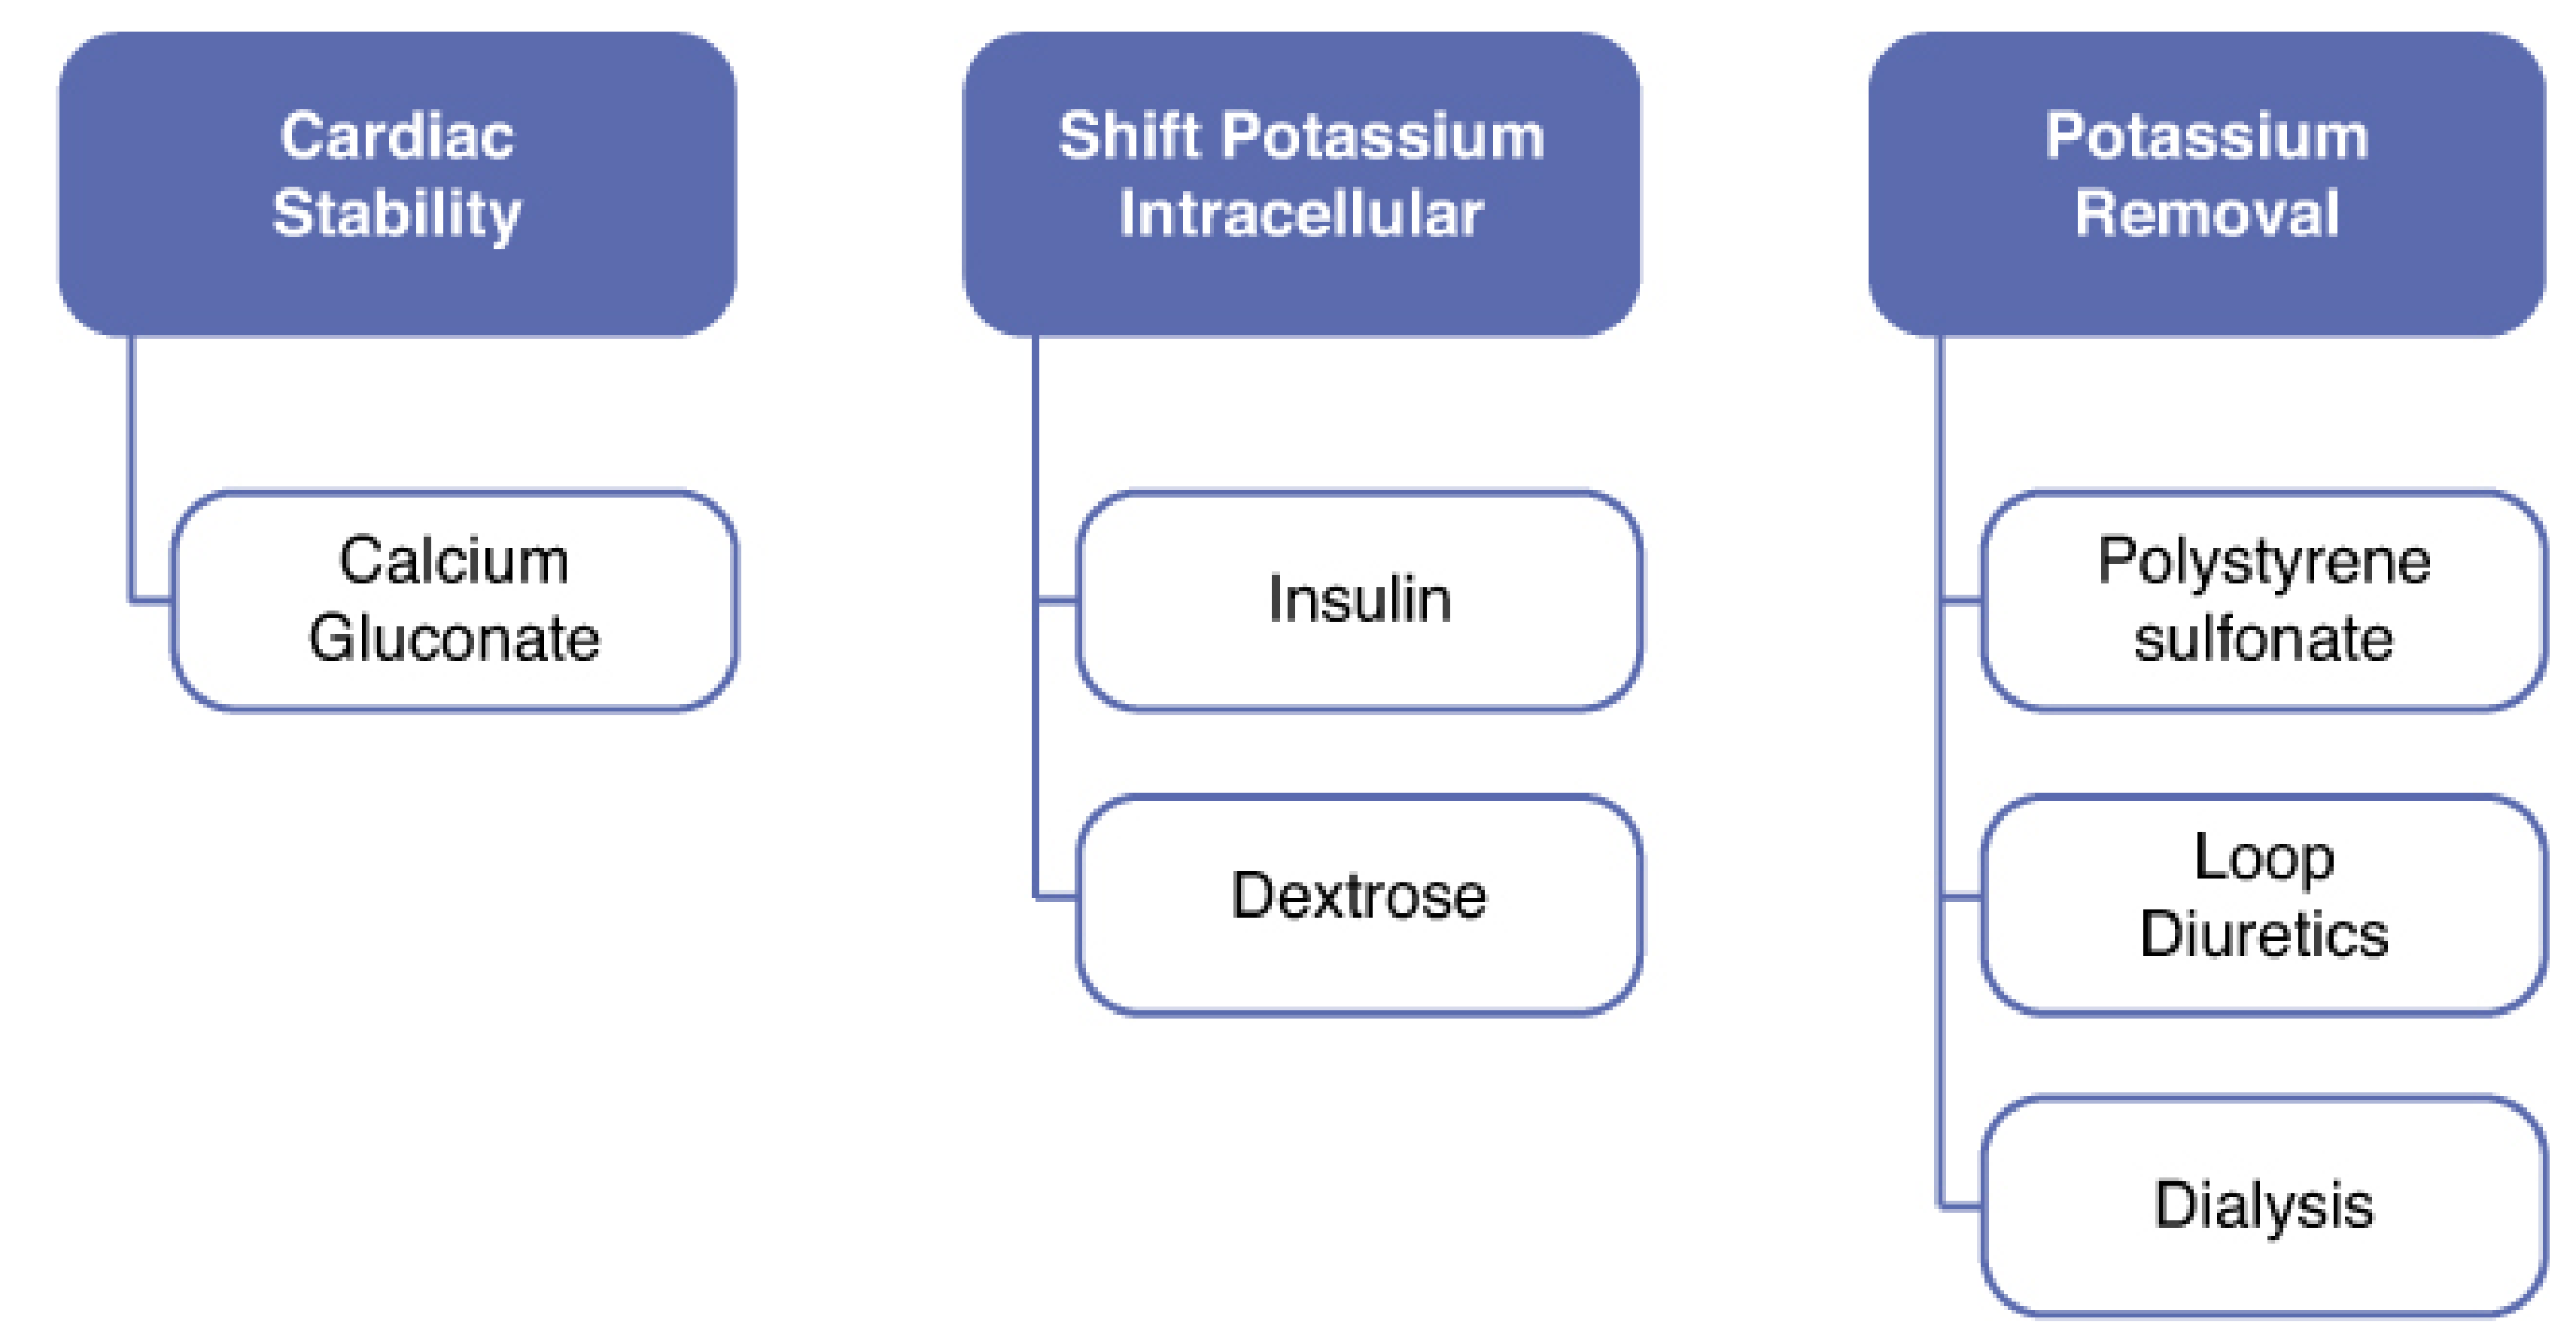
| Goal | Drug | Dose | Onset | Duration | Mechanism |
|---|---|---|---|---|---|
| 1. Cardiac protection | Calcium gluconate 10% | 10 mL IV over 2-3 min | 2-3 min | 30-60 min | Stabilizes cardiac membrane - does NOT lower K+ |
| Repeat if no ECG improvement in 5-10 min | |||||
| 2. Shift K+ into cells | Insulin 10-20 units + Dextrose 50% 25-50g IV | Together over 15-30 min | 15-30 min | 4-6 hours | Insulin drives K+ into cells |
| Salbutamol (albuterol) nebulised 10-20mg | Over 30-60 min | 30 min | 2-4 hours | Beta-2 agonist shifts K+ intracellular | |
| Sodium bicarbonate IV | If metabolic acidosis present | 30-60 min | Hours | Corrects acidosis → K+ shifts in | |
| 3. Remove K+ from body | Calcium resonium (polystyrene sulfonate) | 15-30g oral or PR in water | Hours | Hours | Binds K+ in gut, excretes in stool |
| Furosemide 40-80mg IV | If urine output adequate | 30 min | Hours | Promotes renal K+ loss | |
| Dialysis | If renal failure / refractory | Immediate | Definitive | Physically removes K+ |
- Low potassium diet (avoid: bananas, oranges, potatoes, tomatoes, dried fruits, nuts)
- Stop ACEi/ARBs if K+ consistently >6
- Newer agents: Patiromer (8.4g daily with food) or Sodium zirconium cyclosilicate
HYPOKALEMIA (K+ <3.5 mEq/L)
Causes:
| Mechanism | Causes |
|---|---|
| GI losses | Vomiting (loses K+ + H+ → alkalosis), diarrhea, laxative abuse, ileostomy |
| Renal losses | Diuretics (furosemide = most common, thiazides), hyperaldosteronism, Cushing's, RTA, amphotericin |
| Transcellular shift | Insulin therapy (DKA treatment), alkalosis, beta-2 agonists (salbutamol), hypothermia |
| Poor intake | Malnutrition, starvation, alcoholism |
Symptoms:
- Mild (3.0-3.5): Often asymptomatic
- Moderate (2.5-3.0): Fatigue, weakness, muscle cramps, constipation, palpitations
- Severe (<2.5): Flaccid paralysis (including respiratory muscles), rhabdomyolysis, ileus
ECG Changes in Hypokalemia:
- Flattening of T waves
- U waves (positive deflection after T wave - classic sign)
- ST depression
- Prolonged QU interval
- Severe: ventricular tachyarrhythmias (torsades de pointes)
Treatment:
| Severity | Route | Dose | Notes |
|---|---|---|---|
| Mild (K 3.0-3.5), asymptomatic | Oral | KCl (Slow-K) 600-1200mg TDS or potassium-rich foods | Banana, orange juice, coconut water |
| Moderate (K 2.5-3.0) | Oral + consider IV | KCl supplements + IV if not tolerating oral | |
| Severe (<2.5) or symptomatic | IV | Add KCl 20-40 mEq to 1L NS/RL, max 10-20 mEq/hour via peripheral IV | NEVER bolus IV KCl - causes cardiac arrest |
ELECTROLYTE 3 - CALCIUM (Ca2+) | Normal: 8.5-10.3 mg/dL
Corrected Ca2+ = Measured Ca2+ + [0.8 × (4.0 - albumin)]
HYPERCALCEMIA (Ca2+ >10.3 mg/dL)
Causes - 90% are from just 2 causes:
- Primary hyperparathyroidism - most common in outpatients; elevated PTH, usually asymptomatic, found on routine bloods
- Malignancy - most common in inpatients; PTH suppressed but PTHrP elevated; advanced cancer
Symptoms - "Bones, Stones, Groans, Psychic Moans":
| Mnemonic | System | Symptoms |
|---|---|---|
| Bones | Skeletal | Bone pain, fractures, osteitis fibrosa cystica (in hyperparathyroidism) |
| Stones | Renal | Polyuria, polydipsia, kidney stones (Ca oxalate), nephrocalcinosis |
| Groans | GI | Nausea, vomiting, constipation, anorexia, peptic ulcer |
| Psychic Moans | Neurological | Fatigue, depression, confusion, stupor, coma (at >14 mg/dL) |
Treatment:
| Severity | Treatment |
|---|---|
| Mild (Ca <12 mg/dL), asymptomatic | Stop offending drugs, increase oral fluids, treat underlying cause |
| Moderate (Ca 12-14 mg/dL) | IV fluids (normal saline 200-300 mL/hour) - hydration promotes Ca excretion |
| Severe (Ca >14 mg/dL) or symptomatic | IV NS aggressively + Furosemide (after rehydrated) + Bisphosphonate (zoledronic acid IV - gold standard for malignant hypercalcemia) |
| Malignancy-related | Zoledronic acid 4mg IV over 15 min - works in 24-48 hours |
| Granulomatous/Vitamin D excess | Steroids (hydrocortisone/prednisolone) - inhibit vitamin D activation |
HYPOCALCEMIA (Ca2+ <8.5 mg/dL, corrected)
Causes:
- Hypoparathyroidism - most commonly after thyroid/parathyroid surgery (check for Chvostek + Trousseau after any neck surgery)
- Vitamin D deficiency (very common - especially in sun-deprived populations, malnutrition)
- Hypomagnesemia - low Mg suppresses PTH
- Pancreatitis (fat saponification consumes Ca)
- CKD (impaired vitamin D activation, high phosphate)
- Massive blood transfusion (citrate chelates Ca)
Symptoms - "Neuromuscular excitability":
- Perioral tingling (numbness around lips)
- Tingling in hands and feet
- Muscle cramps → tetany (carpopedal spasm - hands/feet clench)
- Chvostek's sign: Tap facial nerve just in front of ear → facial muscle twitching
- Trousseau's sign: Inflate BP cuff on arm >SBP for 3 min → hand goes into carpal spasm (thumb adducts, fingers extend = "main d'accoucheur")
- Prolonged QT interval on ECG → torsades de pointes
- Seizures (severe hypocalcemia)
- Laryngospasm (emergency - airway obstruction)
Treatment:
| Severity | Treatment |
|---|---|
| Mild, asymptomatic | Oral calcium supplements (calcium carbonate 500mg-1g BD) + oral vitamin D |
| Moderate | Oral calcium + calcitriol (active Vit D) especially if hypoparathyroid |
| Symptomatic (tetany, seizures, laryngospasm) | 10 mL 10% calcium gluconate IV over 10 minutes (slow IV - cardiac monitoring) - can repeat; then maintenance infusion |
ELECTROLYTE 4 - MAGNESIUM (Mg2+) | Normal: 1.7-2.2 mg/dL (0.7-0.9 mmol/L)
HYPOMAGNESEMIA (Mg2+ <1.7 mg/dL)
Causes:
- Diuretics (furosemide, thiazides) - most common hospital cause
- Chronic diarrhea, malabsorption
- Alcohol abuse (renal Mg wasting)
- Diabetes mellitus (renal loss)
- Drugs: aminoglycosides (gentamicin), proton pump inhibitors (long-term), digoxin, cisplatin
- Poor intake + refeeding
Symptoms:
- Mild: Causes other electrolyte disturbances (hypokalemia, hypocalcemia) - often only finding
- Severe:
- Neuromuscular: tremor, muscle cramps, positive Chvostek/Trousseau
- Neurological: confusion, seizures, heightened reflexes
- Cardiac: Torsades de Pointes (the arrhythmia most associated with low Mg - polymorphic VT with QT prolongation)
Key Point: Refractory Hypokalemia
Treatment:
- Mild/moderate: Oral magnesium oxide tablets or magnesium glycinate
- Severe / symptomatic: MgSO4 (Magnesium sulphate) 2g IV over 10-15 min (slowly, watch for bradycardia and hypotension) then maintenance infusion
- Torsades de Pointes: MgSO4 2g IV stat is first-line treatment
- Eclampsia: MgSO4 4g IV loading dose (different context - prevent seizures)
HYPERMAGNESEMIA (Mg2+ >2.2 mg/dL)
Causes:
- Renal failure (can't excrete Mg)
- Massive Mg supplementation (especially in eclampsia treatment)
- Excessive antacids (Mg-containing: gaviscon, milk of magnesia)
- Adrenal insufficiency
Symptoms by Level:
| Mg level | Effect |
|---|---|
| 4-5 mEq/L | Loss of deep tendon reflexes (first sign to check!) |
| 5-7 mEq/L | Hypotension, bradycardia, nausea |
| 7-10 mEq/L | Respiratory paralysis |
| >10 mEq/L | Cardiac arrest (complete heart block) |
Treatment:
- Stop Mg supplementation
- IV calcium gluconate (10 mL 10% over 3 min) - temporarily antagonizes Mg at membrane
- IV fluids + furosemide (promote renal Mg excretion)
- Severe/renal failure: Dialysis
ELECTROLYTE 5 - PHOSPHATE (PO4) | Normal: 2.5-4.5 mg/dL
HYPOPHOSPHATEMIA (PO4 <2.5 mg/dL)
Causes:
- Refeeding syndrome (MOST important ward cause)
- Malnutrition, malabsorption
- Antacid use (aluminum/Mg antacids bind phosphate in gut)
- DKA treatment (insulin drives PO4 into cells)
- Hyperparathyroidism
- Occurs when severely malnourished patient starts eating/receiving nutrition (oral, enteral, or parenteral)
- Carbohydrates in food → insulin release → K+, Mg2+, PO4 all rush into cells → all 3 drop suddenly
- Prevention: Feed slowly, start at 50% of target calories, supplement K/Mg/PO4 before and during feeding
Symptoms of Hypophosphatemia:
- Muscle weakness (including respiratory muscles → ventilator dependence)
- Confusion, seizures
- Hemolytic anemia
- Platelet dysfunction
Treatment:
- Mild: Oral phosphate supplements
- Severe: IV sodium/potassium phosphate infusion
HYPERPHOSPHATEMIA (PO4 >4.5 mg/dL)
- Calcium carbonate (cheapest, also supplements Ca)
- Sevelamer (non-calcium binder - better in dialysis patients)
- Lanthanum carbonate
ELECTROLYTE QUICK REFERENCE TABLE
| Electrolyte | Normal | Low (Hypo) | High (Hyper) |
|---|---|---|---|
| Na+ | 136-145 mEq/L | <135: SIADH, heart failure, cirrhosis | >145: Dehydration, DI, fever |
| K+ | 3.5-5.0 mEq/L | <3.5: Diuretics, vomiting, diarrhea | >5.5: AKI, ACEi, acidosis |
| Ca2+ | 8.5-10.3 mg/dL | <8.5: Hypoparathyroid, Vit D deficiency | >10.3: Hyperparathyroid, malignancy |
| Mg2+ | 1.7-2.2 mg/dL | <1.7: Diuretics, alcohol, diarrhea | >2.2: Renal failure, excess Mg |
| PO4 | 2.5-4.5 mg/dL | <2.5: Refeeding, DKA treatment | >4.5: CKD, hypoparathyroid |
ECG SUMMARY - ELECTROLYTES AT A GLANCE
| Finding on ECG | Electrolyte | |
|---|---|---|
| Peaked T waves | High K+ | ↑K+ |
| Flattened T waves + U waves | Low K+ | ↓K+ |
| Short QT interval | High Ca2+ | ↑Ca2+ |
| Long QT interval | Low Ca2+, Low Mg2+ | ↓Ca2+ / ↓Mg2+ |
| Torsades de Pointes (polymorphic VT) | Low Mg2+, Low K+, Low Ca2+ | Emergency! |
| Wide QRS + sine wave | Severe high K+ | ↑↑K+ (cardiac emergency) |
ELECTROLYTE CORRECTION - THE CARDINAL RULES
RULE 1: SODIUM
→ Never correct Na+ faster than 8-10 mEq/L per 24 hours
→ Too fast = osmotic demyelination → permanent brain damage

RULE 2: POTASSIUM
→ NEVER push KCl IV (causes cardiac arrest)
→ Max peripheral IV rate: 10-20 mEq/hour
→ Always give Calcium gluconate FIRST if ECG changes present
→ Check Mg2+ if K+ won't correct

RULE 3: CALCIUM
→ Always correct for albumin before deciding it's abnormal
→ IV calcium gluconate (not calcium chloride) via peripheral - safer
→ Monitor for QT changes on ECG

RULE 4: MAGNESIUM
→ Check Mg2+ in any patient with unexplained hypokalemia or hypocalcemia
→ Torsades de Pointes = give MgSO4 2g IV immediately
→ Check patellar reflex before each dose in eclampsia treatment

RULE 5: PHOSPHATE
→ Refeeding syndrome - think of it in any malnourished patient getting nutrition
→ Replace K+, Mg2+, PO4 BEFORE starting feeds in malnourished patients